The boring truth about care coordination
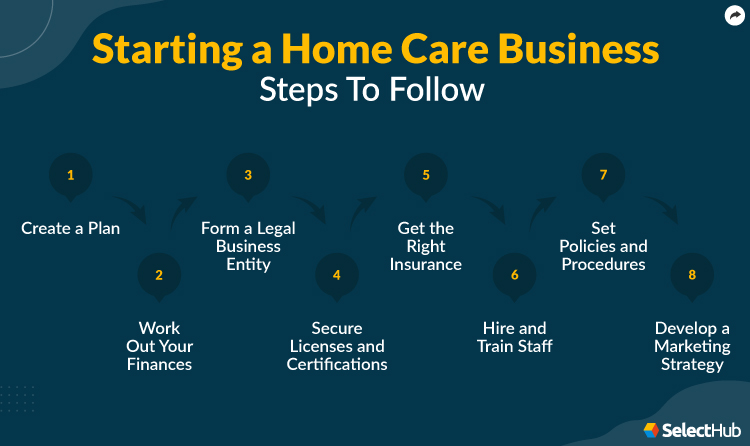
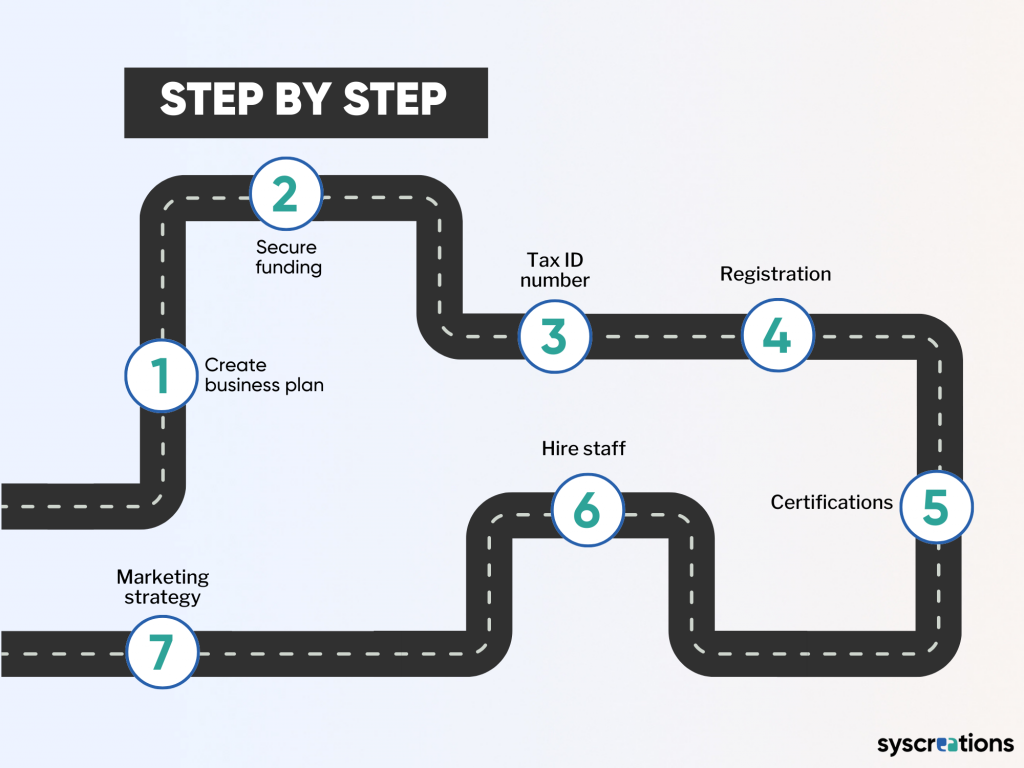
Most people think starting a care coordinator business means getting certified and finding patients. That is not how it works. The actual bottleneck is building referral networks with discharge planners, case managers, and home health agencies who already control access to the patients you need. Without those pipelines, you have a business that exists on paper but generates zero revenue. The first move is figuring out your niche. Care coordination is not a monolith. You might work with aging adults transitioning from hospital to home, pediatric patients with complex needs, mental health clients needing wraparound services, or post-surgical patients requiring follow-up. Each segment has different payers, different regulations, and different referral sources. Pick one and stick with it until you have enough repeat business to expand. I tried handling both geriatric and pediatric cases in year one. It fragmented my focus, diluted my referral base, and cost me about four months of runway. Picking a single lane is not inspirational advice. It is the only way to stay solvent. Next, determine your legal structure. Most care coordinators operate as LLCs because they offer liability protection without the corporate overhead. Get an EIN, open a business bank account, and look into professional liability insurance. Malpractice insurance for care coordinators runs roughly $400 to $1,200 annually depending on your state and caseload volume. Do not skip it. A single complaint about missed medication reminders or a failed handoff can generate a lawsuit regardless of whether you are technically providing medical care.
Licensing requirements vary by state and by what you call yourself. Some states require a care manager certification from NAELA or CCM credentials from the Commission for Case Manager Certification. Others have no formal requirement at all. What matters more is whether you plan to bill insurance or operate on a private pay model. If you intend to bill Medicare or Medicaid, you are looking at significant enrollment paperwork through NPPES and potentially CAQH profile verification that takes three to six months to complete. I learned this the hard way when I signed a contract with a managed care organization before my credentialing was active. They held payment for ninety days while I retrofitted my enrollment status. That delay almost broke the business. The technology stack is where most beginners waste money. You do not need an expensive EHR system on day one. Start with a secure client management platform that handles scheduling, notes, and secure messaging. Tools like MyCareCompass, Coordination, or even a well-configured Google Workspace with HIPAA-compliant add-ons can handle early-stage operations. Spend less than $100 monthly until your client count justifies a dedicated platform. Once you cross twenty-five active cases, upgrade to something with interoperability capabilities so you can exchange data with providers without fax machines and phone tag. The transition from manual to automated documentation usually cuts session prep time from about forty-five minutes per case to roughly fifteen minutes, assuming you build templates and smart phrases early. Building referral pipelines requires a different strategy than marketing to end consumers. Discharge planners and case managers are overworked and skeptical of new vendors. They do not care about your website. They care about whether you will actually return their calls, close the communication loop, and not create additional work for them. I spent the first three months cold-calling hospital social work departments. It was mostly rejected. Then I switched tactics and started attending local Area Agency on Aging board meetings and home health agency in-services. Those face-to-face relationships generated more referrals in six weeks than six months of cold calling. Bring coffee. Take notes. Ask about their pain points. Do not pitch your services until they ask what you do.
Pricing is another area where people consistently undervalue themselves. Care coordination is commonly billed under CPT codes 96170 through 96172 for care management, or you can structure private pay packages that range from $150 to $400 per month for standard coordination and $500 to $1,200 for intensive cases involving multiple providers and frequent crisis response. Insurance reimbursement rates for care management codes vary widely by payer. Medicare Part B reimburses care management at roughly $30 to $70 per encounter depending on the specific code and whether you bill individually or through a group practice. Private pay clients often prefer flat monthly rates because they provide predictability. I recommend offering both options once you have the infrastructure to support insurance billing. There are legitimate downsides to this model that most guides do not mention. Cash flow is lumpy. Referrals come in bursts and then dry up. Insurance reimbursement cycles run thirty to sixty days, which means you might bill in January and not see the money until March. You need at least four months of operating expenses saved before you quit your day job. The emotional labor is also heavier than most people anticipate. You are managing family conflict, advocating against insurance denials, and dealing with patients who are scared or resistant. Burnout is real and it usually hits around month eight when the novelty wears off and the administrative load accumulates without a proportional increase in client volume. One counter-intuitive thing I wish I had known earlier: your strongest asset is not your credentials. It is your responsiveness. A discharge planner who sends a referral at 4 PM on a Friday and gets a confirmation by 8 PM will send every future referral your way. That same planner will blacklist you permanently if you go silent for two days. I once lost a referral source worth approximately $2,000 monthly because I took a long weekend without setting up an out-of-office protocol and a backup contact. That single mistake cost me more than a year of careful networking had built. Automate your acknowledgments. Set clear response-time expectations with every referral source you meet. Never violate your own SLA.
Get the Full Details

Practical next steps if you are serious about this
Research your state requirements first. Spend one week on that alone before you spend a single dollar. Look up whether your state regulates care management titles and what certifications are recognized by major regional payers. Read the credentialing manuals from the two or three insurance companies whose networks you want to access. Then pick your niche, build a minimal operational setup, and start showing up where referral sources actually are. Not where you wish they were. Where they already are.