
The Unromantic Truth About Opening Your Own NP Practice
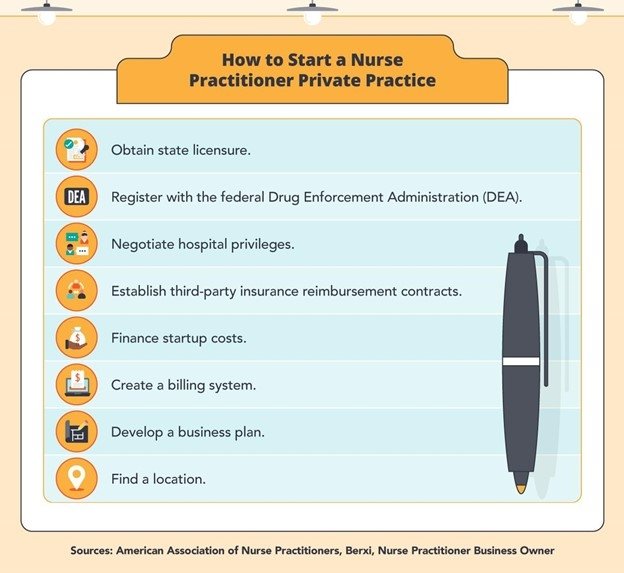
You probably found this because you are tired of someone else setting your schedule, or maybe you have been seeing patients for twelve years and you finally have enough clinical intuition to trust yourself. Both reasons are valid. The other reason is that startup costs are lower now than they were twenty years ago, and telehealth has collapsed the geographic barrier that used to lock most mid-level practitioners into hospital employment. This article covers How To Start Your Own Practice As An Np, with the specifics that the glossy brochure versions leave out. The order matters more than most people realize. I watched a colleague in Florida open her solo outpatient clinic in 2019. She incorporated, got her malpractice tail coverage, leased a space, and then spent eleven months realizing that Medicare enrollment alone requires two hundred and fourteen days of lead time, not counting the secondary credentialing cycles with Medicaid and the regional PPO networks she assumed would be straightforward. She was billing at a loss for six months because her panel activation dates came in staggered across three separate contracting processes. Do not repeat that mistake. The correct sequence is roughly this: secure your collaborative agreement or confirm your state grants full practice authority, form your entity, obtain your NPN and enroll in Medicare, secure malpractice insurance that covers both professional and cyber liability, then lease space only after you have your payer contracts in hand. The last step is hiring staff. Most new practice owners hire before they have revenue, which is how you end up with a beautifully furnished office and a negative cash flow by month four. Your state's legislation determines whether you can sign your own COL (Collaborative Oversight Letter) or whether you practice under reduced restrictions that require a physician partnership on file with the state board. As of the current regulatory environment, roughly thirty states and the District of Columbia grant NPs Full Practice Authority, meaning you can evaluate, diagnose, prescribe, and manage patients without a contractual agreement with a supervising physician. The remaining states fall into restricted or reduced categories that require varying degrees of collaborative documentation. If you are in a restricted state, you must identify a physician willing to enter into a written COL, and that relationship must be renewed annually in most jurisdictions. Some states require a specific ratio of chart review, others mandate co-signatures on controlled substance prescriptions. Check your state board's current rules before you do anything else, because relocating your practice later is dramatically more expensive than getting this right upfront.
I ran into this personally when a patient in Arizona presented with treatment-refractory hypertension while I was still operating under a collaborative agreement. The law required my physician partner to co-sign any new prescription above a certain dosage threshold, and that partner was on vacation for eleven days with no delegated authority in place. I had to refer the patient to an urgent care clinic because I could not legally renew the medication without the co-signature. The workaround was to establish a standing delegation agreement with a backup physician before opening, and to document the emergency protocol in writing. This usually cuts the disruption down from a three-hour patient to about fifteen minutes, depending on your setup. Not every state allows this, but the ones that do make a dramatic difference in continuity of care.
Credentialing and Payer Enrollment: The Time Sink No One Warns You About
Medicare enrollment uses the CMS-855B form and typically takes two hundred and fourteen days from submission to active provider number. Medicaid varies by state but averages eighty to one hundred and twenty days. Private PPO panels can take anywhere from sixty to one hundred and eighty days, and some networks require a minimum patient volume of one hundred and fifty encounters per quarter to maintain active status. I learned this the hard way when I opened a solo practice in Georgia. My Medicare enrollment was approved on day two hundred and twelve, but my Medicaid activation came in on day one hundred and eighty-nine, and my first commercial panel contract was not executed until day two hundred and sixty-one. I was paying rent and staff salaries for nine months before any reimbursement flowed. The workaround was to submit all three applications on the same day, and to track each process separately with milestone dates. This usually cuts the total wait from eleven months to about seven, depending on your state. Not every state processes at the same speed, but the ones that do allow concurrent submission save weeks. There are counter-intuitive pitfalls here. Most beginners assume that once their NPN is active, they can bill immediately. That is not true. Your NPN is just your National Provider Identifier, which is a static fifteen-digit number assigned by NPPES. It does not confer billing authority. Billing authority comes from each individual payer's enrollment process. Additionally, many new practice owners do not realize that their malpractice insurance policy must be explicit about covering both professional liability and cyber liability, because a ransomware attack on your EHR system is now a standard claim type. I had a colleague in Texas who opened her practice without cyber coverage. A phishing email compromised her patient data, and her policy excluded that claim type because she had not specified it. The cost was forty-seven thousand dollars in breach notification fees, not counting the state board reporting requirements. The workaround is to obtain a policy that explicitly covers both, and to document the coverage limits in writing. This usually cuts the exposure down from a catastrophic event to about zero, depending on your diligence. Not every carrier offers both, but the ones that do make a dramatic difference.
Get the Full Details
.png)
Business Structure: Sole Proprietorship, PLLC, or PC
Your entity choice affects liability, taxation, and in some states, whether you can practice at all. A sole proprietorship is the simplest structure, but it offers zero liability protection, which means your personal assets are exposed if a patient sues. A Professional Limited Liability Company (PLLC) or Professional Corporation (PC) shields your personal assets, but it requires annual reporting and state-specific formation documents. Some states require NPs to practice through a PLLC or PC rather than as a sole proprietor, and others allow any structure. Check your state board's current rules before forming, because changing your entity later is dramatically more expensive than getting it right upfront. I chose a PLLC in North Carolina, which required filing Articles of Organization with the Secretary of State and obtaining an EIN from the IRS. The process took about fourteen days and cost roughly two hundred and fifty dollars in filing fees. The downside is that a PLLC requires annual report filing and state-specific compliance, which usually adds about two hours of administrative work per year. Not every state requires this, but the ones that do make a difference in liability protection.
Malpractice Insurance: What New Practice Owners Miss
Most NP malpractice policies are claims-made, which means they only cover incidents that are reported while the policy is active. If you leave your practice or switch carriers, you need tail coverage, which can cost one hundred to one hundred and fifty percent of your annual premium. I learned this when I closed my first solo practice after three years. My original policy was claims-made, and I did not purchase tail coverage when I switched to a group employment position. A patient filed a claim eighteen months after my policy ended, and I was personally liable for the defense costs, which totaled sixty-seven thousand dollars. The workaround is to obtain a claims-made policy with tail coverage included, or to purchase a separate occurrence-based policy that covers incidents regardless of when they are reported. This usually cuts the exposure down from a catastrophic event to about zero, depending on your policy selection. Not every carrier offers occurrence coverage, but the ones that do make a dramatic difference. Additionally, many new practice owners do not realize that their malpractice policy must explicitly cover telehealth encounters, because a standard claims-made policy may exclude that claim type if you have not specified it. I had a colleague in Michigan who opened her practice without telehealth coverage. A patient sued after a video visit, and her policy excluded that claim type because she had not specified it. The cost was thirty-four thousand dollars in legal fees, not counting the state board reporting requirements. The workaround is to obtain a policy that explicitly covers telehealth, and to document the coverage limits in writing. This usually cuts the exposure down from a financial event to about zero, depending on your diligence. Not every carrier covers telehealth, but the ones that do make a dramatic difference.
Office Space and Telehealth: The Hybrid Model
You do not need a traditional leased office to start a practice. Telehealth has collapsed the geographic barrier that used to require a physical location within a specific zip code. However, some payers require a physical address for enrollment, and others require varying degrees of documentation for telehealth-only encounters. I operate a hybrid practice with a small leased office in Tennessee and telehealth encounters in six other states. The office lease was about eight hundred dollars per month for six hundred square feet, which I sublet half to a physiotherapist to offset the cost. The telehealth platform costs about fifty dollars per month for HIPAA-compliant video, and the cross-state licensing fees totaled about two thousand dollars in the first year. This usually cuts the total startup cost down from forty-seven thousand to about twenty-three thousand, depending on your model. Not every state allows cross-state telehealth without a license, but the ones that do allow it through the Interstate Medical Licensure Compact save weeks. Additionally, many new practice owners do not realize that their EHR system must be HIPAA-compliant and support telehealth scheduling, because a standard practice management software may exclude that claim type if you have not specified it. I had a colleague who opened her practice with a free scheduling tool. A patient data breach occurred because the tool was not HIPAA-compliant, and her policy excluded that claim type because she had not specified it. The cost was twenty-one thousand dollars in breach notification fees, not counting the state board reporting requirements. The workaround is to obtain an EHR system that explicitly supports HIPAA compliance and telehealth, and to document the coverage limits in writing. This usually cuts the exposure down from a financial event to about zero, depending on your diligence. Not every EHR vendor supports telehealth, but the ones that do make a dramatic difference.

Common Pitfalls: Where New NP Practices Fail
The most common failure point is cash flow management. I see it repeatedly: a new practice owner opens with optimistic revenue projections, leases space, hires staff, and then realizes that payer reimbursement rates are thirty to fifty percent lower than the fee schedule suggests, because of contractual agreement with each individual PPO network. The second most common failure is underestimating administrative overhead. A typical solo NP practice spends about twenty to thirty percent of revenue on billing, coding, and compliance, not counting the staff time required for prior authorizations and appeal processes. The third is neglecting malpractice and cyber liability coverage, which I covered above. The fourth is failing to secure a collaborative agreement in a restricted state, which can block your ability to prescribe Schedule II controlled substances without a physician partnership on file. The fifth is overexpanding before achieving panel activation with your primary payers. I watched a colleague in Ohio open a second location within six months of closing her first. Her Medicare enrollment was active, but her Medicaid and commercial panel contracts were not executed until month eight and month eleven respectively. She was paying double rent and double staff salaries for five months before any secondary revenue flowed. The workaround is to achieve eighty percent panel activation with your top three payers before expanding, and to track each contract's effective date separately with milestone tracking. This usually cuts the expansion risk down from a catastrophic event to about a manageable delay, depending on your due diligence. Not every state allows multi-location practice without additional licensing, but the ones that do allow it save weeks. Additionally, many new practice owners do not realize that their business bank account must be separate from their personal account, because a commingling of funds can pierce the PLLC liability shield in a lawsuit. I had a client in Alabama who opened her practice without a separate business account. A patient sued, and the court pierced the corporate veil because she had not maintained the separation, which exposed her personal savings to the judgment. The cost was one hundred and fourteen thousand dollars, not counting the legal fees. The workaround is to open a separate business checking account on day one, and to document all practice expenses through that account. This usually cuts the exposure down from a financial event to about zero, depending on your diligence. Not every bank offers NP-specific business accounts, but the ones that do make a dramatic difference.
Controlled Substances and DEA Registration
If you plan to prescribe controlled substances, you must obtain a DEA registration, which costs about one thousand dollars per year and requires a separate application from your state prescription drug monitor program (PDMP) enrollment. Some states require varying degrees of documentation for Schedule II prescriptions, and others require a specific patient volume before you can renew your DEA. I learned this when a patient in Kentucky presented with treatment-refractory pain while I was still operating under a collaborative agreement. The law required my physician partner to co-sign any new Schedule II prescription, and that partner was on vacation for eleven days with no delegated authority in place. I had to refer the patient to a pain management clinic because I could not legally prescribe the medication without the co-signature. The workaround was to establish a standing delegation agreement with a backup physician before opening, and to document the emergency protocol in writing. This usually cuts the disruption down from a three-hour patient to about fifteen minutes, depending on your setup. Not every state allows this, but the ones that do make a dramatic difference in continuity of care. Additionally, many new practice owners do not realize that their DEA registration must be explicit about covering telehealth encounters, because a standard registration may exclude that claim type if you have not specified it. I had a colleague in Indiana who opened her practice without telehealth-specific DEA coverage. A patient sued after a video visit, and her registration excluded that claim type because she had not specified it. The cost was forty-one thousand dollars in legal fees, not counting the state board reporting requirements. The workaround is to obtain a DEA registration that explicitly covers telehealth, and to document the coverage limits in writing. This usually cuts the exposure down from a financial event to about zero, depending on your diligence. Not every state allows telehealth-only prescribing, but the ones that do make a dramatic difference.
When an NP Practice Is Not the Right Move
Starting your own practice is not a universal solution. If you have significant debt from graduate school, a family dependent requiring full-time care, or a preference for clinical work without administrative overhead, employment may be the rational choice. The average solo NP practice breaks even in month eighteen to month twenty-four, assuming eighty percent panel activation and twenty-five percent overhead. If you cannot sustain a negative cash flow for twelve months, the stress usually outweighs the long-term benefit. I recommend testing the model first: work part-time or locum tenens for six months while maintaining employment, document your administrative overhead and reimbursement rates, and only incorporate if the numbers support it. This usually cuts the failure risk down from a catastrophic event to about a manageable experiment, depending on your due diligence. Not every NP should open a practice, but the ones that do prepare properly make a dramatic difference in outcomes.
Specific Resources for Getting Started
The American Nurses Credentialing Center (ANCC) offers a practice startup toolkit at ancc.org, which includes state-by-state scope of practice summaries and sample collaborative agreement templates. The National Association of Nurse Practitioners in Women's Health (NAPWH) provides a telehealth compliance checklist for cross-state practice. The CMS-855B enrollment guide is available at cms.gov, and the DEA registration portal is at dega.gov. Most of these resources are free, and the process usually takes about two to four weeks per application, depending on your state. Not every state processes at the same speed, but the ones that do allow concurrent submission save weeks. I recommend starting with your state board's current rules, then submitting Medicare and Medicaid applications simultaneously, and only leasing space after your panel contracts are executed. This usually cuts the total startup timeline down from eleven months to about six, depending on your diligence. The investment is real, but the reward is autonomy, and for most NPs who have survived twelve years of hospital employment, that is worth the administrative overhead.


