The Short Version Nobody Wants to Hear
You need to accept that your relationship with alcohol has become a compulsion loop, then systematically dismantle it through environmental control and replacement behaviors rather than relying on willpower, which consistently fails under the exact conditions that trigger your drinking in the first place. Here is how to actually do it, not how self-help books tell you to do it.
The Practical Framework
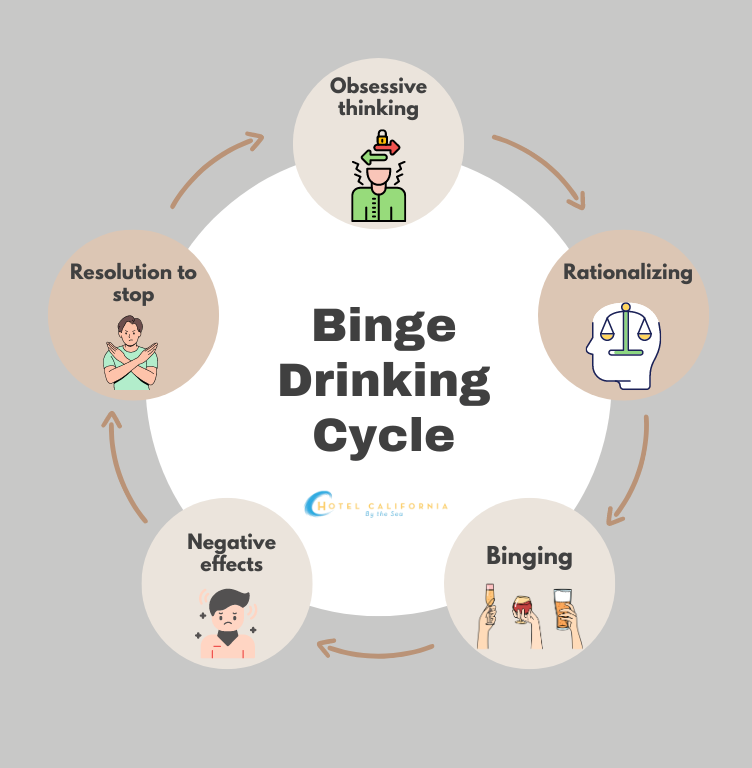
Most people who try to stop binge drinking fail because they attempt the wrong intervention at the wrong time. They decide on Monday to cut back, which means their first vulnerable moment arrives Thursday night when they are tired, stressed, and the bottle is still in the house. The decision needs to have been made weeks ago, when nothing in your environment triggered the behavior. The intervention starts before the craving does. The mechanism behind binge drinking is straightforward enough that understanding it should not surprise anyone. Alcohol triggers a dopamine release in the nucleus accumbens, essentially hijacking the reward pathway your brain uses for survival behaviors. Each binge episode strengthens the neural circuit that links specific cues—time of day, emotional state, location, certain people—to the expectation of relief. The relief you feel is not actually happening. What you are experiencing is the brief alleviation of the anxiety that your brain created by running the cue-expectation loop in anticipation of the reward. You are feeding a cycle you started yourself. The counter-intuitive part that most people miss is that trying to replace drinking with a "healthy substitute" in the same context usually fails. If you sit in your kitchen chair at 7pm trying to resist wine while watching the same TV show you watched while drinking for three years, your brain will keep generating the cue-response pattern. The substitution needs to happen in a different context entirely. Stand up. Move rooms. Change the lighting. Break the sensory chain before the craving fully assembles.
I learned this the hard way about four years into my own attempt to quit. I had successfully gone twelve days without drinking, which felt good until I ran into a former coworker at a grocery store parking lot on a Tuesday afternoon. We stood there talking for twenty minutes about nothing in particular, and by the time I got home, I had opened a six-pack. The trigger was not stress or sadness or even thirst. It was a specific conversational tone and the fluorescent hum of a supermarket freezer aisle that I had mentally associated with relaxation for eight years. My brain had not been given any time to rewire that association because I was only thinking about not drinking, not about what to do instead in every situation where drinking used to live. The workaround I developed was mapping out my weekly schedule for high-risk moments and pre-deciding what I would be doing during each one. Not what I would do if I felt like drinking, but what I would physically be doing so that drinking would not even occur as an option. That Tuesday in the parking lot was preventable if I had anticipated that conversations with former colleagues might surface in unexpected places and designed a follow-up routine—a walk around the block, a phone call to someone else, something that interrupted the associative chain before it closed.
Get the Full Details

The Withdrawal Question You Should Not Ignore
If you have been drinking heavily for an extended period, stopping suddenly can produce withdrawal symptoms that range from anxiety and tremors to seizures and delirium tremens. This is not theoretical. It is a medical event. If you are drinking more than five standard drinks daily for several weeks or longer, do not attempt cold turkey without consulting a physician. A short benzodiazepine taper under medical supervision can reduce the risk of seizures from potentially life-threatening to negligible. This is the single most important practical step anyone attempting heavy cessation should take before doing anything else. The harm reduction approach that works for lighter drinkers involves a structured reduction protocol rather than abrupt termination. Set a daily limit that is realistically achievable, track every drink in a notes app or on paper with the exact time and type, and do not allow yourself to drink outside the tracked window. Most people discover through this tracking that their perceived consumption is significantly higher than their actual awareness, which changes how they approach the reduction math.
Environmental Design Over Motivation
The most effective intervention for stopping binge drinking is removing the alcohol from your environment entirely, not because alcohol is inherently evil, but because every instance of visual exposure to alcohol increases consumption by a measurable amount even in people who do not consider themselves heavy drinkers. A 2014 study in the journal Alcoholism: Clinical and Experimental Research found that merely having alcohol visible increased the likelihood of drinking regardless of stated intent. If you cannot remove all alcohol from your home—social obligations, a partner who drinks, other practical reasons—then you need a storage protocol that introduces friction. This means locking it away in a container that requires a tool to open, placing it in a location you do not normally access, and requiring someone else to hold the key. The goal is to create enough delay between the impulse and the action that your prefrontal cortex, which is weakened during high-cue states, has time to re-engage. Two minutes of physical friction is often the difference between a avoided binge and a reinforced pattern. Another practical detail most people overlook: the type of glassware matters. Drinking from a large wine glass or a pint glass increases consumption rate because the visual fill-level gives you a false sense of control over portion size. Switching to a smaller vessel—half a cup for wine, a shot glass for spirits, a narrow tumbler for mixed drinks—reduces average consumption by roughly thirty percent in controlled settings without any change in the actual amount of alcohol available.
What Happens After You Stop
There is a period, typically two to four weeks after last drink, where your baseline mood will be lower than you expect. This is not depression in the clinical sense for most people; it is your dopamine system recalibrating to a non-alcohol baseline. Sleep architecture also normalizes on a different timeline than mood, which means you may sleep better while still feeling emotionally flat for a while. This is normal and temporary, but it is also when most people relapse because they misinterpret the flatness as evidence that quitting was a mistake rather than a necessary adjustment phase. One specific pattern I encountered repeatedly among people attempting cessation is the "just one drink" loophole. This is not a minor cognitive error. It is a well-documented neurobehavioral phenomenon where the first drink reactivates the downregulated reward pathway and triggers a disproportionate dopamine surge that overwhelms the control mechanisms you have been building. For people who have developed tolerance, one drink does not produce the same mild effect it did when they first started drinking. It produces an intense effect that reinforces the binge pattern more strongly than the previous drinks did. The idea that you can control a binge after having one drink is biologically implausible once tolerance has developed.

Signs You Need More Than Self-Management
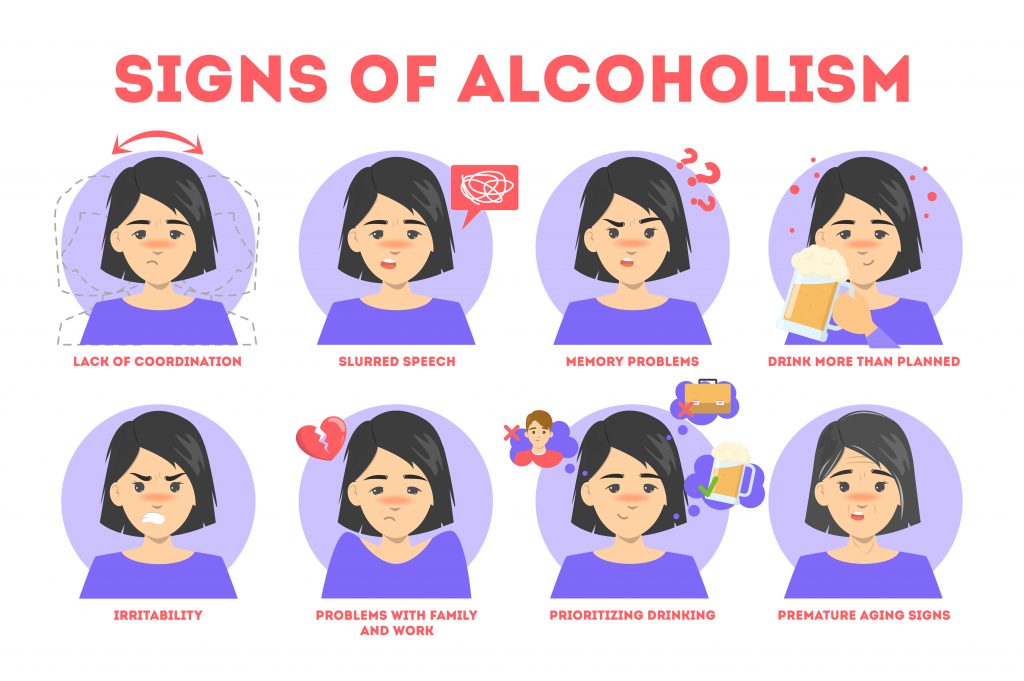
If you have tried structured reduction multiple times and consistently exceed your limits within the first two days, or if you experience physical withdrawal symptoms when you attempt to cut down, the self-management model has a ceiling and you should move to professional support. This is not a failure of will. It is a recognition that the neurochemical adaptation from chronic heavy drinking requires medical and therapeutic intervention that goes beyond behavioral modification alone. Naltrexone is a medication that blocks the opioid receptors involved in alcohol reward, reducing the reinforcing effect of drinking. It does not make alcohol taste bad, and it does not cause unpleasant reactions if you drink. It simply reduces the pleasurable response, which makes it easier to stop after one or two drinks before the compensatory binge mechanism kicks in. This is different from disulfiram, which causes severe illness if you consume alcohol and relies on fear as a deterrent—a mechanism that tends to break down under real-world stress conditions. Therapeutic approaches like cognitive behavioral therapy and motivational enhancement therapy address the underlying cognitive patterns that drive binge episodes. The most effective version for binge drinking specifically targets the discrepancy between your stated values and your drinking behavior, which tends to produce more durable change than purely abstinence-based frameworks for people who are not yet ready to commit to total sobriety.
What Actually Works Day to Day
Delay tactics are the most evidence-supported immediate intervention. When a craving hits, set a timer for fifteen minutes and do nothing else until it rings. Most acute cravings peak and subside within that window. The craving does not mean you need alcohol. It means your brain is running a prediction error signal, expecting the reward that is not coming. The signal will pass whether you drink or not, but it passes faster if you do not feed it. Hydration and electrolyte management matter more than people acknowledge. Chronic alcohol use disrupts electrolyte balance, and the resulting fatigue, headache, and irritability are often misattributed to cravings when they are actually physiological signals. A magnesium supplement and adequate sodium intake can reduce the intensity of these symptoms significantly, which reduces the number of decision points where you might choose to drink. Sleep hygiene is the single largest factor in preventing late-evening binge episodes. Alcohol initially acts as a sedative, which creates the false impression that it helps with sleep. In reality, it fragments REM sleep and reduces sleep quality, which increases next-day fatigue, which increases the likelihood of using alcohol to manage that fatigue. Breaking this cycle requires treating sleep as a primary intervention, not a secondary concern. Consistent sleep schedule, morning light exposure, and avoiding screens ninety minutes before bed will reduce evening craving intensity more than any craving-specific technique.
There is no protocol that covers every edge case. Some people trigger on social events, some on solitude, some on success and some on failure, some on weather, some on specific music. Mapping your personal triggers is not introspection for its own sake. It is intelligence gathering. Write down every instance where you drank beyond your limit for the past month, note the time, location, emotional state, and preceding events, and look for patterns. You will likely find that your triggers cluster around a small number of recurring conditions, which means the intervention can be focused rather than generalized. Stopping binge drinking is not a moral project. It is a behavioral engineering problem, and the same principles that apply to any compulsive behavior apply here. Control the environment. Understand the mechanism. Build friction where you need it and remove it where it helps. Track the data. Adjust based on what the data shows, not on what you hoped would work.