Getting It Right Without Fancy Equipment
I spent about six years working in a busy urgent care clinic where the automatic machines were constantly getting stuck, batteries died, or just gave readings that made no sense. Manual sphygmomanometers were the fallback, and honestly, they ended up being more reliable than the digital units half the time. But they require you to actually pay attention. You can't just press a button and walk away. The core principle is straightforward, even if the execution takes practice. You place an inflatable cuff on the upper arm, squeeze the bulb to cut off arterial flow, then slowly let the pressure down while listening with a stethoscope. The moment you hear the first tapping sound is your systolic reading. When the sounds disappear entirely, that's your diastolic. Between those two points sits the difference, called pulse pressure.
Learning How To Take A Manual Blood Pressure Correctly
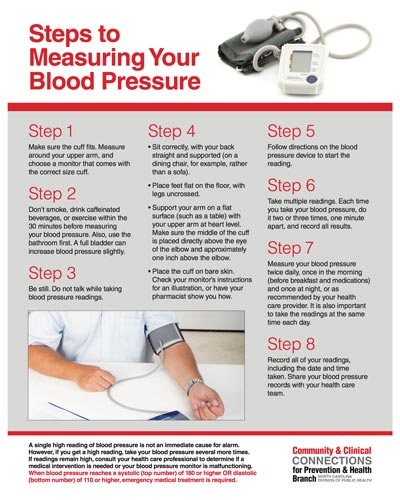
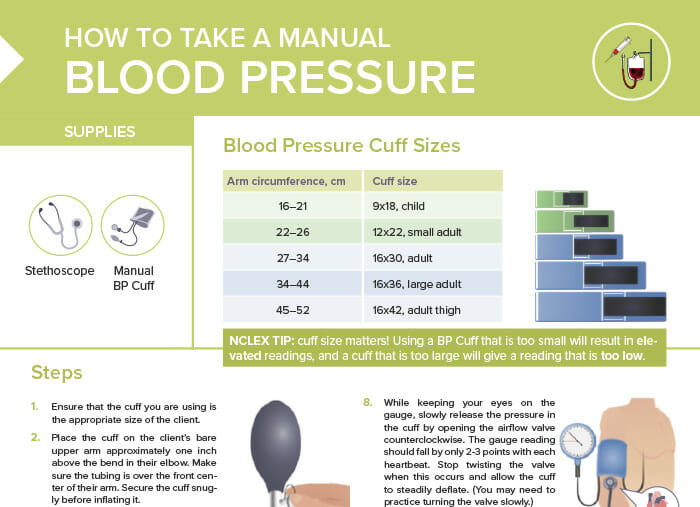
Start by sitting the person down for at least five minutes before you begin. Feet flat on the floor, back supported, arm resting on a surface at heart level. This matters more than most people realize. If the arm is hanging down, the reading can be off by ten to fifteen millimeters of mercury just from hydrostatic pressure. I've seen technicians miss hypertension entirely because the patient's arm was dangling at their side during measurement. Choose the right cuff size. This is where most people go wrong. The bladder inside the cuff needs to wrap around at least eighty percent of the arm circumference. A standard adult cuff on a large arm will give you a falsely low reading. A small adult cuff on a thin arm will give you a falsely high one. Measure the arm midway between the shoulder and the elbow crease before you pick a cuff. I had a patient whose blood pressure read normal on repeated checks until I realized we were using a standard cuff on a sixty-five centimeter arm. Switching to an large adult cuff immediately added thirty-five over twenty to the reading. The patient was hypertensive the whole time. Find the brachial artery. Place the cuff so the bottom edge is about two centimeters above the antecubital fossa, the crease in the elbow. You should be able to palpate the pulse in that area through the cuff material. Mark it with your finger if you need to. Position the stethoscope bell or diaphragm directly over that point, not under the cuff edge. Pressure from the cuff on the stethoscope tubing creates artifact noise that sounds nothing like Korotkoff sounds and can throw you off completely.
inflate the cuff to about one hundred eighty millimeters of mercury, or thirty to forty above where you expect the systolic to be. You should be able to palpate the radial pulse and feel it disappear at some point during inflation. Note that pressure. This is your palpatory systolic estimate. It will often be lower than the auscultatory systolic by ten to twenty millimeters in people with narrowed arteries. Knowing this upfront prevents you from deflating too quickly and missing the first sound entirely. Now open the valve on the bulb slightly. The key is controlled deflation. Aim for two to three millimeters of mercury per second. Faster than that and you'll miss the transition points. Slower than that and you'll cause venous congestion in the arm, which can make the diastolic sound seem to return before it actually should. I usually count aloud while watching the gauge to keep my pace steady. Two-one, two-two, two-three and so on. List for the first clear tap. That's your systolic. Keep listening as the numbers drop. The sounds will change character through the phases. Phase one is the first appearance of clear tapping sounds. Phase two is when they become softer and longer. Phase three brings back a sharper quality. Phase four is a muffled, blurring sound. Phase five is complete silence. The systolic is phase one. The diastolic is phase five in adults. In children, pregnant women, or people with hyperdynamic circulation, phase four can be the correct diastolic point because the sounds may not fully disappear.
Get the Full Details

Record both numbers. Round to the nearest even number since most gauges don't have half-markings. Note which arm you used and whether the person was seated or supine. These details matter for tracking changes over time. There are edge cases that will trip you up. Atrial fibrillation makes the Korotkoff sounds irregular, sometimes with wide variations between beats. In those situations, take three readings and average them. Don't rely on a single measurement. Calcified arteries, common in elderly patients or those with long-standing diabetes, can create a phenomenon called auscultatory gap. The pulse disappears during inflation, reappears briefly, then disappears again. If you inflate only to your palpatory estimate and start deflating, you might miss the gap and record a systolic that is twenty or thirty points too low. Always inflate well above where you expect the pulse to return. White coat effect is another real issue. People consistently read higher in clinical settings due to anxiety. If you're doing manual measurements, note the context. A reading of one hundred forty over ninety in a clinic might be closer to one twenty-eight over seventy-eight at home. I once spent twenty minutes trying to get a stable reading on a patient who kept flinching every time the cuff inflated. He had severe measurement anxiety. We ended up having him sit in the room alone for ten minutes with the cuff on but deflated, then took the reading while he was distracted. The difference was forty points systolic.
The mercury sphygmomanometer is the gold standard for accuracy, but they are being phased out in many places due to environmental concerns and the risk of mercury exposure if the device breaks. Aneroid gauges are the common alternative. They are portable and don't contain toxic material, but they drift over time. I've seen aneroid gauges off by fifteen to twenty millimeters of mercury after a year of heavy clinic use. You should calibration check them against a mercury reference at least annually. A simple water column test can verify accuracy without sending the device out. Digital automatic devices have improved considerably. For routine screening in most adults, they are perfectly adequate and often more convenient. The problem is that they struggle with irregular heart rhythms, severe hypotension, and certain vascular conditions. When I need clinical-grade accuracy, or when a patient has atrial fibrillation, peripheral vascular disease, or is on vasopressor medications in an ICU setting, manual measurement remains the only reliable option. The most important skill you develop is listening. Your ears need to learn what Korotkoff sounds actually are versus ambient noise, breathing artifacts, or the rub of the stethoscope tube against clothing. Practice on friends and family. Take twenty readings on the same person and compare them. If your variation is more than five millimeters between consecutive readings on the same arm, you are either inflating or deflating inconsistently, or your stethoscope placement is shifting. Fix the technique before you trust the numbers.
One practical detail that nobody mentions: warm your hands and warm the stethoscope head. A cold diaphragm on a cold arm triggers vasoconstriction and can raise the reading by a few points. It sounds trivial but it adds up when you are trying to distinguish between stage one and normal blood pressure. Document the time of day, the patient's position, the arm used, the cuff size, and any relevant observations like recent caffeine intake or pain. A blood pressure number without context is barely useful. I've reviewed charts where the only note was a single reading with no indication of how it was obtained, making it impossible to determine whether a trend was real or an artifact of technique. If you are learning this for personal use at home, consider investing in a validated upper arm digital monitor for routine checks and only reach for manual technique when the digital readings seem inconsistent or your doctor specifically requests it. Manual measurement is a clinical skill that takes meaningful practice to perform reliably. The margin for error is wider than most people expect, and the consequences of a missed hypertensive reading are real.