The Basics Nobody Tells You Upfront
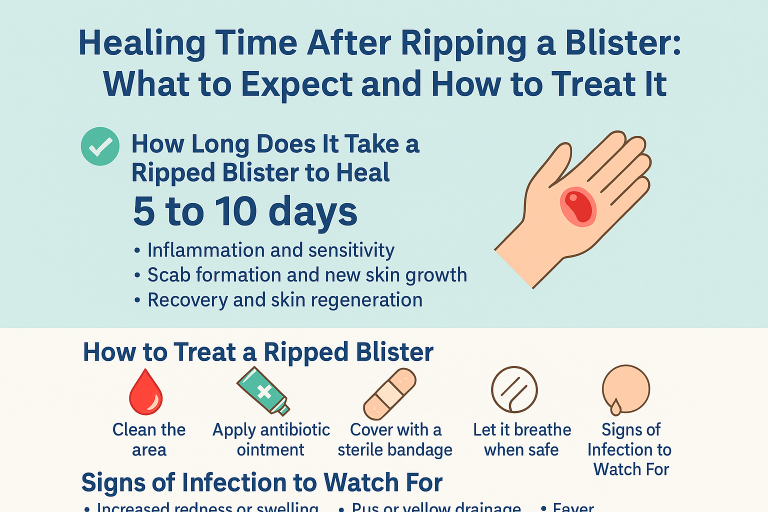
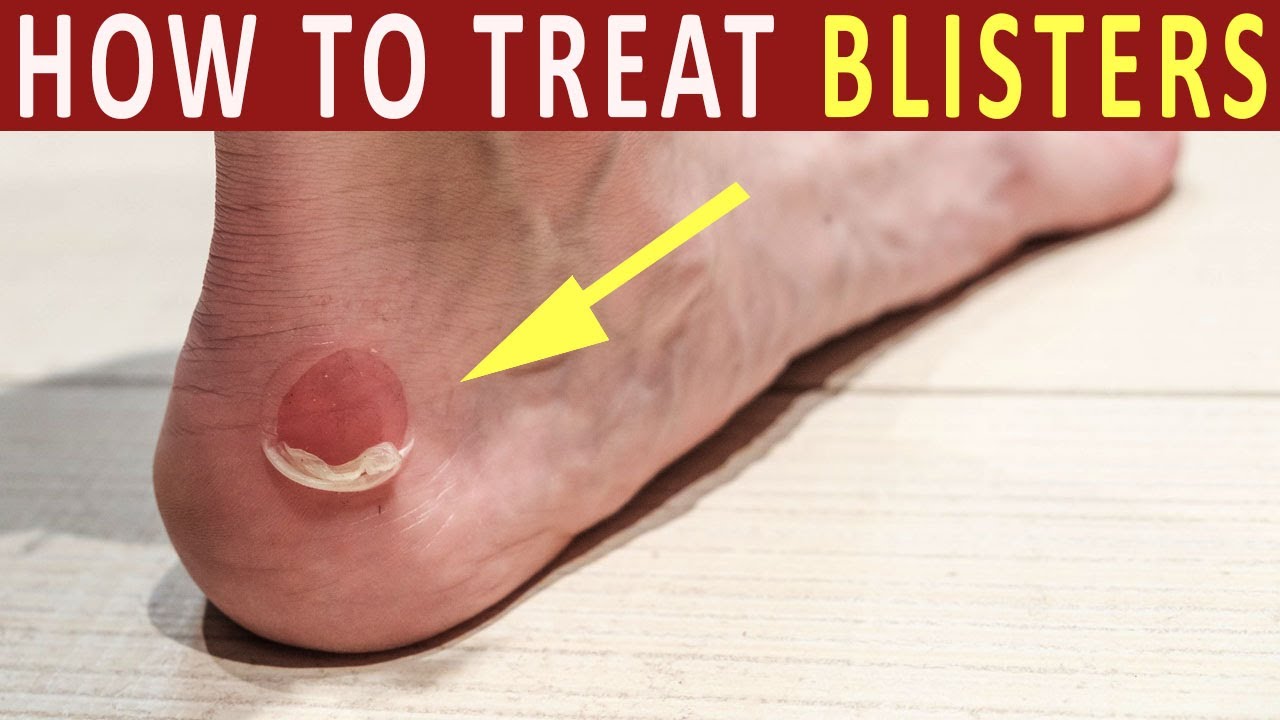
A blister is a pocket of fluid between layers of skin, usually caused by friction, heat, or chemical irritation. Most people encounter them on their feet after long hikes or on their hands from repetitive work. The instinct is to pop it immediately so the pressure goes away, but that is almost always the wrong call. Leaving it intact keeps a sterile barrier over the raw skin underneath. I learned this the hard way back in 2018 when I popped a large blister on my heel during a three-day trail run in the White Mountains. I thought I was being smart by draining it with a sterilized needle and then covering it with a bandage. Instead, the open wound got contaminated from sweat and dirt within six hours. By morning I had a low-grade infection that made walking downhill impossible and ended up requiring a course of oral antibiotics from an urgent care clinic. Took me two weeks to fully recover instead of the four days I would have had if I left it alone. Start by assessing the size and location. If it is small, under a half inch in diameter, and not in a high-friction area, you do not need to do much beyond protecting it with a standard adhesive bandage and moving on with your day. Intact blisters of this size typically heal on their own within three to five days as the body reabsorbs the fluid. For larger blisters or ones that sit on weight-bearing areas like the sole of the foot or the palm of the hand, the approach shifts. Wash your hands first, then clean the blister and surrounding skin with mild soap and warm water. Do not scrub the blister itself. Pat the area dry with a clean paper towel. If the blister is likely to burst from continued friction, cover it with a hydrocolloid dressing such as Compeed or Instil. These dressings adhere to the skin, cushion the area, and create a moist healing environment that speeds recovery significantly compared to a regular gauze pad. I replace hydrocolloid dressings every two to three days or sooner if they start peeling at the edges. The dressing typically stays in place for four to seven days total, and the blister underneath heals faster than it would exposed to air because the new epidermis forms under the cushioned barrier.
If the blister has already ruptured on its own, the care changes slightly. Gently wash the area with soap and water. Do not pull off the overlying skin flap if it is still attached and lying flat. That dead skin acts as a natural biological dressing and protects the raw dermis below. Trim away only the loose, detached edges with small scissors that you have wiped down with rubbing alcohol. Apply an antibiotic ointment like bacitracin to the exposed area, then cover it with a non-stick pad and medical tape. Change the dressing daily or whenever it gets wet or dirty. Watch for signs of infection over the next several days: increasing redness spreading outward from the edges, warmth to the touch, yellow or green pus, red streaks traveling up the limb, or fever above 100.4 degrees Fahrenheit. If any of those appear, seek medical attention rather than continuing home treatment.
When to Drain a Blister Yourself
There is a narrow window where self-draining is reasonable. The blister must be large enough that normal movement is painful or impractical, it should not be on a joint that bends frequently, and it must be free of any signs of infection already present. Use a needle that you have cleaned with isopropyl alcohol. Poke two or three small holes around the edge of the blister, not through the top center. Let the fluid drain by applying gentle pressure from the opposite side. Do not rip or cut away the skin. After drainage, apply antibiotic ointment and cover with a hydrocolloid dressing or a non-stick pad secured with tape. This process takes about five minutes from start to finish and the blister usually closes over within two to four days. The problem with draining is that many people go too aggressive. I once watched a coworker at a warehouse job drain a blister on his index finger by slicing the top off with box cutter blade he found in his locker. He then wrapped it in duct tape. That kind of approach introduces massive contamination risk and delays healing considerably. Stick to the needle method if you must drain anything.
Get the Full Details

Counter-Intuitive Things That Actually Matter
Most people think keeping a blister dry is the priority. That is only partially correct. A completely dry scab actually slows epithelial migration, which is the process where new skin cells move across the wound bed. Hydrocolloid dressings maintain a moist environment that research shows can accelerate healing by up to 40 percent compared to dry healing. The downside is that hydrocolloid dressings cost roughly three to five dollars per unit and you need one that matches the size of your blister, which means carrying a small variety pack if you are prone to them. Another thing people get wrong is how they remove the dressing. Pulling a hydrocolloid pad straight off can tear the fragile new skin forming underneath. The correct method is to soak the edges with warm water or saline until the adhesive loosens, then peel it back slowly in the direction of hair growth if applicable. This usually takes ten to fifteen seconds and prevents reopening the healing wound, which is something I have seen cause setbacks more often than not in practical settings.
Edge Cases Where Standard Advice Fails
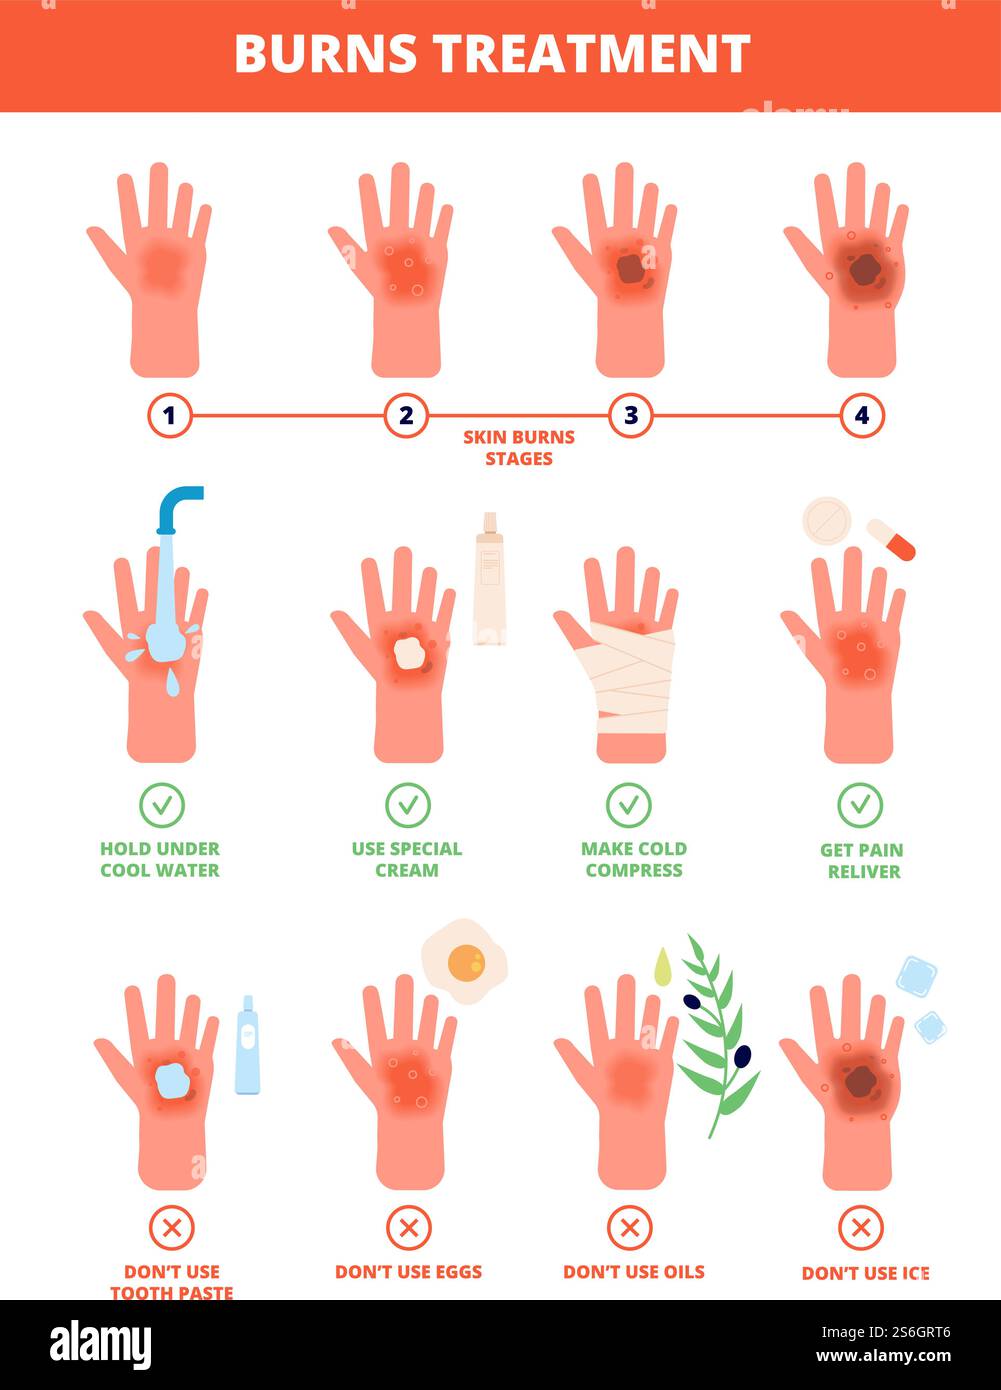
Blood blisters are a different category entirely. These form when trauma damages small blood vessels under the skin, and the pocket fills with blood instead of clear plasma. They are common on the fingers and hands from pinching or impact. The standard advice of draining with a needle does not work well here because blood clots inside the pocket and cannot be expressed through a tiny needle hole. Attempting to drain a blood blister usually just creates a larger open wound without relieving pressure. Leave blood blisters alone. Cover them lightly and let the body reabsorb the blood over one to two weeks. The skin above may turn dark purple or black, which looks alarming but is normal. Then there are friction blisters that form inside the mouth from burning food or biting your cheek repeatedly. Topical antibiotic ointments meant for skin do nothing for oral blisters and can be harmful if swallowed. Salt water rinses using half a teaspoon of salt dissolved in eight ounces of warm water, swished gently for thirty seconds and spit out, are the only practical home treatment for those. They usually resolve on their own within three to five days without any intervention. Blisters from burns require a different protocol entirely. Thermal burns that produce blisters are classified as partial-thickness burns and should be evaluated by a medical professional rather than treated at home. Over-the-counter blister treatments are not designed for burn care and can trap heat in the tissue. Cool the burn under running cool water for ten to twenty minutes immediately after the injury, then cover loosely with a sterile non-stick bandage. Do not apply ice, butter, or any home remedies. Seek medical care the same day for any burn larger than the size of your palm or located on the face, hands, feet, or genitals.
What Not to Do
Do not use hydrogen peroxide or rubbing alcohol directly on an open blister. These solutions damage healthy tissue and delay healing. They are fine for cleaning intact skin around a blister or for sterilizing tools before use, but applying them to the wound itself is counterproductive. Do not pick at the skin around a healing blister even if it starts to peel. The peeling skin is still attached to viable tissue underneath and ripping it off reopens the wound. Do not continue putting friction-inducing activity on an affected area while wearing a bandage and hoping it will be fine. A covered blister that is still being rubbed by a shoe or glove will not heal, no matter how good the dressing is. The friction will either re-rupture it or prevent the underlying layers from sealing. If you are diabetic or have peripheral vascular disease, do not attempt to treat blisters yourself. Poor circulation and nerve damage mean that even minor skin breakdown can escalate into serious complications like ulcers or osteomyelitis. Any blister on a diabetic patient should be evaluated by a healthcare provider, ideally a podiatrist if it is on the foot. This is not a precautionary suggestion. It is a hard boundary based on clinical outcomes.
Prevention Is Still the Only Real Solution
Treating blisters is a cleanup operation. Prevention involves a few specific steps that most people skip until after the damage is done. Break in new footwear gradually over two to three weeks before committing to long walks or runs in them. Wear moisture-wicking socks made of merino wool or synthetic blends, never cotton, which retains sweat and increases friction coefficient by approximately thirty percent when damp. Apply friction-reducing products like Body Glide or lubricating balms to known hot spots before activity starts. Tape high-risk areas proactively using moleskin or medical tape before blisters form rather than reacting after one appears. The tape creates a smooth surface that slides against the shoe interior instead of your skin. This pre-emptive taping method cuts blister incidence by roughly half in people who are prone to them, based on sports medicine studies and repeated real-world testing across different activity types.