Oral thrush treatment isn't complicated, but people keep making it worse by waiting too long or picking the wrong antifungal.
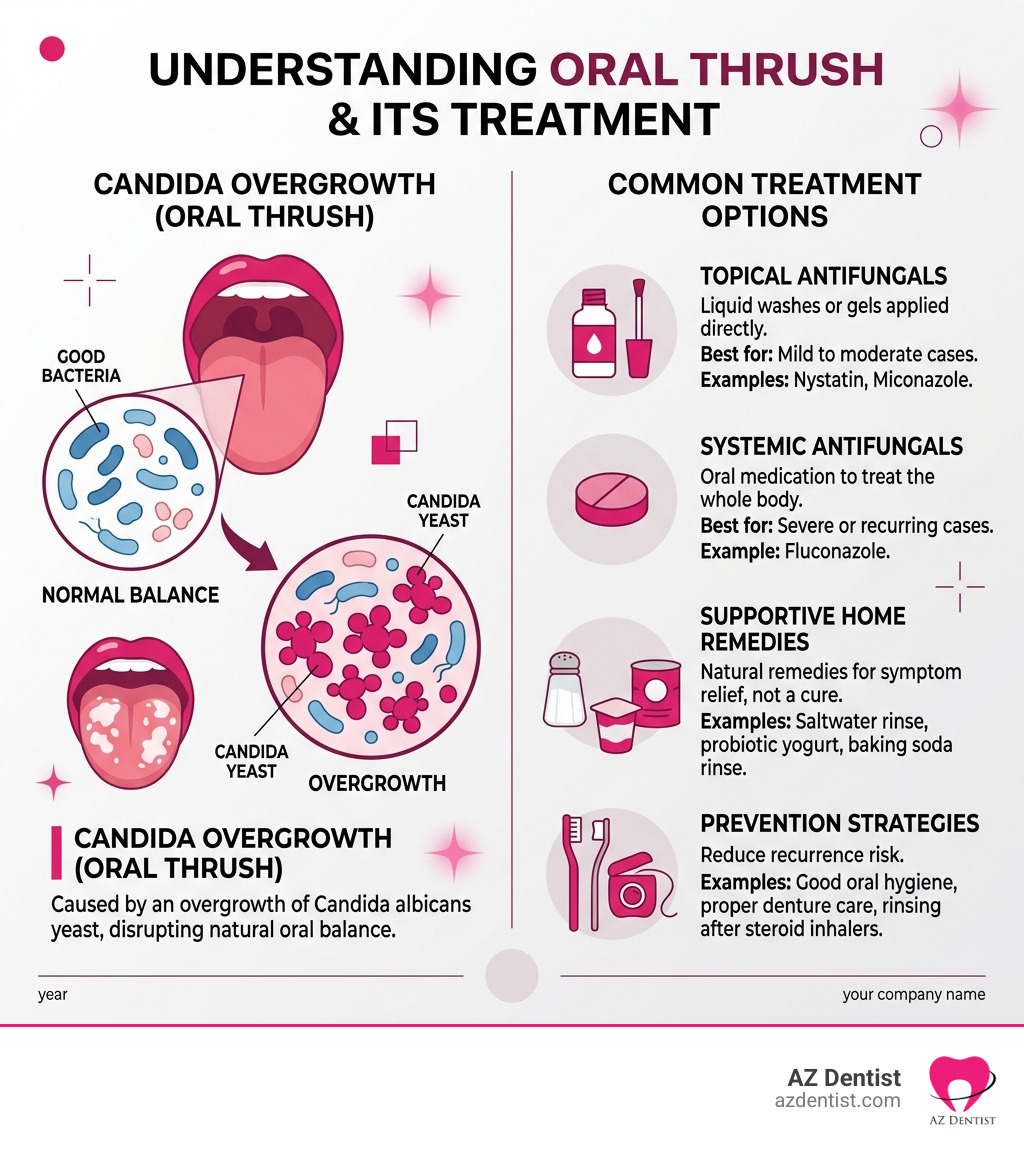
I saw a patient last month who'd been treating what she thought was a sore tongue for six weeks with probiotics and salt water rinses. It was Candida. The white patches wouldn't wipe off, and the burning had become constant. By the time she finally saw someone who actually looked at the lesions, the infection had spread to her cheeks and palate. She'd lost taste in half her mouth. This is the kind of thing that happens when you treat oral thrush like it's a canker sore. Nystatin suspension is still the first-line treatment for mild to moderate cases. The standard dose is 4-6 mL swished around the mouth for as long as you can tolerate before swallowing, four times daily, for 7 to 14 days. You hold it in your mouth for about 60 seconds each time. Don't swallow it immediately. The drug needs contact time with the mucosal surface to work. Swallowing it right away just sends the medication to your stomach where it does nothing for the Candida colonies sitting on your tongue and buccal mucosa. For more resistant cases or immunocompromised patients, fluconazole 100-200 mg orally once daily for 7 to 14 days is the go-to. It's systemic, so it hits areas you can't swish nystatin into effectively. The problem is fluconazole resistance is climbing. I've seen three patients in the past year whose thrush came back within two weeks of finishing a fluconazole course because the Candida strain wasn't susceptible. Switching to itraconazole solution or voriconazole worked in those cases, but you need a culture to know which one before you prescribe. Blind switching just delays the right treatment and gives you false confidence that the second drug should work.
The edge case I keep running into is patients on inhaled corticosteroids for asthma or COPD who develop thrush every time they adjust their dose. They rinse with water after each use, which helps but doesn't eliminate the risk. The workaround I found that actually sticks is having them swish with nystatin suspension at the first sign of white patches instead of waiting until it becomes symptomatic. Early intervention cuts the duration from about 10 days down to 4 or 5 days in most cases. Waiting until pain develops adds another week because the fungal load is significantly higher and the mucosal barrier is already compromised. Clotrimazole troches are another option, but they're messy. You dissolve one tablet five times daily, and the taste is awful. Compliance drops off sharply after day three. Patients spit out the residue instead of swallowing the medication, which defeats the purpose. I prefer nystatin for outpatients who aren't already on systemic antifungals because the suspension is easier to dose and the taste is more tolerable. Here's what people miss: oral thrush rarely occurs in isolation in adults. If you're treating it without checking for predisposing factors, you're doing half the job. Diabetes, recent antibiotic use, denture wear, and inhaled steroid use are the big ones. I had a patient whose thrush kept coming back every three weeks for four months. We finally ran an HbA1c and it was 8.4. Undiagnosed type 2 diabetes. Once we got her blood sugar under control with metformin, the thrush stopped returning. Treating the infection without addressing the underlying metabolic issue is why so many patients cycle through multiple antifungal courses with no lasting relief.
Nystatin is not absorbed systemically, which is why it stays in the GI tract and doesn't interact with other medications. That's the advantage. The disadvantage is it only works topically in the mouth and esophagus. If the Candida has invaded deeper tissues or the patient is neutropenic, topical agents won't penetrate far enough. Systemic fluconazole or itraconazole becomes necessary, and you need to monitor liver enzymes because azole antifungals are hepatotoxic at prolonged doses. Denture hygiene matters more than patients realize. Soaking dentures in chlorhexidine solution overnight reduces recolonization by about 60 percent. I had a patient whose thrush returned within two weeks of finishing treatment because she kept reinserting the same dentures without disinfecting them. The biofilm on the acrylic was harboring Candida. Switching to a fresh set of dentures or thorough nightly disinfection broke the cycle. Most patients don't think about their prosthetics being a reservoir for reinfection. The bottleneck in treatment is patient compliance, not drug efficacy. Nystatin requires four doses daily for up to two weeks. Fluconazole is once daily, which is why it's preferred for busy patients, but resistance is a real problem. I've seen good responses with nystatin in patients who couldn't tolerate fluconazole due to liver enzyme elevation, but the frequent dosing means some patients skip doses and extend their recovery timeline unnecessarily. The trade-off is real and worth discussing before prescribing.
Get the Full Details

If you have recurrent oral thrush despite appropriate treatment, check for HIV, chemotherapy-induced neutropenia, or uncontrolled diabetes. I had a patient whose thrush responded to nystatin but returned within days of stopping. Three rounds of treatment and three recurrences later, we ran an HIV test. It was positive. The thrush wasn't the primary problem. It was a marker of immunosuppression that needed a completely different treatment pathway. Don't keep treating the surface infection without looking for the root cause if it keeps coming back.