
Understanding the Problem Before You Start Moving
Sciatica is just pain radiating along the sciatic nerve pathway, which runs from your lower back through your hips and down each leg. Most cases come from a herniated or bulging disc pressing on the nerve root. Some come from piriformis syndrome where the muscle in your glute compresses the nerve. A few come from spinal stenosis. The treatment approach changes significantly depending on which one you actually have, so if someone is telling you to do the same exercises regardless of cause, they're guessing. I spent years watching people blow through random YouTube routines and make their pain worse. The issue is that not all sciatica movements are equal. Some directions help, some directions hurt, and the difference often comes down to which way the disc is bulging relative to your spine.
How To Treat Sciatica With Exercise: A Practical Framework
The foundational approach is directionally preference-based movement, commonly called McKenzie Method or mechanical diagnosis and therapy principles. The idea is simple enough. You perform repeated movements in one direction, and if symptoms centralize meaning the pain moves out of your leg and back toward your spine, you keep doing that direction. If symptoms peripheralize meaning the pain shoots further down your leg, you stop immediately and try the opposite direction. Here are the most common starting positions and how I've seen them play out in practice. Prone lying is the first step for most disc-related cases. Lie on your stomach for two to three minutes. If that reduces leg pain or brings it closer to your lower back, you continue. If it makes things worse, that's your answer right there. You probably need flexion-biased work rather than extension.
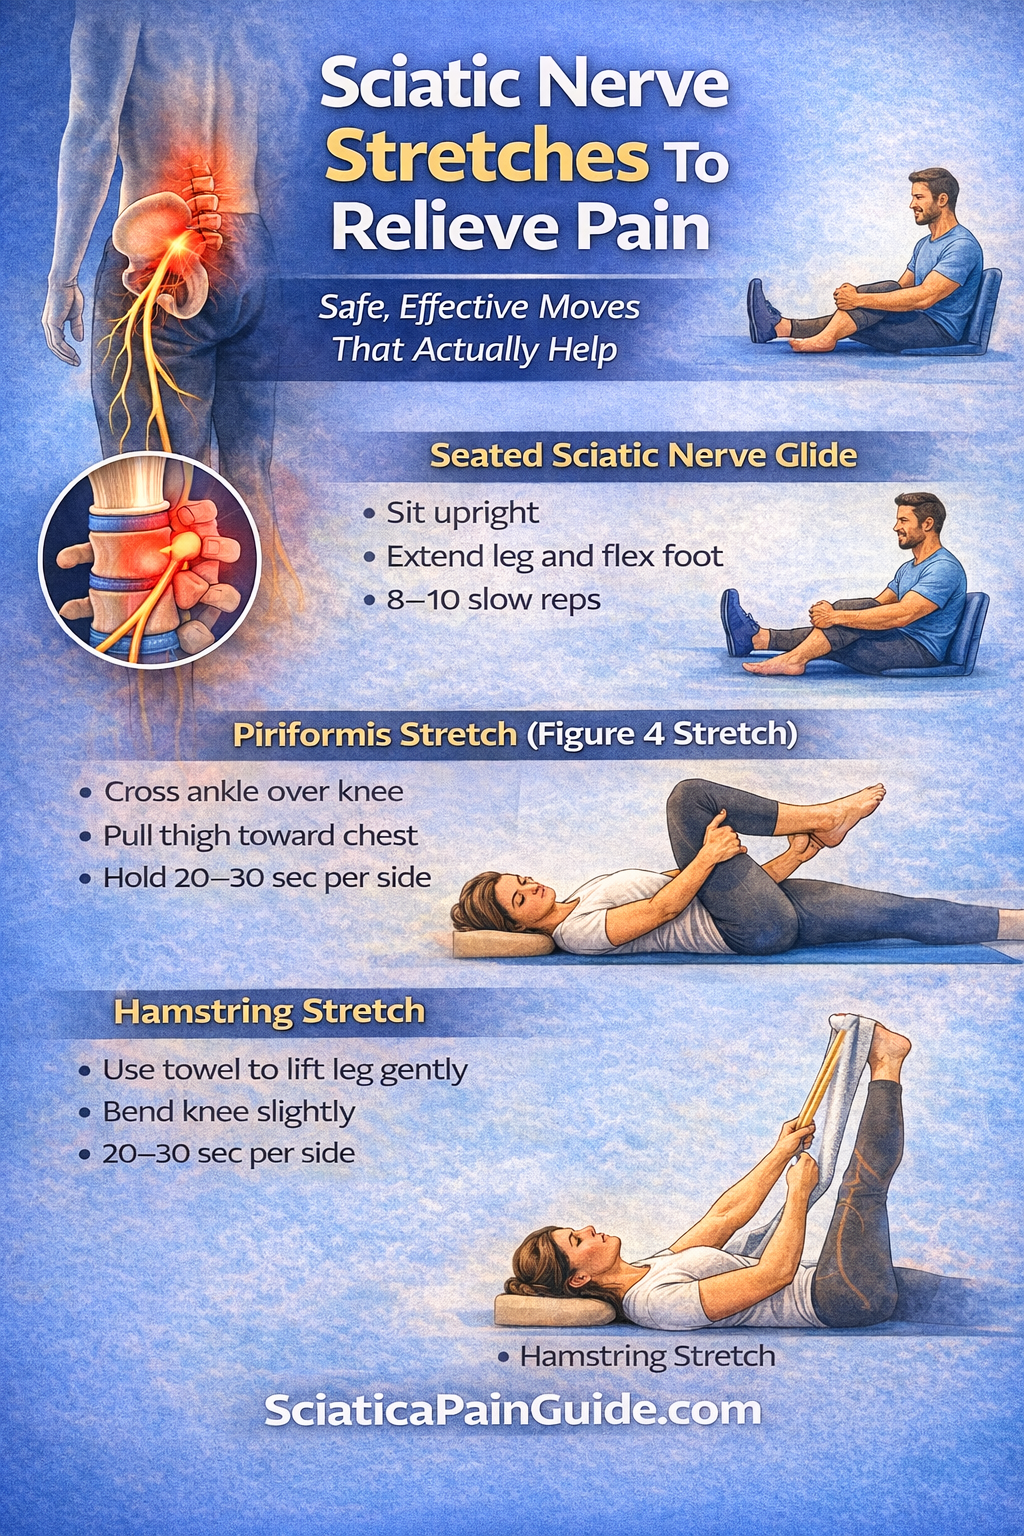
Prone on elbows comes next if prone lying felt neutral or helpful. Rest on your forearms with your hips relaxed on the floor. Hold for thirty seconds to a minute. Repeat ten times. This gently loads the lumbar spine into extension and can help shift a posteriorly bulging disc away from the nerve root over time. Most people need between eight and twenty repetitions before noticing a change, but some feel relief after the first set. Press-ups are the progression. From prone on elbows, place your hands under your shoulders and slowly straighten your arms to lift your upper body while keeping your hips on the floor. Go only as far as feels manageable. Ten repetitions, several times a day. Do not force end range. The goal is a mild to moderate stretch in the lower back, not a deep bend. Pushing too hard in the early days just re-irritates the inflamed nerve. For piriformis-related cases, the approach is completely different. These people usually feel better with flexion and worse with prolonged sitting or aggressive hip extension. A gentle figure-four stretch, seated or supine, held for twenty to thirty seconds and repeated five times, tends to help. Again, if it increases leg pain below the knee, stop. That means you're aggravating the nerve directly rather than releasing the muscle.
Get the Full Details

Walking is underrated and something most patients skip because it feels like nothing. Ten to fifteen minutes of level walking, twice daily, promotes blood flow to the affected structures without significant compressive loading. I've had patients who avoided all movement except bed rest and ended up stiffer and more painful after a week. Gentle motion is almost always better than stillness for disc issues.
Things People Mess Up Consistently
The biggest mistake I see is doing exercises with poor form because they're in pain. People hunch their shoulders, brace their neck, and hold their breath during press-ups. That changes the mechanics entirely and shifts load away from the lumbar spine into the thoracic region where it does nothing for sciatica. Breathe through it. Keep your neck neutral. Let your hips stay heavy on the floor during extension work. Another common error is stopping too soon because the first few reps don't change anything. Peripheralization and centralization are not always immediate. It can take two to three weeks of consistent daily work, usually ten to fifteen reps per set performed three to four times per day, before you see a meaningful shift. I had a patient who quit on day four after press-ups did nothing. She came back on day eleven and noticed her foot numbness had reduced by about half. The nerve was still inflamed but slowly settling. Consistency matters more than intensity here. Hamstring stretching early in the acute phase is also problematic. Tight hamstrings are often a protective reflex from the irritated nerve, not the actual cause of symptoms. Aggressive static stretching of the hamstrings in the first one to two weeks can directly irritate the nerve root further. Wait until the acute radiating pain has centralized before introducing any hamstring work. Even then, keep it gentle and avoid bouncing.
There is also a subset of patients with lateral recess stenosis or severe foraminal narrowing where extension exercises make everything worse. If your leg pain consistently increases during press-ups or standing upright and decreases when you lean forward on a shopping cart or walker, you likely have a stenosis component. Extension-biased exercises will aggravate that. Those patients benefit more from flexion-biased movements like seated forward bends and cycling motions rather than repeated extension. I encountered this exact edge case last year with a client who had been doing press-ups daily for three weeks with no improvement and increasing calf pain. We switched to seated lumbar flexion holds and modified cat-cow movements on all fours with a limited range. Within four days her leg symptoms dropped significantly. The diagnosis turned out to be mixed disc protrusion with lateral recess involvement, which meant pure extension was part of the problem. That one changed the entire protocol.
Progression and What Comes After
Once symptoms have centralized, usually within two to six weeks for most disc-related cases, you can begin adding core stabilization. Dead bugs, bird dogs, and planks are all reasonable options. Start with isometric holds of ten to twenty seconds and build from there. Avoid sit-ups and toe touches. Both place high compressive loads on the lumbar discs and are counterproductive during recovery. Glute activation matters too. Many people with chronic sciatica develop inhibited gluteus medius and maximus function from altered movement patterns. Clamshells and bridges, done gently without compensating through the lower back, help restore basic hip stability. Poor hip stability transfers more stress to the lumbar spine during walking and standing, which undermines the progress you've made. Neural gliding or flossing exercises can be useful in the subacute phase, typically after the first two weeks when acute inflammation has settled. These are gentle, rhythmic movements that move the sciatic nerve through its range without stretching it aggressively. A typical sequence involves lying on your back, hip flexed to about sixty degrees, and slowly straightening and bending the knee while coordinating ankle dorsiflexion and plantarflexion. Ten to fifteen repetitions per side, once or twice daily. If any movement reproduces sharp radiating pain, the nerve is still too irritated and you should skip neural glides entirely until the acute phase passes.
Return to normal activity should be gradual. Most people can resume light daily activities within one to two weeks and more strenuous exercise within four to six weeks if symptoms are improving in the right direction. Heavy lifting, especially with a rounded lower back, should be avoided for at least eight to twelve weeks after the initial episode. The disc needs time to heal structurally, and re-injury during that window is far more common than people expect. If you have tried conservative exercise management for six to eight weeks with no improvement, or if you experience progressive weakness, saddle anesthesia, or bowel or bladder dysfunction, you need to see a physician immediately. Those are red flags that suggest cauda equina syndrome or significant nerve compression requiring intervention beyond exercise. Most sciatica cases resolve without surgery. The data shows roughly eighty to ninety percent of people improve within six to twelve weeks with appropriate conservative care. The exercise component is a meaningful part of that, but it is only part of the picture. Sleep position, prolonged sitting habits, stress levels, and general activity modification all influence outcomes. Ignoring those factors while obsessing over the right exercise sequence is a reliable way to stall your recovery.



