Shin Splints Actually Work Like This
Medial tibial stress syndrome. That is what most people mean when they say shin splints. It is inflammation of the periosteum where the soleus and tibialis posterior attach to the tibia. Runners get it. Dancers get it. People who suddenly started walking 6,000 steps a day on concrete also get it. The standard advice is rest, ice, NSAIDs, modify activity. None of that is wrong. It is also incomplete. Here is what actually happens when you try to recover from shin splints, based on people who have dealt with it more than once.
How To Treat Shin Splints In Practice
Start by understanding that shin splints are a load management problem, not an acute injury in the traditional sense. Your tibialis anterior and the tissues along your medial tibia have been asked to do more work than their current capacity allows. The goal is to bring load back up gradually while keeping pain tolerable. The pain scale that matters here is between zero and three out of ten during activity. If you are at four or five while running or walking, you are still causing microtrauma. Back off until you are at a two or three. Some days that means no activity at all. Other days it means shorter sessions. I found that the single most useful modification was switching to a slightly higher cadence. Instead of letting my stride stretch out, I shortened it and increased steps per minute by about ten percent. That shifted impact forces away from the mid-tibia and toward the ankle and hip. It did not cure anything on its own, but it let me maintain some cardiovascular work while the tissue settled down.
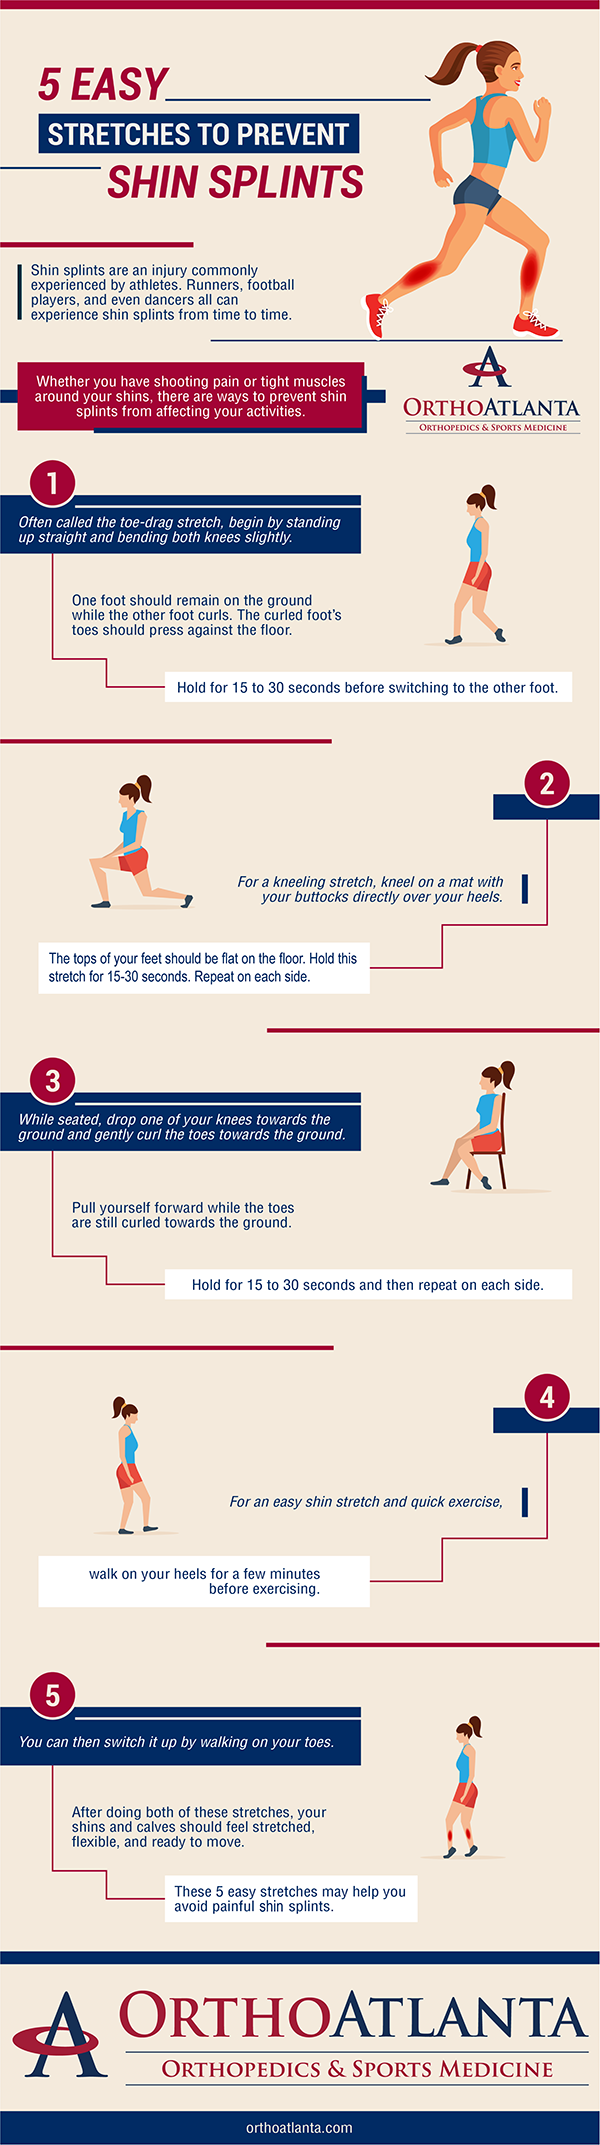
Strength training is where the actual recovery happens. Calf raises, preferably both with the knee straight and the knee bent, because you are loading the gastrocnemius and the soleus separately. Three sets of ten, slow tempo, heavy enough that the last two reps feel genuinely difficult. Do this every other day. I also added single-leg Romanian deadlifts and tibialis raises using a band, because the anterior compartment matters just as much as the posterior chain. Metasole inserts or a temporary arch support can help if you are overpronating. I used them for about six weeks while doing the strengthening work. They are not a long-term solution, but they buy time. Once the calf and tibialis strength improved, I stopped using them.
Get the Full Details

What Nobody Tells You About Shin Splint Recovery
The timeline is not the same for everyone. A typical conservative estimate is four to six weeks before normal activity feels comfortable. Some people are back sooner. Others take three months or longer. The ones who never deal with it again are usually the ones who do not return to full load the day the pain stops. I made the mistake once of running pain-free for two weeks straight and then going back to my old mileage immediately. The shin splints came back worse. The workaround was to cap weekly volume at 80 percent of the previous peak for at least two weeks after pain resolution, then add no more than 10 percent per week. It felt slow. It worked. Footwear matters more than most people think. I tracked the cushioning degradation in my shoes using a simple mileage log. Once a pair hit roughly 350 miles, I rotated them out. Running in dead shoes while already dealing with shin splints is a fast track to making the problem chronic rather than acute.
There is also a specific type of shin splint that does not respond well to rest alone. If the pain is localized to a single small point on the tibia rather than spread along several inches, that can indicate a stress fracture rather than periostitis. An X-ray might not catch it early. If you suspect that, see someone who can order an MRI or bone scan. Pushing through a stress fracture is how people end up with surgery instead of a six-week layoff. Another counter-intuitive thing: cross-training on a stationary bike or in the pool will keep your fitness up without aggravating the tibia, but it will not make the shin heal faster. The tissue still needs progressive mechanical loading to remodel. Swimming and cycling are fine for cardio maintenance. They are not treatment. NSAIDs will reduce pain and let you function, but they do not speed healing. Using them to run through pain consistently is a trap. Take them if you need to walk around, but do not use them as an excuse to add volume.
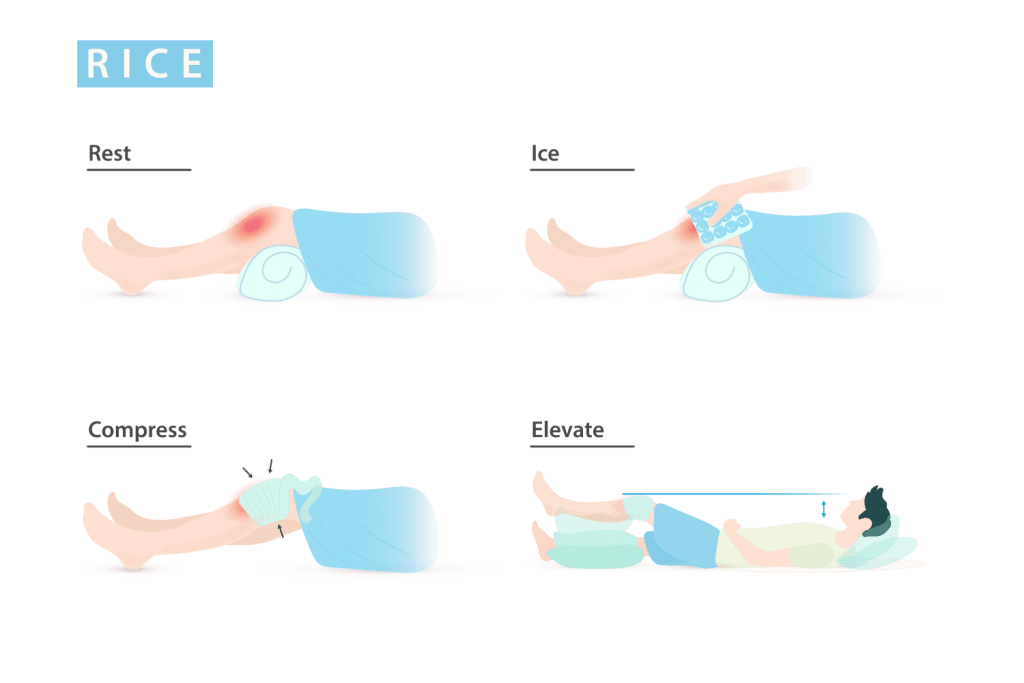
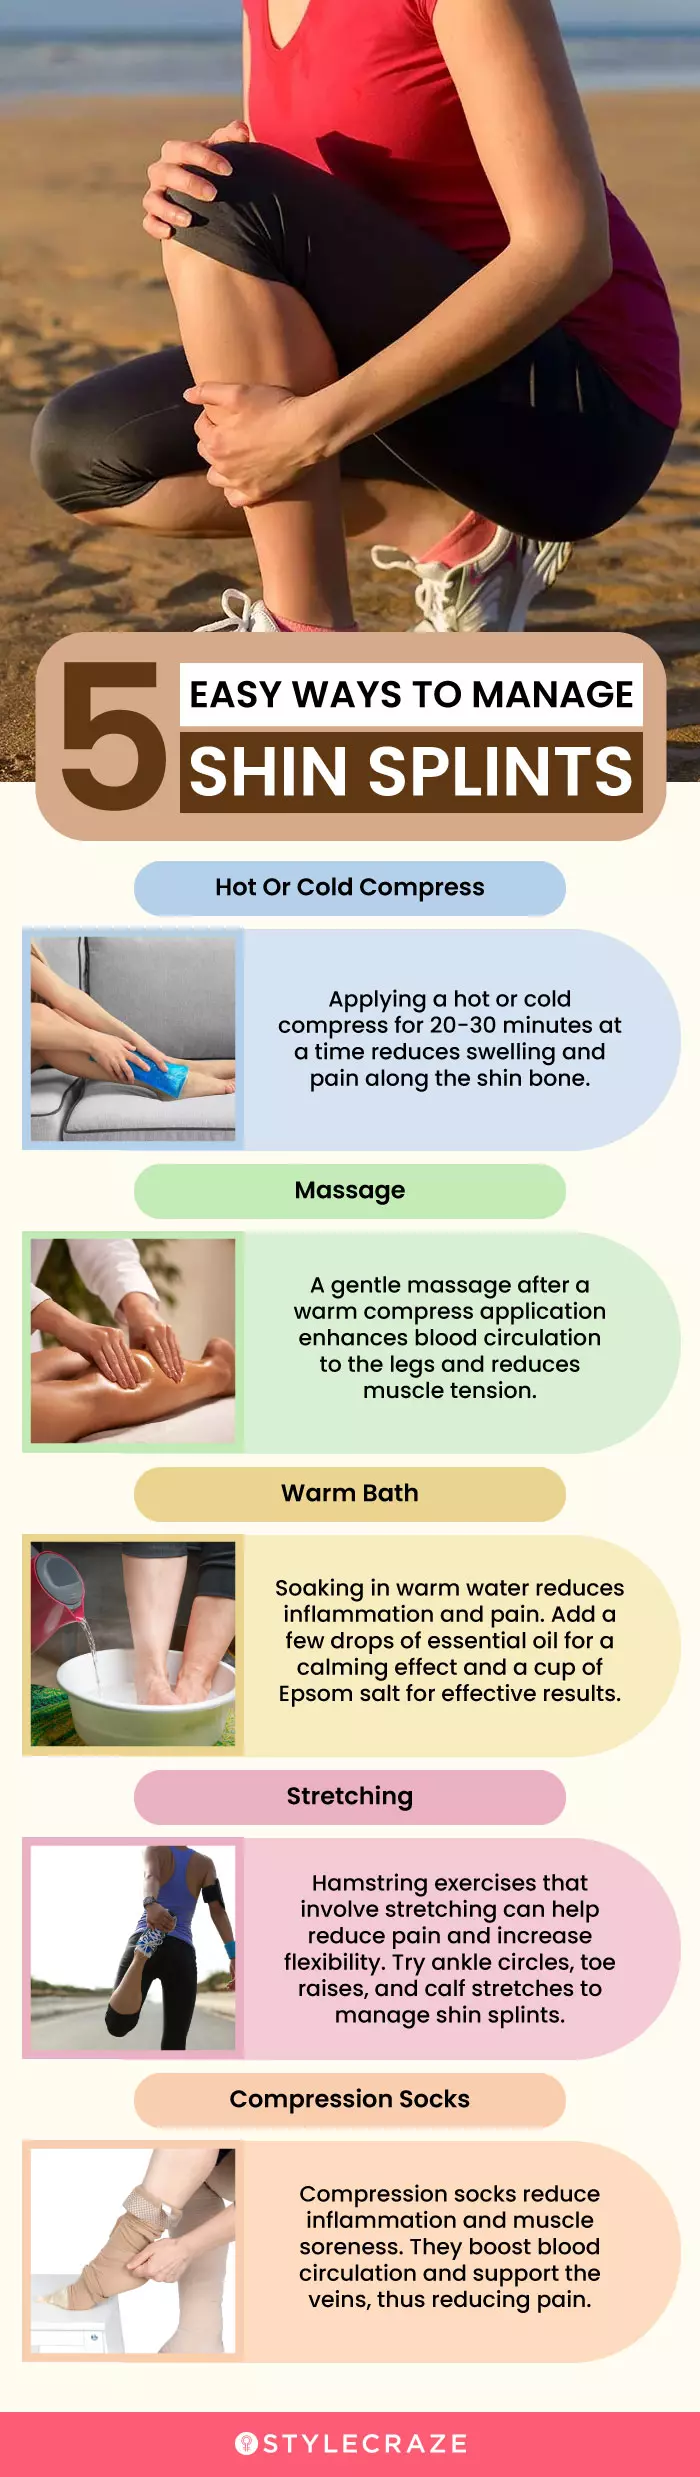
Heat in the morning and ice after activity is a reasonable routine. Not revolutionary. But the combination helps some people manage symptoms more comfortably while the strengthening work does the real repair. I kept it simple: five minutes of heat before loading the leg, fifteen minutes of ice after. The hardest part is psychological. Shin splints make you feel like your fitness will vanish if you stop running for a few weeks. It does not. You lose maybe two to three percent of aerobic capacity in that timeframe if you cross-train. What you gain is a tibia that can actually handle load again instead of breaking down every time you increase mileage by fifty percent. If you have tried everything and the pain persists past eight weeks, it may not be shin splints. Posterior tibial tendon dysfunction, compartment syndrome, and nerve entrapment all present with anterior lower leg pain that looks similar on the surface. Getting a proper diagnosis at that point is worth the time and expense.