The mechanics of an autoinjector are simpler than people think, but the execution is where everything goes wrong.
An EpiPen is a spring-loaded autoinjector that delivers epinephrine (also called adrenaline) intramuscularly into the outer thigh. It's indicated for the emergency treatment of Type I anaphylaxis with symptoms involving the airway, breathing, or circulation. That covers things like throat tightness, wheezing, a sudden drop in blood pressure, widespread hives, or swelling of the lips and tongue after exposure to an allergen. You do not wait to see if it gets worse. You use it when anaphylaxis is suspected. I remember running into a case a few years back where a patient's spouse had been prescribed an EpiPen but stored it in a hot car in the garage all summer. When they finally needed it, the solution inside looked slightly yellowish instead of clear and colorless. The medication had degraded. The device still fired fine because the spring mechanism is independent of the drug integrity, but the epinephrine was partially broken down into adrenochrome, meaning the patient got far less than the labeled 0.3 mg dose. The workaround is simple: check the solution every three months by holding the transparent window up to the light. If it's not clear and colorless, replace it. Don't get clever about it. Also store it at room temperature, not in the bathroom cabinet where humidity spikes, and certainly not in a glovebox or trunk.
How To Use An Epipen
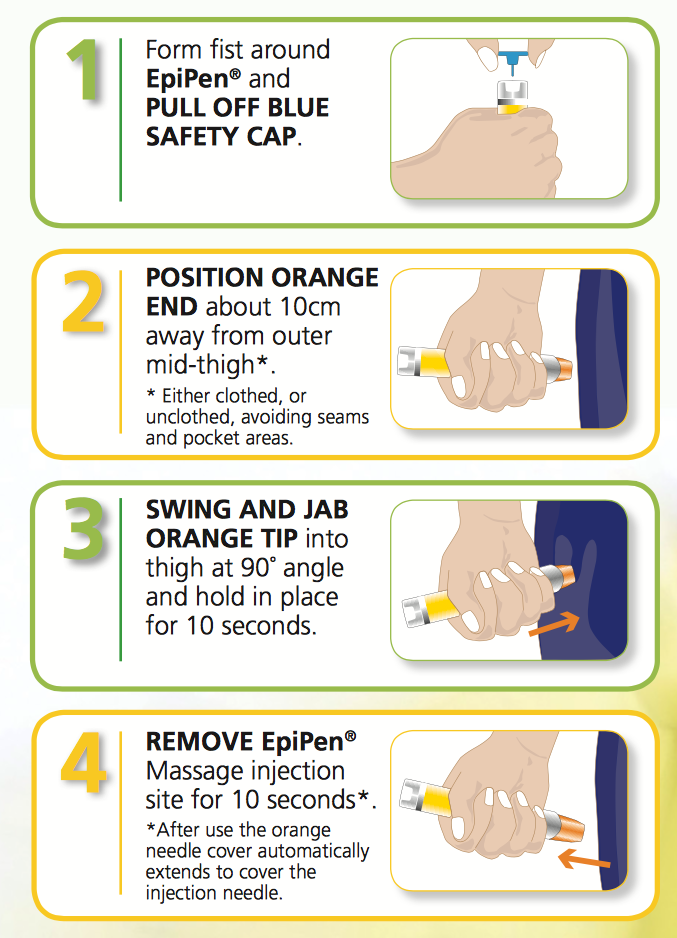
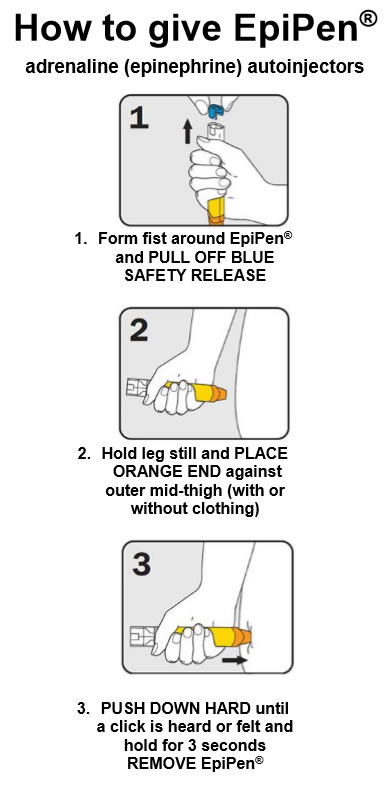
Here is the sequence, stripped of the cartoon illustrations on the box: Step one: grab the EpiPen. Hold it in your dominant hand with the orange tip facing downward. The orange end is the needle. The blue end is the safety cap. You will remove the blue cap by pulling it straight off. Do not twist. Do not thumb-push. Just pull. One motion. That exposes the needle and arms the spring mechanism. You have a few seconds before the needle guard retracts on its own, but don't test it. Just proceed. Step two: swing and stick. Place the orange tip against the middle of the outer thigh. It does not matter if the person is standing, sitting, or lying down. The thigh is the only recommended site. The deltoid, the buttock, the vein — none of those are correct. Aim perpendicular to the leg, not at an angle. Push until you hear or feel a click. That click means the needle has deployed and the dose is being delivered.
Step three: hold it there. Ten seconds. Not five. Not three. A full ten seconds. The needle takes about two seconds to penetrate the muscle and the automatic retraction mechanism begins firing once you lift it. If you pull off early, you are injecting into the subcutaneous fat instead of the muscle, and absorption from fat is unpredictable and significantly slower. You want intramuscular delivery for rapid onset. Epinephrine given IM into the thigh has a peak plasma concentration roughly twice as fast as subcutaneous injection. Step four: remove and massage. Pull the device straight out. The needle retracts automatically into the orange housing. Rub the area for about ten seconds. This helps disperse the medication through the muscle tissue and may reduce local soreness. Check the sight window on the side of the device. After a proper injection, the window turns completely orange. If it is only partially orange or still shows blue, the dose may not have been fully delivered. In that scenario, use a second EpiPen if one is available and seek emergency care immediately. Clothing is not a barrier. I have seen people hesitate because the person is wearing jeans. The needle penetrates typical denim without issue. If the fabric is thick like heavy canvas or multiple layers of winter gear, you can press through it, but a blade or scissors to cut a small opening is faster and ensures the full needle length contacts the thigh. Half an inch of cloth between the device and the skin can dampen the force enough that the needle barely enters the muscle.
Get the Full Details
There is a common misconception that you should inject into the upper arm. Some people try this with children or when the thigh is inaccessible. The data does not support it. The vast majority of anaphylaxis cases show lower success rates with deltoid injection, and the device is simply not designed for that site. Stick to the thigh. After the injection, call emergency services. Not later. Now. Epinephrine's half-life is approximately two hours, but the clinical effect of a single autoinjector dose typically lasts only 10 to 20 minutes. The initial surge reverses bronchoconstriction and raises blood pressure temporarily, but without further medical treatment the reaction can rebound. This is called biphasic anaphylaxis and it occurs in roughly one to two percent of cases after a single epinephrine dose. That sounds low until you are the one dealing with it at 2 AM in an ER waiting room with no antihistamines or steroids on board yet. Another nuance most people miss: if symptoms do not improve within five to fifteen minutes after the first injection, a second dose may be warranted. This is stated on the prescribing information, but very few patients or bystanders know it. Have a second EpiPen accessible at all times if you have a known severe allergy. Carrying only one is a gamble.
There are limitations to the device itself. The 0.3 mg dose is intended for patients weighing 30 kg or more. Children under 30 kg should use the EpiPen Jr, which delivers 0.15 mg. Using a full-dose EpiPen on a small child is not ideal, but in a true anaphylactic emergency, giving epinephrine is still far safer than withholding it. The worst thing that can happen from an extra dose of epinephrine in a child is tachycardia and anxiety, which resolve quickly. The worst thing that happens from no dose is death. The devices expire. Not slowly. They have a hard expiration date printed on the carton and the tube. After that date, the epinephrine potency is no longer guaranteed. The FDA recommends replacement annually or at the expiration date, whichever comes first. I once audited a school nurse's emergency kit and found three expired EpiPens that were past their date by over a year. They looked fine. The solution was clear. But the potency could have been significantly reduced. Always replace before the date, not after. If you need to download or print an instruction card, the manufacturer (Mylan, now part of Viatris) provides a patient guide on their website that you can save to your phone or print and keep in your bag. It is the same information as above but formatted for quick reference. The device tube itself also contains a brief summary, though it is cramped and hard to read in a panic.
The most important thing to remember is that using an EpiPen is the first step, not the last step. It buys time. It does not replace an ambulance ride. It does not replace emergency medical evaluation. The reaction can progress past the point where a second dose helps. Act fast, hold for ten seconds, and get to professional care immediately.