Getting Started With Extracorporeal Shockwave Therapy
Most people buy these machines and immediately press the trigger without thinking through the setup. That is how you waste money and irritate patients. The actual process is more methodical than most manuals suggest. Before you even power the unit on, check your coupling medium. Water-based gel is standard, but if you are working over bony prominences like the calcaneus or olecranon, you need a thicker gel or a dedicated contact cushion. Thin gel allows too much energy dispersion and the pulses lose intensity before they reach the target tissue. I once spent two weeks troubleshooting why a patient's plantar fasciitis treatment was producing zero clinical improvement. Turns out I was using the same gel consistency I'd always used for soft tissue work over the femoral head. Swapped to a conductive hydrogel pad and the results changed overnight. The energy transmission difference was stark.
How To Use Shockwave Therapy Machine Effectively
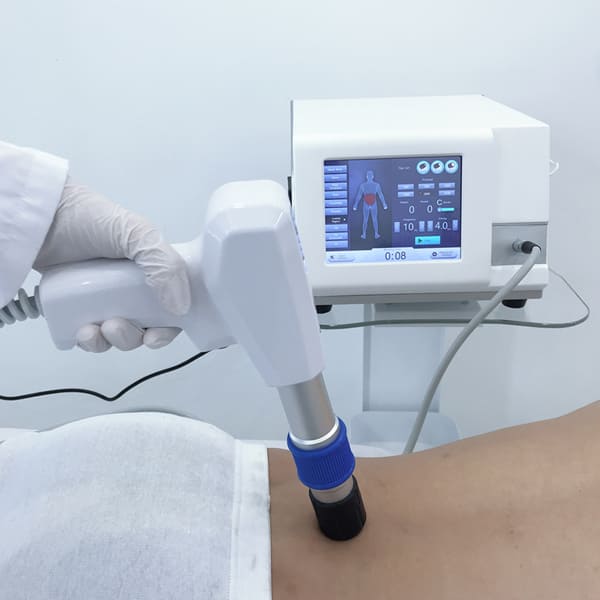
Power up the device and run the self-test if your unit has one. Most modern machines will prompt you through this. Take the time to actually watch it complete—it flags transducer faults that you would not catch by just staring at the screen. Select your transducer type. Focused shockwave and radial pressure wave are fundamentally different modalities, and confusing them is the most common mistake I see. Focused devices deliver energy to a specific depth point, usually between 10 and 40 millimeters depending on the lens configuration. Radial devices blast broad-surface pressure waves that decay quickly with depth, making them better for superficial myofascial work but useless for deep tendinopathies. If you pick the wrong transducer for the condition, you are essentially paying for nothing. Set your parameters. Frequency typically ranges from 4 to 20 hertz. For most chronic tendinopathies, I run between 8 and 12 Hz. Higher frequencies deliver more impulses per second but reduce the peak pressure per pulse. If you are treating calcific rotator cuff tendinopathy where you need fracture energy, you want lower frequency with higher pressure. Energy flux density is measured in millijoules per square millimeter. Start at 0.08 to 0.12 mJ/mm² for conservative protocols. You can escalate to 0.25 or 0.30 for more aggressive protocols on larger muscle groups.
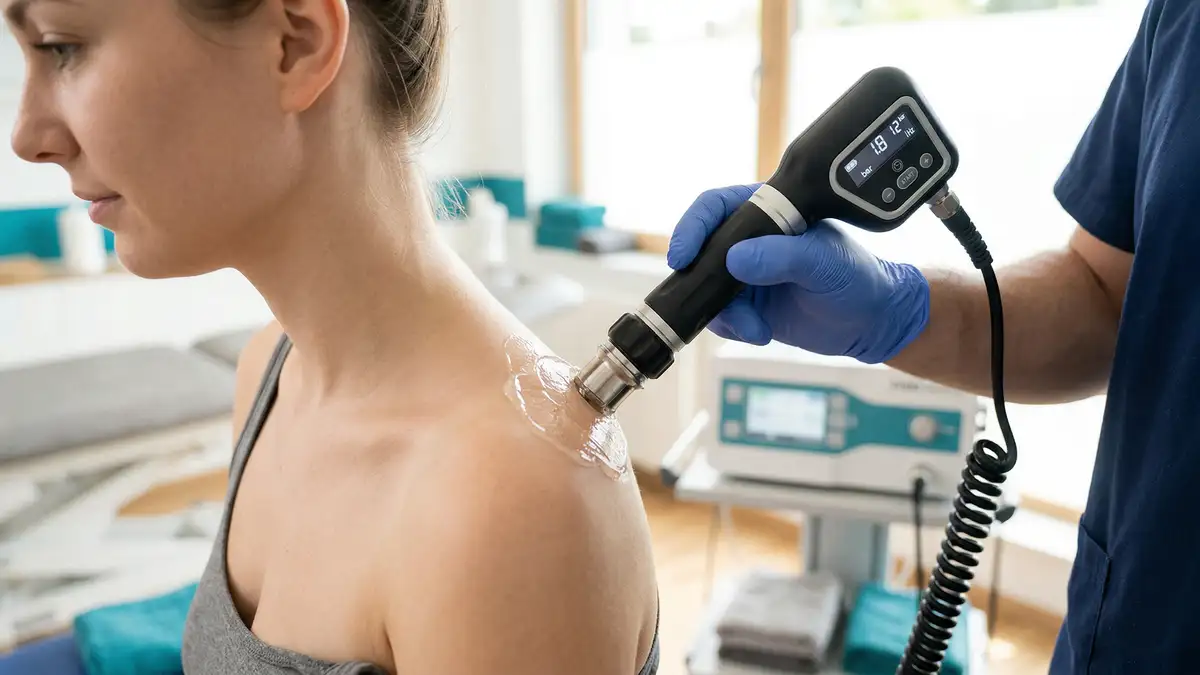
Number of impulses per session matters more than most practitioners realize. A standard treatment is between 1500 and 3000 shocks per area. For a small focal point like the medial epicondyle, 2000 impulses at 10 Hz takes about 3 and a half minutes. Do not rush by cranking the frequency up to hit your impulse count faster—that trades precision for speed and ruins the treatment. Leave the duration alone. Set the frequency, set the energy, and let the machine run its cycle. Position the transducer perpendicular to the skin surface. Angling it even slightly causes the beam to scatter, especially with focused devices. Use coupling gel generously. You should see a thin film between the transducer head and the skin, not a dry gap. If the gel starts drying out mid-session, add more. Drying creates micro-air pockets that block energy transmission completely. For focal treatments, mark the treatment area with a skin-safe marker. A 2 by 2 centimeter grid works well for larger areas. Move systematically across the grid, pausing at each intersection for the programmed impulse count. On mobile joints like the shoulder or knee, reposition the limb between subareas rather than dragging the transducer across moving skin. Dragging distorts the coupling and creates inconsistent energy delivery.
Get the Full Details

Patient tolerance is the real variable here. The treatment should be uncomfortable but tolerable. If the patient is bracing or pulling away, you have either gone too high on energy flux density or hit a genuinely hypersensitive zone. Drop the energy by 20 percent and continue. I had a case with a patient who had lateral elbow tendinosis where the pain tolerance was so low that even 0.08 mJ/mm² was intolerable. I switched to a radial transducer at the same energy setting and completed the session. Radial delivers a broader, less intense impulse pattern and the patient tolerated it fine. Same clinical goal, different delivery method. After the session, wipe off the gel and apply ice if the area is significantly inflamed. Most patients can return to normal activity immediately. Do not recommend heavy loading on the treated area for 48 hours. The microtrauma from the impulses initiates an inflammatory healing cascade, and overloading that area too soon disrupts the process. Protocol frequency is typically once per week for three to five sessions. Some conditions like Achilles tendinopathy respond well to a biweekly schedule instead of weekly. Chronic calcific deposits often need the full five sessions. Acute soft tissue irritation sometimes resolves in two. Track your outcomes in a simple log—condition, parameters used, number of sessions, and patient-reported pain scale before and after each visit. The data will tell you what your settings should look like for the next case.
Common Mistakes That Wreck Treatment Outcomes
Using focused shockwave on acute inflammatory conditions is a mistake. If the tissue is already acutely inflamed with significant edema and thermal changes, adding mechanical trauma from shockwaves will make it worse. Wait until the acute phase subsides. Radial devices are slightly more forgiving here but still not ideal in the first 72 hours of an acute injury. Another frequent error is treating nerve-rich areas directly. The medial side of the elbow near the ulnar nerve, the posterior tibial nerve behind the medial malleolus, the superficial peroneal nerve near the lateral ankle—these are not treatment zones. You can work around them, but direct impulse delivery over a superficial nerve causes radiating pain and can temporarily irritate the nerve itself. Learn the anatomical landmarks. It takes about two weeks of study to memorize the major peripheral nerve pathways in the upper and lower extremities. Contraindications matter. Do not use shockwave over malignant tissue, over the lungs, over the brain or spinal cord, in pregnant patients over the abdominal or lumbar region, or over active infection. Blood thinner medication is not an absolute contraindication but it increases bruising risk significantly. I always ask about anticoagulant use before the first session and adjust energy downward if the patient is on therapeutic doses.
The machine itself requires maintenance. Clean the transducer head with an alcohol wipe between patients. Inspect the coupling line for cracks or wear. Store the unit in a dry environment. The transducer is the most expensive consumable part on these machines and replacing a damaged head runs anywhere from three hundred to twelve hundred dollars depending on the model. Treat it like a precision instrument because it is one. Download documentation for your specific model from the manufacturer website before you start using it. Parameters vary between brands. A setting of 0.15 mJ/mm² on one machine may not deliver the same tissue effect as 0.15 on another. The energy density labels are standardized but the actual output can differ based on transducer construction and generator design. Your machine's manual will have the validated parameter tables for specific conditions. Follow those as your baseline. Shockwave therapy is not a standalone solution for everything. It works well for chronic tendinopathies, calcific shoulder tendinitis, plantar fasciitis, and some cases of delayed bone union. It does not work well for acute muscle tears, ligament sprains in the early phase, or neuropathic pain conditions. Know the evidence base for what you are treating and do not oversell the modality to patients. The results are good but they are not universal.

If you are getting started, begin with one or two conditions you understand well. Pick plantar fasciitis or lateral epicondylopathy as your first cases. The anatomy is straightforward, the parameter ranges are well established, and the outcome tracking is easy. Once you have treated fifteen to twenty cases successfully, expand into more complex presentations. The technique is not difficult. The skill is in knowing when not to use it and how to adjust when the standard protocol is not producing the expected response.