Writing the HPI Section Correctly
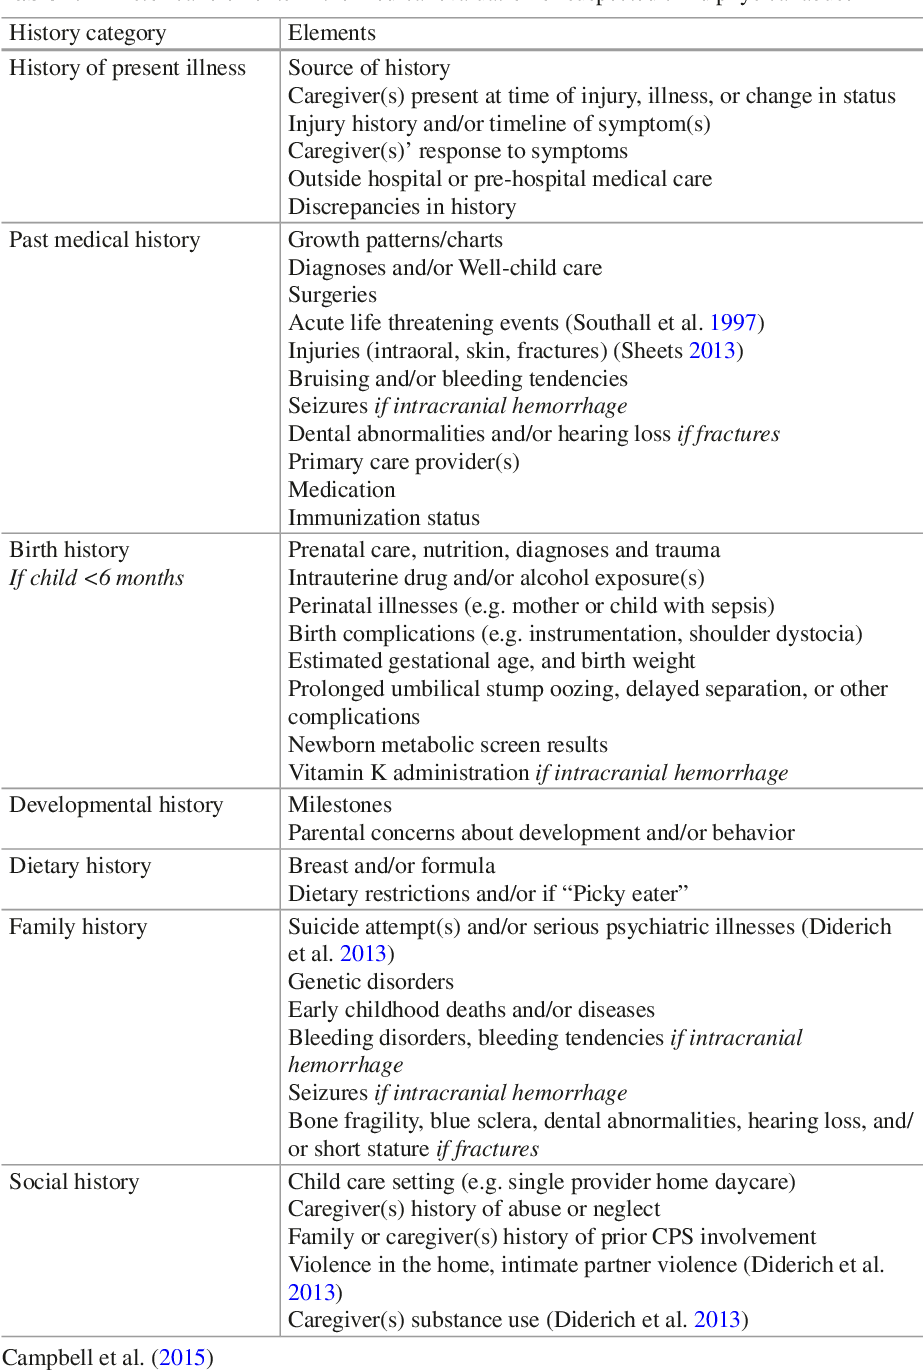
The History of Present Illness is the narrative backbone of any clinical encounter. It tells the story of why the patient is here right now. Most people think it is just a chronological summary of symptoms. That is not accurate. It is a structured argument for why the patient needs evaluation and what diagnoses you are considering. When you write it well, it actually guides your differential diagnosis. When you write it poorly, you leave yourself exposed on documentation reviews.Hpi History Of Present Illness
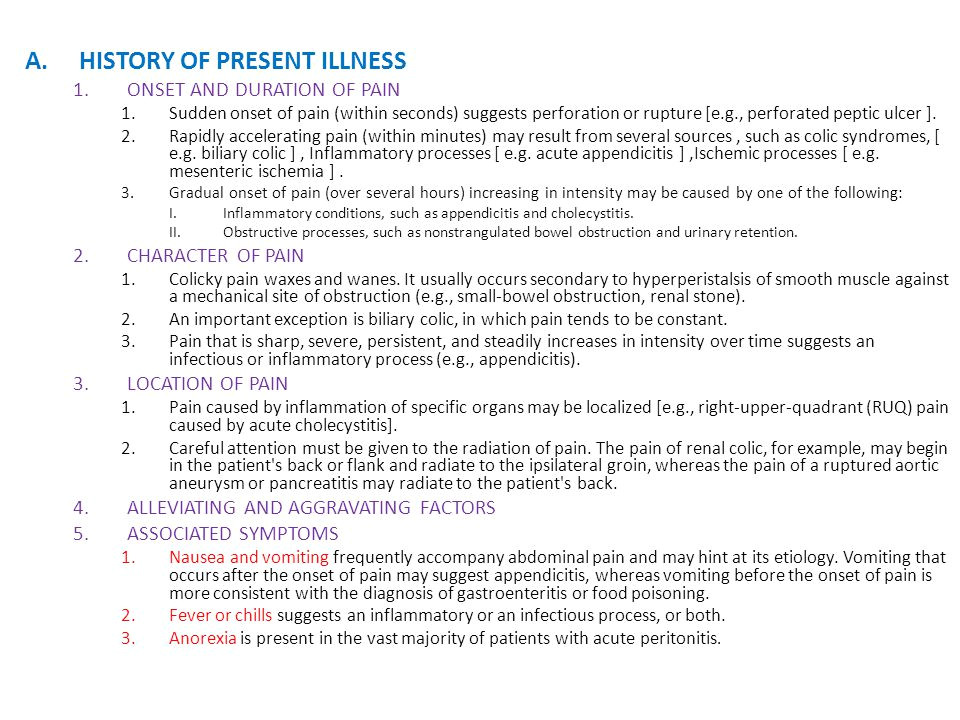
The core components are symptom description, timing, severity modifiers, and associated features. You need to answer where the symptom started, how it progressed, what makes it better or worse, and what else the patient is experiencing alongside it. Think of it as answering the same questions a good historian would ask before you even touch the patient. I used to see residents write "patient presents with abdominal pain" and then move on to the review of systems like nothing happened. That is not an HPI. That is a placeholder. The difference between an acceptable HPI and a solid one usually comes down to whether you capture the qualitative descriptors correctly. Burning versus sharp versus crampy versus dull changes the entire diagnostic pathway. Not the intensity scale. The quality of the pain itself. One specific problem I ran into repeatedly involves patients with atypical presentations of myocardial infarction. A woman came in describing "indigestion" that started three days ago. She had no chest pain. No shortness of breath. No diaphoresis. If I had written "chief complaint indigestion, HPI benign" I would have made a mistake. I described the symptom as epigastric pressure, noted its relationship to eating and exertion, documented the associated nausea and fatigue, and flagged the radiation to the jaw as a concerning feature. Troponin was elevated. She had a silent MI with atypical symptoms. The HPI is where you connect those dots before the lab results come back. If you do not document the reasoning in the narrative, nobody knows why you ordered a cardiac workup for indigestion.
The Method I Actually Use
Start with the chief complaint as the opening sentence. Then move chronologically from onset to present. For each symptom, answer SOCRATES or OLDCARTS depending on your institutional preference. Onset, location, duration, character, aggravating factors, radiation, timing, severity. Do not skip any of them unless the symptom genuinely has no relevant data for one of those elements. If you skip it, document why you skipped it. "No radiation reported by patient" is better than leaving radiation absent from the record entirely. Then document what you ruled out or considered. This is the part most people miss. After describing the presenting symptom, write a brief line about plausible alternative diagnoses and why they are less likely. "Gastroesophageal reflux considered but less likely given absence of positional component and response to antacids." This is not padding. This is defense documentation. It shows clinical reasoning at the point of care. Current medications should appear in the HPI if they are relevant to the present illness. I do not defer them to the medication list section. If the patient is on a beta blocker and presents with tachycardia, mentioning that in the HPI changes the interpretation of the heart rate. Same with NSAID use in abdominal pain cases. Document the medication context right where the symptom is described.
Pitfalls That Cost People Money
The biggest issue I see is template dependency. Copy-pasted HPIs that do not match the actual encounter are the number one reason denials happen. A student wrote an HPI describing right lower quadrant pain and a positive Rovsing sign for a patient who came in for a dermatology follow-up on psoriasis. The EHR auto-populated the surgical template from the previous day. Caught it before signing. These errors are not rare. They happen weekly in every hospital I have worked in. Another common mistake is conflating past history with present history. "Patient has a history of hypertension since 2015" belongs in the past medical history section. In the HPI, you mention hypertension only if it is directly relevant to why the patient is in front of you today. Overcrowding the HPI with chronic conditions dilutes the narrative and makes the actual acute issue harder to find. Reviewers and auditors can scan quickly when the format is clean. They cannot when everything is lumped together. Severity scaling is another area where people get sloppy. Using the patient's own words for severity is far more defensible than assigning your own numeric rating. If the patient says "it hurts enough that I cannot walk," write that. If you write "pain 8 out of 10," you are interpreting their experience through your own scale. The patient's direct descriptor is more useful clinically and more defensible legally.
Get the Full Details

When HPI Documentation Fails
There are scenarios where a traditional narrative HPI does not work well. Patients with fluctuating symptoms, intermittent presentation, or unreliable historians produce HPIs that read as contradictory. In those cases, a timeline format with specific dates and objective findings performs better than a flowing paragraph. I switched to bullet-point chronology for complex chronic pain patients and saw my documentation time decrease while completeness increased. The tradeoff is that some electronic health record systems do not render bullet formats cleanly when transferred between departments. Be aware of your EHR limitations before deviating from standard prose. Also worth noting: the HPI alone cannot compensate for incomplete physical examination findings. A beautifully written HPI with a deficient exam section will still fail audit review. These two sections support each other. The HPI justifies the exam. The exam validates the HPI. Write them together as connected documents, not separate tasks.
Quick Practical Checklist
Before signing any HPI, verify these items exist in the narrative: identifying characteristic of the primary symptom, temporal progression, at least one modifying factor, associated symptoms actually present, and the clinical reasoning behind your initial differential. If any of those five are missing, the HPI is incomplete regardless of word count or template compliance. Good HPI writing takes practice. The structure feels rigid at first but it becomes automatic after enough encounters. The payoff is documentation that protects you, guides your colleagues, and actually reflects what happened during the visit. That is the point of it.