Where Your Kidneys Actually Sit
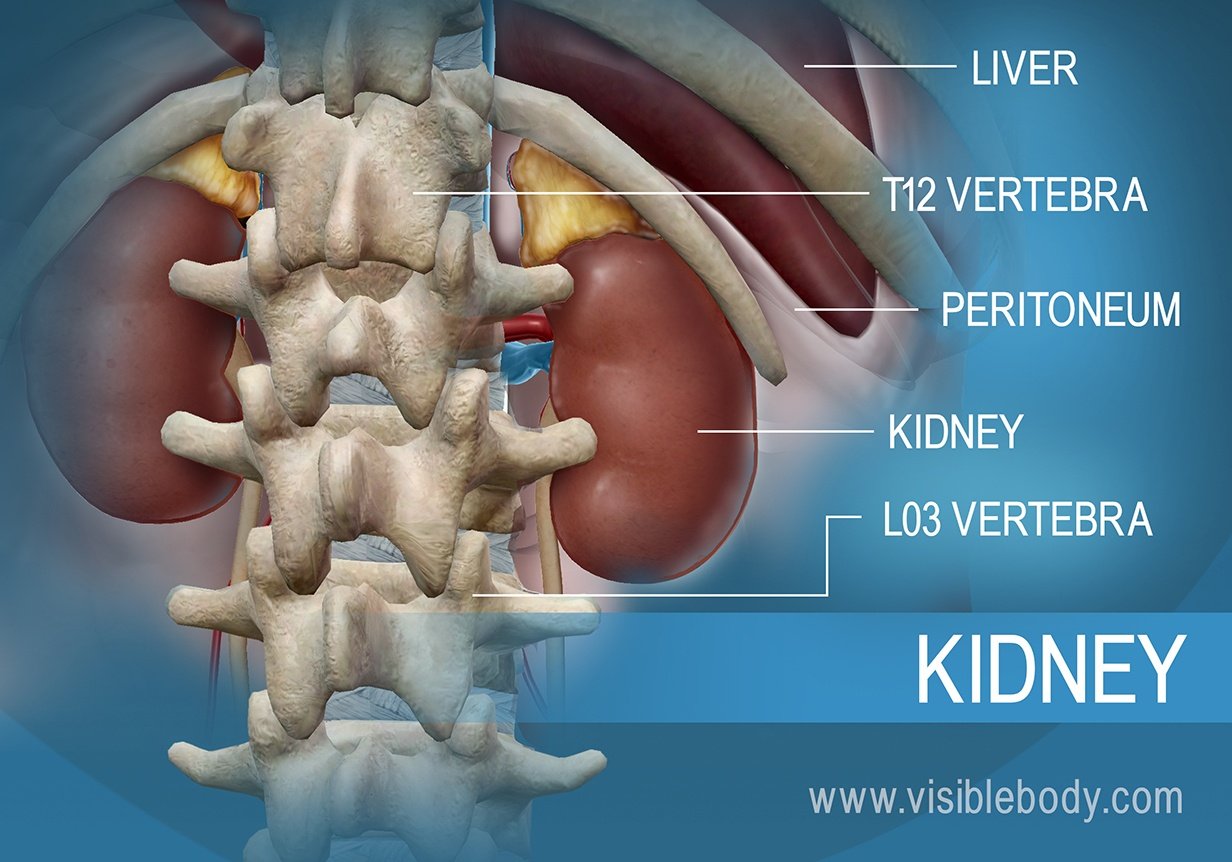
The kidneys sit retroperitoneally on the posterior abdominal wall, roughly between T12 and L3. They're not in the middle of your belly like most people assume. They're pressed up against your back muscles, tucked under the lower rib cage on either side of the spine. The right kidney sits slightly lower than the left because the liver is squatting down on that side. This asymmetry matters more than you'd think if you're doing palpation exams or interpreting imaging. I spent way too long trying to locate kidneys by palpation during my early clinical rotations. Here's the thing nobody tells you: the kidneys are surprisingly difficult to feel in normal-weight patients. You have to position the patient supine, have them take a deep breath and hold it, then press deeply just below the costal margin. Even then, you might only catch the lower pole of the left kidney. The right one is even harder due to the liver shielding it. I found that asking the patient to roll slightly onto their side while you press can sometimes displace the organ just enough to get a handle on it. For anyone studying this for exams, here's a practical trick. Trace the 12th rib. The superior pole of each kidney sits right at the level where that rib crosses the transverse process. If you can identify the 12th rib on a skeleton or a living person, you've basically found the kidney's top edge. The inferior pole lands around the level of the iliac crest on the left and slightly higher on the right. This is consistent enough that it becomes a reliable landmark once you practice it a few times.
There's a common misconception that kidneys sit in the flanks like a pair of beans in a saddle. They don't. They're more posterior than that. If you're palpating from the front, you're pressing through the peritoneal cavity, bowel loops, and fat before you even reach the anterior surface of the kidney. That's why flank tenderness tests like costovertebral angle tenderness are clinically useful. When you tap the CVA, you're hitting the kidney directly through its posterior surface without any intervening structures. It's a surprisingly sensitive maneuver for pyelonephritis or renal calculi, though obviously not specific to either condition. From an imaging perspective, I've seen more students and even some residents misidentify the kidneys on ultrasound because they're looking too far anteriorly. Start the probe in the paraspinal region along the posterior costophrenic recess. The kidney will appear as a bean-shaped structure with a characteristic echogenic renal sinus and hypoechoic cortex. If you're searching from the anterior abdomen, you'll get bowel gas interference and waste half an hour before you find anything. Learning the posterior approach changes everything. The vascular anatomy tied to kidney location is another area where textbook diagrams fall short of reality. The renal arteries branch off the aorta at roughly L1-L2, which means they're horizontal rather than angling downward like you might expect. The right renal artery has to cross posterior to the inferior vena cava to reach its target, making it about 1.5 to 2 centimeters longer than the left. This anatomical quirk becomes clinically relevant during surgical approaches or endovascular procedures. A stent placed on the right side needs to account for that longer, more tortuous path. I've seen complications arise from operators treating both sides as symmetric when they clearly aren't.
Lymphatic drainage follows the renal hila to the lateral aortic nodes, which means renal pathology can manifest as tender lymph nodes in that region rather than in the groin where most people expect. This is easily overlooked during physical examination and can be the difference between catching a retroperitoneal tumor early versus missing it entirely on routine screening. If you're using cadaveric dissection to study kidney location, remember that fixation changes tissue texture significantly. Formalin-fixed kidneys are firmer and smaller than live ones, which can make fascial planes harder to distinguish. I learned this the hard way during my first gross anatomy lab when I spent twenty minutes searching for the renal capsule because the tissue had retracted post-fixation. Fresh frozen specimens or in-vivo imaging will give you a more accurate sense of how these structures actually relate to each other in a living patient. The relationship to surrounding structures deserves attention beyond memorization. Anteriorly, the right kidney touches the liver, duodenum, and hepatic flexure of the colon. The left kidney abuts the spleen, stomach, pancreas tail, and splenic flexure. This matters when you're considering surgical access routes or interpreting cross-sectional imaging. A mass on the left kidney might involve the pancreatic tail before you realize it, and right-sided pathology can involve the duodenum in ways that change your surgical planning entirely.
Get the Full Details

One edge case that consistently trips people up is renal ptosis, or nephroptosis. In certain patients, particularly thin young women, the kidney can descend more than two vertebral bodies when moving from supine to upright position. This isn't pathological in itself but it can cause ureteral kinking and intermittent hydronephrosis. I encountered a patient who presented with recurrent flank pain that only appeared when standing for extended periods. Imaging while supine was completely normal. It took an intravenous pyelogram done in both supine and upright positions to catch the displacement. This is one of those situations where standard anatomical descriptions fail you because they assume a fixed position that doesn't always exist in practice. For anyone preparing for practical exams or clinical rotations, the most useful thing you can do is correlate surface anatomy with real imaging. Pull up axial CT scans at different levels and mark where you expect the kidneys to appear. Then switch to coronal and sagittal views. The three-dimensional orientation becomes intuitive faster than you'd expect once you've done this with enough cases. I've found that spending an hour with a good radiology atlas does more for your spatial understanding than another week of reading textbook descriptions. The blood supply variation is another practical consideration. Accessory renal arteries occur in roughly 25 to 30 percent of the population. These usually branch from the aorta below the main renal artery and enter the inferior pole. During nephrectomy or transplant surgery, missing an accessory artery means leaving renal tissue behind or causing ischemic complications. Preoperative CT angiography has made this less of a surprise, but it's still something that catches inexperienced surgeons off guard when imaging isn't available or when anatomy runs counter to what the scan suggested.
Age-related positional changes are worth noting too. In elderly patients with significant weight loss or muscle wasting, the kidneys can shift downward more than expected. A kidney that sits at L1 in a robust middle-aged adult might sit at L2-L3 in a frail elderly patient. This matters for procedures like renal biopsy where needle trajectory and depth are planned based on standard anatomical assumptions. Blaming your technique when you miss because you didn't account for the patient's body habitus is a rookie mistake I made more than once before I started routinely verifying landmarks with point-of-care ultrasound.
Quick Reference Points
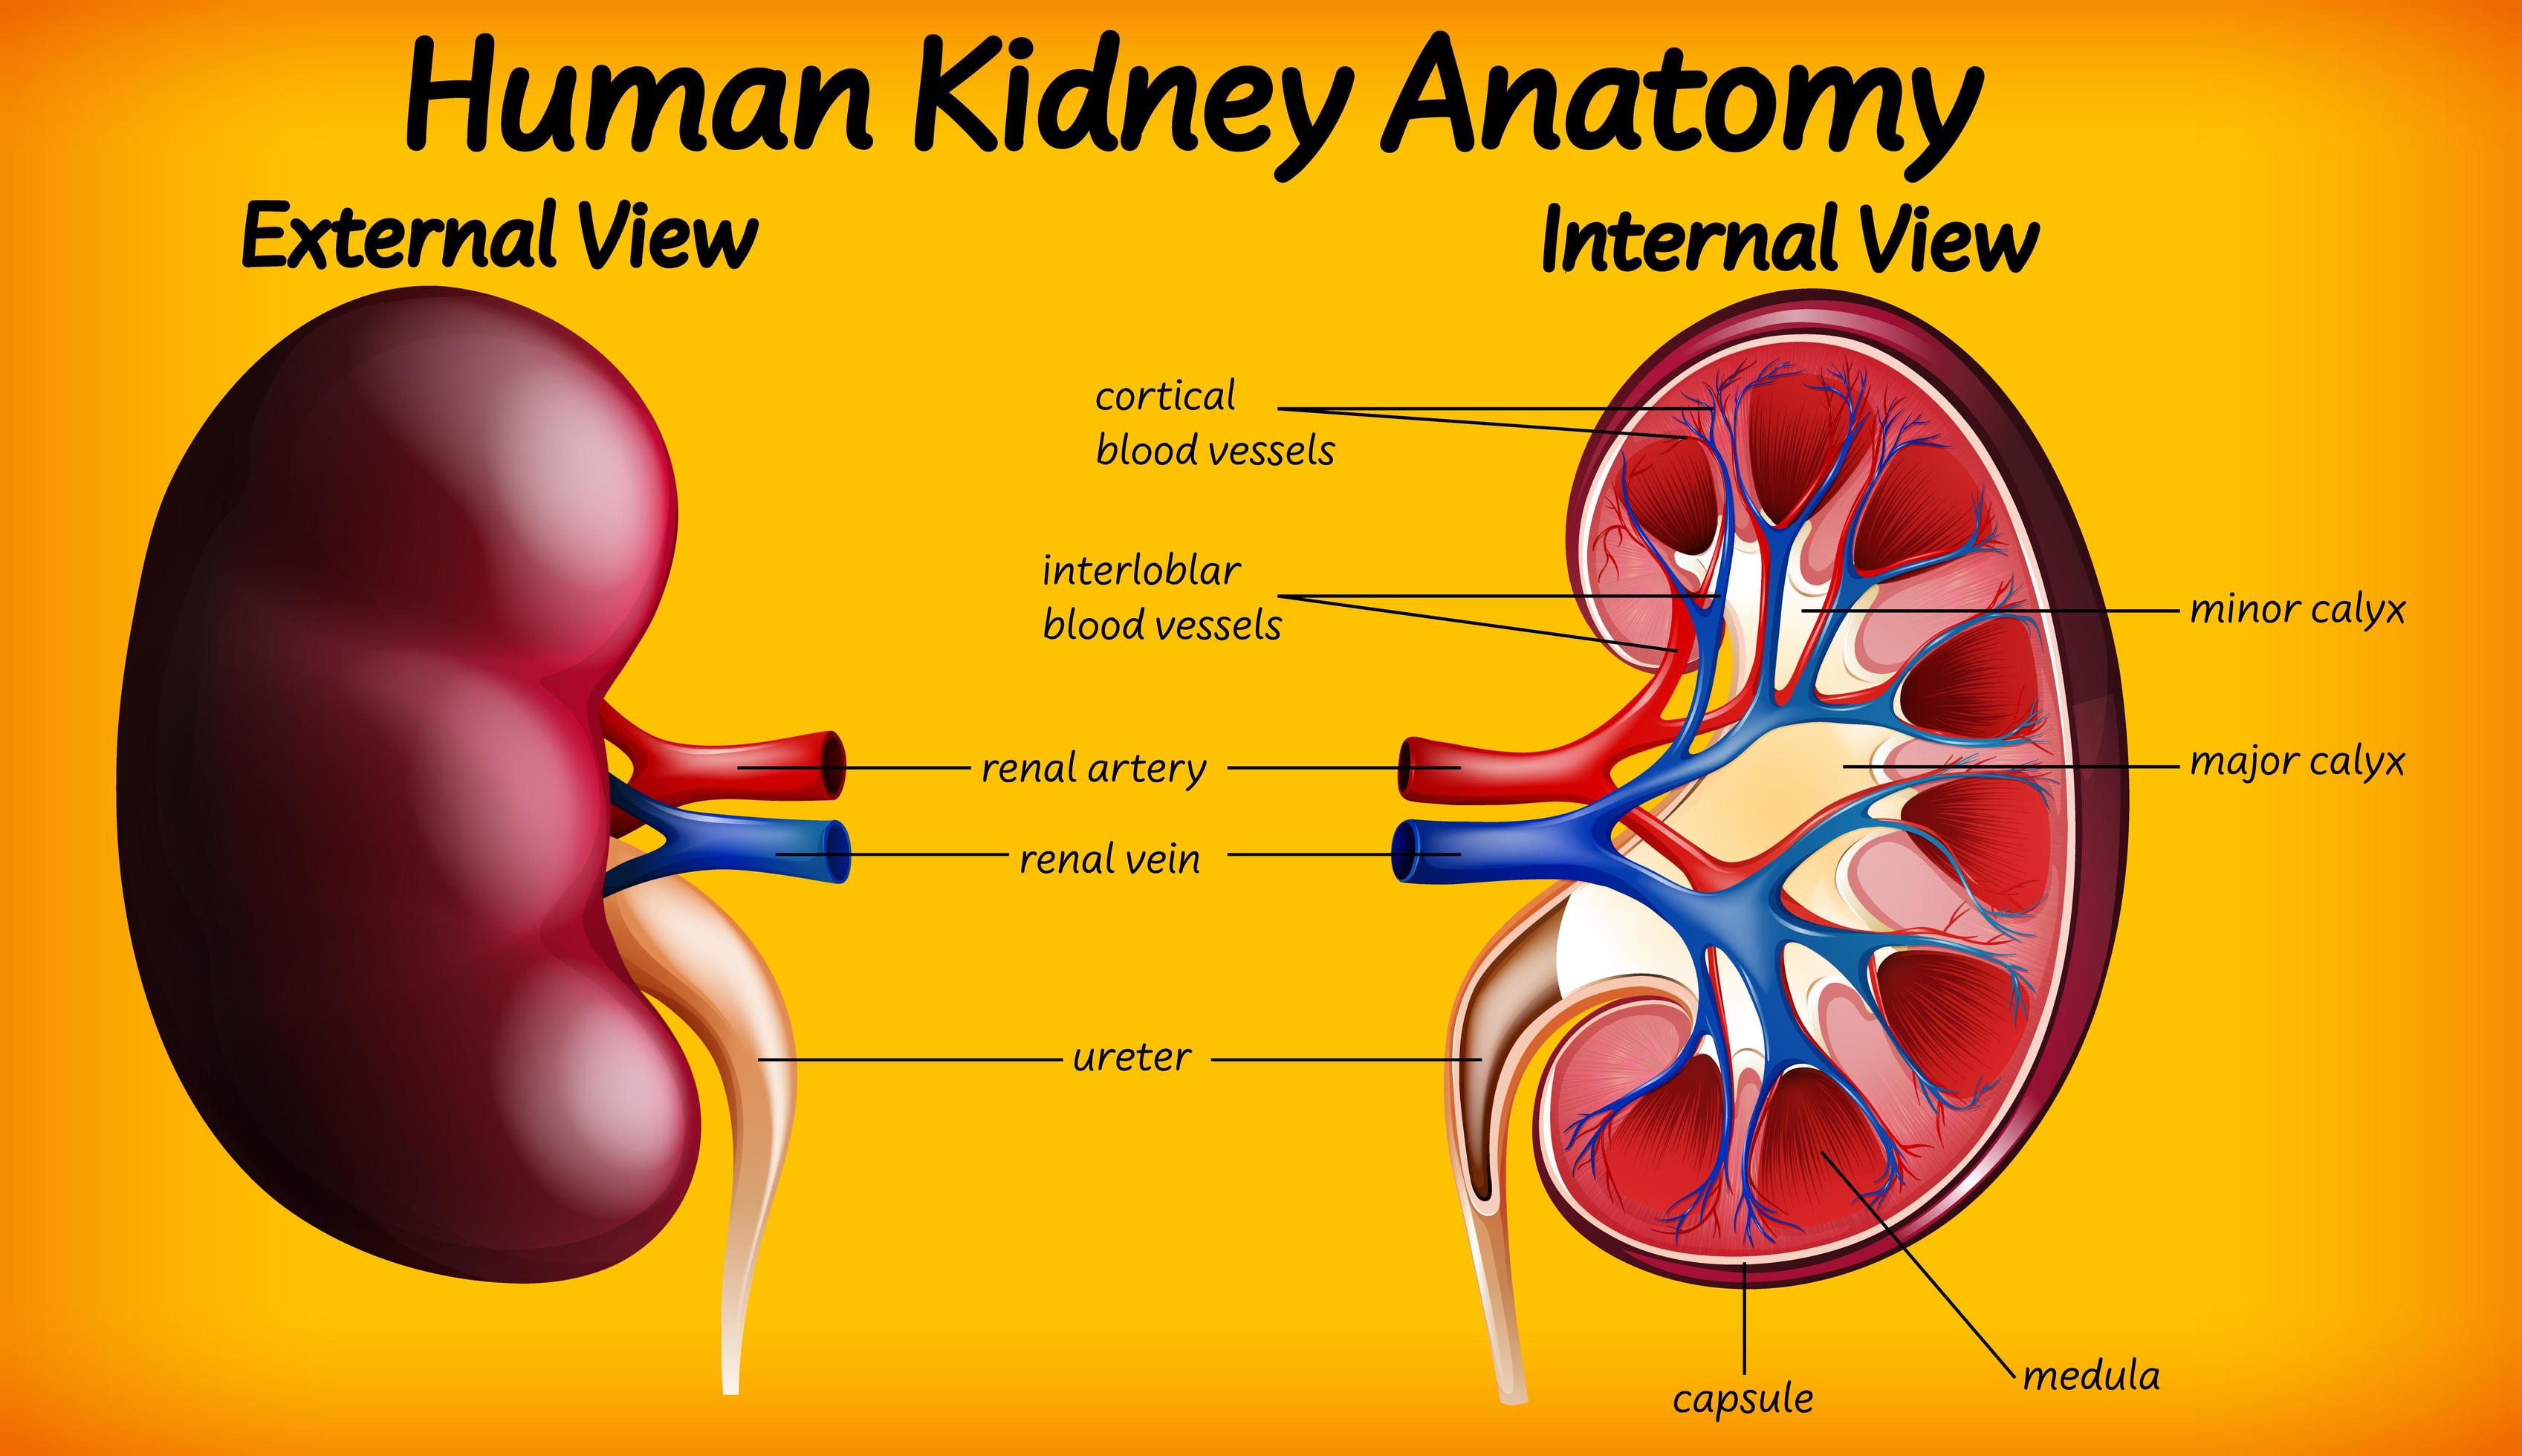
The left kidney sits higher, around T12 to L2. The right kidney sits lower, around L1 to L3. Both rest against the psoas major muscle. The renal hilum faces anteriorly and medially. The renal pelvis transitions into the ureter at the lower pole region. These landmarks hold true in the vast majority of cases, but variation exists and you should always confirm with imaging when it matters clinically. Palpation is unreliable for detecting normal kidneys in most adult patients. Clinical significance usually appears through imaging findings, laboratory abnormalities, or referred pain patterns rather than direct tactile assessment. Don't waste time trying to master a technique that has limited diagnostic yield unless you're specifically training for physical examination skills that will be tested. Understanding the three-dimensional relationships takes practice. Cadaver labs help. Radiology rotation helps more. Watching yourself palpate a colleague while simultaneously reviewing their CT scan on a tablet is about as efficient as it gets for building practical anatomical intuition.