Getting the Posterior View Right When You Actually Need It
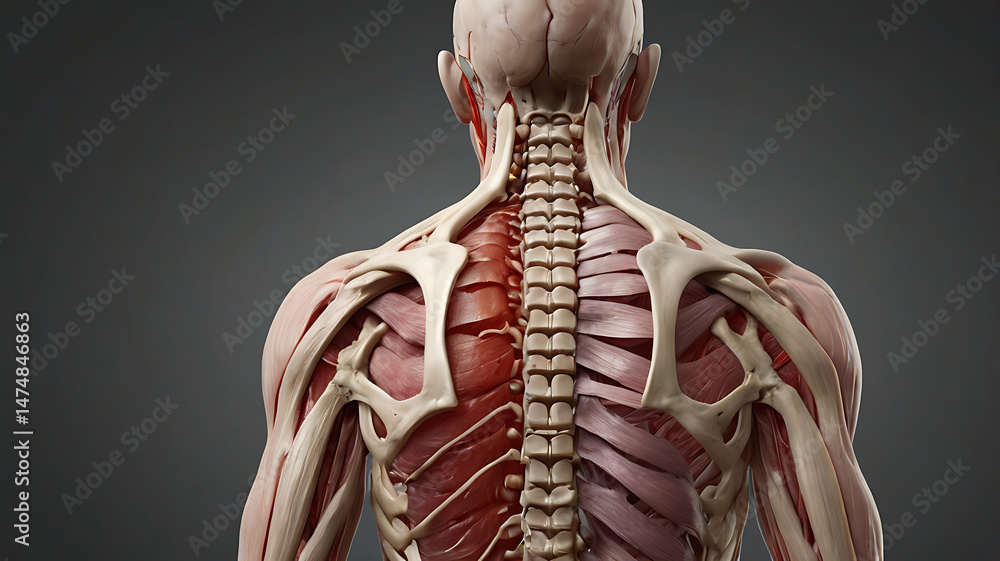
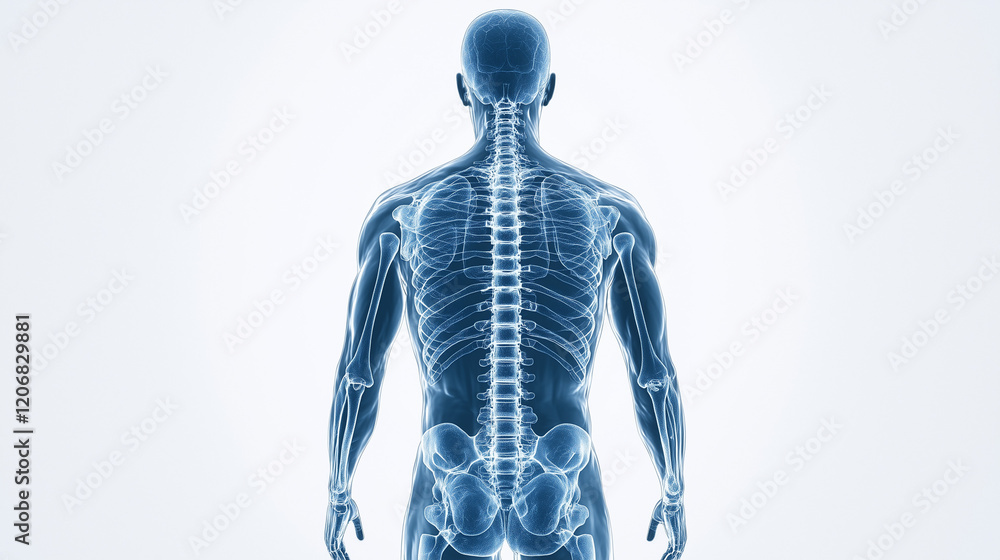
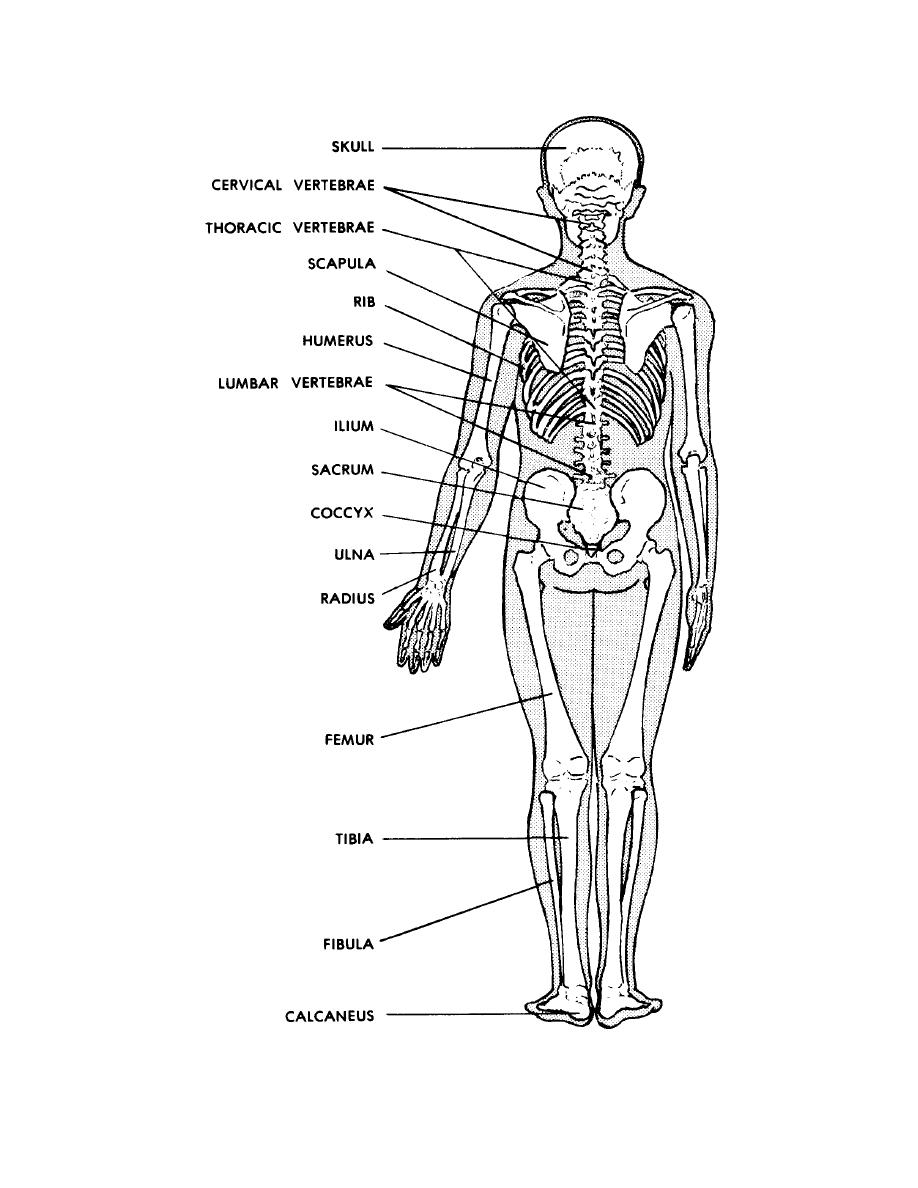
Most people learning anatomy hit a wall when they get to the back. The anterior structures have names you can find on flashcards—rectus abdominis, pectoralis major, biceps brachii. Everyone knows those. The posterior side is where things fall apart. I spent three years doing cadaver lab dissection and still got tripped up on posterior view anatomy because the learning materials assume you already understand 3D spatial relationships from a front-facing baseline. They don't. The posterior view isn't just the anterior view flipped around. That's the first mistake. The muscle attachments, the fascial planes, the way things layer over each other—they shift significantly because of how the body's been adapted for bipedal posture over thousands of years. A deltoid on the front looks nothing like a deltoid on the back, even though it's technically the same muscle. The gluteals are a cluster of three distinct muscles on the posterior that students regularly confuse as one lump. The erector spinae group runs vertically along the spine and is practically invisible from the surface in most people until you're looking at an athletic build or a very lean specimen. Here's what I wish someone had told me during my first year: the posterior view is less about memorizing individual muscles and more about understanding the kinetic chain. Everything in the back connects to everything else. The trapezius doesn't just sit on your upper back—it fans out and interlocks with the latissimus dorsi, the rhomboids, and the teres major in ways that matter for understanding posture, not just passing an exam. When I was studying for my practical exams, I used to draw the posterior view blind on a mannequin, then compare it to actual cadaver photos. The gap between what I thought I knew and what was actually there was enormous.
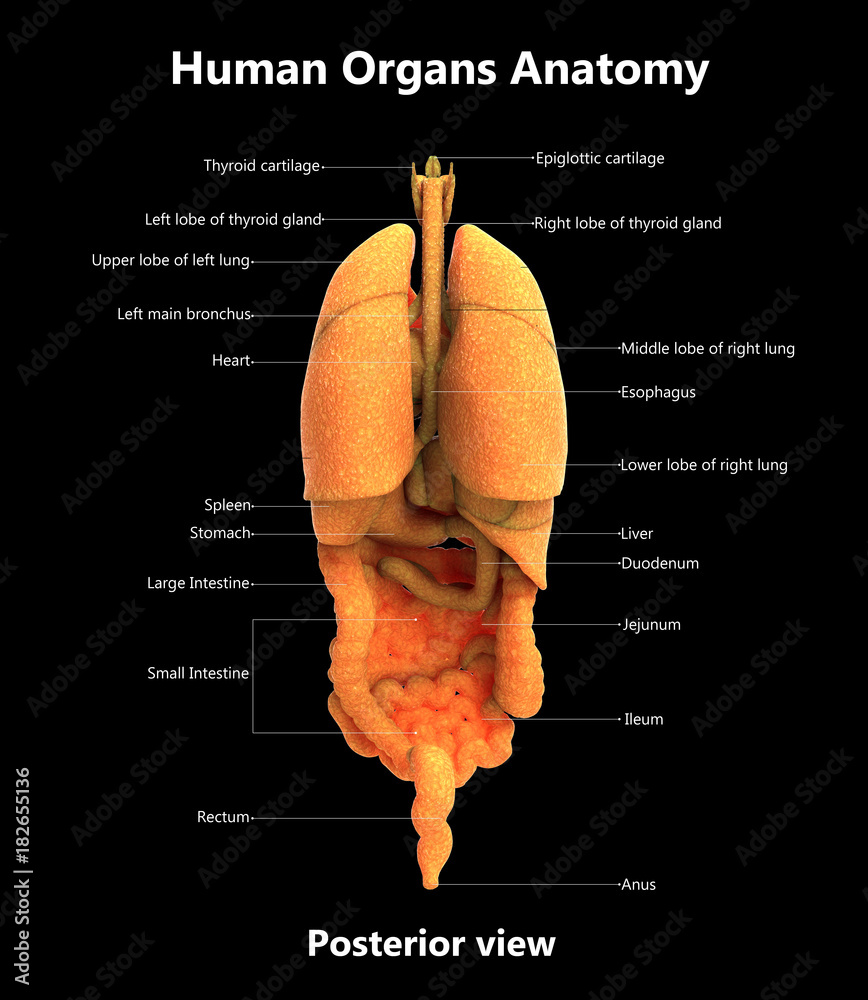
One thing that genuinely surprised me when I started working with imaging data: the superficial posterior chain is dramatically different from the deep posterior layer. You've got the skin, subcutaneous fat, and the superficial fascia sitting on top of the erector spinae group, which sits on top of the transversus abdominis and multifidus. Most atlases show you one or the other. Very few show you how they actually relate to each other in a living body. I once spent two weeks trying to understand why my MRI cross-references weren't lining up with the textbook diagrams. Turns out the textbooks were showing a dissected specimen with the superficial layers removed, and I was trying to map that onto radiological images where everything was still in place. That mismatch cost me a lot of time. The workaround was simple once I figured it out: I started using a 3D anatomy app like Complete Anatomy or Visible Body alongside the atlas, toggling layer visibility on and off so I could see how the posterior structures stacked in three dimensions.
What You Actually Need to Know
If you're going to work with the posterior view—whether that's for medical school, athletic training, physical therapy, or animation—you need to know these regions inside out: The head and neck posterior: The occipitofrontalis has its posterior belly right there at the base of the skull. The sternocleidomastoid you already know from the front, but from the back you'll see the splenius capitis and the splenius cervicis underneath it. These are the muscles that control head rotation and extension. They're easy to miss because they're buried under the trapezius unless you're looking at a very lean person or a dissection. The upper back: This is where the trapezius lives. It's the largest superficial muscle in the entire posterior view. It covers almost everything else except the latissimus dorsi lower down. The rhomboids are underneath the trapezius and connect the scapula to the spine. The levator scapulae runs along the side of the neck down to the shoulder blade. If you can only memorize three muscles here, make it these three. They're clinically relevant for posture issues and shoulder dysfunctions that show up constantly in practice.
Get the Full Details
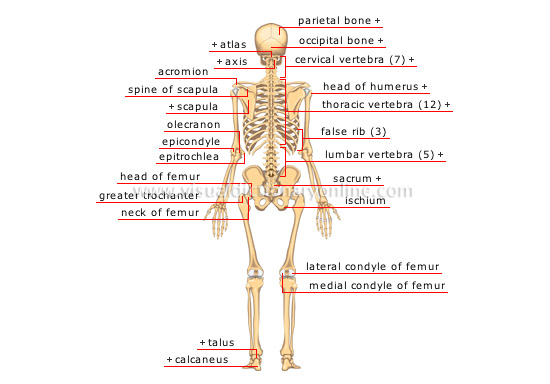
The lower back: The erector spinae is your main structure here. It runs the entire length of the spine and consists of three columns: the iliocostalis, longissimus, and spinalis. The quadratus lumborum sits deeper and is often overlooked but is critically important for lateral flexion and core stability. I've seen physical therapists miss lumbar issues because they were too focused on the erector spinae and ignored the quadratus lumborum entirely. It's a real problem in clinical settings. The arms posterior: The triceps brachii is straightforward—three heads, easy to identify. The anconeus is a small triangular muscle near the elbow that's frequently forgotten but matters for elbow stability. From the posterior view, the extensor muscles of the forearm are all visible along the lateral and posterior aspects. These are the muscles responsible for wrist and finger extension, and they're commonly involved in conditions like tennis elbow, which is actually lateral epicondylitis affecting the extensor common tendon. The legs posterior: The hamstrings—biceps femoris, semitendinosus, semimembranosus—are the big ones here. They originate at the ischial tuberosity and insert along the tibia and fibula. The gastrocnemius is the prominent calf muscle you can see from behind. The soleus sits underneath it. The plantaris is a tiny muscle that almost nobody notices but shows up in anatomy exams constantly. I once failed a practical because I couldn't identify the plantaris on a cadaver. It's barely two centimeters long. Don't be me.
The Pitfalls That Trip Everyone Up
The biggest issue I see is that people treat posterior view anatomy as a separate chapter instead of a perspective shift. The muscles are the same ones you learned anteriorly, just viewed from behind with different attachments visible. When you stop thinking of them as separate and start thinking of them as the same structures from a different angle, everything gets clearer. Another problem is the fascial layers. The thoracolumbar fascia is a thick sheet of connective tissue that covers the deep muscles of the lower back and acts as an attachment point for the latissimus dorsi, the abdominal muscles, and the gluteus maximus. It's essentially the central hub of the posterior kinetic chain. Most students skip over it because it's hard to see in diagrams and doesn't have a flashy name. In practice, it's one of the most important structures for understanding lower back pain and core mechanics. Here's a counter-intuitive one: the gluteus maximus is actually the largest muscle in the human body, not the quadriceps or the masseter like most people guess. From the posterior view, it dominates the hip region. But here's what the textbooks don't emphasize enough—it's not just about hip extension. It's the primary muscle responsible for maintaining upright posture against gravity. When it's weak or inhibited, everything downstream (the hamstrings, the lower back, the knees) starts compensating. I've seen patients with chronic lower back pain whose root cause was a dormant gluteus maximus. Activating it through targeted exercises resolved the back pain without a single intervention on the back itself.
How to Actually Study This Stuff
Stop reading atlases passively. Draw the posterior view from memory on a blank piece of paper. Then check your work. The gap between what you drew and what's correct will show you exactly what you don't know yet. Do this every day for two weeks and your retention improves dramatically. Use palpation. Find your own scapula from the back. Feel your own spine. Run your fingers along your trapezius and notice where it inserts into the clavicle and the scapula. Do the same for the latissimus dorsi—it's much wider than people expect and attaches from the lower spine all the way up to the humerus. Palpating your own body while you study makes the anatomical relationships stick in a way that flat images never will. If you're working with imaging—MRI, CT, ultrasound—the posterior view requires a different mental model than cadaver-based study. Imaging shows you cross-sections and slices, not surfaces. I found that practicing with axial and sagittal views alongside the standard posterior view made a huge difference. Start with the axial slices at the lumbar level and work your way up. Each slice gives you a different piece of the posterior puzzle. Within a month of doing this consistently, I could mentally reconstruct the full posterior anatomy from any single cross-section.
What This Approach Doesn't Do Well
The posterior view as traditionally taught is pretty static. Real bodies move, and muscles change shape, length, and tension depending on position. A relaxed posterior view looks completely different from an engaged one. The trapezius, for example, flattens out when your shoulders are relaxed and bunches up noticeably when you shrug. If you're only studying the relaxed position, you'll be confused when you encounter a dynamic situation—whether that's in a clinical assessment, a sports performance context, or animation work. Also, body composition matters enormously. In a person with higher body fat, especially around the back and glutes, many of the key posterior landmarks become obscured. The spinous processes, the scapular borders, the iliac crest—these are all critical reference points that disappear under tissue. I had a student once struggle for months because all her reference images were of lean specimens, and then she couldn't identify anything on an average body type. It's a real limitation of most anatomy education. For people who need this for clinical or athletic purposes, I'd recommend supplementing any standard atlas with dynamic ultrasound or motion-capture resources. The field of functional anatomy is still not well-represented in most introductory materials, and relying solely on static diagrams will leave gaps in your understanding that show up when you actually need to apply it.
There are some solid resources available online—Human Anatomy Atlas by Visible Body, Complete Anatomy, and the open-source Kenhub platform all have good posterior view modules. For free options, the Open Anatomy project and the Histology Guide both have detailed posterior region coverage if you know where to look.