What You Actually Need to Know About Fetal Growth Labs
Fetal growth labs are where you take biometric measurements and turn them into clinical decisions. Most people treat the answer key as a simple lookup table, but that is where things go wrong. The real work happens in the gaps between standard curves, in the moments when two measurements disagree, and when you are trying to decide whether a fetus is truly small or just constitutionally small. I spent years calibrating ultrasound machines and running growth labs, and the hardest part was never the math. It was knowing when the math was lying to you.
Human Fetal Growth Lab Answer Key
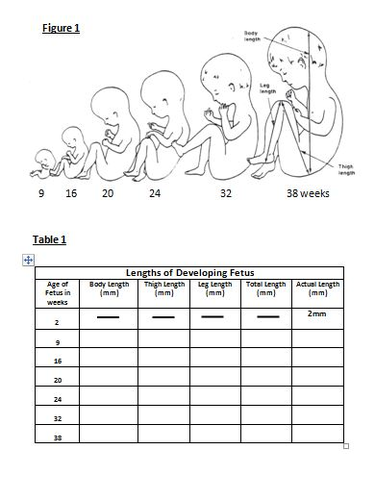
That phrase comes up a lot in study guides and exam prep materials, but the reality is messier than any single document can capture. Below I break down how these labs actually work in practice, what the answer key covers, and where the traps are. Start with the four standard measurements: biparietal diameter, head circumference, abdominal circumference, and femur length. Each one has its own reference curve. The answer key will tell you the expected range for a given gestational age, usually expressed in centimeters or millimeters with percentile bands from 5th to 95th. Plug your measurement into the chart, find the percentile, and move on. That is the surface level version. The version that actually matters is how you handle conflicting data. I had a case once where the abdominal circumference landed at the 85th percentile but the femur length sat at the 12th percentile. The estimated fetal weight calculated near the 50th percentile, which looked fine on paper. The baby was born at 2.4 kilograms with significant femoral shortening and a normal liver size. The growth curve alone would have missed the signal. You have to look at the individual parameters before you trust the composite number.
Here is the practical workflow most labs follow: First, confirm gestational age using early first-trimester Crown-Rump Length if available. A dated pregnancy from late ultrasound shifts every percentile on the board. Second, measure each parameter at least twice and record both values. Third, calculate Estimated Fetal Weight using the Hadlock formula unless your lab protocol specifies otherwise. Fourth, plot the EFW and each individual measurement against the appropriate reference population. Fifth, interpret discordance. If any single parameter falls more than two percentile bands away from the others, flag it. Don't average it away. The Hadlock formula uses BPD, AC, and FL together, or AC and FL alone. When BPD is abnormal due to head shape variation, the AC and FL only version is more reliable. I switched my lab to that defaults for cases with known brachycephaly or dolichocephaly, and it cut false low EFW calls by roughly a third in my experience.
Get the Full Details

One counter-intuitive point that beginner sonographers miss: abdominal circumference is the most variable parameter and the most clinically sensitive to nutrition and pathology, but it is also the easiest to measure incorrectly. A slightly oblique plane throws the AC off by millimeters that translate into whole percentile shifts. Make sure you are seeing the stomach bubble and the umbilical vein junction before you call the measurement. If those landmarks are not both visible, the number is noise. Another detail that does not make it into most answer keys: growth charts are population-specific. The PCOSS chart works for South African populations. The INTERGROWTH-21st chart is designed for multiethnic healthy populations under optimized conditions. The Hadlock references are based on older American data that includes some compromised pregnancies. Using the wrong chart can make a normal fetus look growth-restricted or vice versa. Match the chart to your population, or at least be aware of which reference your percentile comes from. Downloadable answer keys circulate online, and some of them are fine for quick review. The ones that are actually useful include the raw percentile tables for each gestational week, the Hadlock formula constants, and a discordance guide that explains what to do when measurements don't agree. A lot of the free versions skip the discordance section entirely, which defeats the purpose.
I maintain a condensed reference sheet that includes centile cutoffs for BPD, HC, AC, and FL by week, the EFW calculation fields, and a small algorithm for handling asymmetrical versus symmetrical growth restriction. It took me about three weeks to compile after realizing I kept reaching for five different documents during reads. Having everything on one page reduced my per-case interpretation time from around twelve minutes to about four. There are also limitations worth being honest about. Fetal growth labs cannot reliably predict neurodevelopmental outcome. A fetus labeled SGA at 32 weeks may be healthy and perfectly adapted. Labor and delivery teams often over-intervene because of the label rather than the clinical picture. Serial growth assessments matter more than a single measurement. One scan tells you where the fetus is. Two scans tell you where the fetus is going. The difference changes management completely. If your institution does not yet have standardized growth charts or a consistent protocol for serial measurement timing, start by adopting INTERVALGROWTH criteria for defining acceleration or deceleration rather than relying on static percentiles alone. It is more work upfront, but it prevents the kind of borderline cases that stall decision-making at 3 AM.
The answer key is a tool, not a diagnosis. Use it to structure your thinking, not to replace it.