The Cervical Region Doesn't Care About Your Textbook Diagrams
Seven vertebrae. That's the easy part everyone memorizes. C1 through C7, from the skull down to the thoracic junction. But if you've ever tried to actually work with Human Neck Bones Anatomy — whether that's imaging, surgery prep, or even just understanding chronic pain referrals — you've already noticed that the diagrams lie to you in very specific ways. I spent three years reading cervical CT scans for a orthopedic radiology group. Learned more from the bad ones than the good. The ones that made you stop and stare.
Understanding Human Neck Bones Anatomy Through Real Cases
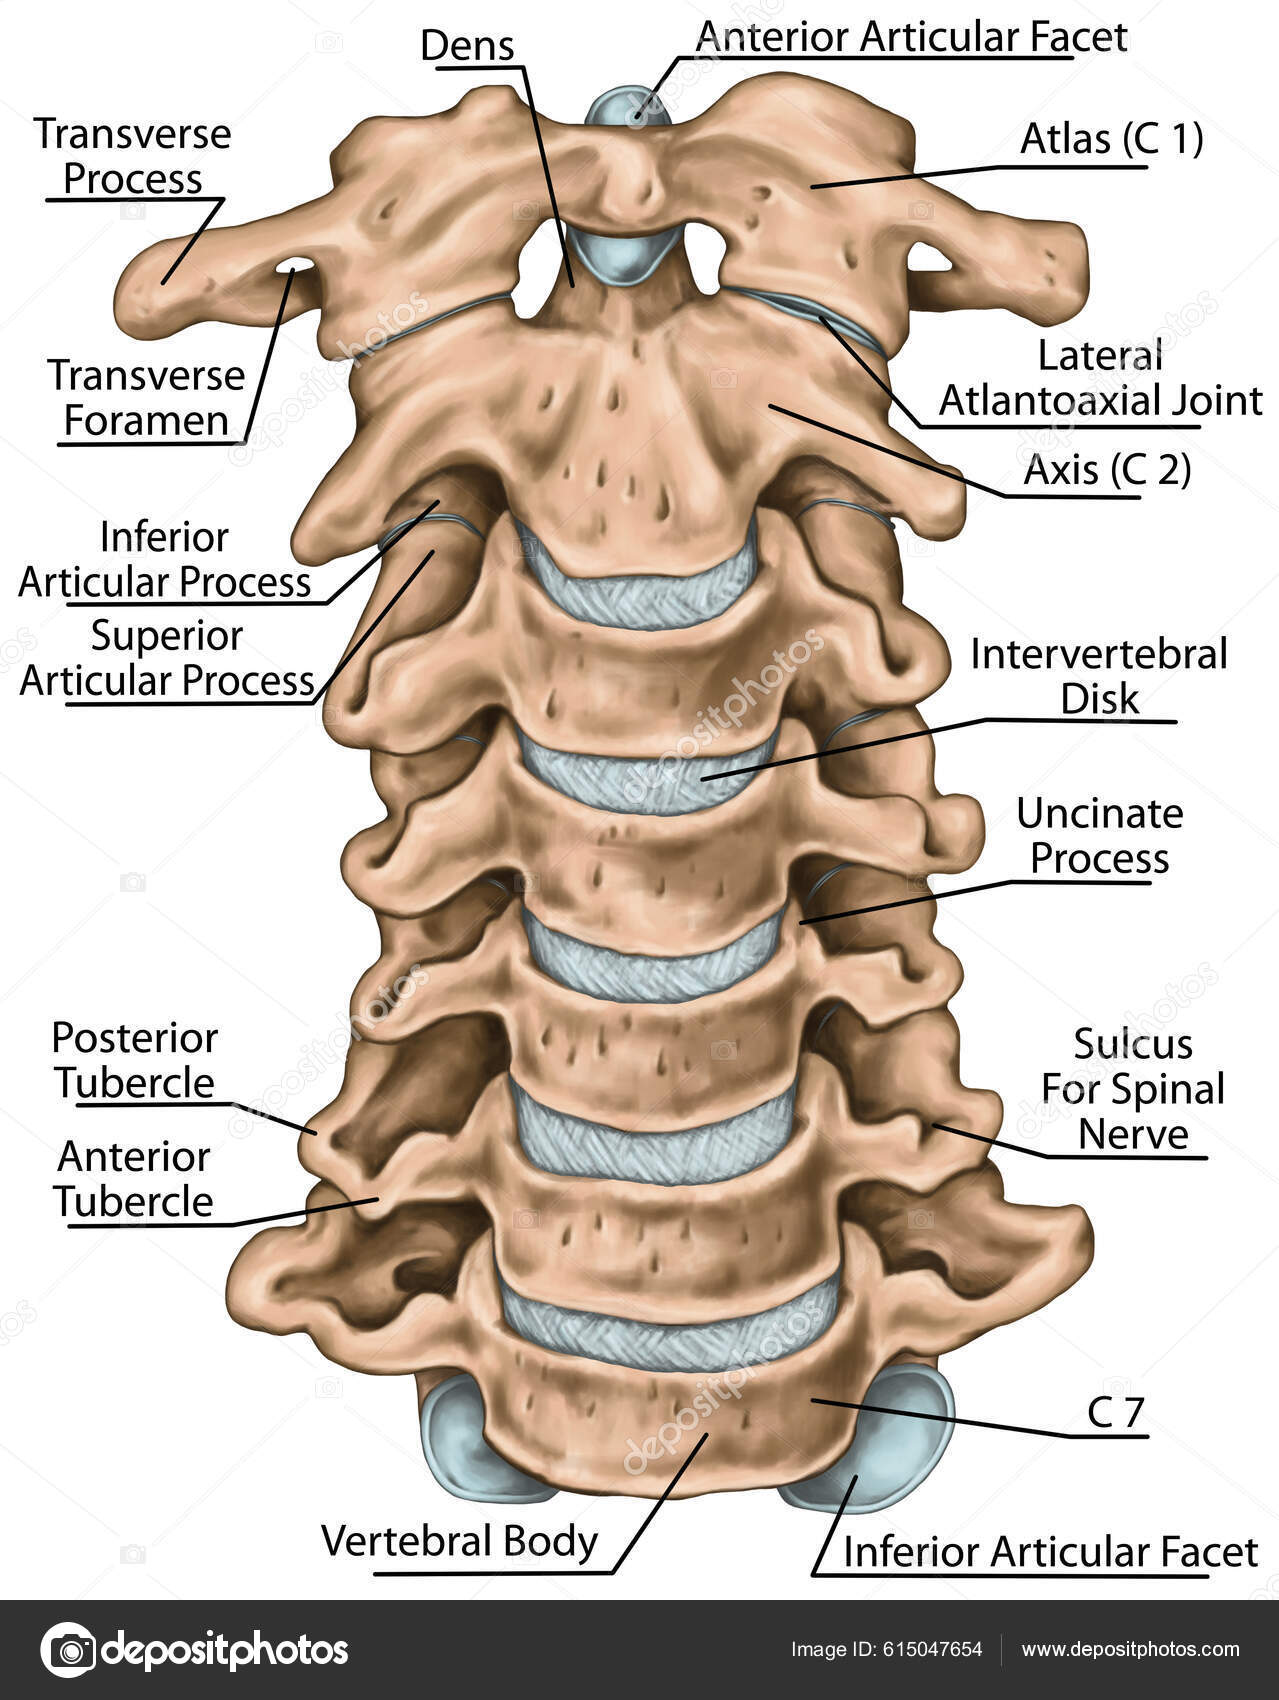
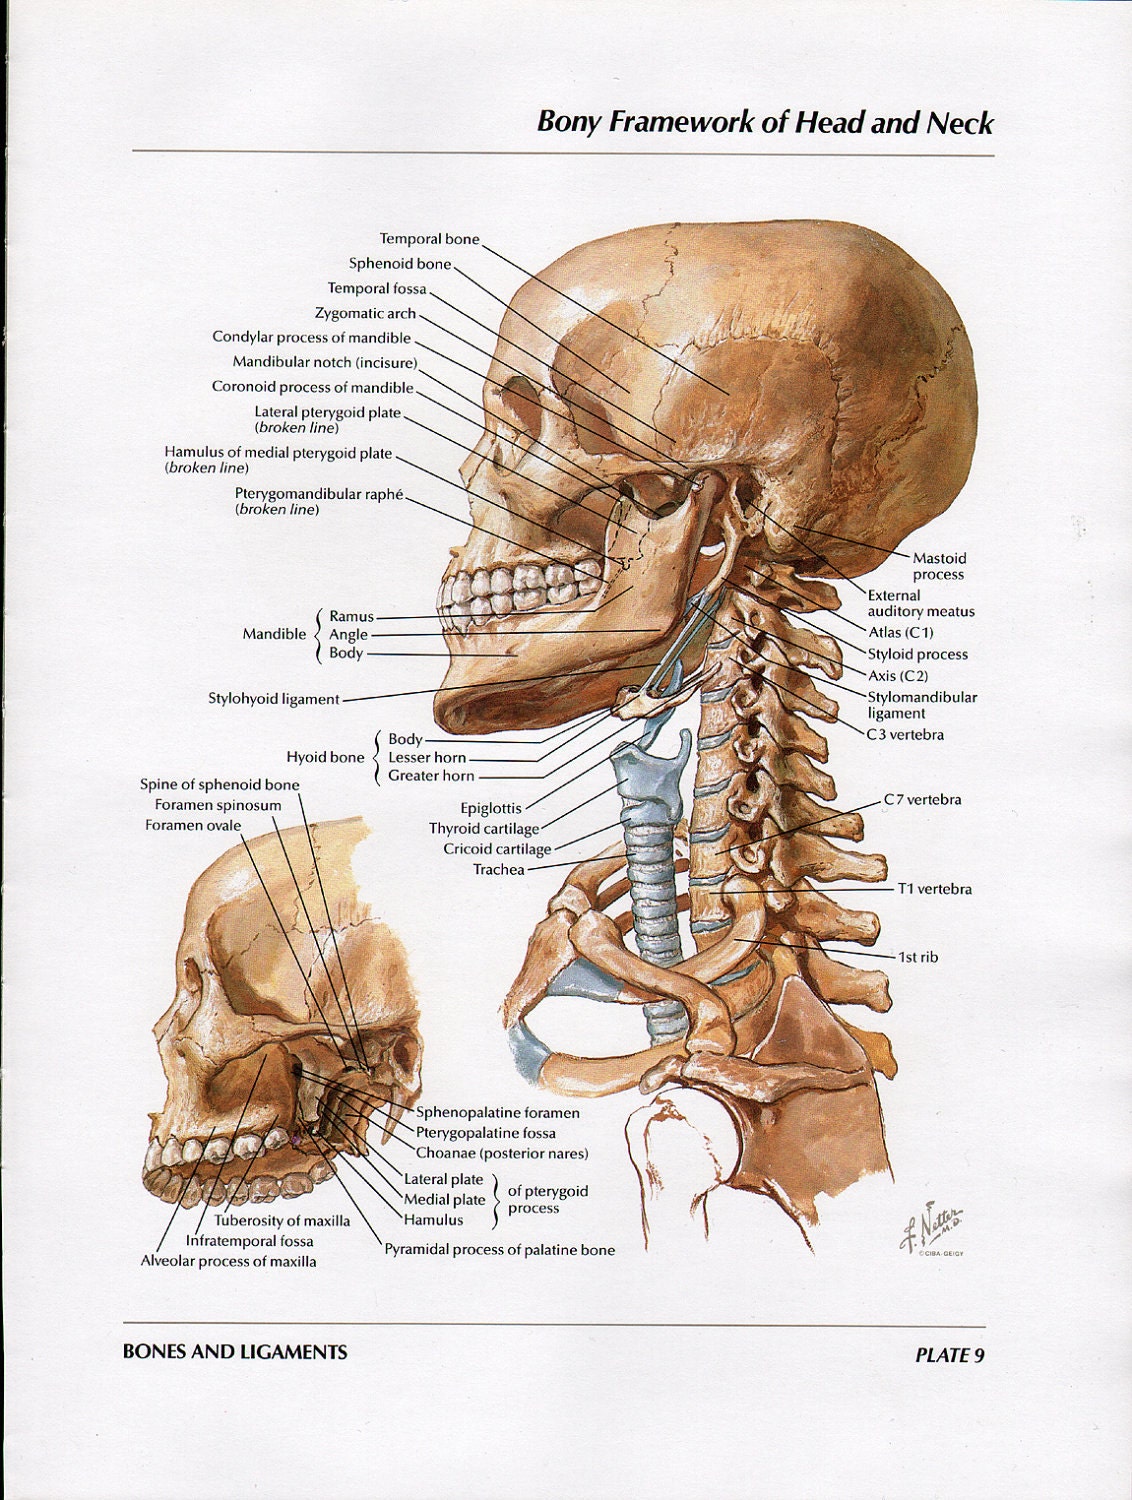
Let me start with something most people get backwards. The atlas (C1) and axis (C2) aren't really "neck vertebrae" in the same way C3 through C7 are. C1 has no body. It's a ring. C2 has the dens, that tooth-like projection that acts as a pivot point. Together they handle roughly 50% of your neck's rotational range. The rest of the cervical spine — the subaxial spine, as we call it — handles flexion, extension, and lateral bending. The intervertebral foramina are where things get interesting and where beginners consistently mess up their spatial reasoning. Each nerve root exits above its corresponding vertebra, except C8, which exits between C7 and T1. So a C5-C6 disc herniation compresses the C6 nerve root, not C5. This matters when you're localizing symptoms or planning a surgical approach. Here's a concrete example from my time in the reading room. We had a patient presenting with right-hand weakness and numbness in the thumb and index finger. Standard teaching says that's C6 radiculopathy. The MRI showed a moderate C5-C6 disc protrusion. Seemed straightforward. But when I traced the actual course of the nerve root through the neural foramen at that level, it was just touching the disc without meaningful compression. Meanwhile, at C6-C7, there was severe foraminal stenosis from uncovertebral joint hypertrophy — something you'd miss if you only looked at disc spaces. The patient's symptoms matched C7, not C6. Wrong level surgery is one of the most common surgical errors in the cervical spine, and it almost always comes from not correlating the anatomy precisely with the clinical picture.
The uncinate processes and Luschka's joints are another area where textbook diagrams are woefully inadequate. Those bony ridges on the lateral sides of the vertebral bodies develop during childhood and progressively create the uncovertebral joints. When they hypertrophy with age or degeneration, they narrow the neural foramina from the anterior-lateral direction. This is a primary mechanism for cervical radiculopathy that most general practitioners don't fully appreciate because standard sagittal MRI views don't show it well. You need axial cuts at the foraminal level, and even then, the anatomy is crowded and confusing if you're not familiar with the landmarks. The vertebral arteries deserve specific attention. They don't just run through the transverse foramina — they enter at varying levels, most commonly C6 but anywhere from C1 to C7. In about 2-3% of the population, one or both vertebral arteries enter at C1 or C2, which completely changes the surgical risk profile for anterior cervical procedures. Before any anterior cervical discectomy or corpectomy, you need to know where those arteries are. A CT angiogram takes ten minutes and prevents a catastrophic intraoperative complication that can result in brainstem infarction. The ligamentous structures are equally important and equally ignored in basic anatomy courses. The posterior longitudinal ligament runs along the posterior aspect of the vertebral bodies inside the spinal canal. It's narrow centrally and wider laterally. A central disc herniation has to push through this ligament to cause cord compression, while a far-lateral herniation bypasses it entirely and compresses the nerve root directly. The ligamentum flavum connects the laminae and thickens with age, contributing to spinal canal stenosis. When you combine disc bulging, uncovertebral hypertrophy, and ligamentum flavum thickening, you get the classic triad of cervical spondylotic myelopathy — progressive cord compression that causes gait disturbance, hand clumsiness, and eventually bowel and bladder dysfunction if left untreated.
Get the Full Details

Here's a practical problem I encountered that isn't covered in any anatomy textbook. I was reviewing a cervical spine CT for pre-surgical planning and noticed that the patient's C2 nerve root — the one that supplies sensation to the back of the head — was encased in bone from a congenital fusion. Not a recent fracture or degenerative change. A full bony fusion of the C2-C3 facet joints on one side. The patient had been complaining of occipital neuralgia for years and had tried multiple nerve blocks without lasting relief. The blocks kept missing because the nerve root's course was anomalous. We had to use intraoperative fluoroscopy to map the exact exit point before decompressing it. Without knowing the underlying anatomical variant, that procedure would have been a guessing game. Another thing people get wrong is the relationship between the dens and the spinal cord. The transverse ligament of the atlas holds the dens against the anterior arch of C1. If that ligament ruptures — from trauma or rheumatoid arthritis — the dens can migrate posteriorly and compress the brainstem. This is a neurosurgical emergency. The Atlanto-dental interval on a lateral X-ray should be less than 3mm in adults. Anything more suggests ligamentous instability. On MRI, you want to see that space clearly with the ligament visible as a dark band behind the dens. If it's disrupted, you've got a problem. The cervical lordosis is another deceptively simple concept. Normal cervical curvature is approximately 40 to 60 degrees of lordosis from C2 to C7. Loss of this curve — straightening or even reversal into kyphosis — is one of the most common findings on cervical imaging. It's associated with degenerative changes, muscle spasm, and poor postural habits. But here's the nuance: a straight spine isn't always pathological. Acute muscle spasm from a whiplash injury can temporarily flatten the curve, and it often returns to normal within six to eight weeks. Chronic loss of lordosis, especially when accompanied by disc height loss and osteophyte formation, is a different story and tends to progress.
Disc heights vary by level. C5-C6 and C6-C7 are the most mobile segments and the most common sites of degeneration. The disc height at these levels is approximately 10 to 12 millimeters in a healthy young adult, decreasing with age. The total cervical disc space from C2-C3 through C7-T1 accounts for roughly 20% of total cervical spine height. When disc degeneration progresses, the loss of height reduces the neural foramen dimensions by approximately 30 to 40%, which is why foraminal stenosis is so common in cervical spondylosis. If you're studying this for clinical purposes, I'd recommend moving beyond netter-style illustrations immediately. High-resolution axial and sagittal MRI sequences will teach you more in a week than a month of studying static diagrams. Look at the naked MRI scans — the ones without annotations — and try to identify every structure before checking the key. It forces you to actually see the anatomy rather than recognize labeled pictures. Free resources like Radiopaedia have extensive cervical spine case collections with detailed explanations. Spend time there. The blood supply to the cervical spine is worth a quick mention because it has clinical relevance. The vertebral arteries provide the majority of blood flow to the upper cervical spine and spinal cord. Segmental arteries from the ascending cervical and deep cervical arteries supply the lower cervical vertebrae and posterior elements. The anterior spinal artery runs along the anterior surface of the cord, and the posterior spinal arteries run along the posterior surface. Knowledge of this vascular anatomy is critical when planning posterior cervical fusion approaches to avoid compromising cord perfusion.
One limitation I should note about imaging-based learning: standard CT and MRI protocols aren't optimized for all cervical structures. Routine cervical spine CTs often have slice thicknesses of 2.5 to 3 millimeters, which means partial volume averaging can obscure small foramina and nerve roots. If you're trying to study the finer details — the actual course of nerve roots through the foramina, the precise anatomy of the uncovertebral joints — you need thin-slice reconstructions at 1 millimeter or less. Similarly, standard MRI protocols may not include dedicated neuroforaminal views, which are oblique sagittal reconstructions angled to parallel the neural foramina. Without these views, foraminal stenosis is easy to underestimate. The cervical ribs and anomalous anatomy come up more often than you'd expect. A cervical rib at C7 is present in about 0.5 to 1% of the population and can cause thoracic outlet syndrome by compressing the lower brachial plexus. But even smaller variants — aelongated C7 transverse process that contacts the first rib — can produce similar symptoms and are far more common. These aren't emergencies, but they're easy to miss if you're not actively looking for them on imaging. Fusion anomalies are another category worth noting. Klippel-Feil syndrome involves congenital fusion of two or more cervical vertebrae, most commonly C2-C3 and C3-C4. It's present in roughly 1 in 4,000 to 1 in 50,000 people. Most individuals are asymptomatic and discovered incidentally. But associated anomalies are common — renal abnormalities, hearing loss, scoliosis, and cardiac defects. If you identify cervical vertebral fusion on imaging, a brief screening for these associations is appropriate.
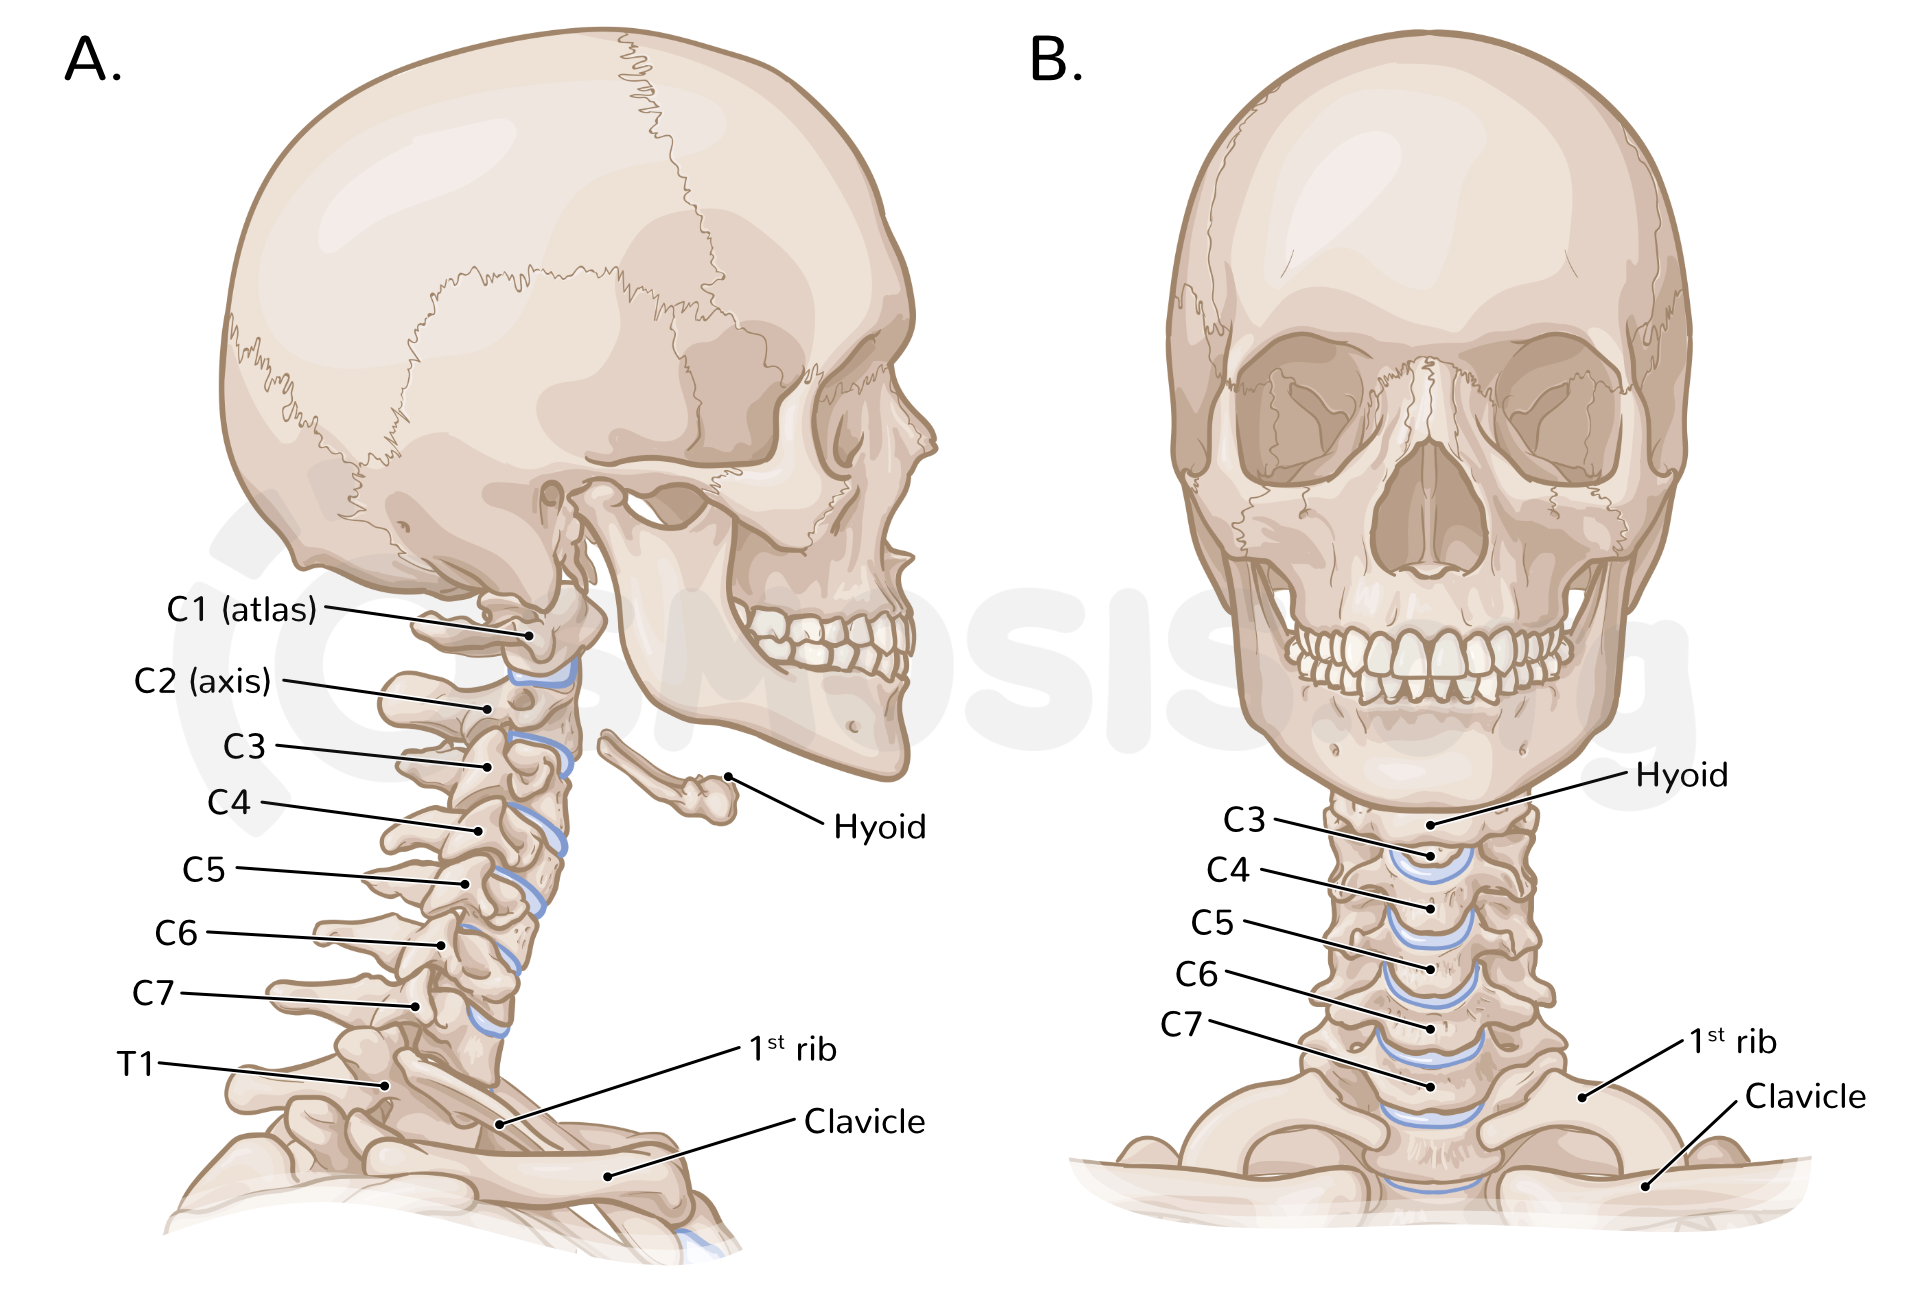
The take-home point isn't that the anatomy is complicated. It's that the complications arise from the interactions between structures. A disc herniation doesn't cause symptoms in isolation. It causes symptoms by compressing a nerve root that may already be narrowed by uncovertebral hypertrophy, with a ligamentum flavum that's thickened from chronic mechanical stress, in a spine that's lost its lordosis and shifted into kyphosis. Understanding Human Neck Bones Anatomy means understanding these relationships, not just memorizing the names of seven vertebrae. The details matter because the clinical consequences of getting them wrong are real and significant.