Using an Anatomy Reference the Way It Actually Works
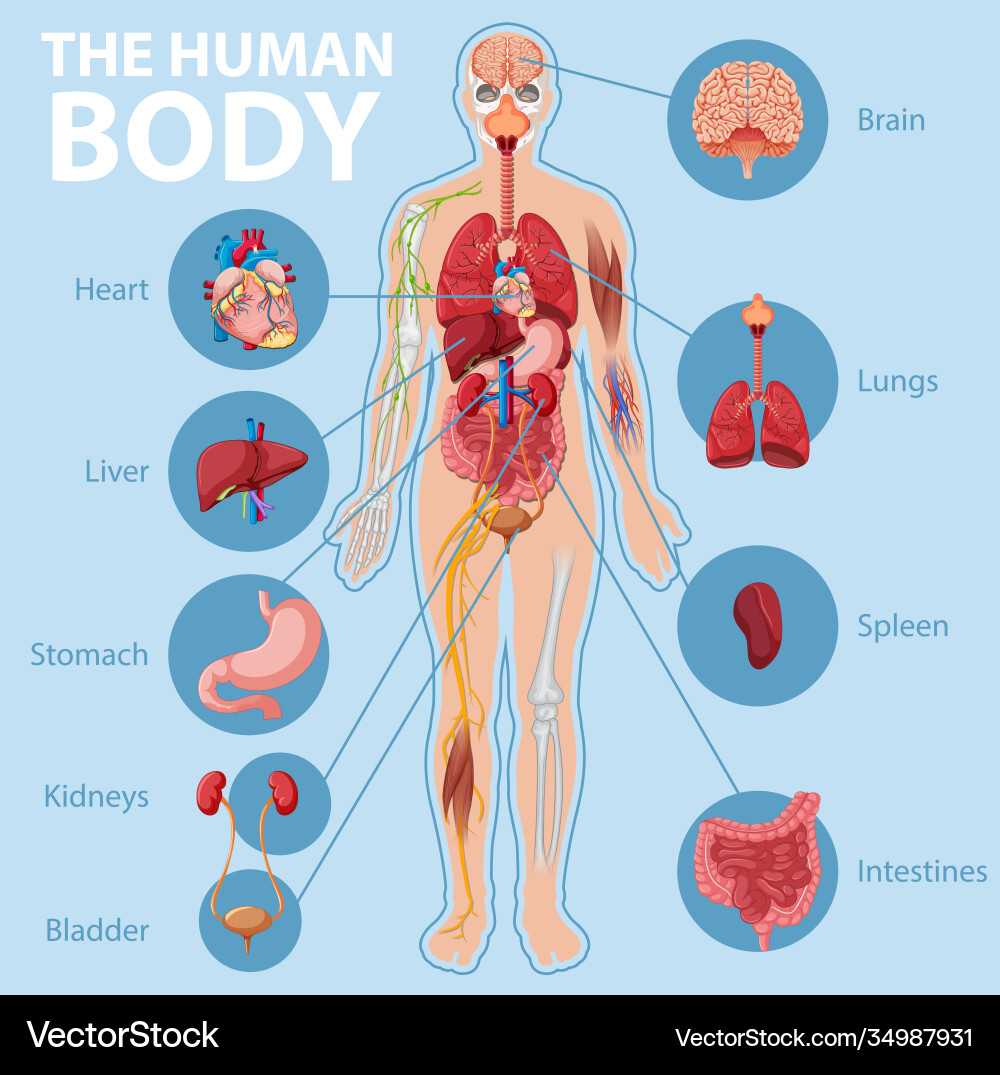
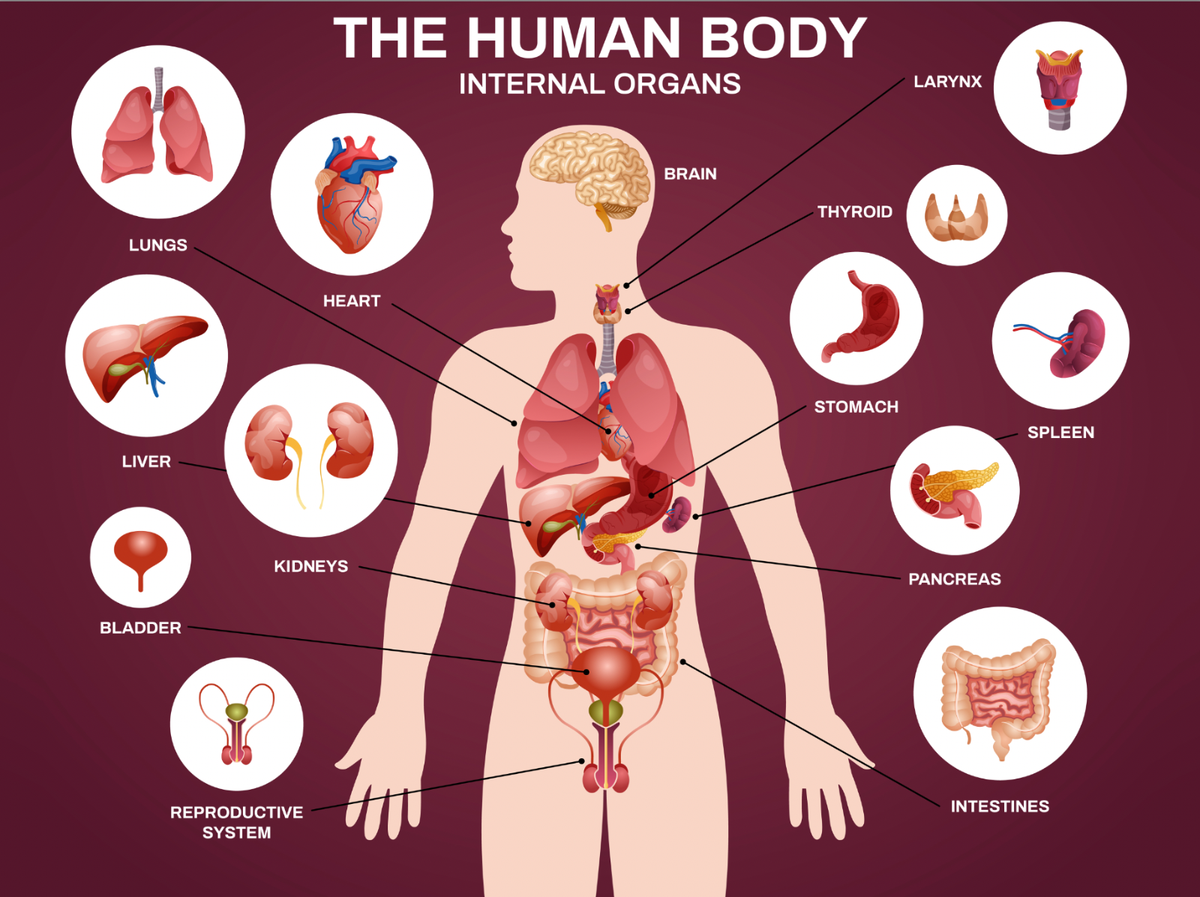
You pick up a Human Organ Anatomy Chart and the first thing you notice is how clean everything looks. Every organ sits exactly where the textbook says it should. The diaphragm is a perfect dome. The liver occupies the right upper quadrant without spilling over. That's the problem with them — they're drawn for students who have never opened a real cadaver. I spent three years in a gross anatomy lab before I stopped trusting illustrations blindly. Here's what I learned about reading these charts like a clinician instead of a med student.
Why Print Version Beat Everything I Tried
Digital versions look sharp on a screen but you can't circle things quickly. I switched to laminated wall charts at about 24x36 inches because you can actually layer them. Put one showing the cardiovascular system on top of the respiratory chart. The pulmonary arteries overlap the bronchi in a way that digital zoom just can't replicate. You understand spatial relationships differently when you can physically move the paper. Most free downloads online are from 1998 and use Gray's Anatomy plate numbering that nobody teaches anymore. The ones worth buying come from publishers like Netter, Moore, or Clinically Oriented Anatomy by Keith Moore. A proper chart will label the hilum of the lung on the left side differently than the right, show the porta hepatis with the portal triad, and include the peritoneal reflections on the stomach. If it doesn't show whether something is intraperitoneal or retroperitoneal, throw it out. The charts from the Chinese Medical Association or the Anatomical Society of India tend to have better regional detail for surgical approaches. I bought one from a medical supply store in Pune for about twelve dollars and it's still my go-to for retroperitoneal anatomy. The German illustrations from Elsevier are the most precise for cardiovascular variants.
The One Mistake Everyone Makes
People memorize charts instead of learning relationships. You can rote-learn that the inferior vena cava passes through the caval opening at T8 and move on, but that doesn't help you when you're looking at a CT scan and can't find it because the patient has a prominent liver caudate lobe pushing against it. I learned this the hard way during my first week of radiology rotation. The attending asked me to point out the IVC on a contrast study and I froze because my mental image from the chart didn't match what was actually there. Real bodies vary. The chart shows a single hepatic vein entering the IVC. In practice, up to forty percent of people have accessory hepatic veins draining separately. The chart shows the spleen tucked under ribs nine through eleven. In a trauma patient with splenomegaly fromportal hypertension, that spleen extends all the way to the pelvis. The chart isn't wrong. It's just incomplete.
Get the Full Details
How I Actually Use These Charts Now
I don't study them cover to cover anymore. I use them as lookup tools during clinical work. When I'm prepping a patient for a cholecystectomy, I pull out the chart and trace the cystic duct, cystic artery, and the biliary tree. Then I look at the chart showing the hepatobiliary system and note where the cystic artery usually arises from the right hepatic artery and remember that variant anatomy shows up in about fifteen percent of cases. The chart gives me the baseline so I know what to expect surgically. For EKG interpretation, I keep a chest anatomy chart at the nurses' station. Not a full organ chart, just the thoracic cross-section showing heart chambers, great vessels, and lung fields. When a patient comes in with ST elevation in leads II, III, and aVF, I look at the chart and remind myself that the inferior wall sits against the diaphragm and that right ventricular involvement changes everything about fluid management. The chart doesn't tell you that. It just reminds you of the anatomy so you can make the clinical connection.
What These Charts Can't Teach You
No printed or digital chart prepares you for a body with extensive surgical adhesions from prior operations. I saw a chart once that showed the duodenum as a neat C-loop around the head of the pancreas. Then I watched a surgeon take forty-five minutes to dissect through dense peritoneal bands just to expose the same anatomy. The chart assumes pristine conditions. The operating room rarely delivers that. Charts also can't show you the variation in autonomic innervation. The enteric nervous system in the gut has more neurons than the spinal cord, and no chart does justice to that complexity. If you're studying for boards, the Netter atlas covers enough. If you're actually going to operate, you need operative atlases and case experience, not just a wall chart.
Quick Practical Notes
A standard human organ anatomy chart set for a medical office runs about eighty to one hundred fifty dollars depending on whether you want laminated or vinyl. The laminated versions peel at the edges after eighteen months of rolling and unrolling. Vinyl holds up better but costs extra. Digital subscriptions to platforms like Complete Anatomy or Visible Body cost about two hundred dollars a year and are useful for rotation through layers, but they're terrible for quick reference during rounds. If you're a student, buy one good printed chart and use it daily. If you're a practicing clinician, get the regional sets — thorax, abdomen, pelvis, upper limb, lower limb — and keep them in your office or clinic. The investment pays for itself the first time you need to explain to a patient where their appendix actually sits relative to the psoas muscle and why a retrocecal appendix doesn't cause the classic McBurney's point tenderness.