Navigating Hygienist Scope Of Practice By State
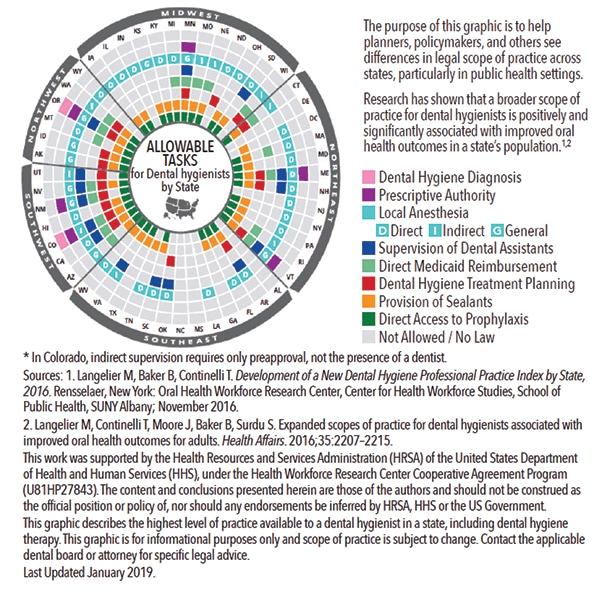
You're three minutes into a prophylaxis and realize you might be about to cross a line depending on which side of a state border you parked on. That's the day-to-day reality of working across different hygienist scope of practice regions. The difference between a routine scaling appointment and a compliance violation usually comes down to one thing: where exactly your license is active. The Dental Hygiene Practice Act in each state defines what you can do independently versus what requires a dentist's direct involvement. Some states grant full independent practice after you meet certain criteria. Others require the supervising dentist to be physically present in the building for basic prophylaxis work. Then there are states somewhere in the middle with indirect supervision protocols that have their own documentation requirements. The National Board Dental Hygiene Examination scores and expanded function certifications shift what you're legally allowed to do in most jurisdictions. A certified dental assistant can sometimes help you move faster in states that allow collaborative team practices, but that assistance model itself varies significantly by region.
I learned this the hard way during my second year of practice. I accepted a locum tenens position at a clinic in a state with tighter supervision rules than my home state. During a morning block, I administered a local anesthetic for a deep cleaning and assumed the general anesthesia protocol was identical to what I was used to. It wasn't. The state required the supervising dentist to complete specific documentation before any anesthetic administration, and that paperwork had been sitting incomplete on the front desk for two days. I stopped what I was doing, contacted the office manager, and rescheduled those patients until the forms were properly executed. That situation cost me half a day of chair time but it completely changed how I verify state-specific requirements before accepting any out-of-state position. I now call the state dental board directly during my interview process and ask specifically about anesthesia protocols, autonomous prescribing authority, and whether direct supervision means the same thing on paper as it does in actual clinical enforcement.
The Three Supervision Levels and What They Actually Mean
Direct supervision requires the dentist to be present in the office suite and authorize each procedure before you begin. Indirect supervision means the dentist evaluates the patient first and is available for consultation during your treatment. General supervision is the loosest standard where the dentist doesn't need to be on-site but must have examined the patient within a specified timeframe. Here's what nobody tells you during orientation: the definition of "present in the office" varies by state inspection standards. Some states consider a dentist on the premises if they're in the adjacent medical building next door. Others require them in the exact same structure. I worked with a hygienist who got a formal reprimand because her supervising dentist regularly stayed in a coffee shop two blocks away while she provided care in a rural satellite location. The board ruled that distance violated the direct supervision requirement even though the dentist was technically reachable by phone. The case citation from that hearing still shows up in study guides for state jurisprudence exams. Prescribing authority is another area where assumptions get people in trouble. Five states grant hygienists independent prescribing authority for topical anesthetics and fluoride products under specific conditions. Four additional states allow collaborative prescribing agreements between hygienists and dentists. Outside of those nine states, attempting to prescribe anything beyond what's explicitly listed in your state's practice act constitutes practicing dentistry without a license. I've seen experienced hygienists get placed on probation for writing a prescription for chlorhexidine gluconate rinse in a state where that medication falls outside the permitted scope regardless of clinical appropriateness.
Get the Full Details

Working Around Limitations Without Crossing Into Liability
There are legitimate clinical situations where your state's scope restrictions create real patient access problems. Rural areas frequently have fewer dentists willing to maintain the direct supervision model that certain states require. When that happens, you need to understand what your practice act actually permits before you assume a workaround exists. The most common productive approach involves understanding your state's delegation laws. Some states allow dentists to delegate certain diagnostic procedures to hygienists through formal written protocols. Once that delegation is in place and properly documented in the patient's chart, you may be able to perform assessment tasks that would otherwise require direct physician authorization. The key word here is documented. I've watched colleagues skip the written protocol step because "everyone knows we do this." The board doesn't care about everyone's habits. They care about whether the signed delegation form exists on file. Another overlooked area involves community health centers and public health settings. Many states have expanded scope provisions that only activate within federally qualified health centers or similar institutional settings. If you're employed through a county health department or a nonprofit dental clinic, you may have broader procedural authority than you'd have in a private practice setting doing the exact same work. I verified this for a colleague who wanted to administer nitrous oxide in a school-based clinic. Her private practice office had denied the request based on their internal policy, but the state's expanded scope law for school-based settings explicitly permitted it. She needed to understand which regulatory framework governed her specific employment location.
There are scenarios where no amount of scope navigation helps. States that restrict hygienists from administering any injectable anesthetic beyond the intralesional limit create genuine barriers for patients with severe dental anxiety who need comprehensive periodontal therapy. No procedural workaround exists for that gap in the practice act. In those situations, the honest answer is often referral to a sedation dentist or a facility that operates under a different licensing category. Pushing past that boundary thinking you can manage without certification creates liability that extends well beyond your professional license.
Keeping Your Credentials Current Across State Lines
Continuing education requirements differ substantially between states. Some require specific coursework in infection control, pain management, or pharmacology that may not align with what you need for renewal in another jurisdiction. I maintain licenses in three states and track renewal cycles separately for each one. The CE credits I completed for my primary state don't always transfer to the secondary states, and the documentation requirements for audit purposes vary enough that I keep separate digital folders for each license. If you're considering multi-state practice through interstate compacts, check whether your state has actually joined the Dynamic Dental Hygiene License Compact. Not every state participates, and the compact doesn't automatically grant you practice authority in all member states without separate credential verification. I've seen hygienists assume compact membership provided blanket authorization and then discover they were operating illegally in a state that participated in the compact but required additional application processing before credentials became active. The practical tip that saves the most headache: verify your scope of practice every time you accept a position in a new state, even if you've practiced there before. Practice acts amend regularly. Procedures that were permissible last year might require different supervision parameters this year. I noticed a change in my own state's guidelines when the board added a requirement for documenting medical consultation prior to treating patients with certain cardiovascular conditions during cleanings. The change happened without any clinic-wide announcement. I found it through the monthly newsletter and adjusted my clinical workflow accordingly within the same week.