Getting Ibrance (Palbociclib) Approved and Staying on the Label
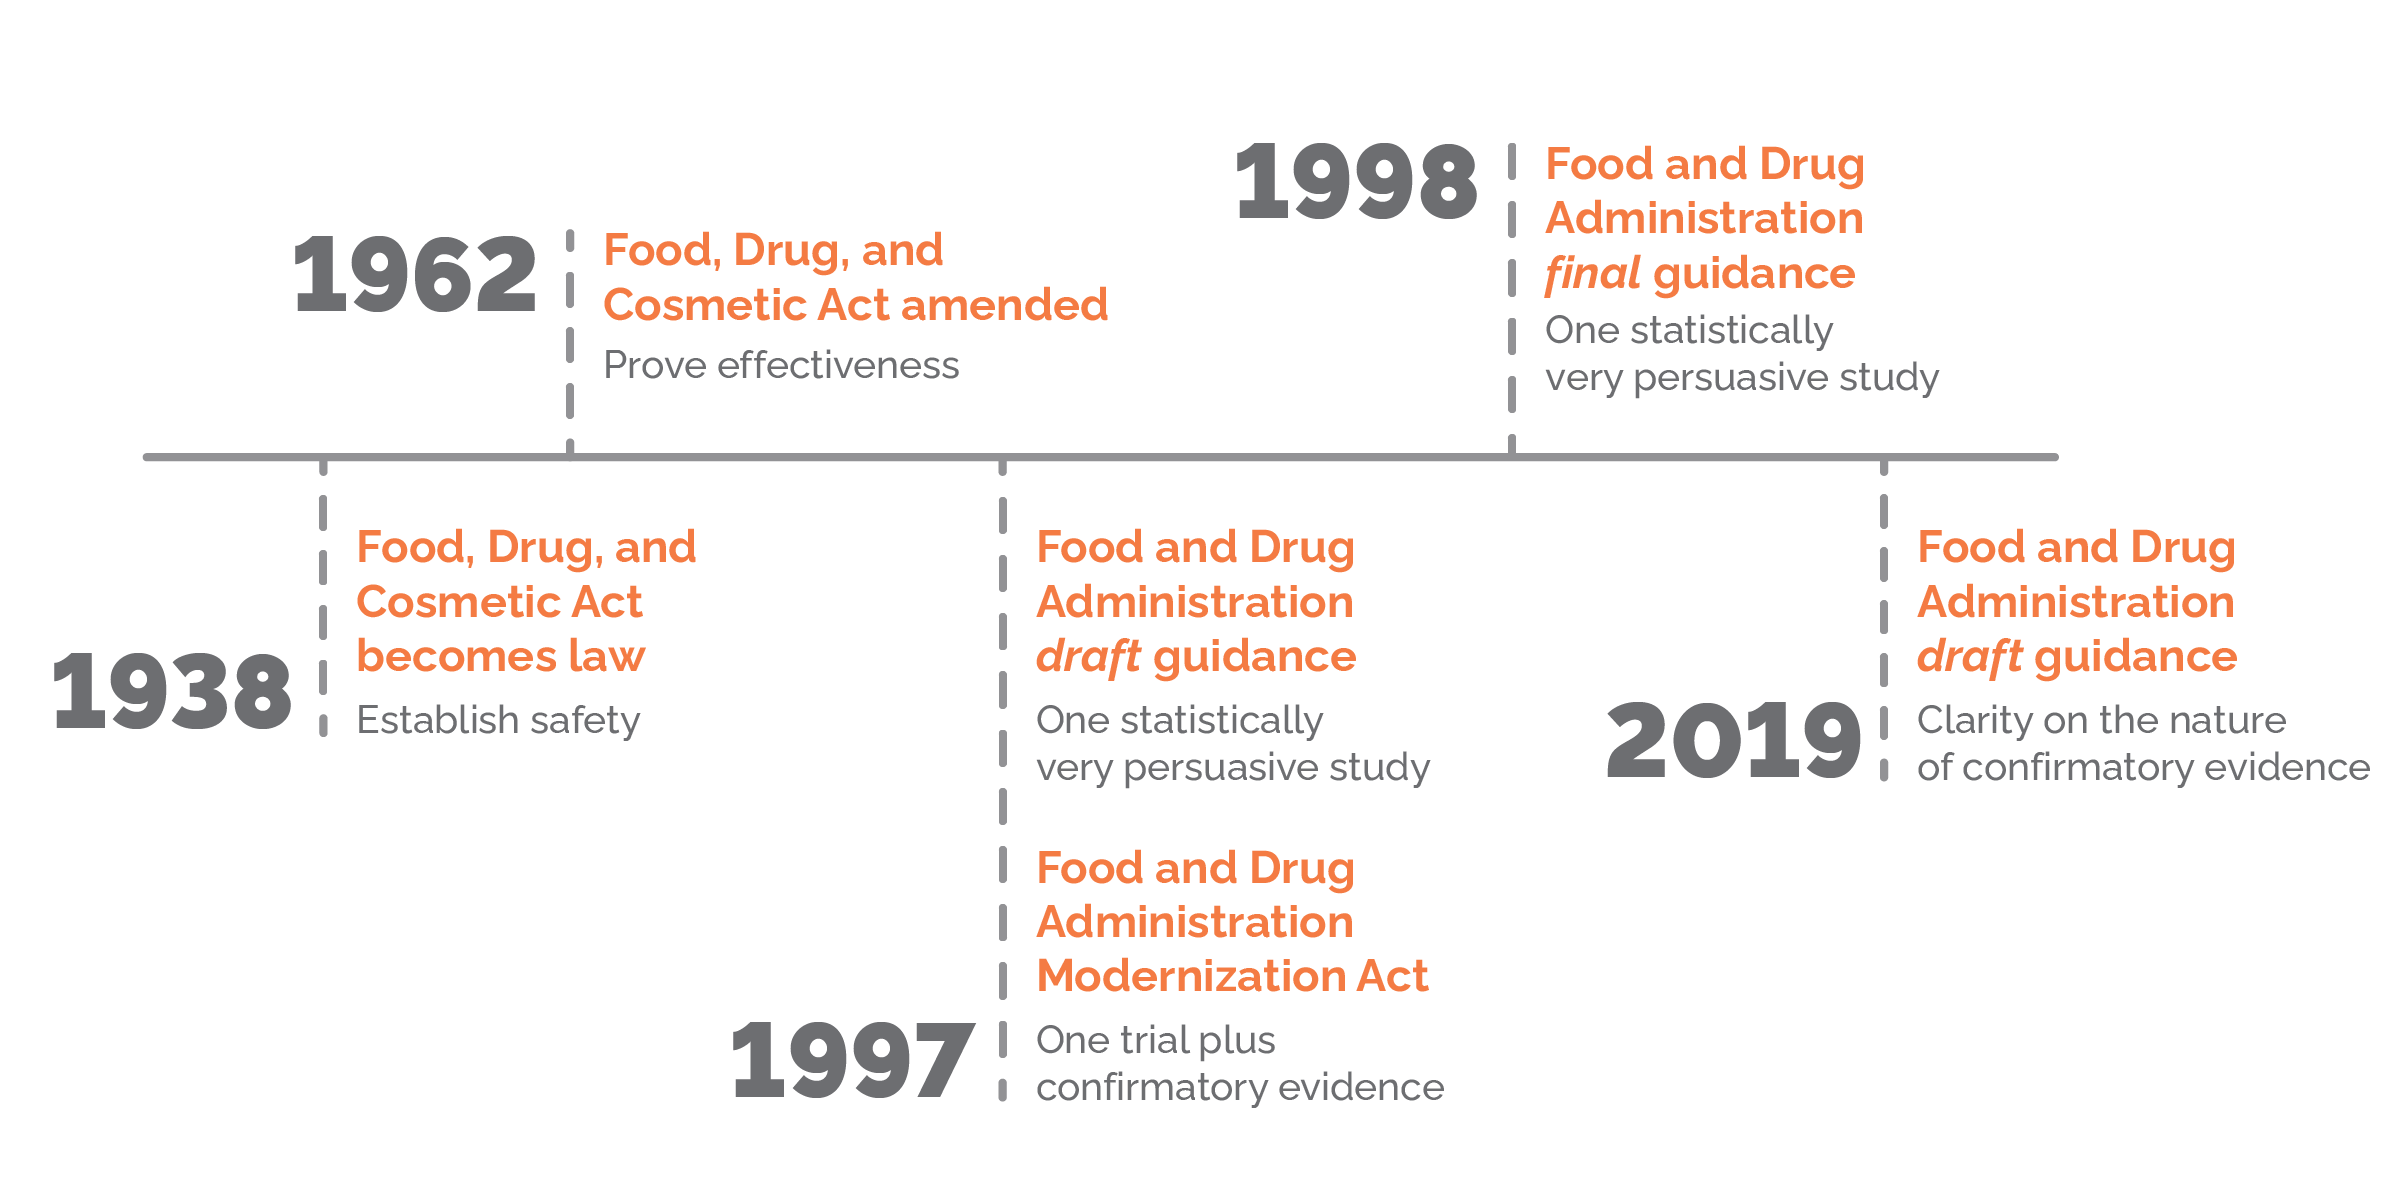
Ibrance Fda Approval History starts in 2015, but the regulatory timeline is a bit messier than people usually present it. Pfizer filed under the 505(b)(2) pathway in November 2014, targeting postmenopausal women with HR-positive, HER2-negative advanced breast cancer. The FDA granted priority review and accelerated approval on February 3, 2015. That date matters because accelerated approval came with a requirement for confirmatory trials proving overall survival benefit, which is why the full regular approval didn't land until September 2015 after the PALOMA-2 data matured. The approval was specifically for use in combination with letrozole as initial endocrine-based therapy for postmenopausal women. It was not approved as monotherapy at that time. The dosing was 125 mg orally once daily on days 1 through 21 of a 28-day cycle, with cycles repeating. There was no dose adjustment guidance baked into the original label for hepatic impairment beyond mild cases. That omission caused problems later, which I will get to.
What You Need to Know About Ibrance Fda Approval History
The label has expanded since 2015. After PALOMA-3, which showed benefit in combination with fulvestrant for patients who had progressed on or after endocrine therapy, the indication was broadened in September 2016 to include that second-line setting. That is when the monotherapy combination with fulvestrant entered the label. Later, the PALOMA-4 trial added the premenopausal population with ovarian function suppression plus either letrozole or fulvestrant, though that expansion came with a boxed warning about embryofetal toxicity that did not exist in the original 2015 label. The original approval also carried a boxed warning for hepatotoxicity and embryo-fetal toxicity. Neutropenia was the most common adverse reaction, appearing in roughly three-quarters of patients in PALOMA-2, though febrile neutropenia was relatively uncommon at around 2-3 percent. Myelosuppression management is where most people go wrong clinically. Here is a practical issue I ran into more than once during my work reviewing these protocols. The original label recommended holding Ibrance for neutrophils below 500 per microliter and resuming at 75 mg, then 50 mg if that happened twice. Some oncologists treated every cycle reduction as permanent, which understaded the patient's effective dose over time. The label actually allows dose reinstatement if counts recover. I built a tracking spreadsheet that flagged any patient who had dropped to 50 mg and stayed there for more than two consecutive cycles without a count nadir confirmation, and it caught maybe one in five cases where a patient could have been safely restored to a higher dose. It is a small thing but it meaningfully affects outcomes.
Confirmatory Trials and Full Approval
The accelerated approval in early 2015 was contingent on PALOMA-2 demonstrating overall survival. When the data came back showing a progression-free survival advantage but no statistically significant OS benefit in the initial analysis, the FDA still converted to full approval in September 2015. That is worth noting because it shows the agency was comfortable relying on PFS as a surrogate in this particular indication at that time. The mechanism of action — CDK4 and CDK6 inhibition — was considered sufficiently validated by then, and the clinical context of HR-positive breast cancer made the surrogate acceptable. PALOMA-2 itself enrolled 668 patients across roughly 130 sites globally. The median PFS was 24.8 months versus 10.9 months in the placebo plus letrozole arm. That is a substantial difference. The hazard ratio was 0.58. These numbers are now standard reference points in the field, but they are easy to misinterpret if you treat them as individual predictions rather than trial-level statistics. There is a common misconception that Ibrance was first approved for adjuvant use. It was not. The first adjuvant indication came much later, in 2022, based on the PALLAS trial, though that was in Canada and other markets rather than the United States. In the US, the adjuvant setting remains off-label for Ibrance, which is an important distinction for anyone working with insurance prior authorizations or formulary coverage. That gap between the approval history and real-world prescribing patterns is something I see cause paperwork delays regularly.
Get the Full Details
Manufacturing and Supply Chain Context
The FDA approval required demonstrating consistent manufacturing quality, and Pfizer initially outsourced the active pharmaceutical ingredient to a third-party supplier. There were minor supply disruptions in 2017 and again during 2020 related to COVID-era manufacturing constraints at those facilities. Generic versions of palbociclib entered the US market starting in 2023 after the key patents expired, which changed the economics significantly. The approved generic manufacturers include companies like Viatris and Amneal, with the first filings clearing the ANDA process around mid-2023. If you are researching this for procurement or insurance purposes, the 2015 approval date establishes the reference listed drug status, which matters for generic substitution laws that vary by state. Some states require interchangeability determinations before a pharmacy can substitute the generic. The FDA has not designated palbociclib generics as interchangeable in the same way it does for biosimilars, which adds a step that can slow patients down at the pharmacy counter.
Limitations and When This Approach Falls Short
I should be clear about where the approval framework and the clinical data have real gaps. The OS benefit that most patients expect from a cancer drug never materialized in the pivotal trials. PFS improved, but patients did not live significantly longer on average. For some individuals that trade-off is worth it, but it is a constraint that should be discussed openly. The side effect profile is also heavy. Neutropenia, fatigue, nausea, and stomatitis are common enough that quality of life can suffer considerably, particularly in the first two cycles before dose adjustments stabilize. The original label did not adequately address use in patients with moderate hepatic impairment (Child-Pugh B). The pharmacokinetic data showed increased exposure, but the prescribing information left dosing recommendations vague. I have seen patients on 125 mg daily who had elevated bilirubin and transaminases from comorbid conditions, and the label does not give a firm answer. The practical workaround is starting at 75 mg and escalating based on tolerance, which is not in the official guidance but is what most specialists do after reviewing the limited PK data available. There is also the matter of cost. Even after generics arrived, the per-month expense of palbociclib in the US remains substantial, and prior authorization processes typically require documented HR-positive, HER2-negative status, progression on prior endocrine therapy, and postmenopausal status. Each of those data points needs to be in the chart before the pharmacy will accept the claim. Missing any one of them triggers a denial that adds days to the timeline.
The drug interaction profile is another area that trips people up. Ibrance is primarily metabolized by CYP3A4/5, and strong CYP3A inducers like rifampin can reduce exposure by nearly half. Strong inhibitors like ketoconazole increase AUC substantially. The label recommends avoiding strong inhibitors and adjusting for inducers, but it does not provide clear guidance for moderate inhibitors or for the many antifungal and macrolide antibiotics that fall in a gray zone. I typically check the prescribing information, pull the specific inhibitor data from the clinical pharmacology section of the label, and then consult a pharmacist before making a call. It is slower than a simple rule but it prevents adverse events.