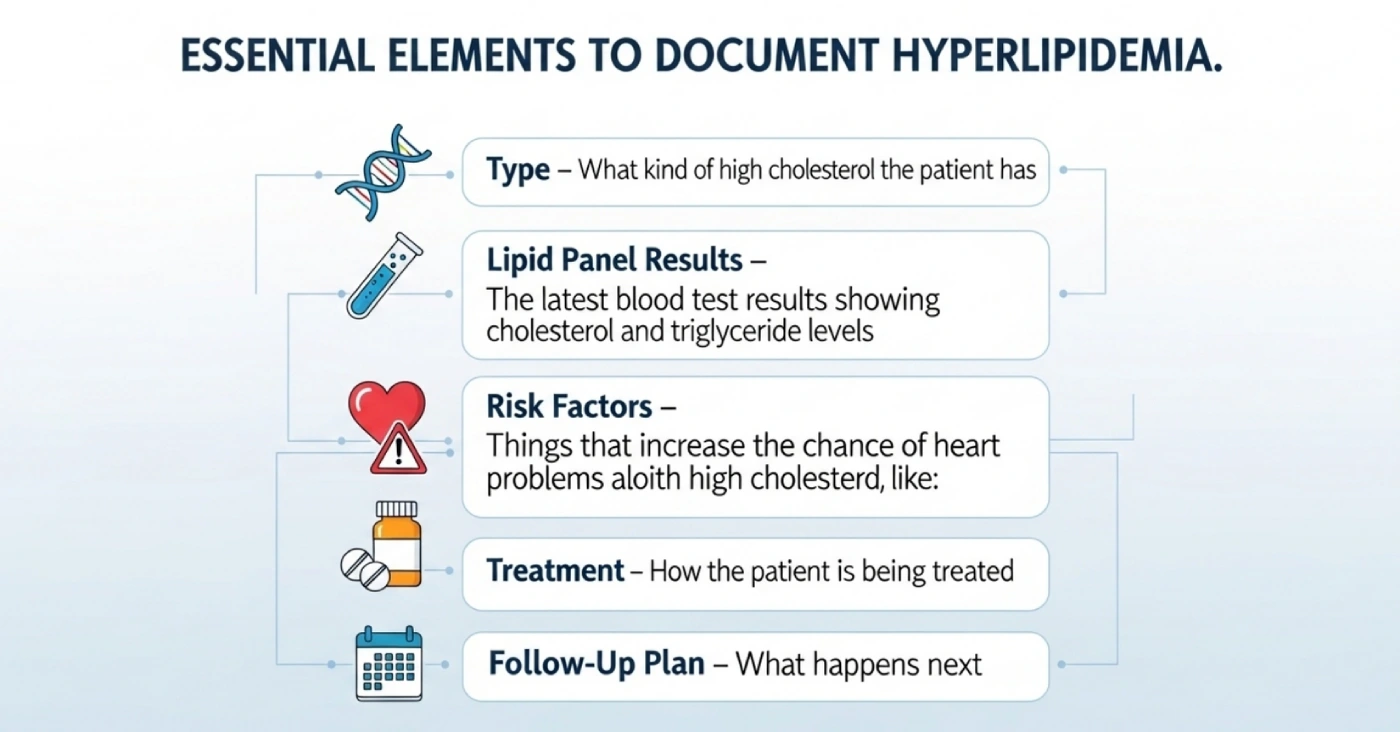
Getting the Hyperlipidemia Code Right
I spend more time than I'd like admitting on Icd 10 Code For Hyperlipidemia. Most coders treat it like it's simple — slap on E78.5 and move on. That approach works until you get a denial that makes you question your entire career. Let me walk through what actually happens in practice, the way it should have been taught to me during my first year. The basic code assignment is straightforward if you read the documentation first. Hyperlipidemia falls under category E78, which covers disorders of lipoprotein metabolism. The most commonly used code is E78.5, which describes unspecified hyperlipidemia. It's the default when a provider documents hyperlipidemia without specifying the exact type. Many people think this is a catch-all bucket for when they don't have enough information. It's not. Use it when the documentation genuinely doesn't support anything more specific.
Icd 10 Code For Hyperlipidemia Specifics
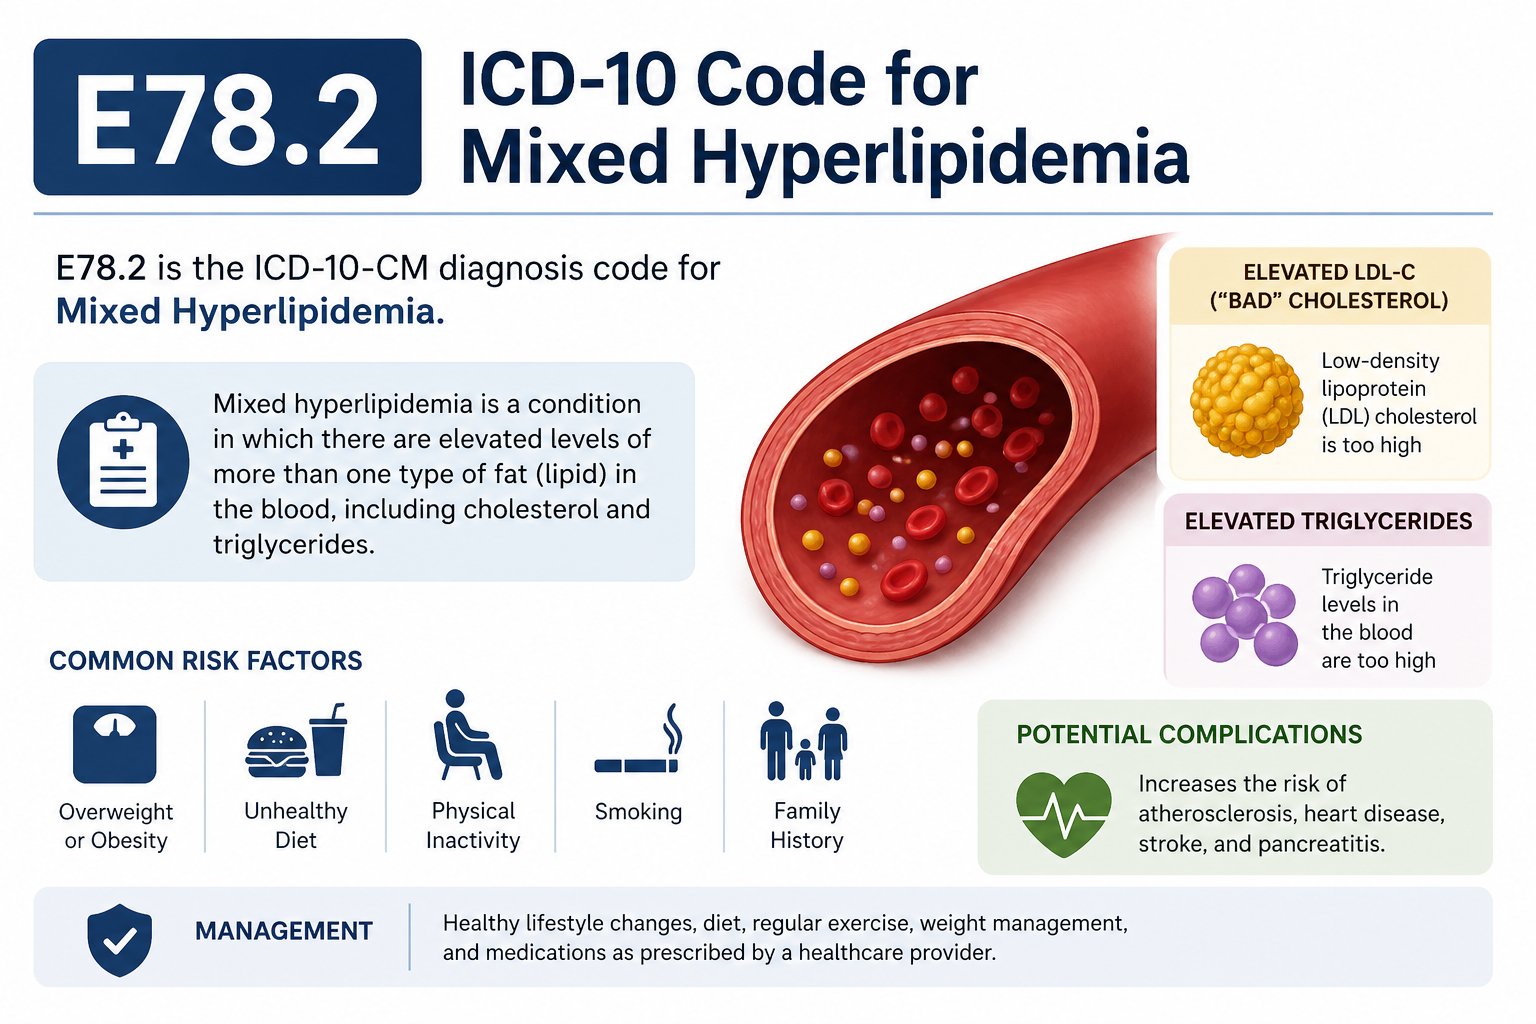
Hypercholesterolemia alone gets coded as E78.0. Elevated triglycerides is E78.1. Combined hyperlipidemia — and I can't stress this enough, the distinction matters — is E78.2. If a patient has both elevated cholesterol and elevated triglycerides, E78.5 is wrong. You need E78.2 or potentially both E78.0 and E78.1 if the provider's documentation treats them as separate findings rather than a single mixed condition. Mixed hyperlipidemia shows up as E78.2, but you'll see plenty of providers document "elevated lipids" and leave it at that. Elevated lipids is vague. You can't assume hyperlipidemia from elevated lipids alone without clarification from the provider. This is a documentation gap that causes audits. Here's something nobody mentions in the training materials: when hyperlipidemia is documented alongside diabetes, the coding interaction changes everything. E78.5 does not take priority. You need to determine whether the hyperlipidemia is documented as a comorbidity or as an incidental finding. Most EHR systems will auto-suggest the primary diagnosis, but that suggestion is based on the admitting reason, not the clinical relationship between conditions. I had a case last month where a patient was admitted for diabetic ketoacidosis and had hyperlipidemia noted in the chronic condition list. The initial coder assigned E78.5 as a secondary diagnosis, which added risk adjustment points. The auditor flagged it because the hyperlipidemia was completely unrelated to the admission and the provider had only listed it as a historical finding without active management notes for the current encounter. The claim was correct, but the risk score was inappropriate. I pushed back and had it removed.
The second issue that catches people repeatedly involves long-term current drug therapy. When a patient is on statins for hyperlipidemia, Z79.899 is used as an additional code to indicate the medication. This is required by CMS for accurate risk adjustment. I see this code left off constantly. It's not optional for Medicare Advantage encounters. The base diagnosis code for hyperlipidemia and the Z code for medication use are both required and neither compensates for the absence of the other. One more practical note: familial hypercholesterolemia is E78.00 and E78.01, with the fifth character distinguishing between homozygous and heterozygous forms. If a provider writes "familial hypercholesterolemia" without specifying the type, you query. Do not assign E78.00 and hope for the best. Query letters from my department average about three days, and we track them religiously because uncleared queries delay claim submission. Documentation specificity is where most errors happen. A physician note that says "patient with high cholesterol" is not equivalent to a note that says "hypercholesterolemia." The medical record needs the condition name as it maps to ICD-10. Informal terminology is fine clinically, but it does not survive coding review. When I audit our own output, I pull cases where the provider used lay language and verify that the coded term matches the official index entry.
Get the Full Details

There's a limitation worth noting upfront. ICD-10-CM has a fundamental problem with hyperlipidemia: the code set forces a choice between unspecified and highly specific categories, and there's significant gray area in between. A patient with borderline high cholesterol who is being monitored but not yet treated has no clear code. The closest options are R78.1 (elevated lipid levels) or E78.5, but each carries different implications for risk adjustment and billing. Some payers expect R78.1 for borderline findings. Others expect E78.5. The documentation needs to be explicit about whether the finding is abnormal or borderline before you choose. This ambiguity is system-wide and affects every coder who handles metabolic panels. My workaround for the borderline case is to add a query to the provider with two specific questions: is the elevated lipid finding a current abnormality requiring treatment, or is it a monitoring finding? The answer determines whether E78.5 or R78.1 applies. This adds maybe ten minutes per affected case, but it prevents the denial that would cost significantly more later. For the actual lookup process, the CDC ICD-10-CM lookup tool at cdc.gov is the authoritative source. It's free and updated annually with the October release cycle. Third-party code lookups exist, but they lag the official updates. I only trust the CDC source for final verification because the difference between E78.5 and a nearby code in the same family can be one character and the billing impact is real.