Getting Competent in Both IFS and EMDR Actually Takes a Real Investment
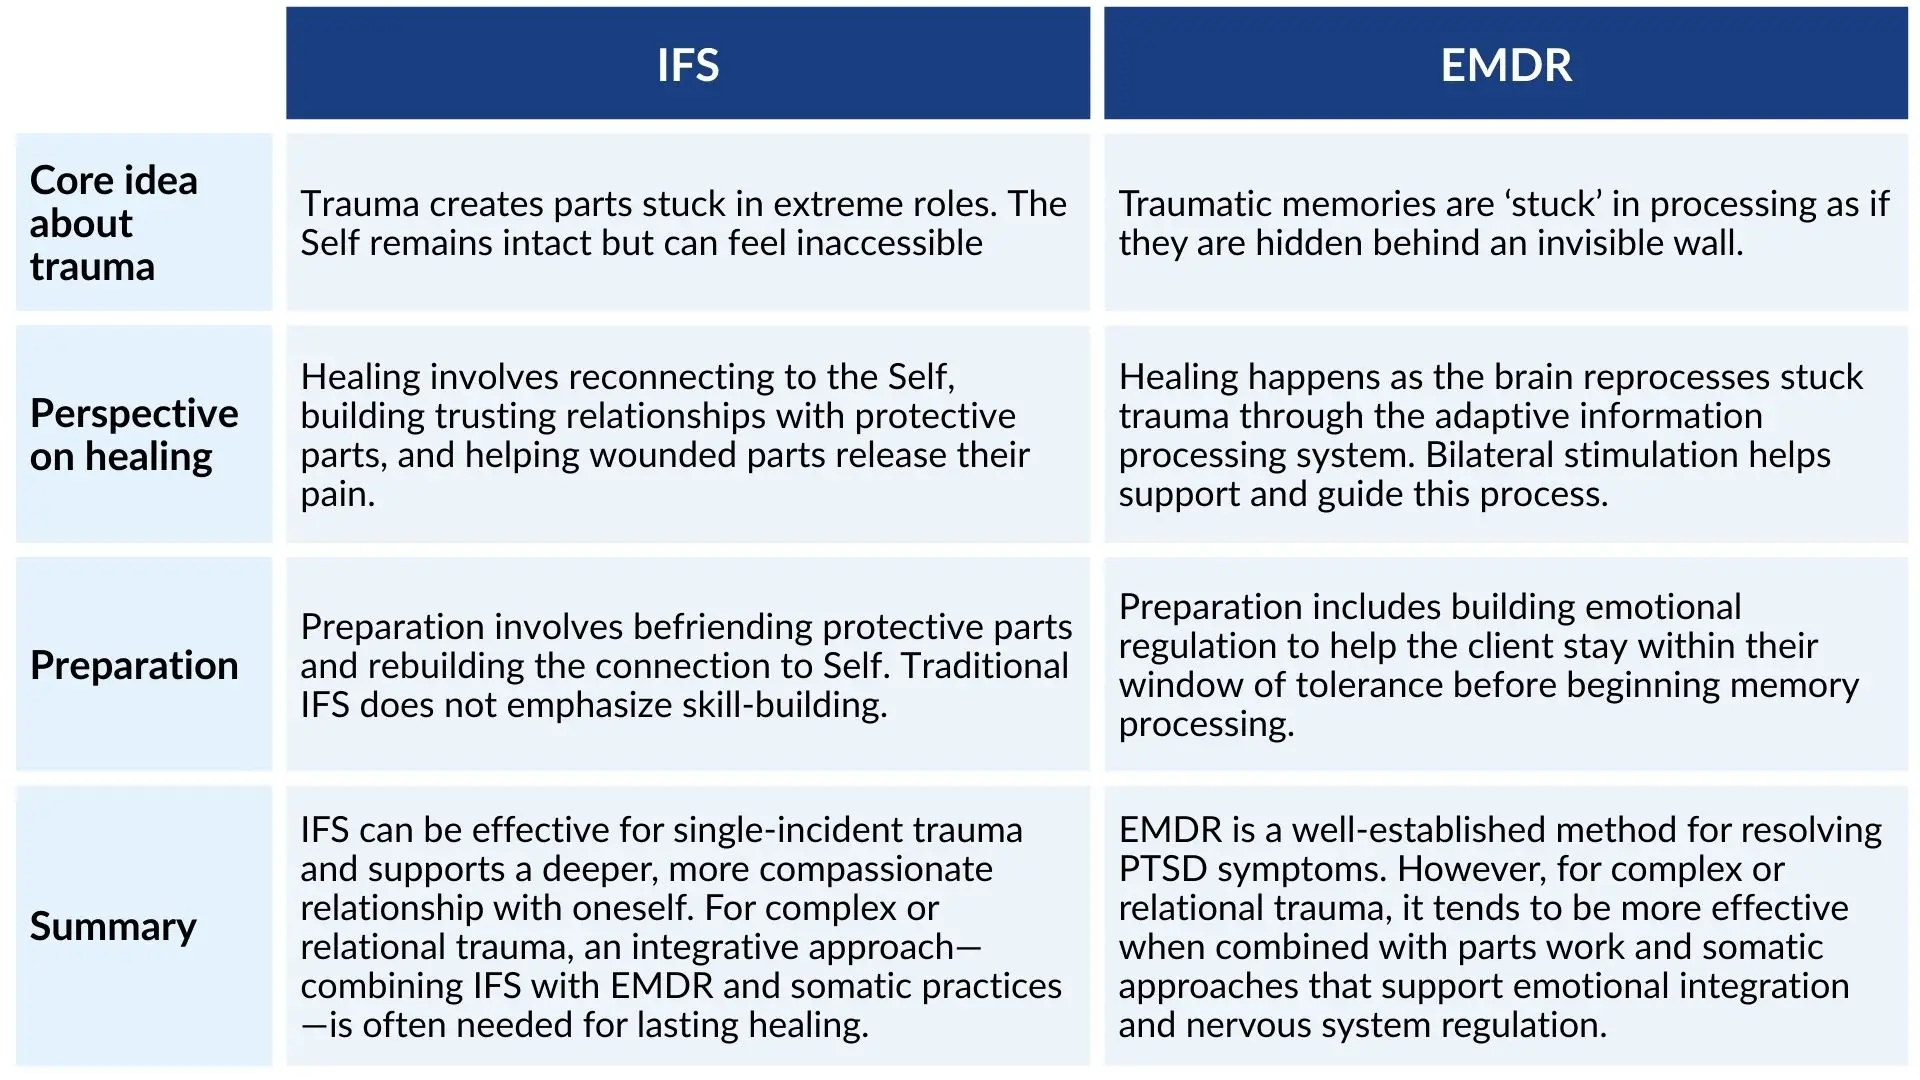
Most people who come to this topic are therapists looking to expand their clinical toolkit. You can pick up the surface-level concepts from a weekend workshop, but that does not make you competent. I spent roughly eighteen months working through structured training programs before I felt comfortable actually running a session that integrated both modalities. Here is what actually happens when you go through proper Ifs And Emdr Training. Internal Family Systems and EMDR were not designed to run together. They come from completely different theoretical frameworks. Richard Schwartz built IFS around the idea that the mind is made of multiple subpersonalities or parts, each with their own perspective and emotional weight. Francine Shapiro developed EMDR around bilateral stimulation to help the brain process traumatic memories. When you train in both, you are essentially learning two separate languages and then figuring out how to have them hold a conversation with a client. The training pathway usually looks like this. You complete foundational IFS Level 1 training, which typically runs three to five days split across a few weekends. Level 2 follows another three to five days, usually six to twelve months later, where you dig into parts work that is more complex and resistant. Then there is EMDR Level 1, which is a standard two-day intensive, and Level 2, another two days. After that, you do your supervised hours. EMDR requires fifteen hours of consultation over at least twelve months. IFS recommends ongoing consultation but does not enforce a strict hour minimum the way EMDR does.
I skipped the EMDR Level 2 course for three years because I did not feel I had enough client contact to justify it. My training coordinator told me I was being cowardly and that Level 2 covers dissociation and complex trauma protocols that Level 1 barely touches. She was right. I went back and completed it. It added about forty hours to my education but changed how I handle clients who fragment during processing.
What Actually Happens When You Combine Them in Practice
The most common question I get is whether you should do IFS parts work first and then EMDR, or the other way around. The answer depends entirely on the client's capacity for internal communication. If someone cannot identify or talk to their parts without becoming overwhelmed, you run into trouble very quickly when you try to process a memory. The parts will either block the processing or hijack it entirely. I usually establish some basic IFS infrastructure first. That means helping the client recognize that parts exist, getting a neutral or curious part of them to observe rather than react, and establishing a simple signal so the client can communicate between parts during a session. This typically takes three to five sessions. After that, I introduce EMDR's standard eight-phase protocol, but I adapt it. The preparation phase becomes longer because I am doing parts check-ins between sets. If a client's anxious part starts flooding during desensitization, I pause the bilateral stimulation and shift into parts dialogue until the part settles. This can add ten to fifteen minutes to an otherwise ninety-minute session. Here is something most training programs do not emphasize enough. You do not process the traumatic memory directly with EMDR until the parts that are holding that memory are willing to let you approach it. I had a client whose exiled part would literally take them offline whenever I brought up a specific date. We spent six weeks just building rapport with that part. Not processing. Just building rapport. The part wanted guarantees that it would not have to carry the memory alone anymore. I had to negotiate with a subpersonality about its job responsibilities. That is just what it looks like when you actually do this work.
Get the Full Details

Common Mistakes That Will Derail Your Training
The biggest mistake I see trainees make is treating parts as if they are just metaphors. They say things like "I know this is just a part of me" during a session and wonder why the part reacts negatively. Parts are not metaphorical in the clinical sense. They have subjective experience. When you dismiss a part as symbolic, you damage the therapeutic alliance with that part and the client's ability to access internal resources. The fix is straightforward. Address parts with the same respect you would give any other component of the therapeutic relationship. Ask them what they need. Negotiate. Do not bypass them. Another mistake is trying to run EMDR while simultaneously doing deep parts work. These are different cognitive modes. Parts work requires curiosity and relational engagement. EMDR desensitization requires focused attention on the memory network while bilateral stimulation runs. If you are actively dialoguing with a part during a set, you are not giving the memory processing system what it needs. I keep them sequenced. I do parts work between sets or in separate sessions, not during the bilateral stimulation itself. I also want to be clear about where this combination fails. Clients with severe dissociative disorders, particularly those diagnosed with DID or OSDD, need a very different protocol. Standard EMDR training does not prepare you adequately for working with distinct identity states. IFS parts work with client systems requires specialized training that goes well beyond the standard Level 1 and 2 curriculum. If you have a client like this, do not improvise based on your general IFS and EMDR knowledge. Seek out consultants who specialize in dissociative work. There are dedicated programs through the International Society for the Study of Trauma and Dissociation that will serve you better than adding more hours to the standard tracks.
Practical Considerations Before You Enroll
You should have at least two years of post-licensure clinical experience before starting IFS Level 1. Not because you need to be an expert, but because you need to have seen enough clients to recognize when your own parts are reacting to a client's parts. I had a trainee in my first supervision cohort who got visibly agitated during a case presentation about a client's angry part. She did not realize her own part was triggered until I pointed it out. She had only been practicing for eleven months. That is too soon to reliably distinguish client dynamics from countertransference. Cost is another practical factor. IFS training through the Schwartz Center runs approximately two thousand dollars per level. EMDR training through an EMDRIA-approved provider runs between fifteen hundred and three thousand dollars depending on the region and instructor. Consultation hours run about one hundred to two hundred fifty dollars per session. If you budget eighteen months and do the math, you are looking at roughly eight to twelve thousand dollars total to reach a baseline of competency. That does not include lost income from taking weekends off for training. The ROI is real if you plan to build a trauma practice. Therapists who integrate IFS and EMDR report higher client retention and fewer stalled cases. Trauma clients who did not respond to single-modality treatment often engage more readily when both frameworks are available. I would estimate it cuts my average treatment duration for complex PTSD by about three to four months per client compared to using either modality alone. That translates to more completions per year and better outcomes on standard measures like the PCL-5.
I still get asked occasionally whether you can learn this from books or online courses instead of in-person training. You can learn the concepts that way. You cannot become competent that way. The supervision component is non-negotiable, especially when you are working with the overlap between these two models. You need feedback on your timing, your case conceptualization, and your own part responses in real time. Recording sessions and getting consultation on them is acceptable. Self-study alone is not.