Getting the Iliopsoas to cooperate
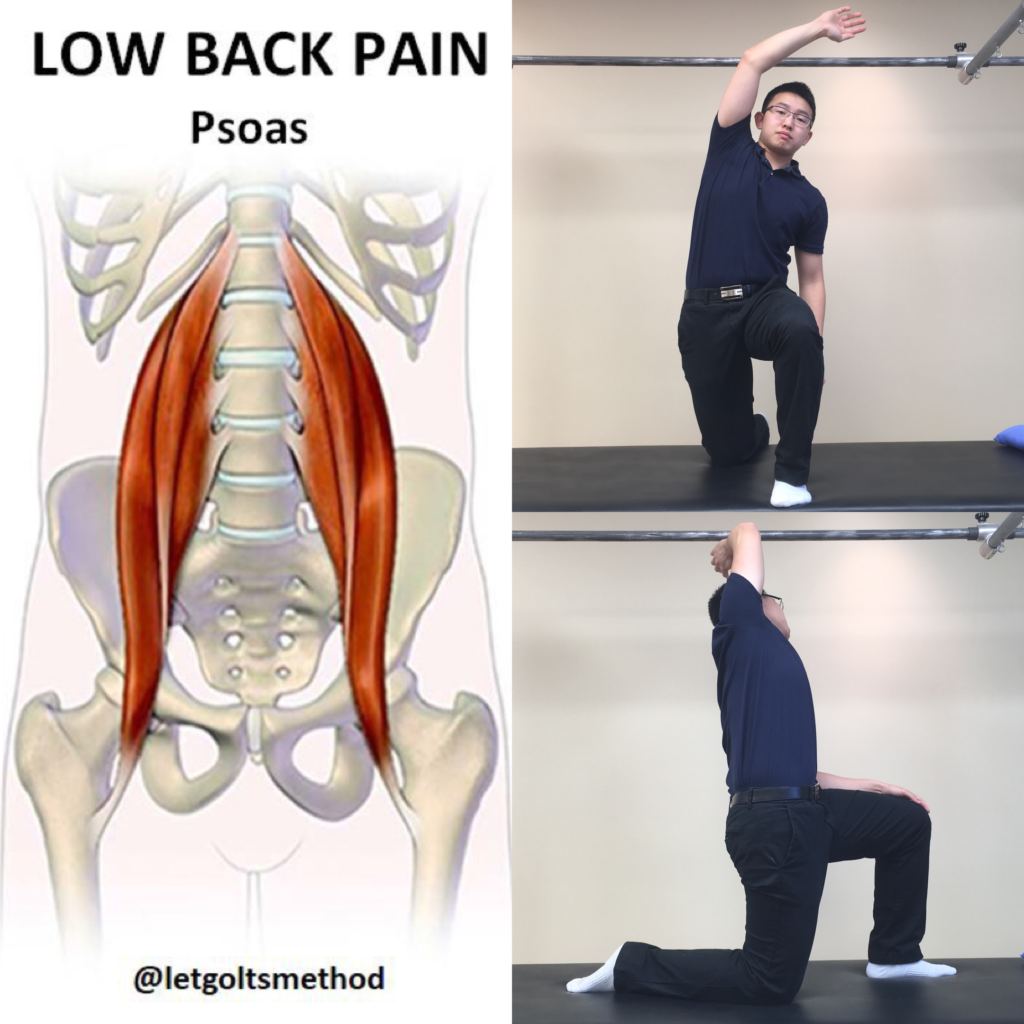
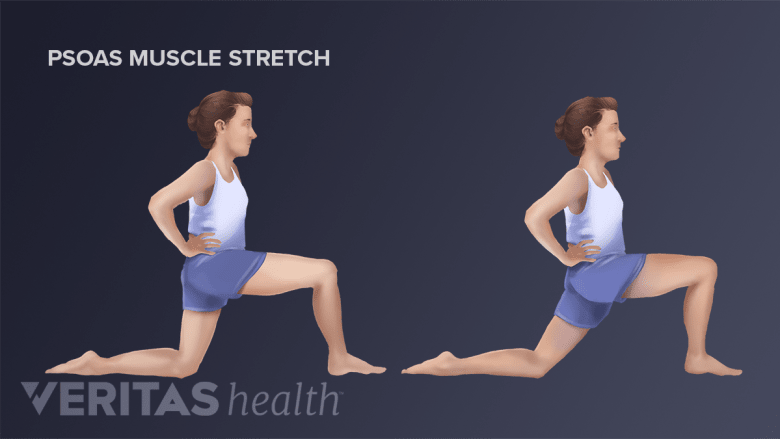
The hip flexors are stubborn. Most people know this if they've ever sat at a desk for a decade and then tried to touch their toes. The iliopsoas complex — psoas major, iliacus, and psoas minor when they're present — shortens and adapts to being in a flexed position. That adaptation isn't just tightness in the muscular sense. It's neural. The stretch reflex gets downregulated at end range, so you can force yourself into a deeper position, but the tissue isn't actually lengthening. It's just being accommodated. I used to watch patients do the classic half-kneeling hip flexor stretch and feel like I was watching them fool themselves. They'd arch their lumbar spine about two inches, shove their pelvis forward as hard as they could, and then report feeling it "deep in the front of the hip." What they were really feeling was lumbar extension compressing the posterior elements of their spine. The iliopsoas barely participated. This is by far the most common mistake I see, and it's also the easiest to fix.
Iliopsoas Stretch Physical Therapy Techniques That Actually Work
Here's the setup most therapists should be using. Have the patient lie supine on the treatment table with both legs extended. Take the target leg and flex the hip to about 90 degrees, keeping the knee extended. Then gently extend the hip past neutral — let gravity do the work while you control the amplitude. The key detail nobody mentions in the textbooks: posteriorly tilt the pelvis. Have the patient actively draw their belly button toward their spine and tuck their tailbone slightly. You can verify this by placing your hand on their anterior superior iliac spine and feeling it move posteriorly. Without that pelvic tilt, the stretch just translates into lumbar extension. Hold for 30 to 45 seconds. Repeat three times. That's it. That's the whole protocol for a basic passive stretch. The reason this works better than the half-kneeling version is that supine positioning eliminates the ability to compensate with lumbar lordosis. Gravity provides a consistent, quantifiable load. There's no ground reaction force to brace against. The stretch magnitude is determined entirely by where you place the hip. Now here's the part that caught me off guard early in my career. I had a patient — construction worker, 42 years old, chronic low back pain with what I thought was a tight right iliopsoas. We did the stretch exactly as described above for six weeks, three times a day. He reported zero change in his symptoms. Not one improvement. I was frustrated because everything in the literature said this should work. So I went back and re-evaluated. Turns out his psoas wasn't the problem. His L4 nerve root had mild irritation from a degenerative disc, and the pain was referring into the anterior hip region. The iliopsoas was fine. It was just being blamed. This happens more often than you'd expect. Radiculopathy, sacroiliac joint dysfunction, and even femoroacetabular impingement can all refer pain to the anterior hip and mimic iliopsoas tightness. If a patient doesn't respond to a proper stretch protocol within three to four weeks, stop stretching and reassess the differential diagnosis.
Another nuance that people miss: the psoas major has a unique relationship with the lumbar vertebrae. It attaches to the transverse processes and vertebral bodies of T12 through L5. When you stretch the iliopsoas, you're also loading the thoracolumbar junction. For patients with any degree of spinal instability, spondylolisthesis, or recent disc pathology, aggressive hip extension can aggravate their condition. In those cases, stick to gentle range of motion without going into hip extension beyond neutral. The stretch intensity should be around a 3 out of 10 on the discomfort scale, not the 6 or 7 that most patients push for. The tissue adapts to moderate, sustained loading. Aggressive stretching triggers a protective muscle spindle response that actually increases tone. For the intermediate approach, add a rotation component. From the supine position with the hip flexed to 90 degrees and knee extended, passively rotate the hip internally by allowing the lower leg to drop medially. This changes the line of pull along the iliopsoas fibers and can reach regions that straight hip extension doesn't. Hold for 30 seconds. Then externally rotate by letting the leg fall laterally. Again, 30 seconds. The internal rotation stretch is particularly useful for athletes who spend a lot of time in hip flexion with external rotation — runners, cyclists, dancers. Their iliopsoas adapts to that specific position and needs the counter-movement to re-establish length across all planes. There's a version I use sometimes for patients who can't tolerate the supine stretch. It's the seated figure-four variant. The patient sits on a chair or the edge of the table with feet flat. Cross the affected ankle over the opposite knee, then lean forward from the hips while keeping the spine neutral. This produces a stretch through the posterior hip capsule and gluteal region that indirectly loads the iliopsoas through reciprocal inhibition. It's gentler but also less specific. I'd classify this as a supplementary technique rather than a primary one.
Get the Full Details

Frequency matters more than most people realize. A single daily session won't produce meaningful change in tissue length. The collagen network in a shortened iliopsoas responds to repeated, sustained loading over multiple days. I recommend three sessions per day minimum, spread across the day rather than clustered together. Morning, afternoon, evening. Each session takes about five minutes total. That's a very small time investment for what you get out of it. The timeline for results varies. Most patients notice some improvement in range of motion within two weeks. Complete resolution of a chronic shortening — and I mean truly chronic, lasting years — can take eight to twelve weeks of consistent work. Don't expect faster results. The fascia and connective tissue remodel slowly. Anyone promising you'll fix a year-old tight hip flexor in two days is selling something other than physical therapy. One more thing that surprised me clinically. I started noticing that some of my patients who stretched their iliopsoas daily actually got worse at certain movements. Their hip extension improved, yes, but their squat depth decreased and they reported feeling unstable during lunges. After some reflection, I realized what was happening. The iliopsoas is also a hip flexor and a stabilizer of the lumbar spine during loaded movements. Over-stretching it without accompanying strength work reduces its capacity to stabilize the spine under load. The workaround was straightforward — add hip flexor strengthening exercises after the stretching protocol. Eccentric contractions specifically. Single-leg Romanian deadlifts, slow eccentric squats with emphasis on the descent phase, and resisted hip flexion with bands. Three sets of eight to twelve repetitions, twice per week. This rebuilds the length-tension relationship that stretching alone disrupts. Stretching without strengthening is just making the muscle longer and weaker. That's not a good outcome for anyone who moves under load.
If you're reading this as a patient doing stretches on your own, here's what I'd say. Start with the supine technique. Lie on your back, pull one knee toward your chest, then slowly lower that leg toward the floor while keeping your lower back pressed into the surface. If your back arches, you've gone too far. Stop and reduce the range. Breathe normally. Don't hold your breath. Do it three times a day. Be patient. If after three weeks you haven't noticed any change, or if the stretch causes sharp pain rather than a dull pulling sensation, stop and see a qualified professional. Sharp pain is a signal that something else is going on, and more stretching won't fix it.