How Nightmare Rewriting Actually Works
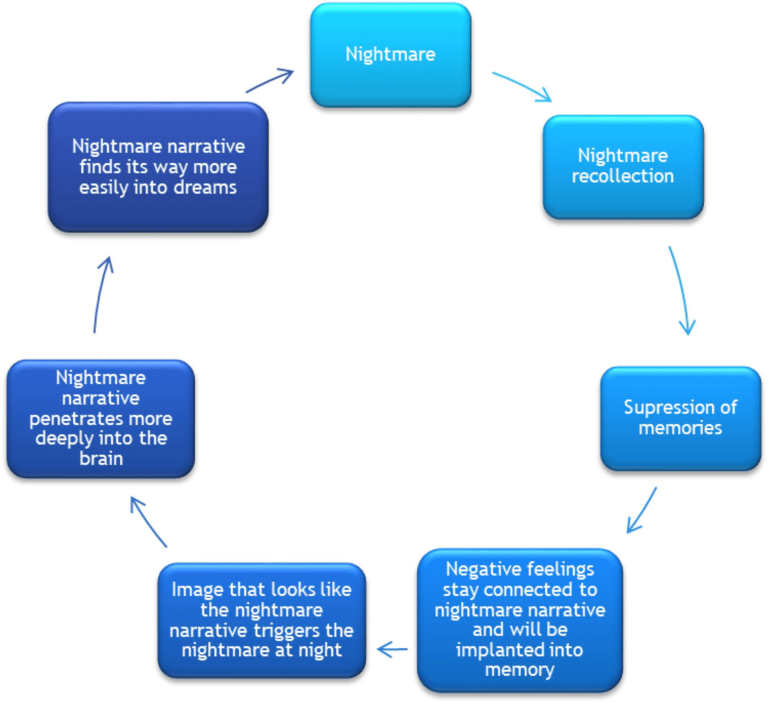
Imagery Rehearsal Therapy starts with a recurring nightmare. You write it down verbatim first. Not a summary, the actual scene — waking sweat, specific details, the moment it becomes unbearable. Then you pick the most distressing part and change it. This isn't positive thinking. You're literally editing the memory trace before it consolidates overnight. Cohen developed this in the late 1980s while working with combat veterans who couldn't stop having the same combat nightmares for years. Standard exposure therapy wasn't touching it. What he found was that sleep-related memories are partially reconsolidated each time you dream them, which means they're temporarily malleable. If you intervene between the dream and the next sleep cycle, you can shift the emotional valence of the entire sequence. That's the mechanism. Everything else is just paperwork.
Using Imagery Rehearsal Therapy Worksheets
A standard worksheet has five sections, though people tend to overcomplicate this. Section one asks for the nightmare as-is. Write it like you're describing a video. Keep it clinical. Section two is the rewrite. This is where most people go wrong because they make the new ending too dramatic. A nightmare about being chased doesn't need to become a scene where you turn around and defeat the chaser. It just needs to become a scene where you find the door and walk away, or the chaser loses interest, or you wake up in your actual bed. The brain accepts mundane resolutions faster than heroic ones because they don't trigger disbelief. Section three is repetition. You read the rewritten version aloud every day for ten minutes. Morning and evening. Ideally before and after sleep, but that's not strictly necessary. The key is consistency across multiple days, not intensity in a single session.
The Parts Nobody Talks About
Most people skip the grounding step before they even open the worksheet. If you're already in a hyperaroused state when you try to rewrite a nightmare, your amygdala won't let the new version stick. You'll read through the rewrite and your body will still be bracing for the original threat. I used to see this constantly with clients who'd come in after a particularly bad night and immediately wanted to "fix it." I'd make them spend fifteen minutes doing box breathing or listing five sensory details in the room first. Once their heart rate dropped below the activation threshold, the rewrite actually worked. Without that step, the worksheet is just journaling with extra steps. Another thing that trips people up: the rewrite needs to be specific enough to visualize but flexible enough to not feel like another script you're forced to follow. I had a client whose new ending always involved a character named "Officer Daniels" appearing to resolve the scene. After three weeks, the brain started adding Officer Daniels automatically, which defeats the purpose because now the relief is externally dependent rather than self-generated. She switched to her own voice in the rewrite and the breakthroughs accelerated within a week. There's also the issue of trauma networks that fire together. Sometimes the nightmare you're rehearsing is just one node in a cluster. You'll rewrite the chase scene perfectly, sleep well for four nights, then have a different nightmare that's emotionally identical but scenario-adjacent. That's normal. The brain hasn't learned the new pathway yet — it's still using the old one because the old one connects to other fear memories. Keep going. This usually resolves within two to three weeks of consistent practice.
Get the Full Details

When It Doesn't Work
IRT doesn't work for everyone and it's worth knowing when to stop pushing it. People with active dissociative disorders sometimes can't form coherent mental images at all. The worksheet becomes impossible because the imagery component is offline. In those cases, grounding-based protocols or EMDR come first. Severe insomnia from any cause will also undermine the reconsolidation window — if you're sleeping less than four hours a night, the memory isn't cycling through REM sleep properly and the rehearsal has nowhere to embed. There's also a small subset of clients where the rewrite backfires. Instead of reducing distress, the new imagery triggers a different fear response because the brain interprets the altered outcome as a sign that the original threat is still present and now something else is wrong too. I've seen this twice in practice. Both times the client went back to the original nightmare imagery and worked with a therapist on paced exposure first. The IRT came back later and stuck.
A Practical Setup
Print a simple one-page sheet with four fields: Nightmares this month, Most frequent nightmare, Written rewrite, Hours rehearsed. Track for fourteen days. The format matters less than the repetition. A half-sheet of notebook paper works. The digital versions floating around are fine but they add unnecessary choices — color coding, multiple pages, guided prompts — that slow you down. The actual intervention is writing and rereading. Speed matters more than aesthetics. If you're working through this alone and the nightmares haven't changed after twenty-one days of consistent practice, that's a signal to bring in a clinician. Not because the method failed, but because there may be something underneath the imagery that the worksheet alone can't reach. IRT is targeted. It's not a catch-all. But for the right case — a single recurring nightmare, stable enough mental state, capacity for visualization — it's one of the higher-yield interventions you can do on your own.