Using Imaging Anatomy Of The Human Brain A Comprehensive Atlas Including Adjacent Structures in Clinical Work
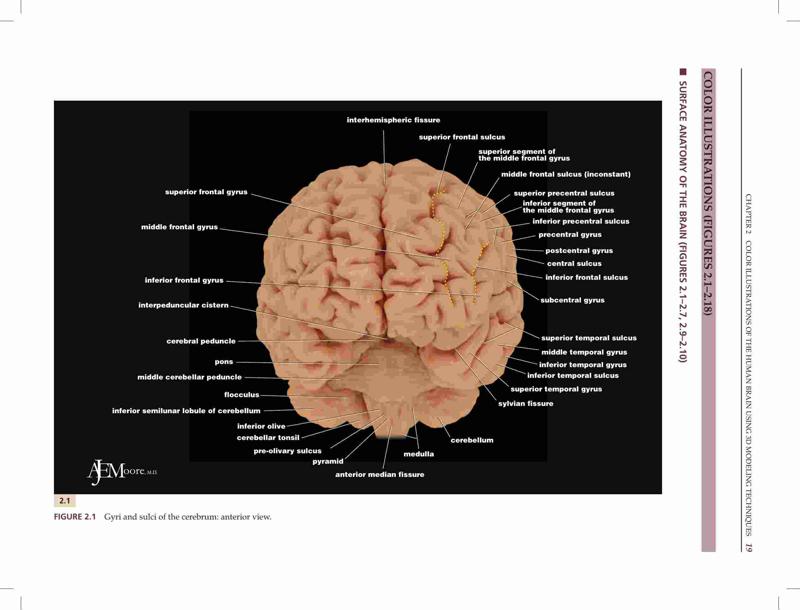
I still keep a physical copy of Imaging Anatomy Of The Human Brain A Comprehensive Atlas Including Adjacent Structures on my desk. Digital versions are convenient, but when you're trying to cross-reference a small subarachnoid collection with the nearby venous drainage pattern, having the plates right there saves time. The book itself was put together by a team of neuroradiologists and neuroanatomists, and it covers conventional MRI sequences alongside CT and a few surgical anatomy correlations. The atlas is organized by anatomical region rather than by pathology. You get axial, coronal, and sagittal plates at each level with labeled structures. The adjacent structures section — orbits, skull base, temporal bone, cervical spine — is where this diverges from the typical standalone brain atlas. That's also where I've found it most useful and where it trips people up if they're not careful.
Imaging Anatomy Of The Human Brain A Comprehensive Atlas Including Adjacent Structures
Here is how I actually use it during my reading day. I start with the region that matches the clinical question. If a patient comes in with facial numbness, I go straight to the trigeminal cistern plates and the Meckel's cave section. I flip through the labeled diagrams first to orient myself on the relevant neurovascular relationships at that level, then I pull the patient's DICOM series and scroll through matching slices. The atlas doesn't replace your PACS workflow, but it does help when the anatomy on screen looks ambiguous. The labeling is consistent across plates, which matters more than you might think. Different atlases use different conventions for naming the same structure. This one sticks to a fairly standard nomenclature, which reduces the back-and-forth mental translation when you're reading under time pressure. One thing beginners miss is the scale. The anatomical plates are rendered at a relatively large size compared to what you see on a typical clinical workstation. That makes fine structures look clearer than they appear on routine protocol. A small meningioma at the petrous apex that is barely perceptible on a standard T2 sequence becomes more obvious once you understand the normal tissue planes from the atlas. It does not mean the atlas is giving you a better image. It means the illustration strips away the noise so you can recognize the architecture.
There is a specific problem I ran into a few years ago that illustrates the practical value and also the limitations. A patient presented with isolated horizontal diplopia. The clinical exam pointed toward a sixth nerve palsy, but the initial MRI read as normal. I went back through the atlas to the caudal pons and lower medulla plates, specifically the sections showing the dorsal exit zone of the abducens nerve. On the patient's thin-slice T2 fat-saturated images, there was a subtle hyperintensity along the nerve just before it pierced the Dorello canal. It was easy to overlook because the signal abnormality was tiny and the slice thickness was two millimeters. The atlas plate for that exact region showed the normal course and the expected relationship to the petroclival ligament. Comparing the two side by side made the finding undeniable. I revised the report and the patient ultimately had a small vascular loop compressing the nerve, confirmed on high-resolution FIESTA imaging later. The workaround that helped in that case was simply printing the relevant atlas plate at 100 percent and laying it next to the monitor. No special software, no registration. Just visual comparison. Digital overlay tools exist, but they add steps and often introduce misalignment that makes the exercise worse. When I talk to residents about this atlas, the most common question is whether to pair it with an online resource. My answer depends on their level. For PGY-2 or early PGY-3, the atlas alone is sufficient for building the structural foundation. Once they are doing independent reads, they should supplement it with open-access materials like Radiopaedia or the ACR Appropriateness Criteria for sequence-specific guidance. The atlas will not tell you which protocol to order. It assumes you already know that part.
Get the Full Details

A few technical points that matter more than people realize. The plates are not sourced from a single scanner or a single field strength. Some images come from 1.5T studies and some from 3T. Signal characteristics of normal structures shift slightly between field strengths, particularly CSF on T2 and the gray-white matter differentiation on T1. The atlas acknowledges this in the preface but does not annotate every plate with the field strength used. If you are learning on 3T images and referencing a plate captured at 1.5T, subtle differences in appearance can be misleading. I have caught myself second-guessing a normal variant because the atlas representation did not quite match the higher-resolution 3T appearance of the same structure. Another nuance that trips people up is the representation of venous structures. The atlas shows the dural venous sinuses and superficial cortical veins clearly, but the detail is more schematic than photographic in many cases. On a real scan, venous varices, prominent arachnoid granulations, and asymmetric sinus development are common and can mimic pathology if you do not know the normal spectrum. The atlas plates smooth over that variability to some degree. I always keep a separate resource like the venous anatomy sections in Rhoton's microsurgical atlases nearby when I am reading cases that involve the posterior fossa venous drainage. The adjacent structures coverage is a genuine strength. The orbital apex, the petroclival junction, the foramen magnum region, the cervical spinal cord at C1-C2 — these are areas where standalone brain atlases typically fall short. The atlas dedicates actual plates to these zones rather than skimming them. For anyone who reads head and neck imaging occasionally, that dedicated coverage is worth the purchase price alone.
There are downsides, and I want to be blunt about them. The publication date means the imaging protocols represented are somewhat dated. Modern accelerated sequences, quantitative susceptibility mapping, and multi-shell diffusion are not covered. If your practice relies heavily on those techniques, the atlas will not help you interpret the new contrast mechanisms. It is a structural reference, not a methods reference. The book is also heavy and awkward to carry between reading rooms. I got a PDF version for travel, but the resolution on the color plates does not hold up well when you zoom in on a tablet. I prefer the physical copy for detailed study and the PDF only for quick lookups on a laptop when I am away from the main reading station. If you are trying to decide whether to invest in this, here is a practical filter. If your work involves neuroradiology fellowship training, neurosurgery residency, or head and neck radiology, this atlas is one of the more complete single-volume references available. If you are a general radiologist who reads a handful of brain MRIs per week and never deals with skull base or orbital pathology, you might get more utility from a focused neuroimaging primer instead. The breadth of this atlas is its advantage and its limitation at the same time.
I keep mine on the shelf next to my copy of Neuroanatomy Through Clinical Cases. The two complement each other well. One gives you the clinical reasoning framework. The other gives you the high-resolution anatomical reference. Together they cover most of what I need without reaching for a third volume.

Practical Tips for Getting the Most Out of This Resource
Start with the axial plates and work your way through the coronal and sagittal views for the same level. The cross-referencing builds spatial understanding faster than studying each plane in isolation. I spend about twenty minutes each morning flipping through a random section before I start my reads. It keeps the anatomy fresh without requiring a dedicated study session. When you encounter an unusual variant on a patient scan, go back to the atlas and check the normal range first. Most apparent anomalies are just normal variants that look strange because you have only seen the typical presentation. The atlas shows enough variation to help you distinguish real pathology from benign anatomical diversity. Print the plate you need. Do not rely on screen capture. The color calibration on monitors varies too much, and the fine line work in the illustrations loses detail when digitized. A clean printout lets you annotate with a pencil and flip it against the monitor without losing focus on the task.
The atlas is not a substitute for understanding basic cross-sectional anatomy from a textbook like Gray's Anatomy for Students or Netter's. It assumes you already know the fundamentals. If you are struggling to identify basic structures on a routine MRI, the atlas will feel overwhelming. Build the foundation first, then use this as your reference tool. For download options, the physical book is available through major medical publishers and academic bookstores. The digital version, if offered through your institution's library, tends to have the same plate quality as the print edition. Be cautious with pirated PDFs circulating on informal forums. The image quality is often degraded, and the pagination gets scrambled, which makes cross-referencing a nightmare. Your institution likely already has a license through EBSCO, ProQuest, or a similar aggregator. Check there first before looking elsewhere. I have been using this atlas for several years now, and it has not lost its usefulness. New imaging techniques come and go, but the underlying anatomy does not change. That is why a good structural atlas outlasts any single imaging protocol. The brain looks different on DWI than it does on FLAIR, but the caudate nucleus stays in the same place regardless of the sequence you are using.