Getting Through the Imbruvica Fda Approval History Without Losing Your Mind
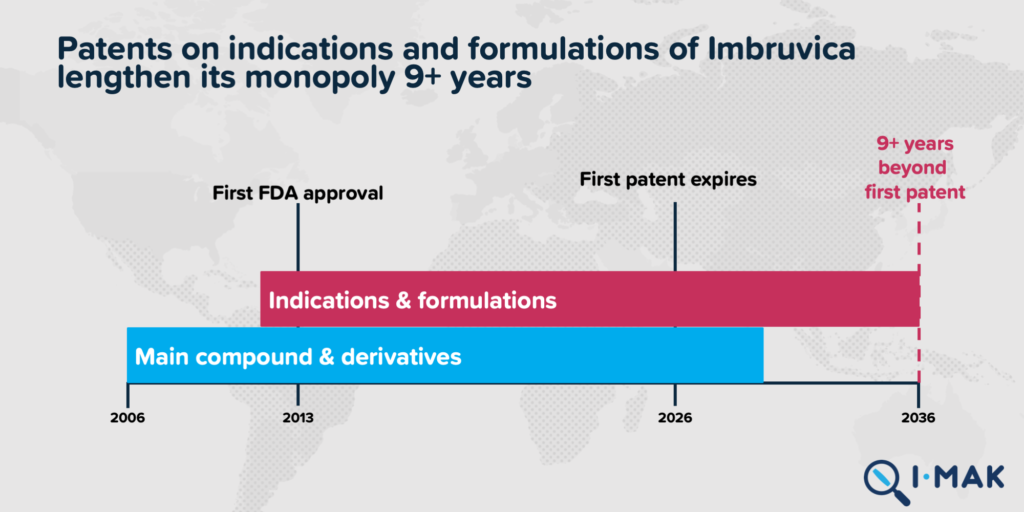
When you're working in oncology drug development or compliance, pulling together the Imbruvica Fda Approval History is one of those tasks that sounds simple until you start digging. The drug is ibrutinib, a BTK inhibitor originally from Pharmacyclics before AbbVie bought them out. The timeline itself is well-documented, but the actual value is in understanding the sequence and the regulatory strategy behind each filing. The first approval came through in November 2013 for mantle cell lymphoma in patients who had received at least one prior therapy. That was an accelerated approval under the oncology pathway. The pivotal trial was BRiCK, a single-arm study showing response rates around 58% in heavily pretreated MCL patients. Not exactly huge numbers by some standards, but in that population with limited options, it was enough for the FDA to grant approval. Then in February 2014, about three months later, the indication expanded to include chronic lymphocytic leukemia. This was based on the RESONATE trial, which compared ibrutinib to ofatumumab in previously treated CLL. The progression-free survival benefit was significant enough to support the label expansion. I recall sitting through the oncology drugs advisory committee meeting transcripts during that period, and the discussion around cardiovascular safety signals was already coming up. Those signals would shape labeling for years to come.
The marginal zone lymphoma approval came later, in June 2016, based on the PCN-1003 trial data. Then WM in January 2017. The CLL extension for first-line treatment happened in October 2017 following the iLLUMINATE trial results, which showed ibrutinib plus lenalidomide outperforming chlorambucil plus lenalidomide.
How This Actually Plays Out in Practice
What nobody tells you when you're asked to compile this kind of history is how much legwork goes into verifying each date and indication against primary sources. The FDA database has the information, but it's scattered across different submission types. The original NDA (125523) for MCL is one document. The supplemental BLA filings for each new indication are separate. Pharmacyclics' corporate restructuring under AbbVie adds another layer of confusion because the sponsor information changes mid-stream. I spent about two days once cross-referencing the approval dates with the Federal Register notices and the actual FDA drug approval letters. The published dates can differ depending on whether you're looking at the Accelerated Approval date versus the full approval date. For MCL, the accelerated approval was November 13, 2013, and the full approval came later on January 20, 2017. That four-year gap matters if you're tracking regulatory milestones for a portfolio analysis. One thing that trips people up is the post-marketing commitment tracking. After the initial MCL approval, the FDA required Phase 4 studies confirming clinical benefit. The CONNECT trial was one of them. If you're documenting the Imbruvica Fda Approval History for a regulatory file or a competitive intelligence report, you need to note which approvals remain under accelerated pathways and which have been converted to traditional approval. As of my last check, the MCL indication had completed its confirmatory trial requirements, but not all supplemental indications went through the same conversion process.
Get the Full Details

Counter-Intuitive Details Most People Miss
Here's something most summaries get wrong: the 2014 CLL approval wasn't just a straightforward indication expansion. The label for CLL initially carried specific warnings about hemorrhage risk and atrial fibrillation that were less prominent in the MCL label. The dosing recommendations also differed slightly between indications. When you're compiling this for a formulary review or a health economics analysis, treating the approvals as identical copies of the same drug misses real clinical and regulatory distinctions. Another detail that gets overlooked is the orphan drug designation angle. Ibrutinib received orphan drug status for several indications before they got full approval. MCL, WM, and CLL all had orphan designations. That matters for pricing and market exclusivity calculations, and it's part of what made the accelerated approval pathway viable. The combination of orphan designation plus accelerated approval created a regulatory shortcut thatAbbVie exploited effectively across multiple indications. The patent dispute history also complicates any complete picture. Generic ibrutinib manufacturers challenged the patents, and the FDA approval timeline intersected with the Orange Book listings in ways that affected when generics could actually reach market. If you're researching this for a business development reason rather than a purely regulatory one, that intersection is where the real complexity lives.
Where This Information Falls Short
The FDA approval history for Imbruvica is well documented for the United States, but it doesn't capture the parallel regulatory journeys in the EMA, PMDA, or other markets. The European approval came through in July 2014 for CLL and MCL, which is close but not identical timing. If you're building a global regulatory timeline, you need separate research for each jurisdiction. The approval indications also diverge somewhat — the EMA approved ibrutinib for chronic graft-versus-host disease in 2022, which the FDA has not yet done. Also worth noting: the FDA approval letters and the actual prescribing information are not always in perfect alignment. The label gets amended frequently through supplementary submissions, and the approval date doesn't necessarily reflect when the most current label was filed. If precision matters for your work, don't rely on a single summary document. Pull the original approval letters from the FDA website and check the label amendment history separately.