What Actually Goes Into a Mobility Care Plan
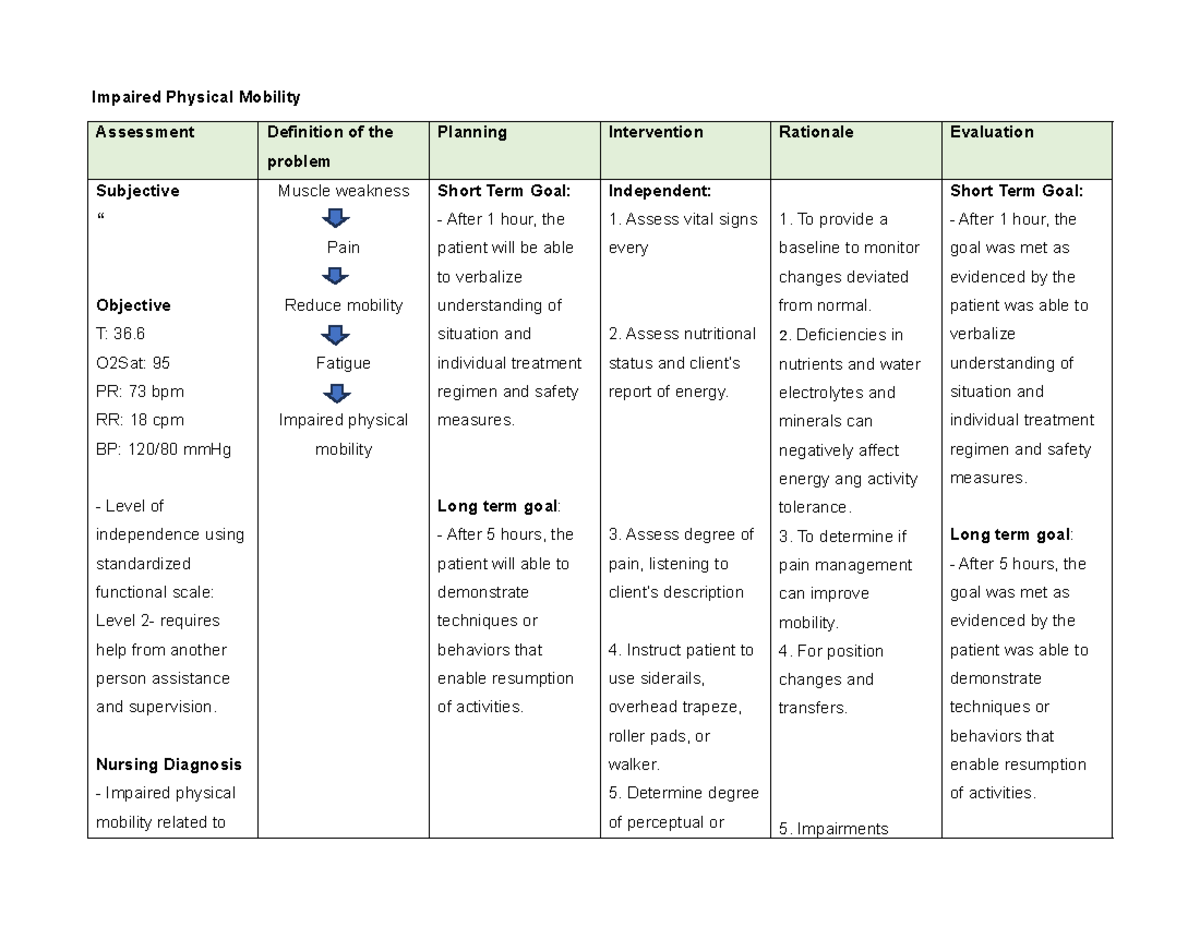
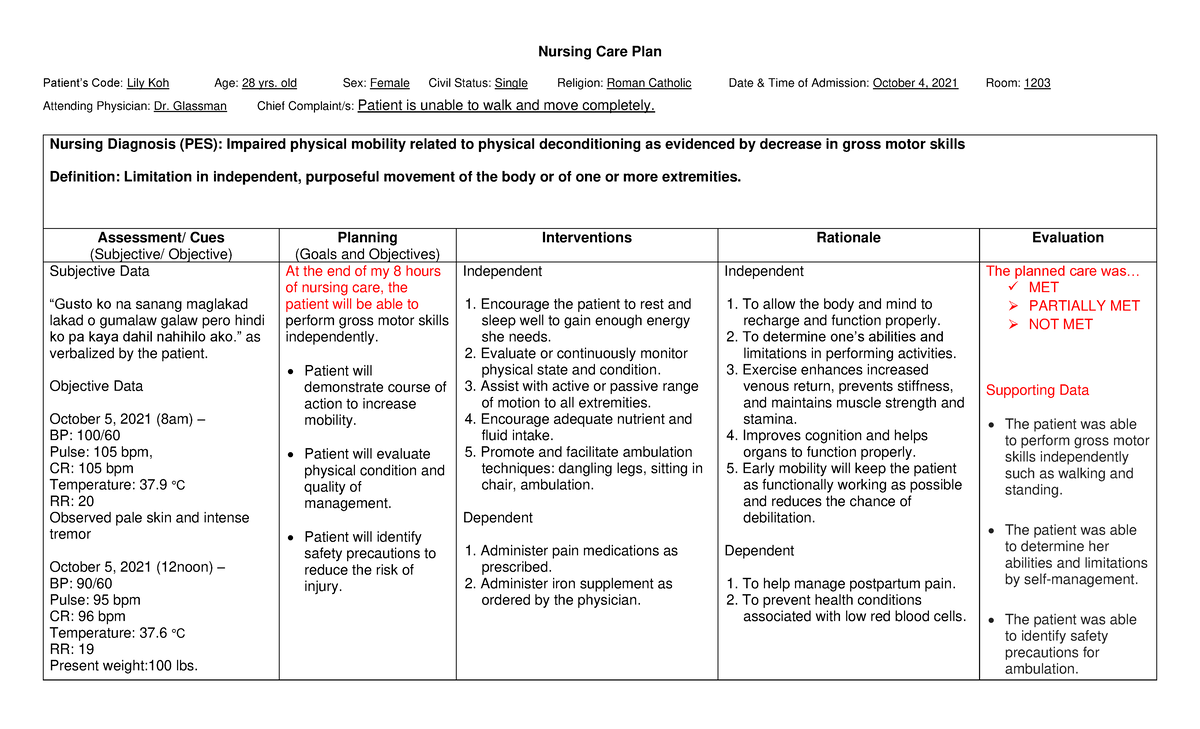
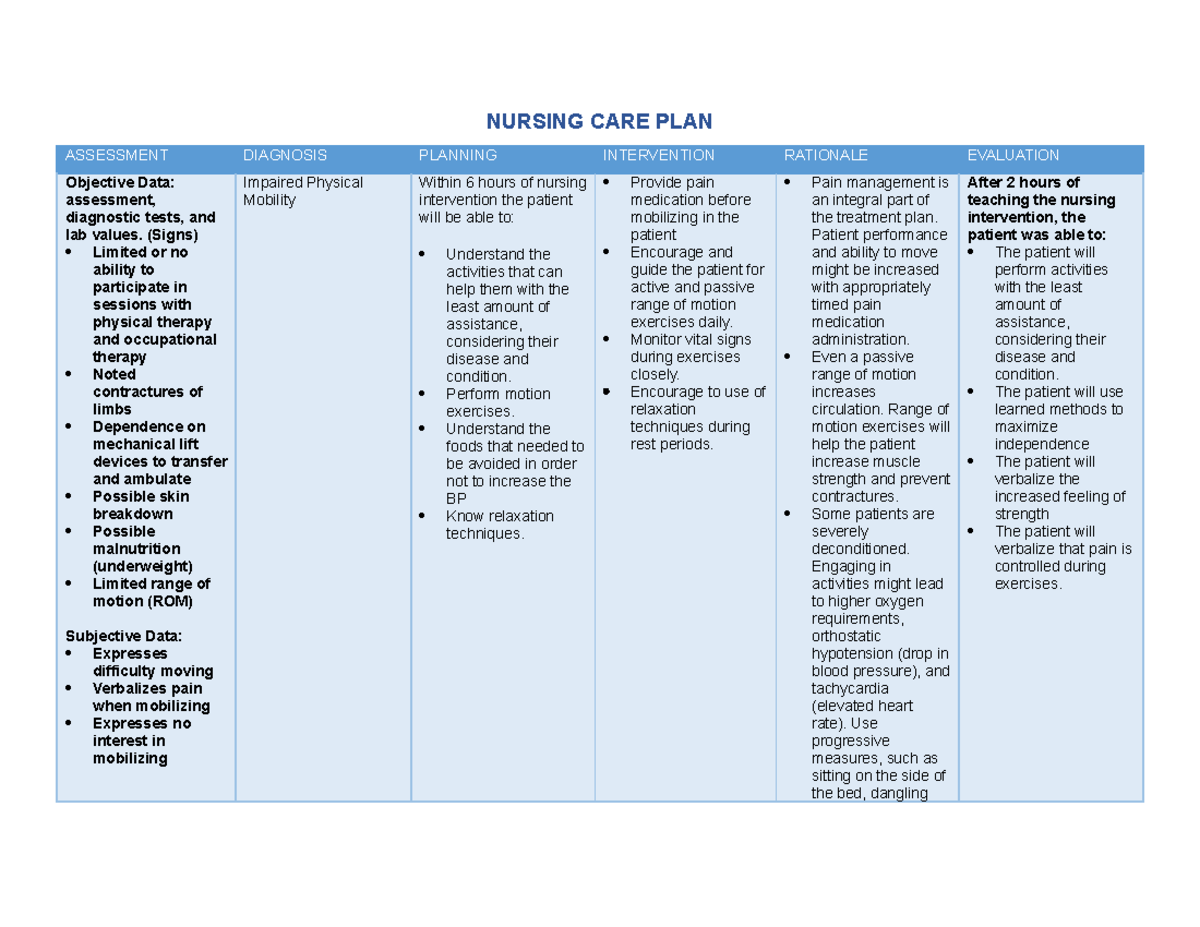
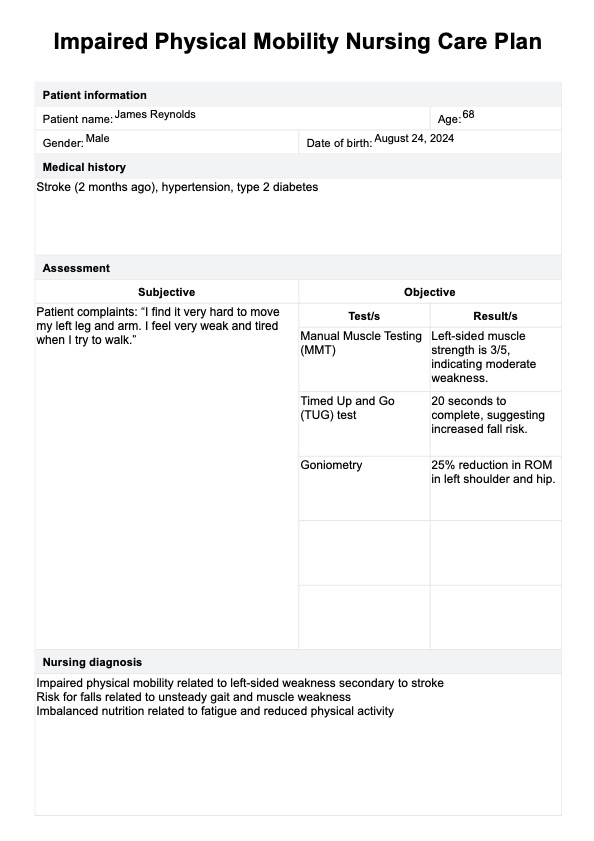
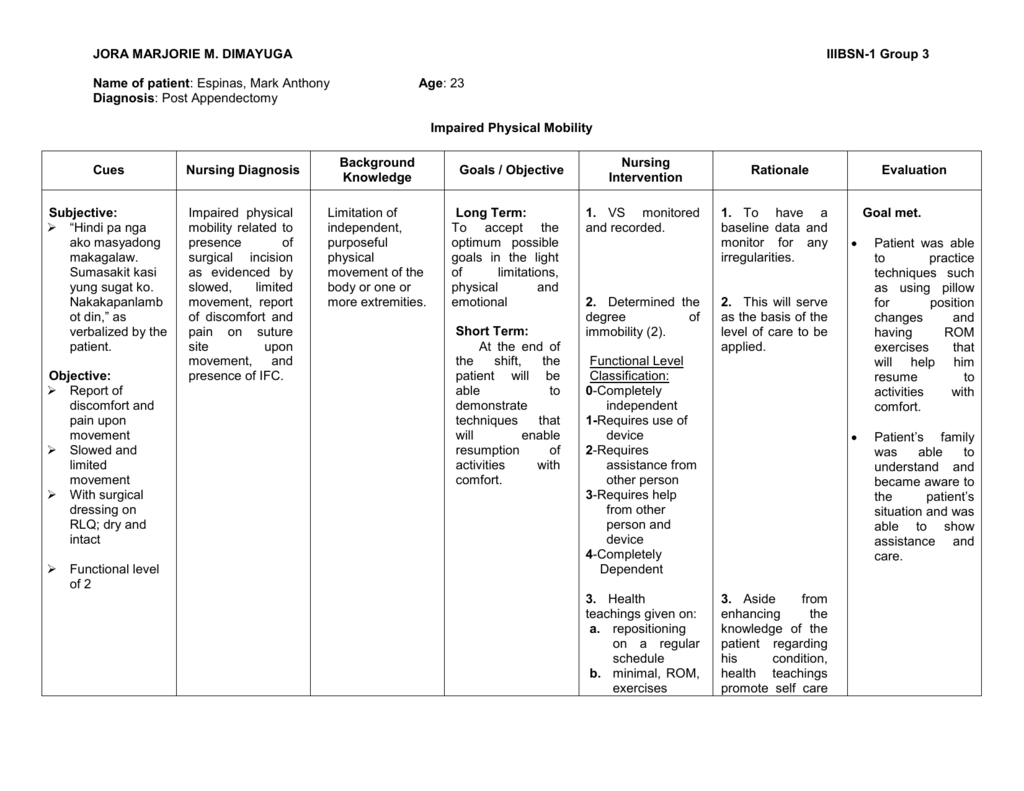
A nursing care plan for impaired physical mobility is a structured document that outlines assessment findings, diagnoses, goals, interventions, and evaluation criteria for patients who have limited movement. It is not something you fill out and forget. The document needs to be specific enough that any nurse covering a shift can read it and understand exactly what to do, when to do it, and how to recognize if the patient is getting worse or better. I started working with these plans back when we were still using mostly paper charts in a med-surg unit. One of the first things I learned was that generic templates don't cut it. You can write "reposition q2h" all day, but if the patient has a hip fracture with weight-bearing restrictions and a concurrent DVT risk, that one line doesn't tell the whole story. The plan needs to account for the actual clinical picture. The assessment phase is where most people rush through, and that creates problems downstream. You need a thorough mobility assessment that goes beyond the standard Glasgow Coma Scale or basic vital signs. I use the Braden Scale for pressure ulcer risk, but I also document the patient's actual range of motion in each joint, their muscle strength using the 0-5 MRC scale, their ability to perform transfers independently or with assistance, and their balance during standing attempts. Documenting that a patient can roll from supine to side-lying with minimal contact guard assistance but cannot sit to stand without moderate assistance tells you more than a blanket "mobility impaired" label ever would.
After assessment comes the nursing diagnosis. The NANDA-I label here is "Impaired Physical Mobility," but the related factors matter enormously. Is it related to neuromuscular impairment? To immobility secondary to pain? To deconditioning? To cognitive deficit? The related factor determines everything that follows. If the mobility issue stems from uncontrolled pain, your interventions should prioritize pain management before mobilization. If it is neurological, you are looking at different strategies entirely. I had a patient once who seemed completely non-compliant with repositioning. Turns out the "non-compliance" was because he had severe peripheral neuropathy and every time we moved him, he experienced burning pain so intense he would clamp down and refuse to cooperate. Once we adjusted the pain regimen and switched to smaller, more frequent repositioning rather than big moves, the whole dynamic changed. The diagnosis was still impaired physical mobility, but the underlying cause was neurologic pain, not psychological resistance. Goals should be measurable and time-bound. "Patient will improve mobility" is not a goal. "Patient will sit at the edge of the bed for 10 minutes with standby assistance by day 3" is a goal. I like to set both short-term and long-term goals. Short-term goals address immediate safety and prevention of complications. Long-term goals address the actual functional improvement the patient is working toward. Interventions are where the real work happens. Let me walk through what this looks like in practice on a typical shift-based plan.
Repositioning is obviously central, but the specifics are what separate a competent plan from a mediocre one. Q2H repositioning is the baseline, but you need to specify the positions. Sequential positions matter: supine, left lateral, right lateral, prone if tolerated, high Fowler's with proper support. You need to document heel suspension devices, pillow placement under the calves to eliminate pressure on the posterior calcaneus, and the use of pressure-redistributing surfaces. I once worked with a patient who kept developing sacralStage 2 ulcers despite being repositioned every two hours on schedule. The breakthrough came when I noticed the pillows we were using under the knees were creating a shear force as the head of the bed was elevated. Switching to a knee-height pillow that maintained neutral hip alignment and eliminating direct pressure under the popliteal space resolved the issue. The intervention looked the same on paper but the execution made the difference. Skin assessment needs to be systematic. I document the condition of the sacrum, greater trochanters, posterior heels, scapulae, occiput, and elbows at every repositioning cycle. Color, temperature, integrity, and any areas of non-blanchable erythema get noted. Using a standardized skin assessment tool like the NPUAP staging system keeps documentation consistent across nurses. Range of motion exercises form another critical component. Passive ROM is indicated when the patient cannot initiate movement themselves. Active-assistive ROM when there is some voluntary participation. Active ROM when the patient can move independently through the available range. I document the specific joints addressed, the number of repetitions, the patient's tolerance, and any increase in pain or spasticity during the exercises. A patient with a stroke on the left side might have good ROM in the right upper extremity but significant contracture risk in the left shoulder. Targeting the at-risk joints prevents complications that are much harder to reverse later.
Get the Full Details

Transfer training and ambulation protocols need to be clearly defined based on the patient's weight-bearing status and assistive device requirements. If the patient is partial weight-bearing, that percentage needs to be stated. If they require a Hoyer lift, the staff need to know how many people are required and what the procedure is. I had a case where a post-surgical patient was documented as "ambulate with walker" but the plan never specified that the walker needed to be a pick-up type due to upper extremity weakness, and the patient kept dropping the front-legs model during transfers. Updating the equipment specification in the plan prevented several near-falls. Pain management before mobilization activities is not optional. I typically plan to administer prescribed analgesics 30 to 45 minutes before physical therapy sessions or structured repositioning schedules for patients who report moderate to severe pain with movement. Documenting the timing relationship between medication administration and mobility activities helps the team understand why a patient may be more or less cooperative at different times of day. Nutritional support deserves attention in the mobility care plan because protein-energy malnutrition directly impairs muscle strength and wound healing. I document current albumin and prealbumin levels, caloric intake percentage over 24 hours, and any nutritional supplements being provided. A patient eating less than 50 percent of meals consistently is going to lose muscle mass rapidly, which compounds the mobility problem. Noticing that pattern early and escalating a nutritional consult is part of the plan.
DVT prophylaxis runs parallel to mobility interventions. Early ambulation is the best natural prophylaxis, but when that is not immediately achievable, sequential compression devices and pharmacologic prophylaxis per provider orders are standard. Documenting the device settings, the leg measurements for proper SCD sizing, and the bleeding risk assessment keeps everything organized. Evaluation is where plans either work or they don't. I compare the patient's current functional status against the established goals at regular intervals. If the goal was to sit at the bedside with contact guard assistance by day 3 and on day 3 the patient still requires maximal assistance to achieve that position, the plan needs adjustment. Common reasons for goal non-achievement include uncontrolled pain, new medical complications, inadequate staffing for the intervention frequency, or goals that were simply unrealistic given the patient's overall prognosis. One counter-intuitive thing I learned is that sometimes doing less mobilization is the right call. A patient who is hemodynamically unstable, actively bleeding, or in severe uncontrolled pain may need mobility interventions temporarily restricted while the underlying issue is addressed. Writing "hold ambulation" with a clear clinical rationale and a planned reassessment time is legitimate documentation. It is not giving up. It is clinical judgment.
Another nuance that people miss is the difference between mobility and activity tolerance. A patient might have adequate strength and range of motion to transfer independently but have such poor cardiopulmonary endurance that they become dizzy and diaphoretic after three minutes of activity. The care plan needs to address both components separately. Mobility interventions and activity intolerance interventions are related but distinct, and conflating them leads to incomplete planning. The documentation should also include patient and family education components. Teaching a patient and their family how to safely reposition in bed, how to recognize early signs of skin breakdown, what movements to avoid based on their specific condition, and how to use assistive devices correctly extends the care beyond the hospital or clinic walls. I always include a teach-back verification in the plan to confirm comprehension rather than just assuming the information was absorbed. Interdisciplinary coordination is essential. The mobility care plan should reference communications with physical therapy, occupational therapy, nursing, and the attending provider. When PT evaluates a patient and recommends a particular transfer technique or level of assistance, that recommendation should be reflected in the nursing care plan so there is consistency across the team. I have seen cases where the care plan said one thing and the PT notes said another, and that creates confusion at the bedside.
Common Mistakes That Undermine These Plans
The most frequent error I see is writing interventions that are too vague to implement. "Encourage mobility" means nothing to a nurse trying to get a 200-pound post-abdominal surgery patient out of bed at 2 AM. Specificity saves time and prevents errors. Another common mistake is setting goals that are impossible given the patient's condition. Writing "patient will walk independently in hallway by discharge" for a patient who is 85 years old, newly diagnosed with congestive heart failure, and has not been out of bed in four days sets everyone up for failure. The goal should reflect the patient's actual baseline and realistic trajectory. Failure to update the plan as the patient's condition changes is the third major issue. A patient who improves rapidly may be ready for a higher level of assistance within days. A patient who develops a new complication may need the plan scaled back temporarily. Static plans are obsolete plans.
Poorly documented related factors lead to misdirected interventions. If the diagnosis says "related to neuromuscular impairment" but the actual problem is pain avoidance, the treatment will miss the mark. Taking time to clarify the etiology during assessment prevents this problem.
A Note on Documentation Efficiency
Writing comprehensive mobility care plans does not have to take forever. I found that using a structured template with dropdown selections for common interventions and required fields for goals and assessments cut my documentation time significantly. The key is making sure the template forces you to address the specifics rather than allowing you to submit a skeleton plan that looks complete on the surface but is empty in substance. Some institutions use standardized care plan protocols that auto-populate based on diagnosis codes. These can be useful starting points but should never be used verbatim without clinical customization. A stroke protocol and a hip fracture protocol share some interventions but diverge significantly on others, and merging them carelessly produces a plan that is technically correct in both areas and practically useless in both. The bottom line is that a well-constructed Impaired Physical Mobility Care Plan is a living clinical document that reflects the actual patient, not a boilerplate exercise. It guides daily nursing actions, communicates the plan across the care team, and provides a framework for measuring whether the interventions are working. Getting it right takes effort upfront but pays for itself in reduced complications, fewer adverse events, and more efficient care delivery.