Documenting What You Actually See, Not What the Chart Says
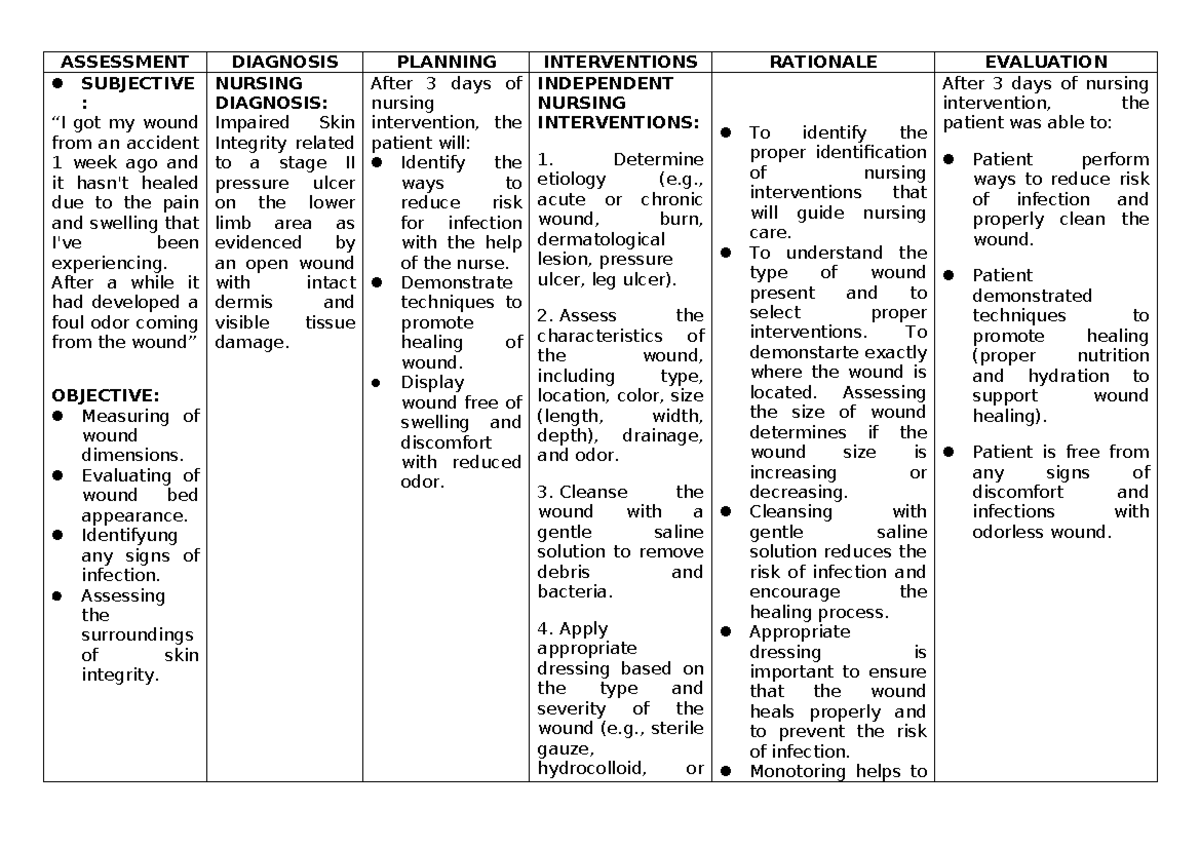
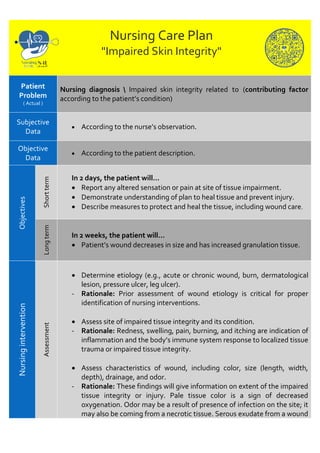
The biggest mistake I see new nurses make with impaired skin integrity isn't in the assessment itself. It's in how they write it down. They'll document Stage II pressure injury with a photograph that doesn't show depth, a size measured at only two points when three are needed, and a care plan that says "turn q2h" without noting what actually keeps the patient off that sacrum for more than twenty minutes. Documentation that reads like a checkbox exercise is legally worthless and clinically useless. Both things matter to me. This is a NANDA-I approved diagnosis defined as damage to the epidermis and/or dermis. The actual nursing diagnosis statement has three parts: the problem label, the related factor (etiology), and the defining characteristics (evidenced by). A properly written one looks like Impaired Skin Integrity related to prolonged pressure and shear as evidenced by non-blanchable erythema over the sacrum measuring 4cm x 3cm with partial-thickness skin loss. That's it. No poetry. Just the components that let another clinician understand exactly what's happening and what you believe is causing it. I spent four years working oncology and wound care before moving into case management. One thing that never gets taught properly in school is that the same skin breakdown presentation can have completely different etiological factors, and your related factor drives everything about the interventions. Pressure causes ischemia through sustained compression. Shear causes deeper tissue damage because the skin sticks to the surface while the underlying fascia and muscle slide downward. Moisture-associated skin damage from incontinence or exudate looks similar but requires a fundamentally different approach. Get the related factor wrong and your care plan is just expensive guesswork.
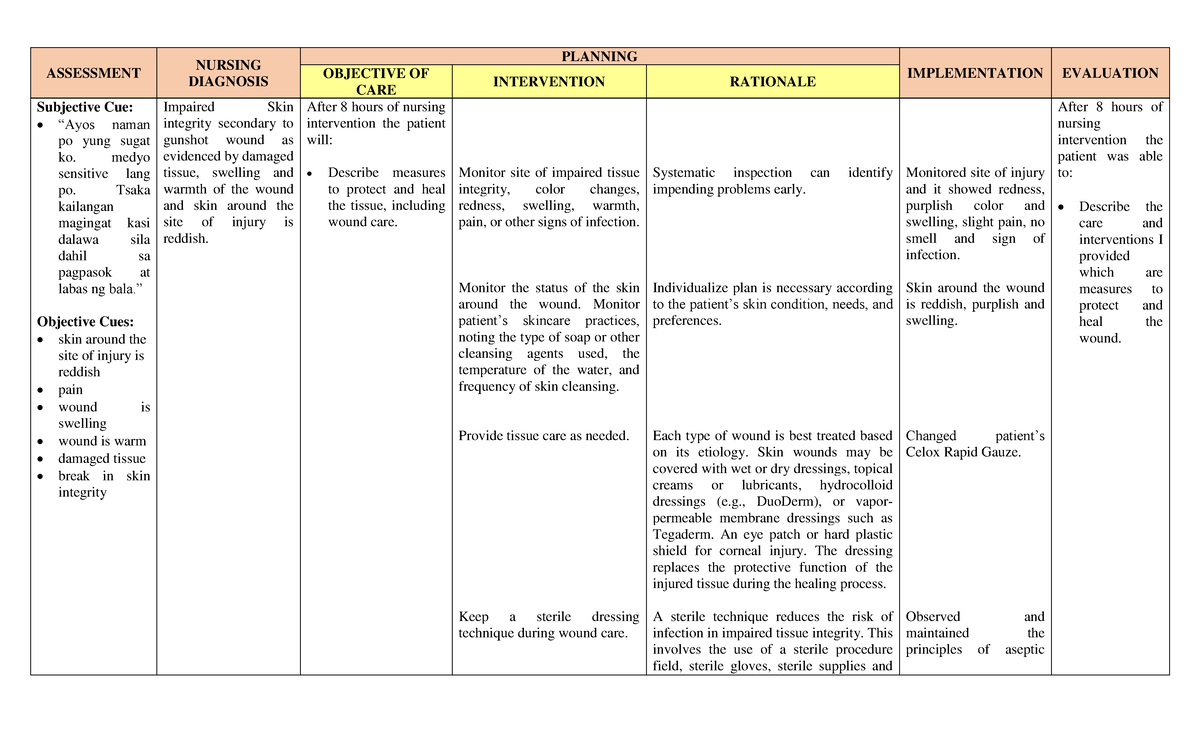
Here's something nobody tells you until they've made the mistake themselves. Braden scale scores are useful as a screening tool but they're not diagnostic. I had a patient who scored 16 on the Braden scale, which puts them in low-risk, and still developed a Stage III pressure injury under the heel within five days. Why? The Braden scale doesn't adequately account for hemodynamic instability, vasopressor use, peripheral vascular disease, or the fact that this particular patient's heels were suspended in traction. The scale told us she wasn't at risk. Her physiology told us she was. Always assess the skin directly regardless of what the score says. When you're writing the care plan, the defining characteristics need to be objective and measurable. Non-blanchable erythema is good. Red skin is vague. Full-thickness tissue loss with visible subcutaneous fat is specific. Unstageable pressure injury because the wound bed is covered in slough or eschar is also a valid classification but you have to document that you've attempted debridement or that the clinical evaluation confirms the stage cannot be determined. Staging assumptions based on visual inspection alone without clearing the wound bed will come back to haunt you during a chart audit. I ran into a complicated case last year involving a patient with impaired skin integrity secondary to combined pressure and medical device-related injury. The oxygen cannula had caused a Stage II pressure injury on the left nares that we'd missed for three days because we were focused entirely on the sacral wound. The nares injury was partially hidden by the device itself. The workaround was simple but it required me to physically remove the cannula during each assessment, document the nares separately on the skin integrity sheet, and switch to a high-flow nasal cannula system that eliminated direct contact with the nostrils. The nares healed in four days once we addressed the source. It was a reminder that device-related skin breakdown is the most overlooked category in any unit and it happens everywhere, not just ICU.
For intervention prioritization, remove the causative factor before you do anything else. Repositioning protocols are table stakes. What actually moves the needle is addressing the microenvironment around the wound. Moisture balance matters more than most nurses realize. An occlusive dressing on a moderately exuding wound will macerate the surrounding skin within hours. A transparent film over a heavily exuding wound is just creating a bacterial incubator. I use a algorithm that starts with wound bed assessment, then moisture level, then periwound skin condition, and finally selects the dressing based on those three variables rather than whatever the supply catalog has in stock that week. Nutrition is another area where documentation is routinely done poorly. Saying "poor nutrition" as a related factor without referencing albumin, prealbumin, weight trends, or oral intake percentages is insufficient. I track weight weekly, note whether the patient is completing less than fifty percent of meals, and correlate that with wound progress. Patients with impaired skin integrity who are consuming less than their estimated caloric needs will not heal regardless of how good your dressing selections are. Protein supplementation alone doesn't solve this either. You need total calories plus protein plus micronutrients like vitamin C and zinc. The wound care literature is pretty clear on this but hospital dietary services don't always connect the dots. One counter-intuitive thing about moisture management is that sometimes the best intervention for impaired skin integrity is actually keeping the skin dry in areas that aren't wounded. Periwound skin on a patient with chronic incontinence-associated dermatitis will degrade faster if you're constantly wiping it with standard wipes. I switched to no-rinse pH-balanced cleansers and barrier creams containing dimethicone instead of zinc oxide for the non-wounded areas. Zinc oxide is fine for the acute phase but it creates a film that interferes with subsequent assessments and makes it harder to see true skin color changes. Dimethicone barriers are breathable and they don't obscure the skin. This detail took me two years to figure out through trial and error.
Get the Full Details
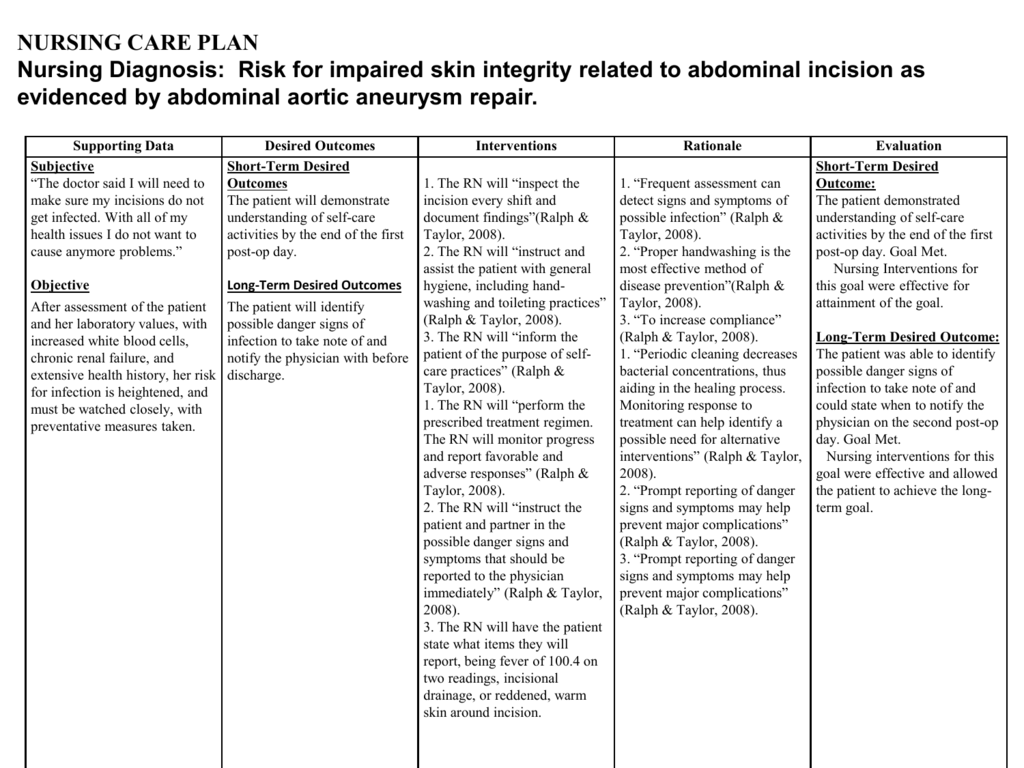
Education for patients and families is where care plans typically fall apart after discharge. You can write the most thorough plan on the unit and it means nothing if the patient transitions to a home environment without understanding the repositioning schedule, the signs of worsening breakdown, and the dressing change sequence. I create a one-page laminated handout for each patient that includes a repositioning schedule with specific angles, a photo of their wound with stage and dimensions noted, and a decision tree for when to call versus when to continue current protocol. The decision tree portion is what actually reduces readmissions for worsening pressure injuries. Without it, patients either ignore early signs or panic at minor changes. The downsides of the current nursing diagnosis framework for impaired skin integrity are worth acknowledging. The NANDA taxonomy doesn't have a separate category for medical device-related pressure injuries even though they're one of the fastest-growing categories in acute care. It also lumps together pressure injuries, surgical wounds, and traumatic skin losses under a single diagnosis label, which flattens important clinical distinctions. When you're documenting for interprofessional communication, this lack of granularity forces you to work around the framework rather than letting it serve you. Consider supplementing the NANDA diagnosis with a wound-specific classification system like the PAGS framework or the NPUAP staging system in your objective findings section so that the clinical picture isn't lost inside the nursing language. Evaluation criteria need to be tied directly to your measurable outcomes. Instead of "skin integrity will improve," write "periwound erythema will decrease by fifty percent within seven days" or "wound dimensions will reduce by at least twenty percent at the next formal assessment." These metrics give you a timeline for reassessment and a clear signal when the current plan isn't working. If a Stage II injury isn't showing any reduction in size after fourteen days of appropriate intervention, you're either missing an etiological factor or the wound has progressed to a higher stage. Both possibilities require a wound care consultation, not just more of the same dressing changes.
The bottom line is that impaired skin integrity nursing diagnosis works well when you treat it as a clinical reasoning tool rather than a documentation requirement. The assessment drives the diagnosis, the diagnosis drives the interventions, and the interventions are only as good as your ability to evaluate whether they're actually producing measurable change. Most of the failures I've seen trace back to one of three things: inadequate initial assessment, misidentified etiology, or static care plans that aren't updated when the wound doesn't respond. Fix those and the rest of the process becomes straightforward.