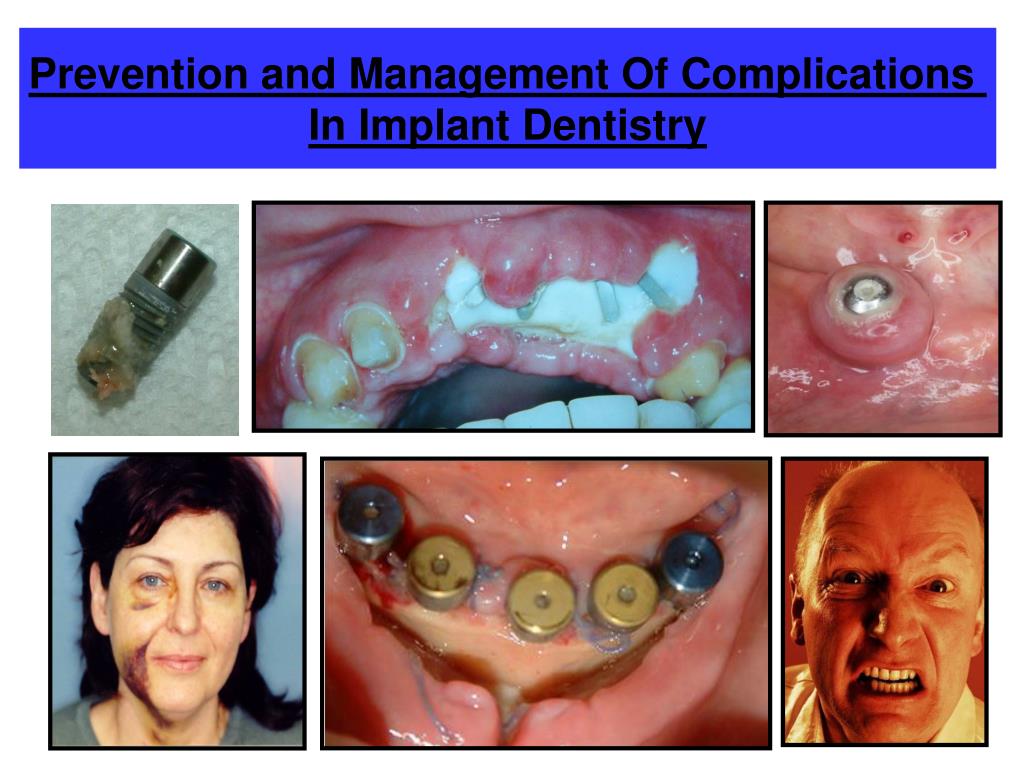
What Actually Goes Wrong With Dental Implants
Most implant failures aren't dramatic. They're slow, quiet, and usually traceable to something you should've caught six months earlier. I've been placing implants since the early 2000s, and the ones that give you trouble are rarely the ones you'd expect. Here's the breakdown of why they fail, how to stop it, and what to do when it's already happening. Let's start with the actual problem. Implant complications etiology prevention and treatment isn't one thing—it's a cascade. A small mistake in the planning phase compounds over months until you're left with mobility, infection, or bone loss around the fixture. The key is understanding where the cascade starts, because stopping it early changes everything.
Bacterial Biofilm And Peri-Implantitis
This is the big one. Peri-implantitis affects roughly 22 percent of implants after five years, according to the meta-analyses. It's essentially the same disease process as periodontitis, but the tissue response around a titanium surface is weaker and the biofilm adheres differently. Once you see probing depths over 5 millimeters with bleeding on probing, you're already in established disease territory. I had a case last year—a 58-year-old male, non-smoker, good systemic health. Six units, full arch. He came back at month 18 complaining about a bad taste near the lower right second premolar implant. Probing hit 8 millimeters, slight suppuration, and the radiograph showed moderate vertical bone loss around that fixture. The cause was clear: he'd been brushing aggressively with a hard brush for years, traumatizing the mucosa and creating a niche where plaque could accumulate. The workaround I used was straightforward. First, I had him switch to a soft brush and a water flosser set to medium. Then we did mechanical debridement with titanium curettes—never steel, steel scratches the implant surface and makes things worse—and followed up with chlorhexidine rinses twice daily for two weeks. The probing depth came down to 4 millimeters within three months. The bone didn't regrow, but the inflammation stopped progressing. That's the realistic outcome in most cases—you're managing, not reversing.
Overload And Mechanical Failure
Cantilevered prostheses are where I see the most preventable mechanical complications. A three-unit bridge on a single implant with a two-unit cantilever puts roughly three to four times the occlusal force on that fixture compared to a direct load. I've had implants fracture at the neck after about four years when patients clench or grind without a night guard. The failure mode is usually a screw loosening first, then abutment fracture, then implant body fracture if you ignore the early warning signs. The prevention strategy is boring but effective. Keep cantilevers under two teeth. Measure the bone-to-implant ratio on the CBCT before you commit to the prosthetic design—if the apical bone is less than 10 millimeters behind the most posterior implant, you need either more fixtures or a shorter cantilever. Torque the screws to the manufacturer's specification and recheck them at the one-month review. Most screw loosening happens within the first six months as the components seat. If a screw loosens more than twice, replace it. You can't reuse them reliably past that point.
Get the Full Details
Early Failure: Lack Of Osseointegration
An implant that doesn't integrate fails within the first three to six months. The typical presentation is mobility at the time of uncovering or abutment connection. Risk factors are well documented: smoking increases early failure rates by roughly two to three times, uncontrolled diabetes pushes it up similarly, and inadequate primary stability (less than 35 newton-centimeters of insertion torque) is a strong predictor. I don't place implants in Zone 4 or 5 bone unless I'm doing some form of grafting or using a shorter, wider fixture designed for softer bone. Here's something practitioners miss: you can have good primary stability and still lose the implant. It happens when you have micro-motion above 150 microns during the healing phase. That's about the width of three human hairs. If the patient is chewing on that side too early, or if the bone quality was over-drilled during osteotomy preparation, the fibrous tissue wins and you get a fibrous encapsulation instead of osseointegration. The fix is to reduce healing time expectations in compromised sites and go with a delayed loading protocol if the bone density is D3 or D4. Don't try to prove a point with a fixture that isn't going to hold.
Infection And Early Post-Operative Complications
Acute infection after placement is relatively uncommon—under 5 percent in most studies—but it's usually manageable if you catch it early. The typical timeline is 48 to 72 hours post-op with increasing pain, swelling, and erythema that's worsening rather than improving. This is different from normal post-operative discomfort, which should peak around day 2 and then steadily decline. If pain gets worse after day 3, you're dealing with something else. I antibiotics. Not always, but in cases where the flap wasn't closed primarily, where there was significant bone graft material exposed, or where the patient has any systemic compromise, I'll prescribe amoxicillin 500 milligrams three times daily for seven days, or clindamycin 300 milligrams if they're penicillin-allergic. The evidence actually supports this approach better than you might think—it reduces early infection rates from about 4 percent down to under 1 percent in higher-risk cases. For low-risk patients with clean cases and good primary closure, no antibiotic is reasonable and probably preferable from a resistance standpoint.
Soft Tissue Complications
Mucosal recession around implants is more common than most people realize. It's often cosmetic rather than functional, but when it gets significant, you lose the seal and the underlying bone becomes vulnerable. The main causes are thin biotype, trauma from the healing abutment, or improper prosthetic emergence profile. A convex emergence profile that's too wide creates a plaque trap and pushes the tissue apically over time. My approach to prevention is mostly about case selection and surgical technique. If the patient has a thin scalloped biotype, I'll do a connective tissue graft at the time of implant placement or shortly after. It adds about 1.5 millimeters of keratinized tissue on average, and that makes a real difference in long-term stability. For established recession, the treatment is more variable. Some cases respond to soft tissue grafts alone. Others need the prosthetic revised first to eliminate the traumatic contour before grafting will succeed. You have to address the cause, not just the symptom.

When To Refer And When To Treat In-House
Not every complication needs a specialist. Routine peri-implant maintenance, screw loosening, minor soft tissue irritation—these are all things you can handle in general practice. What I refer out: implant fractures, significant peri-implantitis with bone loss approaching two-thirds of the implant length, sinus communication issues after placement, and any case where the patient has uncontrolled systemic disease affecting healing. The referral threshold depends on your comfort level and the complexity of the case. err on the side of consulting earlier rather than later. The reality of implant complications is that most of them are predictable if you take the planning phase seriously. A proper CBCT, appropriate implant selection for the available bone, controlled loading protocol, and patient education about home care will prevent the vast majority of problems. The ones that slip through are usually the result of cutting corners somewhere—rushing the osteotomy, ignoring bone quality, or failing to address existing periodontal disease before placing fixtures. The etiology is almost always identifiable in hindsight. Prevention is just a matter of being systematic about the things that matter. If you want the full literature, the 2017 European Workshop on Periodontology and the 2020 World Workshop on Periodontics both have comprehensive consensus reports on peri-implant diseases and their management. The treatment algorithms are fairly standardized now. The hard part isn't knowing what to do—it's catching the problem before it reaches the point where you need to make a decision.