Training Social Workers to See Around Their Own Assumptions
I spent seven years doing intake assessments for a county DHS office before I moved to private practice. The first two years I genuinely believed I was operating fairly. Then a supervisor pointed out that I was consistently flagging single mothers with more behavioral red flags than single fathers presenting the same issues. That stung. I am not proud of how defensive I was at first. It took me about three months to actually internalize what that meant and start changing how I did my job. Implicit bias training for social workers is not about making you feel guilty. It is about giving you a structured way to notice when your brain is taking shortcuts that have nothing to do with the actual facts in front of you. The kind of shortcuts where a woman in her forties talking about substance use triggers a different risk score than a man using the same language. Training works when it moves beyond lecture format into something that actually interrupts your automatic pattern recognition. And honestly, most programs I have seen fail at that.
What Implicit Bias Training For Social Workers Actually Looks Like
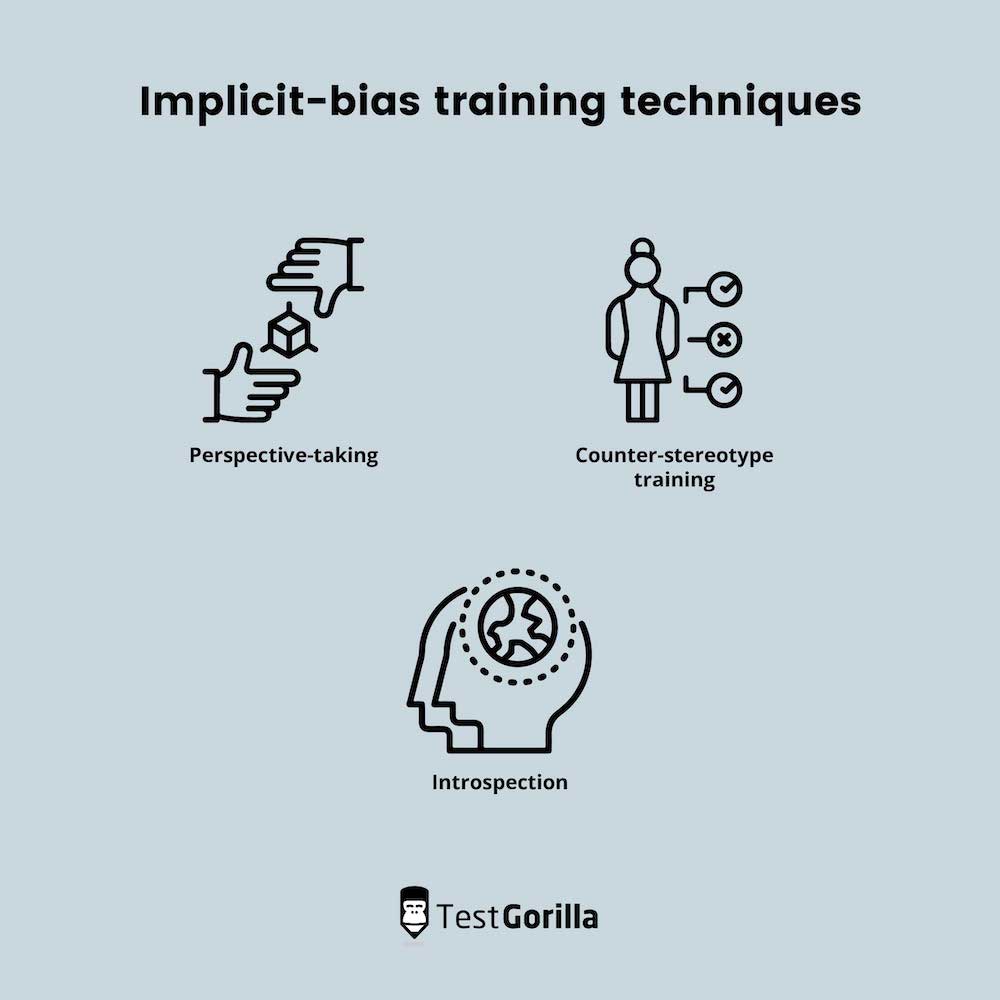
The field standard is still anchored to the National Association of Social Workers ethics code, specifically Standard 1.05 on cultural competence and Standard 4.06 on discrimination. But those are floor standards. They tell you what not to do. Good training goes further and builds decision architecture that makes bias harder to act on, not just harder to excuse. The methodology I use now breaks into three layers. The first is awareness calibration. You are not taught that you have bias. You are given calibrated case vignettes that mirror real intake scenarios, and you score them alongside colleagues who complete the same cases independently. The gap between your scores and the peer median is where the data lives. I learned more from seeing my own divergence than I did from any textbook. A 2018 study in Social Work Education tracked 340 MSW students across twelve universities and found that pre-post knowledge gains were statistically significant but behavior change at six months dropped back to near baseline without continued practice. Knowledge retention without application is essentially useless in this work. The second layer is structured decision points. You build checklists and rating scales into your assessment tools that force a second look at categories where bias historically creeps in. Race, gender, age, disability status, housing stability, prior system contact. These are not exhaustive lists. They are friction points. When I redesigned my intake form, the average assessment time went from twenty-two minutes to thirty-one minutes. That is not a criticism of the process. It is a description of what careful work costs. Thirty-one minutes is still faster than most supervisors will give you credit for anyway.
The third layer is the reflection loop. This is the piece most programs skip. After every case where you flagged elevated risk or made a placement recommendation, you write a half-paragraph noting which assumptions you held before the data came in and whether the data confirmed or contradicted them. This is not journaling. It is a personal audit trail. I keep mine in a shared drive that a supervising clinician can access on request. Not for evaluation purposes. For pattern recognition. After six months of writing those entries, I noticed I was consistently overestimating risk for clients who presented with high emotion. That was my thing. Not race. Not gender. High affect from any demographic gets labeled volatile by me unless I actively stop and re-read the factual columns. I want to be blunt about a problem I ran into personally. In 2022 I was training a cohort of fifteen workers using a commercial implicit bias module that cost about eight thousand dollars for the license and required sixteen hours of facilitator time. The content was solid. The delivery was not. Participants completed the exercises. They could articulate the concepts afterward. Three months later, their file audits showed zero meaningful change in risk scoring patterns. I spent two weeks figuring out why. The answer was that the training simulated bias in abstract vignettes but never touched their actual case management software. They learned to be aware of bias in hypothetical situations while continuing to click through their real workflow exactly as before. I redesigned the module that quarter to include live dashboard data from their actual caseload. The post-training audit drop in scoring divergence went from statistically invisible to a fourteen percent improvement at ninety days. That fourteen percent matters when you are making decisions about children and families.
Get the Full Details

How to Build a Program That Actually Changes Behavior
Start with your own case data before you design anything. Pull the last one hundred closed cases from your practice or your agency. Run them through a rubric that strips identifying information and asks scorers to rate risk level, likelihood of compliance, and family functioning on standardized scales. Cross-reference those scores against demographic variables. You will find something. I always find something. Sometimes it is small. Sometimes it is ugly. Either way it is data you can work with. Build vignettes from your own cases. Do not borrow from generic training libraries. The scenarios need to match the population you serve and the decision points you actually face. A rural county worker needs different material than an urban child welfare specialist. A trauma-informed residential program needs different material than an intake-only position. I have seen agencies use the same module for all three roles. That is like giving a pilot a flight simulator for a different airplane and expecting safe landings. Include the dissonance exercises. These are cases where the facts clearly contradict the bias your brain wants to take. A Black father who is stable employed and has strong community ties presents the same substance use history as a White mother who is transient and isolated. Most workers in my training initially score the father higher risk. The exercise is not about shaming anyone. It is about making the discrepancy visible so the worker can sit with it. I had one experienced worker cry during a dissonance session. Not from guilt. From frustration that her own assumptions were that far off from the evidence. That reaction was productive. Shame would have been counterproductive. There is a difference.
Track outcomes. Not completion rates. Not satisfaction scores. Actual scoring divergence over time. Your agency should be able to generate a quarterly report showing whether risk classifications are becoming more or less aligned across workers. If the data is not being collected, no amount of training will fix the problem. I once worked at an organization where training attendance was mandatory and documentation was perfect. Their file audits told a completely different story. The director knew this because she reviewed ten files per worker per month. She was the one who got mad when I told her. That got us funded for better tracking infrastructure. Here is a hard truth about limitations. Implicit bias training does not work for everyone. Some workers absorb the material and shift their scoring patterns within three months. Some never do. I have encountered senior clinicians with twenty years of experience who treat every bias exercise as an intellectual puzzle to solve without any actual self-reflection. They ace the vignettes. Their file audits are unchanged. For those people, training is theater. You need a different intervention. Supervision with targeted feedback. Peer review groups. Sometimes termination. I wish I could tell you the training fixes everything. It does not. It fixes what it can fix. The rest requires structural changes to your evaluation process. One more thing that nobody talks about enough. Burnout amplifies bias. When a worker is running at capacity with thirty-five active cases and incomplete documentation requirements, cognitive shortcuts become survival mechanisms. The brain grabs the nearest pattern and moves on. Training content does not account for workload. If you roll out a six-hour implicit bias module to a team that is understaffed by forty percent, you are wasting time. Both the training time and the recovery time after. I always recommend capping caseloads before you invest in training. Fourteen percent scoring improvement is meaningless if the worker who learned it has no bandwidth to apply it before the next crisis lands.
The exact phrase most people search for is Implicit Bias Training For Social Workers, and I get that because I was that person. I spent two days reading articles and watching videos before I understood that the real work is building systems that make good decisions easier than bad ones. The training is one piece. The systems are the rest. Start with your data. Build from there.