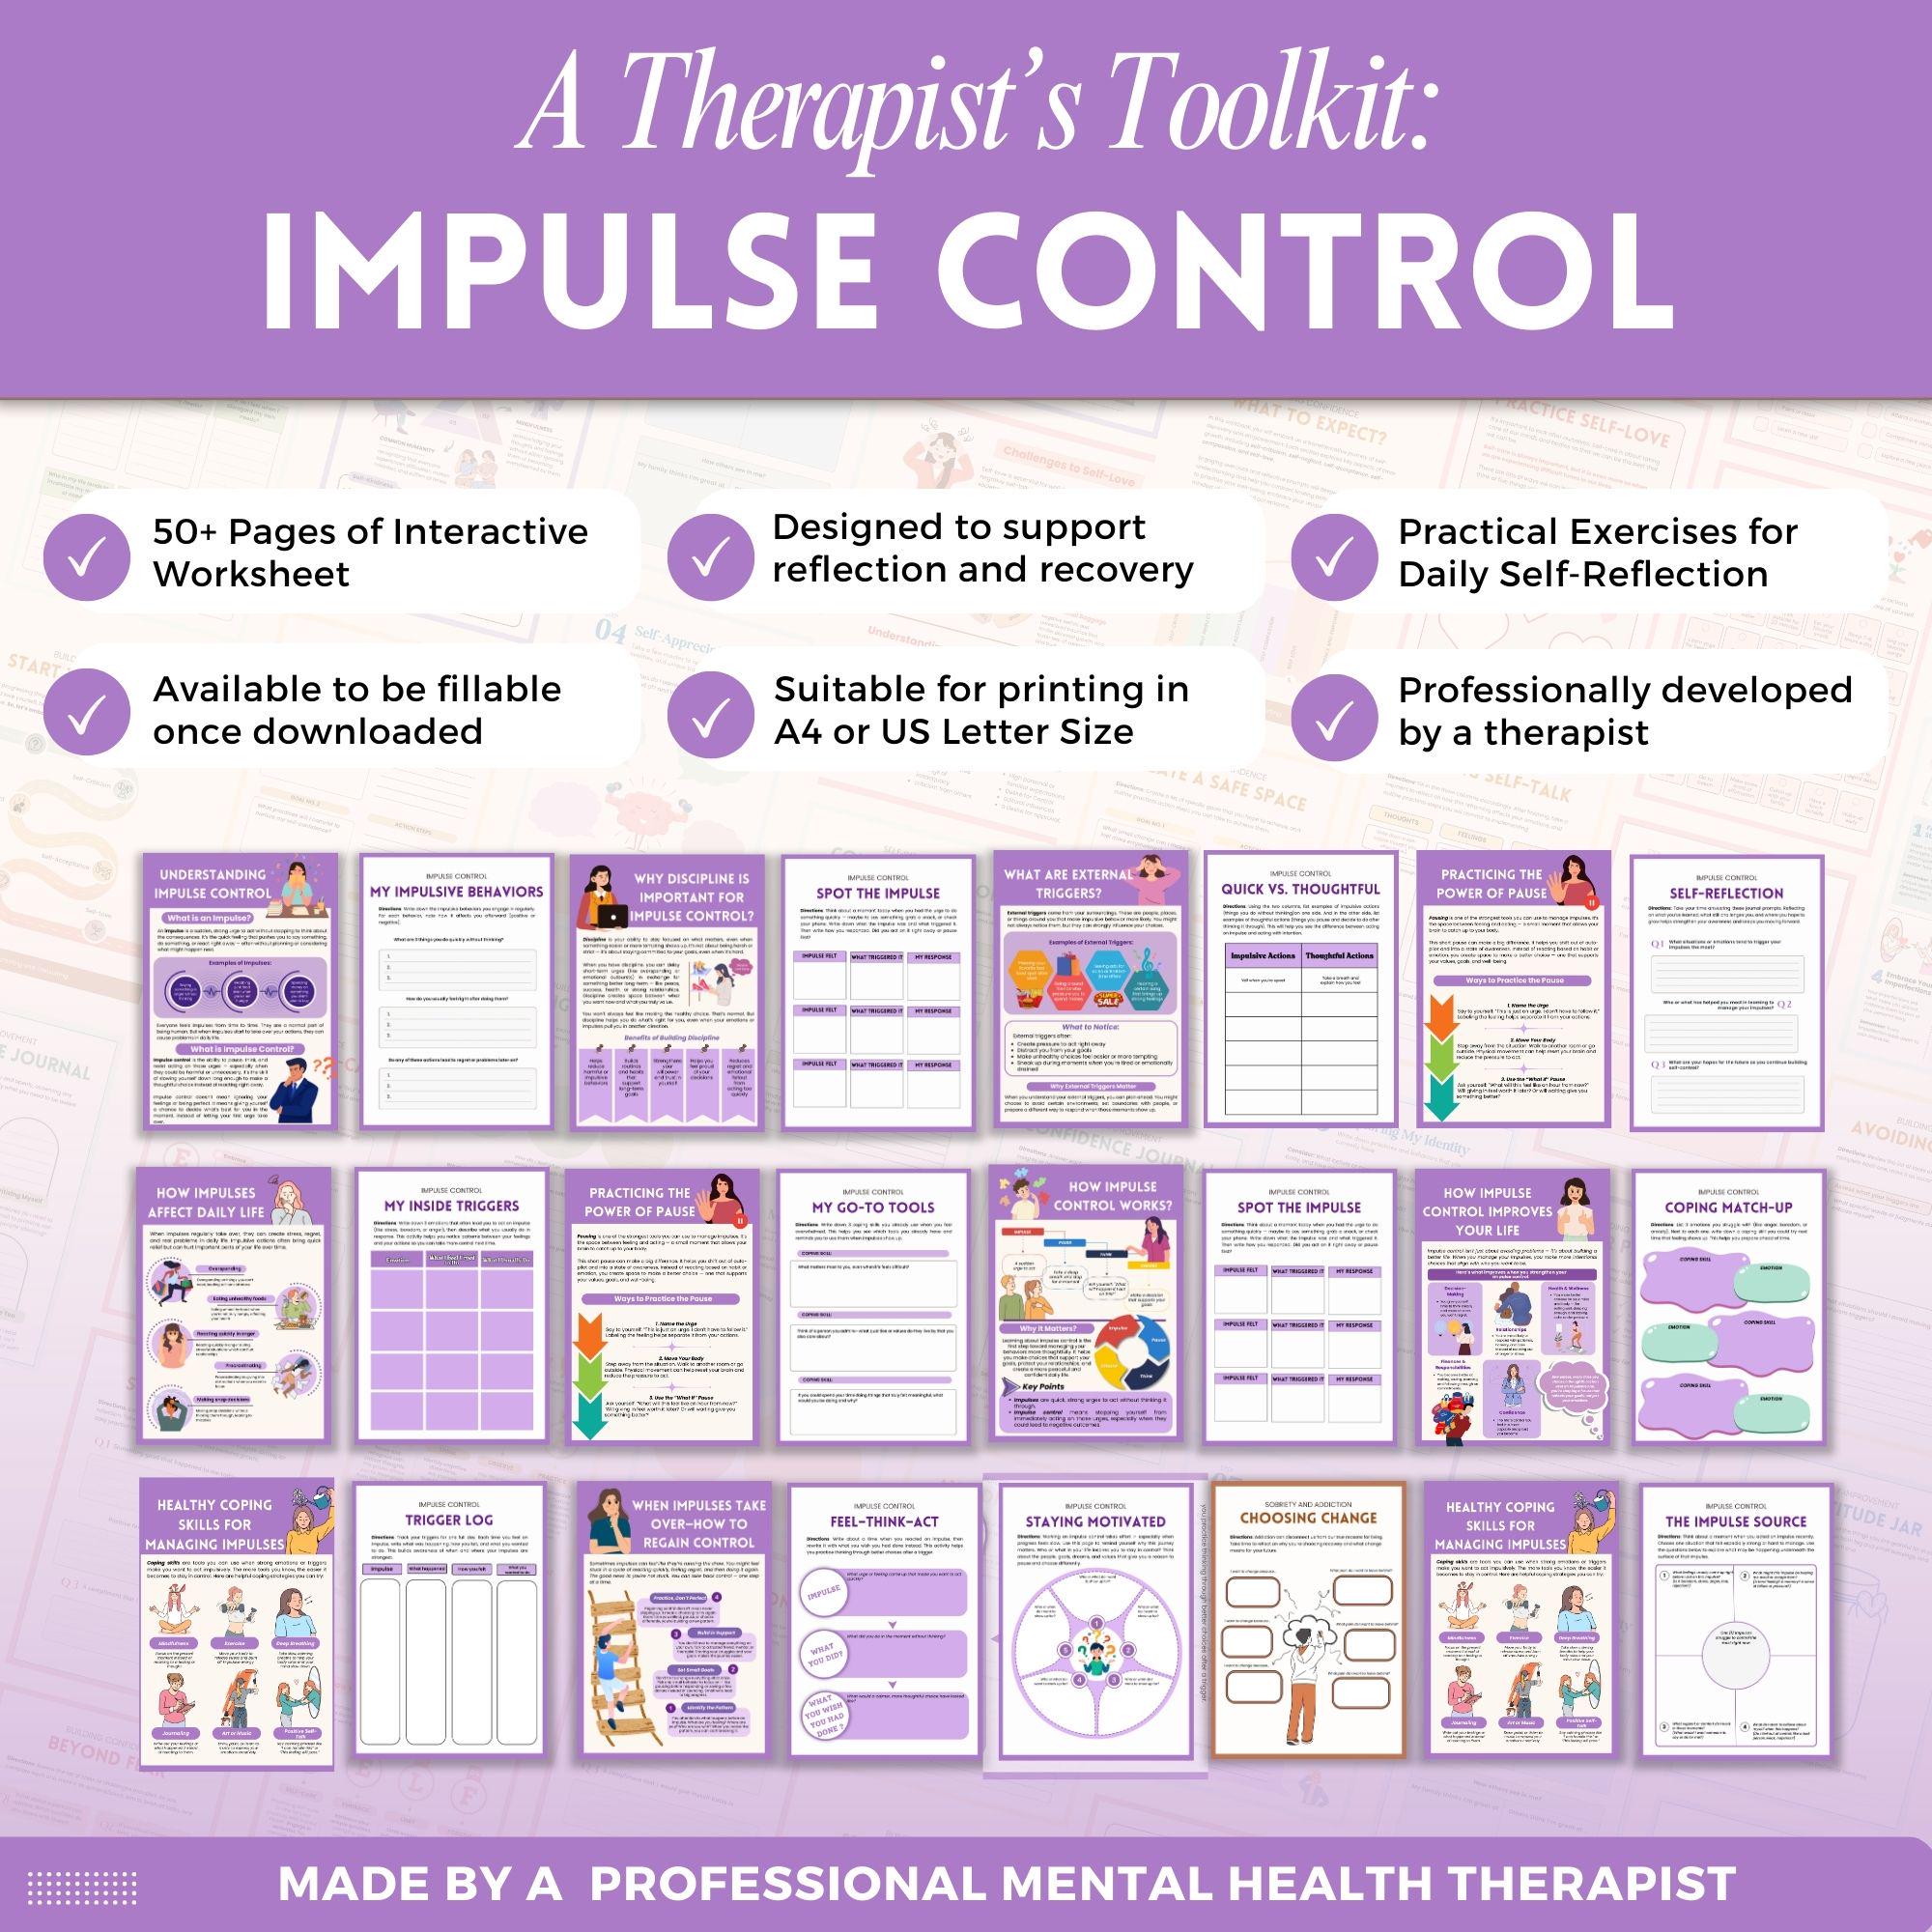
Impulse Control Therapy Worksheets Explained
I have used these worksheets with dozens of clients over the years. They are not a magic bullet, but they do something very specific: they externalize the internal dialogue that happens right before someone acts on an impulse. That gap between trigger and action is where the work actually lives. The basic format is straightforward. A client gets a sheet with columns for the situation, the urge intensity, the emotion felt, and then a few questions about what alternative response they could try next. You fill it out after the event, not before. Doing it in real time usually means the person is too triggered to write coherently anyway. Waiting until later lets the nervous system settle enough to be honest about what happened.
What Are Impulse Control Therapy Worksheets?
They are structured prompts used in dialectical behavior therapy, cognitive behavioral therapy, and acceptance and commitment therapy contexts. The worksheets guide clients through identifying triggers, tracking impulse strength on a scale, and developing planned responses. The goal is to build awareness so the automatic reaction has something to push against. Here is a practical detail most guides skip. The worksheet works best when you have already practiced the skills separately. If a client tries to complete a worksheet while simultaneously learning how to cope with the urge, both tasks fail. Pick one skill first, like distress tolerance, and reinforce it before adding the worksheet tracking. You usually see better compliance when the worksheet becomes a log of things they already know how to do, not a new demand on top of everything else. I encountered a specific problem once with a client who had severe OCD-related checking impulses. The standard worksheet format was making it worse because he would spend twenty minutes filling out the sheet, which became a compulsion itself. The ritual of completing the worksheet was serving the same function as the original impulse. My workaround was simple: I cut the worksheet down to three fields only. Situation, urge rating, and one sentence describing what he did instead. Anything longer became just another loop. We tracked compliance for two weeks and gradually expanded the form only when he showed he could handle it without spiraling.
One counter-intuitive thing worth noting. Some impulse control worksheets include a column for "what would happen if I acted on it." This is intended to ground the client in consequences, but it can backfire with certain conditions. For people with gambling disorder, for example, reviewing the potential positive outcomes during a high-urgency session actually increases the craving. I have seen clients report higher urge scores after completing that section. The fix is to either remove that column entirely for gambling and shopping compulsion cases, or move it to a separate exercise done only when the person is in a calm state, not at peak trigger. Another nuance most people miss involves the timing of review. The worksheet is useless if the client fills it out and never looks at it again. The actual therapeutic benefit comes from reviewing the completed sheets together in session, usually weekly. Patterns emerge that the person did not notice on their own, like how certain times of day or specific types of social interaction consistently precede the strongest urges. I usually have clients bring at least five completed worksheets to the first review session. Anything less and the data is too sparse to draw meaningful conclusions from. There are legitimate limitations to be aware of. These worksheets rely on self-report, which is inherently unreliable under stress. Clients will underreport urge intensity or overreport the success of alternative coping strategies because they want to feel like they are doing it right. This is not dishonesty. It is a well-documented bias in clinical settings. Pairing worksheets with some form of objective measure, like a partner check-in or a habit-tracking app with timestamped logs, helps correct for this drift.
Get the Full Details

They also do not work well for all disorders. If the issue is purely physiological, like a side effect from medication causing akathisia, no amount of worksheet work will address the root cause. Some clients present with impulse problems that are actually stemming from untreated ADHD or bipolar mania. In those cases, the worksheets can create a false sense that the person has more control than they actually do, which delays proper medical evaluation. I always recommend a thorough diagnostic assessment before committing to a worksheet-based treatment plan. If you want a free set of worksheets, there are several reputable sources. Psychology Today offers a printable impulse control worksheet pack. The DBT Skills Training handouts from Marsha Linehan's manual have adapted versions available through various clinic websites. New York Post also published a simplified version during the pandemic that some therapists still use as a starting point. The key takeaway is that the worksheet is a tool, not the treatment itself. It gives structure to reflection and creates a record you can analyze later. But the actual skill development happens in the moments between the trigger and the response, not on the paper. Use the sheets to track progress, spot patterns, and stay accountable. Do not expect them to replace the harder work of building new habits under pressure.