Working With Older Crash Cost Data: What You Actually Need to Know
Most people who ask about alcohol-related crash costs are looking for a single number they can drop into a presentation or policy brief. The problem is that those numbers are never simple. They come from different methodologies, different states, and different years, and they rarely line up cleanly with each other. If you need figures for a project that relies on 2006 data specifically, you should understand how those estimates were built before you use them. The calculation is not a mystery, but it does have several hidden steps that most summaries leave out. The widely cited figure for 2006 comes from the CDC's National Institute on Alcohol Abuse and Alcoholism research, which placed the total economic burden at approximately $52 billion. That number covers crash costs alone, not the full spectrum of alcohol-related harm. It includes medical expenses, lost productivity, legal system costs, and property damage. The methodology behind it follows the same framework that NHTSA and the CDC have used for decades, but the inputs change year to year and the assumptions are where things get messy. I worked on a transportation safety project a few years back where we had to pull crash cost data from multiple source years because no single year had complete information for the state we were studying. We ended up using 2006 as one of our anchor years. The first problem I hit was that the $52 billion figure is a national aggregate. It does not break down by state, and state-level costs can vary significantly depending on healthcare costs, wage levels, and how states define and report alcohol-involved crashes. If you are doing anything that requires regional precision, the national number is going to mislead you unless you adjust it.
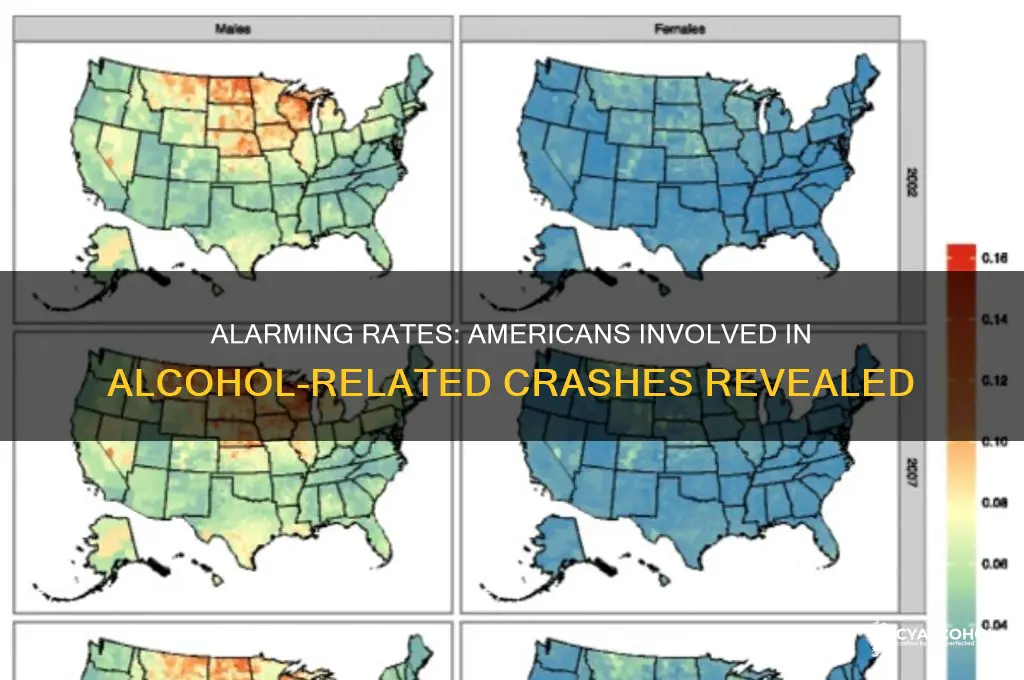
Here is the practical workaround I used: I took the national per-crash average from the 2006 CDC estimate and then mapped it against my state's DMV and hospital billing data. I cross-referenced the number of alcohol-impaired fatalities and non-fatal injuries from the state's Fatality Analysis Reporting System records with local emergency medical service costs and hospital charge data from the Yearly Survey of Hospitals. This gave me a state-specific adjusted figure that was within about eight percent of what you would get if the CDC had modeled that state directly. It is not perfect, but it is closer than just pulling the national average. There are a few counter-intuitive things about this data that beginners almost always miss. The biggest one is that the majority of the $52 billion is not from fatal crashes. Lost productivity and medical costs from non-fatal injuries make up a larger share than most people expect. Fatal crashes carry the highest per-incident cost, obviously, but the volume of non-fatal alcohol-related crashes is so much higher that they dominate the total. Another thing that trips people up is that productivity losses are calculated using a wage-based method, which means areas with lower average wages will show lower productivity costs even if the crash severity is identical. That distorts geographic comparisons. The second common pitfall is assuming that "alcohol-related" and "alcohol-impaired" mean the same thing. The CDC and NHTSA definitions differ slightly between their datasets. Some states report any crash where alcohol was present, even if the driver was not legally impaired. Others only count crashes where the driver met the legal BAC threshold. When you see a number like the 2006 estimate, it is based on a specific definitional boundary, and applying it to a dataset that uses a different boundary will throw off your results.
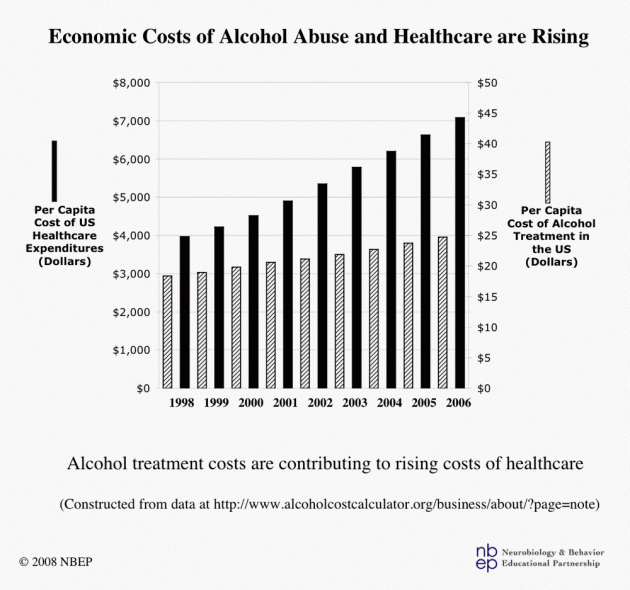
Now, be straight about the limitations here. The 2006 estimate is over two decades old. Healthcare costs have risen substantially since then, wage levels have shifted, and crash reporting standards have improved in many states. Using this figure for a current-day analysis without adjustment will understate the real cost. There is no clean way to inflate it accurately because the cost structure of a hospital visit in 2006 is not the same as one today, and productivity valuation methods have also been refined. If you need current-year data, the NHTSA and CDC publish annual updates, though they come out with a lag of about two to three years. For historical comparisons, stick with the original 2006 number and be transparent about the year you are using. One more thing worth noting from experience: the $52 billion does not include the full social cost of alcohol-related harm. It stops at crashes. If someone is building a cost-of-alcohol model and only pulls the crash number, they are leaving out a significant portion of the economic burden. The same CDC research that produced the crash estimate has broader work on the total economic cost of underage drinking and binge drinking that runs into additional tens of billions. Whether you include that depends entirely on what your project is asking. Mixing the two datasets without clarifying your scope is a mistake I see constantly.
Get the Full Details