Understanding the Actual Work of Health Science Research
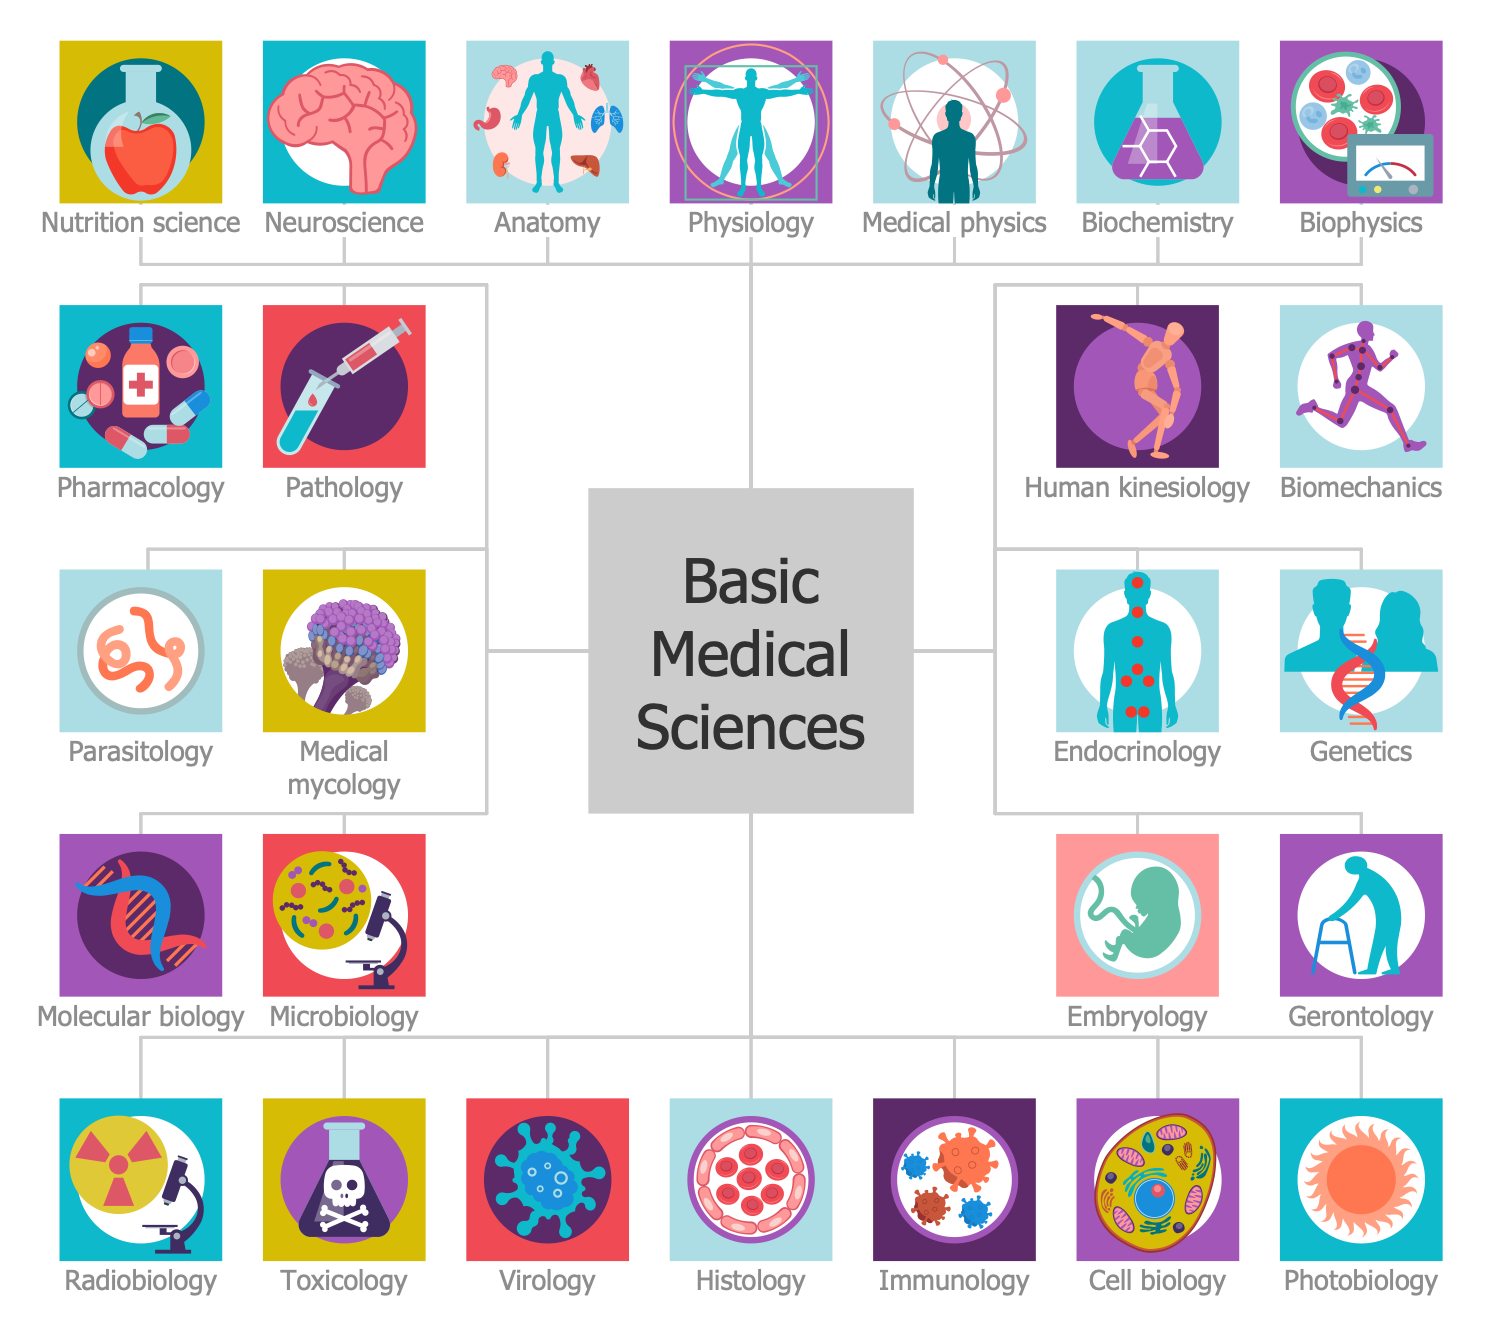
Most people think health science is just reading papers and writing reports. It is a lot more grind than that. I have spent years navigating institutional review boards, messy datasets, and the gap between what published studies claim and what actually happens when you try to replicate them. Here is how it works when you are inside the machinery. Health science is interdisciplinary by necessity. You cannot do epidemiology without statistics. You cannot design a clinical trial without understanding pharmacology and ethics. The field pulls from biology, chemistry, social sciences, and data science. The people who survive in it tend to be the ones who accepted that specialization comes later. Early on you need to be broadly competent or you will drown in jargon from other departments. I ran into a specific problem a few years ago that illustrates this well. We were tracking medication adherence in a diabetic population using electronic health records. The data looked clean at first glance. Standard deviation was low. Samples were consistent. Then I realized the lab was using three different glucose monitoring systems across different clinic sites, and those systems reported values in different units with different calibration curves. The aggregate data was technically valid but clinically meaningless. I had to pull individual site protocols, map every device type to its conversion factor, and reprocess the entire dataset. That took six weeks. We caught it before publication because I was the one who had to write the methods section. Most teams miss this.
Research Methods That Actually Work
Systematic reviews and meta-analyses get the most visibility, but they are also the easiest to botch. The problem is that adding more studies does not automatically make a result more reliable. If every study in your meta-analysis shares the same methodological flaw, you just get a precise estimate of a wrong answer. I have seen this happen with vitamin D supplementation trials where the baseline deficiency rates varied enormously between climates but the analysis treated them as comparable populations. Prospective cohort studies are more work but tend to produce usable results. You follow a group over time, collect exposure data before outcomes occur, and adjust for confounders statistically. The key insight nobody tells you upfront is that your confounder list should never be exhaustive. It should be strategic. You pick the variables most likely to distort your specific relationship of interest. Adding fifty covariates usually introduces more noise than it removes. I learned this the hard way when a paper I co-authored included an overadjusted model that actually inflated the confidence interval to the point where a real effect became statistically invisible. The simpler model told the true story. Clinical trials remain the gold standard when properly conducted, but the dropout rate in real-world trials is dramatically higher than what journals publish. Attrition bias is a structural problem, not a bug. Participants leave because of side effects, cost, inconvenience, or worsening conditions. Ignoring this skews results toward treatment effectiveness. The workaround is pre-registering your analysis plan including how you will handle missing data, then reporting both intention-to-treat and per-protocol results. This doubles your manuscript length but saves you from having to defend your conclusions later.
Statistical Tools You Should Know
R is the default now. Python is acceptable for certain workflows. SPSS and SAS still exist in older labs and regulatory settings. Pick one and commit. The tool matters less than knowing what each test actually assumes. T-tests assume normality. ANOVA assumes homogeneity of variance. Non-parametric alternatives exist but they have lower power. You need to know when to switch and when to just accept the limitation. Mixed-effects models are widely underused. They handle repeated measures and clustered data better than traditional approaches. If you are measuring the same patients across multiple time points or patients within the same clinic, a standard regression will give you biased standard errors. Mixed models account for the hierarchical structure without throwing away data. The learning curve is steep because the syntax is not intuitive. I spent three months going back and forth with a biostatistician before I understood random intercepts versus random slopes. Once it clicked, it saved me from designing two separate studies that would have been covered by one. Bayesian methods are gaining traction but they are not a magic fix. They require specifying priors, which introduces subjectivity that frequentist methods technically avoid through their framework. The advantage is that Bayesian analysis gives you a probability distribution for your parameter rather than a binary significant or not result. In health science where decisions affect real patient outcomes, that nuance matters. The disadvantage is that reviewers who learned frequentist statistics in graduate school will question your prior choices. Expect that pushback.
Get the Full Details

Publication and Peer Review
Writing for peer-reviewed journals is a skill that has almost nothing to do with understanding the science. The IMRaD structure is rigid because reviewers expect it. Introduction establishes the gap. Methods describes what you did. Results presents findings. Discussion interprets them. Deviating from this format increases review time and frustration for everyone. I once submitted a paper with a narrative-style methods section to save space. It came back with a request to rewrite it in standard format, delaying publication by four months. The discussion section is where most papers fail. Authors either overstate their conclusions or understate them out of excessive caution. The correct approach is narrow and honest. State what your results show. Acknowledge the limitations that matter. Do not list every possible alternative explanation. Your readers are competent. They do not need you to defend your work against every conceivable criticism that someone could raise three years after publication. H-index and journal impact factors are flawed metrics but they are what the system uses. This is not a mystery. Funding agencies and promotion committees rely on them. You can argue they are inadequate while still playing the game. Pick journals strategically. Target ones where your methodology would be understood by reviewers rather than ones with the highest impact factor that would treat your work as peripheral. A solid paper in a decent specialty journal reaches the right audience faster than an rejected paper chasing a top-tier name.
Data Management and Reproducibility
Raw data storage is a legal and ethical obligation, not an administrative task. Patient data requires de-identification beyond just removing names. Dates need shifting. Geographic details need rounding. The HIPAA safe harbor method has fourteen identifiers. People forget that zip codes and dates are on that list. I had a dataset flagged during IRB review because the admission dates were granular enough to reconstruct patient identity in a small rural community. We had to aggregate to monthly intervals, which reduced our analytical precision but kept the study compliant. Version control for data and code is non-negotiable. Git applies to research workflows the same way it applies to software development. Your analysis should be reproducible from start to finish by someone else with access to the raw data. I have lost count of the projects where I returned six months later and could not figure out which transformation script produced the final numbers. Document everything. Comment your code. Keep a README that explains the directory structure and the processing pipeline. This is tedious and nobody will thank you for it until you need it and are grateful you did.
Where the Field Is Heading
Real-world evidence is growing in importance. Regulatory bodies now accept it for certain approvals alongside traditional clinical trial data. This means electronic health records, insurance claims, and patient-generated data are becoming legitimate research sources. The challenge is data quality. These sources were designed for billing and clinical care, not research. Missing values, coding errors, and inconsistent documentation are structural features, not anomalies. Researchers who learn to work with imperfect data will have an advantage over those who insist on pristine datasets that do not exist outside of controlled studies. Artificial intelligence in health science is being oversold and undersold simultaneously. The hype cycle focuses on diagnostic algorithms that match or exceed radiologist performance. The reality is that most of these models fail to generalize across populations and hospital systems. A model trained on data from one hospital network often performs poorly at another due to differences in patient demographics, imaging equipment, and clinical workflows. The practical applications right now are narrower: triage optimization, adverse event prediction, and administrative automation. These are less glamorous but they deliver measurable improvements without requiring complete data standardization across institutions. The biggest structural problem in health science is replication. The replication crisis affected psychology and economics first, but it is now clearly present in medical research too. P-hacking, selective reporting, and publication bias distort the literature. Small sample sizes produce false positives. Industry-funded studies show more favorable outcomes than independent research. These are known problems with known solutions. Registration, preregistration, data sharing, and registered reports are the mechanisms. Adoption is slow because the incentives have not changed. Journals still reward novelty over confirmation. Institutions still reward volume over verification. Until those incentives shift, the system will continue to produce more papers with less cumulative reliability.

If you are entering this field, expect to spend more time on data cleaning and protocol navigation than on actual discovery. The work is incremental. Breakthroughs are rare and usually built on years of unglamorous foundational effort. The people who stay in health science tend to be the ones who found satisfaction in the process itself rather than waiting for dramatic results. That is not a motivational speech. It is a warning based on watching peers burn out or leave for industry roles where the feedback loop is shorter and the constraints are different. Choose accordingly.