What You Actually Need to Know About Inflammation Of A Vein
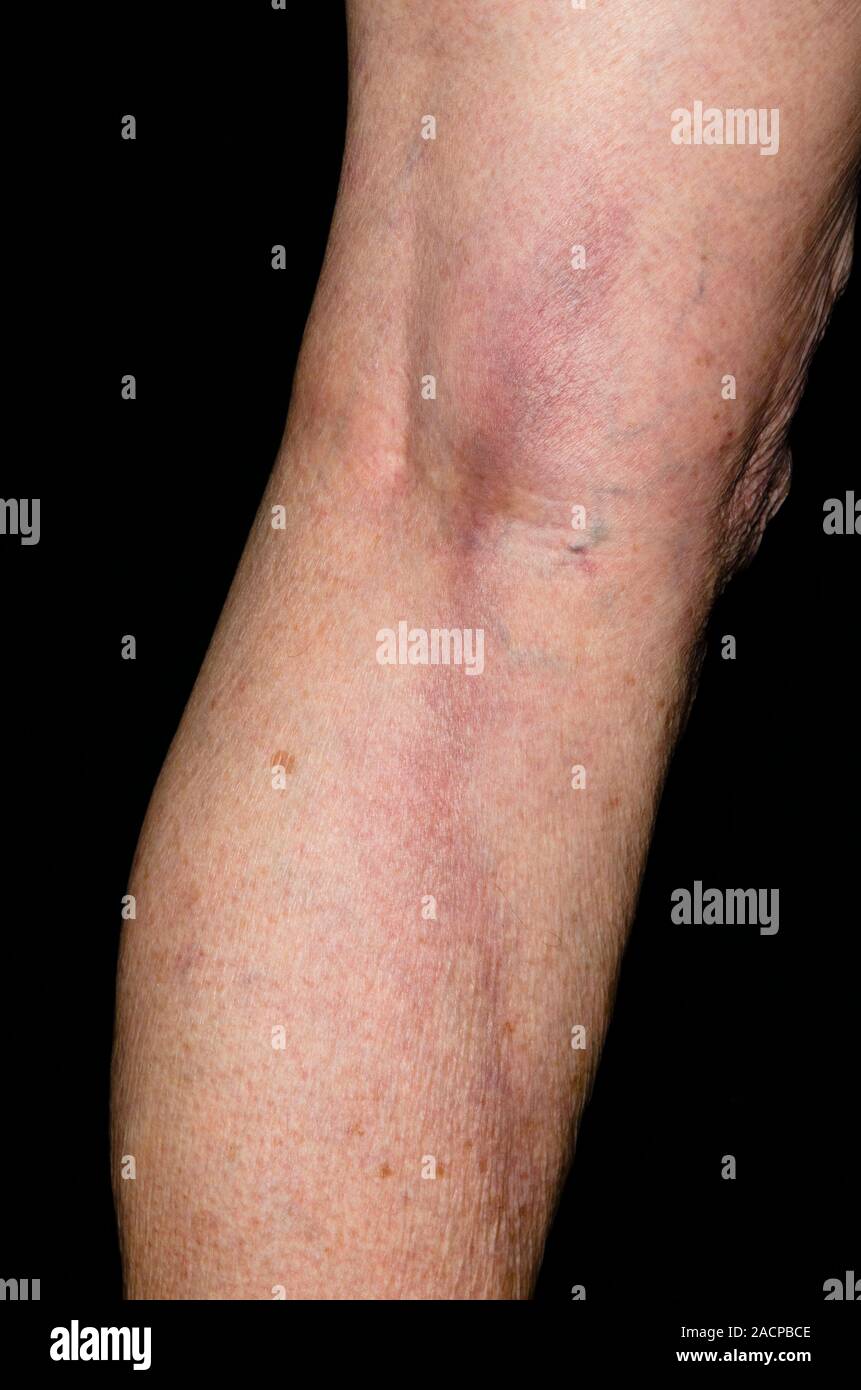
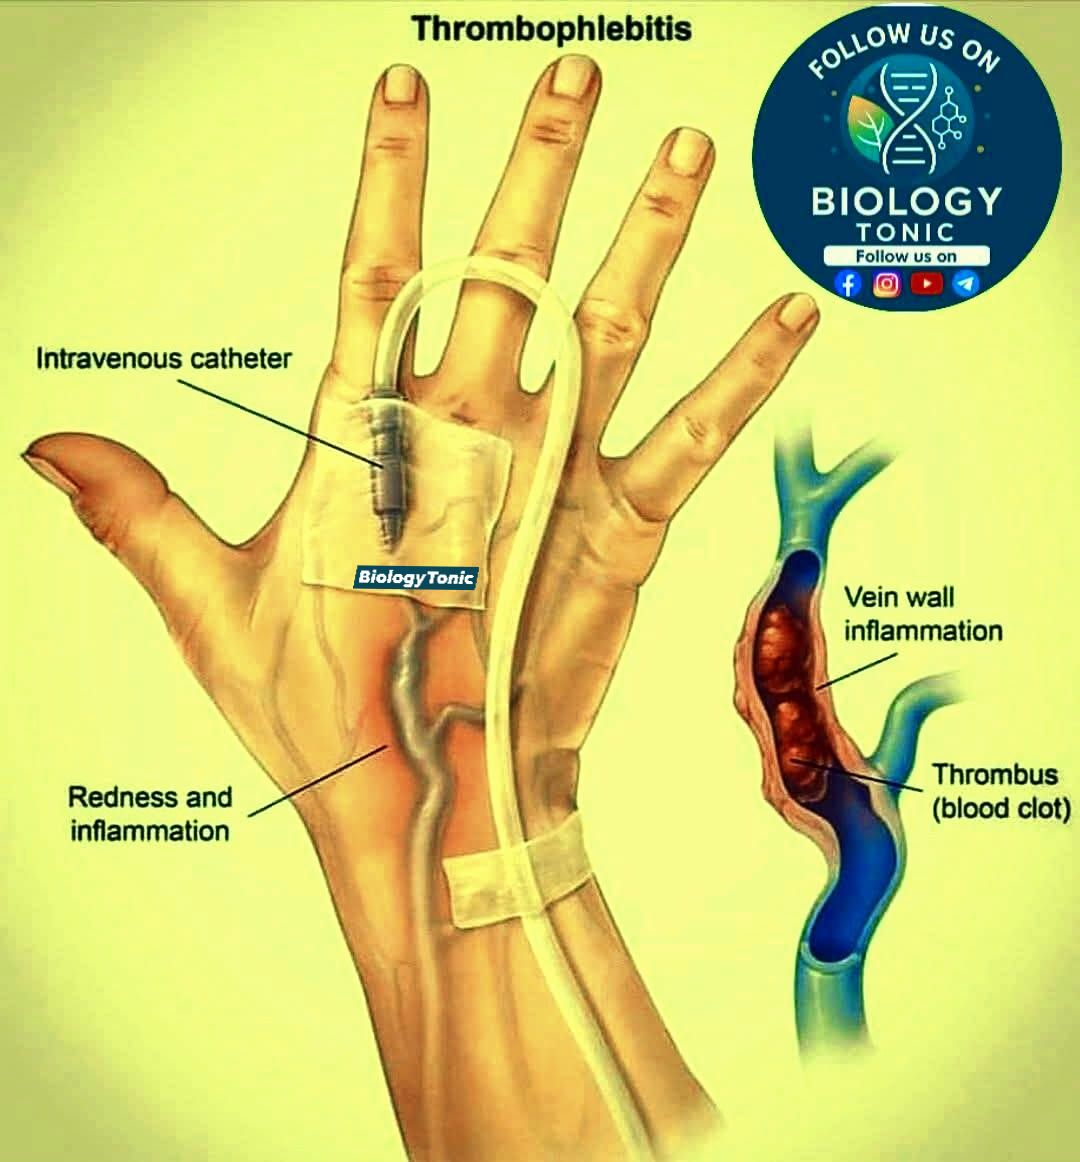
It's called phlebitis when a vein gets inflamed. Most of the time it happens because a vein is irritated from an IV line, a blood draw, or a bruise that forms after an injury. Less often it's caused by a small blood clot. The difference between a mild local reaction and something that needs a doctor's attention matters more than most people realize. The main sign is a tender, red, warm line along where a vein runs under the skin. You might feel a firm cord-like structure when you press along it. If you've had an IV recently, this is often just local irritation and resolves on its own in a week or two. That doesn't mean you ignore it. Superficial thrombophlebitis — when a clot forms in the vein alongside the inflammation — shows up in roughly a third of people with noticeable phlebitis. It usually stays superficial but occasionally extends deeper, and that's when things shift from inconvenient to dangerous.
When Inflammation Of A Vein Needs Medical Attention
The red flags are fairly clear. Swelling that spreads beyond the immediate area around the vein. Fever over 100.4°F. The redness expanding rapidly rather than slowly improving. Pain that gets worse after the first few days instead of better. If the affected vein is near the groin or upper leg, that carries higher risk because superficial veins in that region can connect to the deep venous system. A Doppler ultrasound is the standard way to check whether a clot has extended into deep veins. I've seen too many people wait until the swelling became massive before getting scanned. Management depends on whether you're dealing with simple irritation or thrombophlebitis. For straightforward phlebitis without a significant clot, the treatment is mostly conservative. Warm compresses applied for 15 to 20 minutes several times a day reduce inflammation and improve local blood flow. Nonsteroidal anti-inflammatory drugs like ibuprofen or naproxen help with both the pain and the inflammatory process itself. Compression stockings rated at 20 to 30 mmHg of pressure at the ankle support venous return and reduce the pooling that worsens symptoms. Elevation above heart level when sitting or lying down also cuts down on the hydrostatic pressure that drives swelling. If a Doppler confirms a superficial thrombus, the protocol changes. Low-molecular-weight heparin or fondaparinux for a limited duration — typically 45 days for thrombi longer than 5 cm — is the standard approach. Topical NSAID gels like diclofenac can be used alongside oral medications. Surgery to remove the affected vein segment is rarely needed anymore unless the thrombus is progressing toward the deep system despite anticoagulation.
A specific complication that caught me off guard involved a patient who developed phlebitis along the cephalic vein after a peripheral IV was left in place for four days post-surgery. Standard treatment was warm compresses and NSAIDs. After a week, the redness had clearly improved but a hard nodule persisted at the insertion site. Imaging showed a small organized thrombus with a tiny channel of flow still present around it. What I found was that continuing compression and heat for another ten days resolved the nodule completely, but stopping too early because the surface redness had faded led to recurrence in several other cases I observed. The visible improvement is misleading. The inflammation inside the vein wall lingers well past the point where the skin looks normal. Another counter-intuitive point: movement matters more than rest. Complete immobilization of the affected limb increases stasis, which promotes clot extension. Gentle walking and regular ankle pumps maintain venous return without putting excessive strain on the inflamed vein. Bed rest should only be recommended if the thrombus is very close to the deep system and there's concern about embolization, and even then it's temporary until anticoagulation takes effect. The biggest pitfall people make is assuming all phlebitis is the same. A post-infusion irritant phlebitis from a vesicant drug like potassium chloride requires different handling than septic phlebitis from an infected IV site. Septic phlebitis presents with purulent drainage at the entry point, persistent fever despite antibiotics, and tenderness that follows the vein path. That requires antibiotics targeting skin flora — usually cephalexin or clindamycin if MRSA is a concern — and often removal of the catheter within 48 hours. Missing this diagnosis and treating it as simple irritation delays proper care significantly.
Get the Full Details
Recurrence is another factor people underestimate. If you've had phlebitis in one location, the risk of it happening elsewhere is higher than the general population. This isn't random. It points to underlying venous insufficiency or hypercoagulable tendencies that deserve investigation if the episodes are recurrent. A basic workup including a complete blood count, PT/INR, and PTT can rule out obvious coagulopathies. If those come back normal and you're still getting repeated episodes, checking for antiphospholipid antibodies and Factor V Leiden mutation is reasonable. Prevention comes down to a few practical steps. Rotating IV sites every 72 to 96 hours in hospital settings reduces catheter-related phlebitis substantially. Using larger veins for infusions, especially for irritating medications, prevents the high concentration from damaging the vessel wall. For people who draw blood frequently, applying pressure for a full three minutes after needle removal instead of the usual 30 seconds prevents hematoma formation that can trigger phlebitis. Compression garments during prolonged standing or sitting help people prone to venous stasis. The recovery timeline varies. Mild irritant phlebitis from a brief IV placement typically improves within five to seven days. Thrombophlebitis takes longer — two to four weeks for the acute symptoms, and the firm cord can remain palpable for several months even after the inflammation has fully resolved. That residual induration is normal and doesn't indicate ongoing disease.
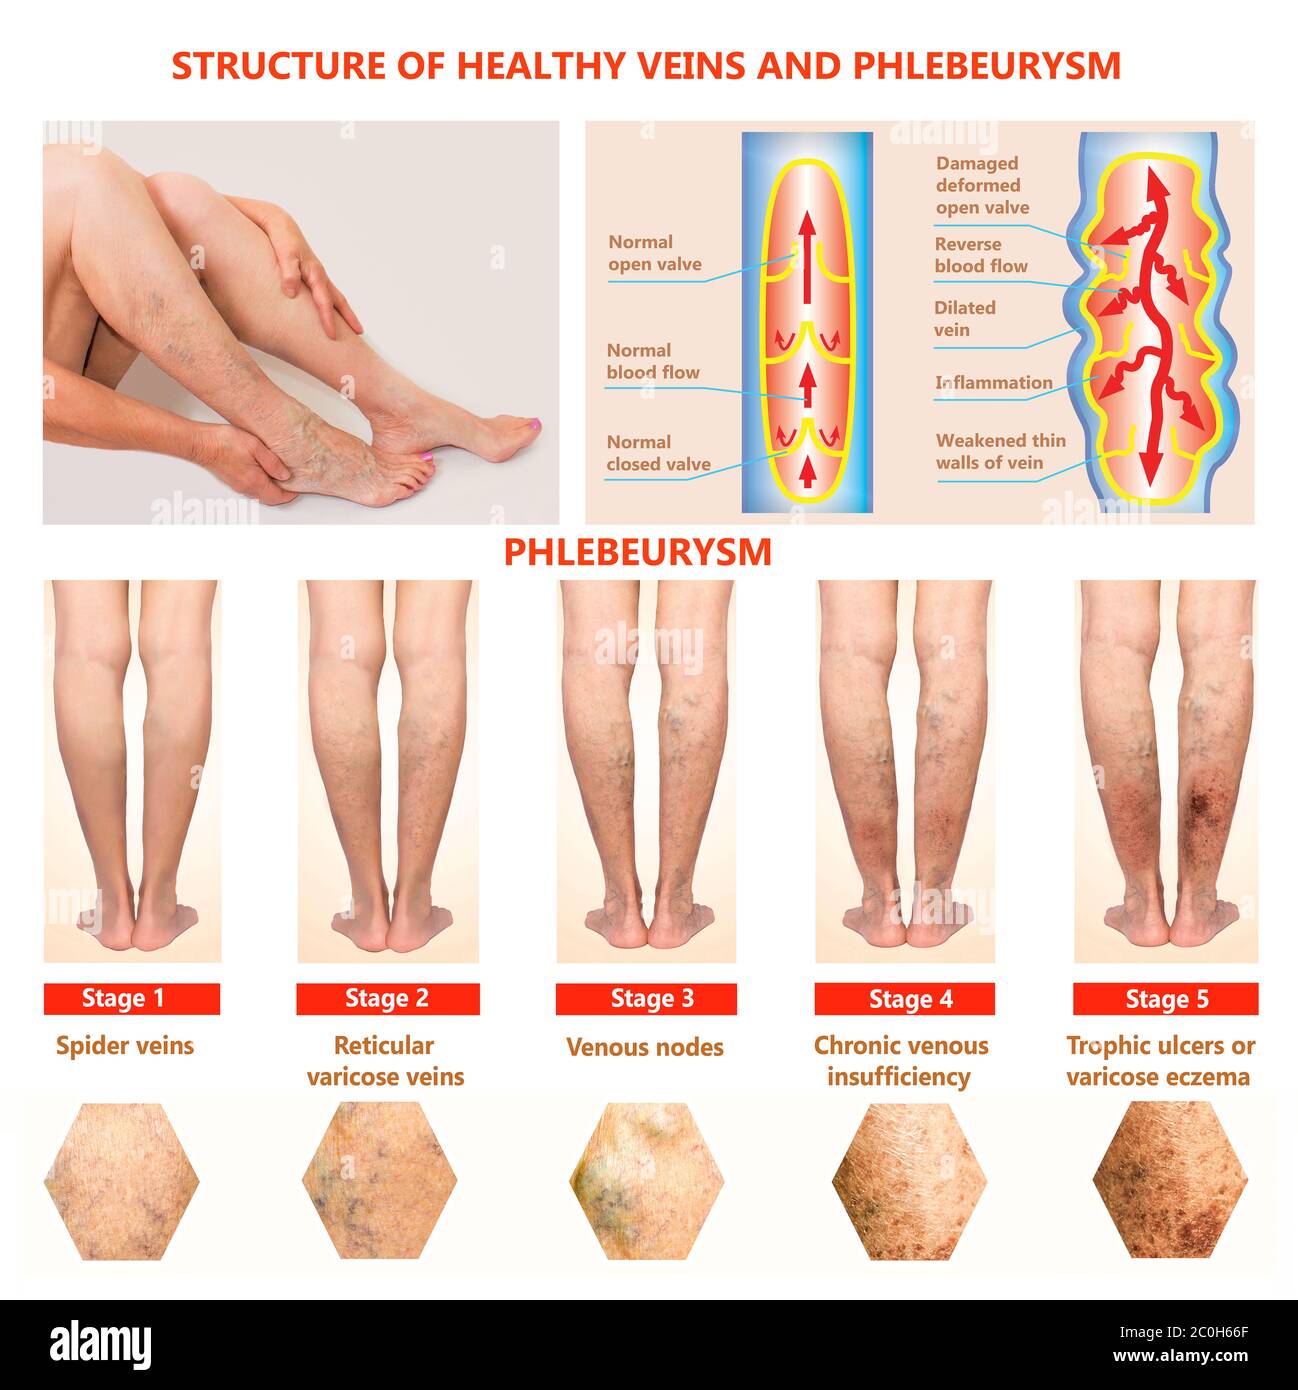
There's no reliable over-the-counter product that speeds resolution beyond what warm compresses and NSAIDs already do. Some products claim to use horse chestnut extract or gotu kola, but the evidence is thin and the quality of supplements varies wildly between brands. The safest and most effective approach remains the basics done consistently. One scenario where treatment clearly fails: if you have extensive varicose veins and develop phlebitis along one of them, conservative measures alone may not be sufficient. These veins have poor wall integrity to begin with, and the inflammation can persist indefinitely. Referral to a vascular specialist for possible endovenous ablation or sclerotherapy after the acute phase settles is the appropriate next step. Continuing to manage it with compresses and NSAIDs in these cases just delays definitive treatment.