Collecting Language Samples Without the Standardized Test Headache
An informal language sample gives you raw, uncontrived data about how someone actually uses language in real time. You record a conversation or play session, transcribe it, run MLU or lexical diversity calculations, and you know what the person does without the constraints of a normed battery. It is the bread and butter of clinical SLP work. Most people treat it like it is more complicated than it actually is. The workflow starts with choosing the right context. I always prefer free play or a casual interview over a structured task because scripted interactions suppress natural syntax and reduce the frequency of embedded clauses, subordinate structures, and pragmatic markers. You need about 100–150 utterances for a reliable sample, which usually means 15 to 25 minutes of natural interaction depending on the speaker's rate. Recording happens on a phone or a dedicated voice recorder positioned within two feet of the speaker. I use a Zoom H1n when I am in the clinic and fall back to my phone if I am doing a home visit. The quality difference matters more than people admit.
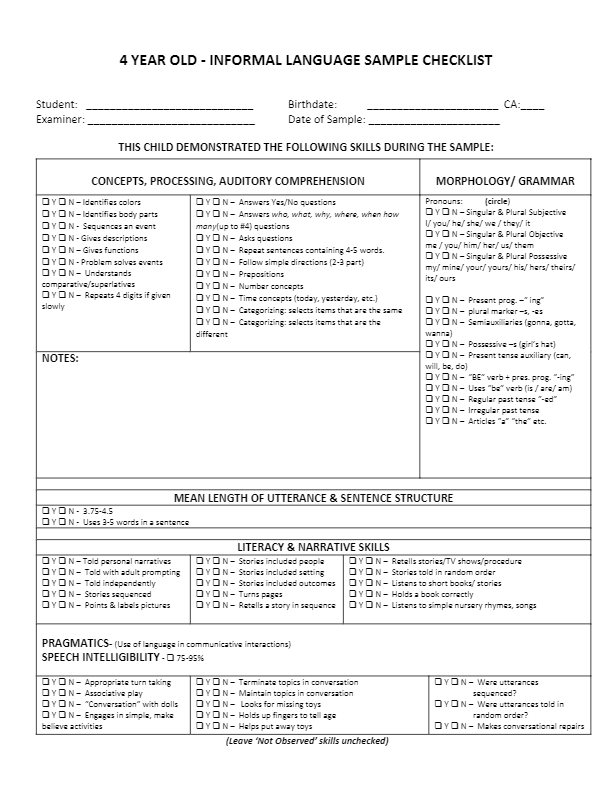
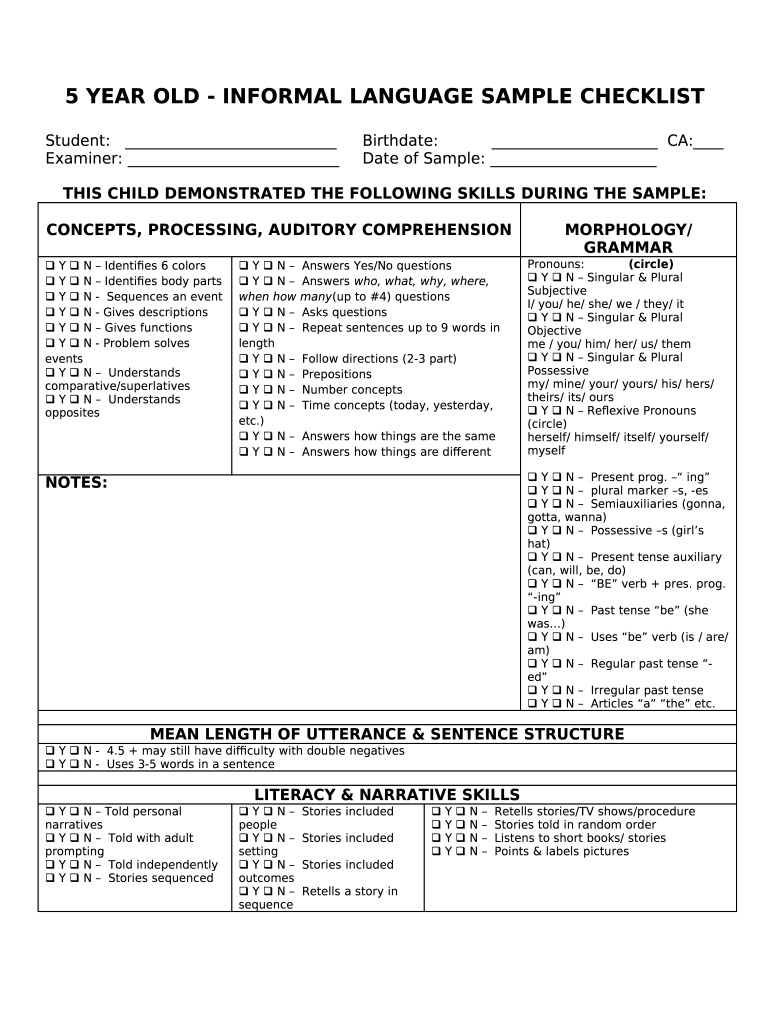
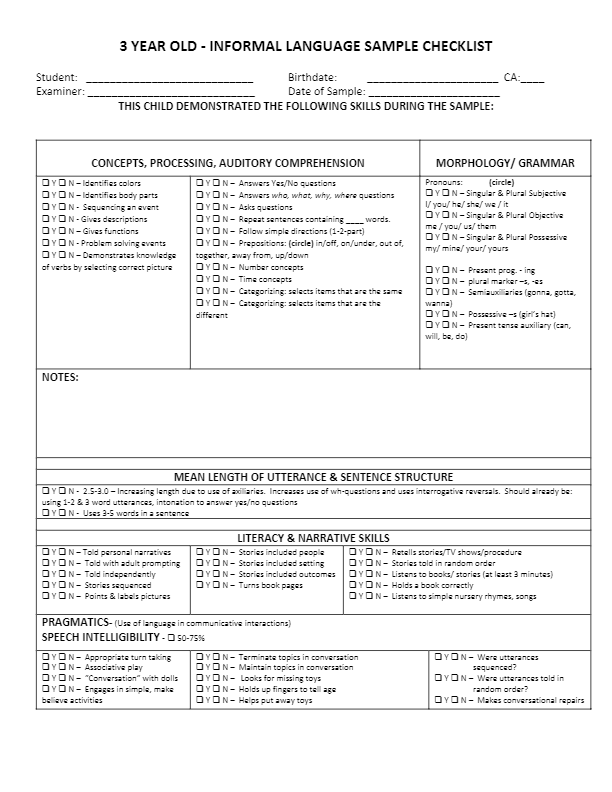
Informal Language Sample Checklist
Here is the concrete list I go through before, during, and after collection. It keeps me from forgetting the steps that matter most. Pre-collection checks: - Confirm informed consent and explain the process to the client or caregiver in plain language
- Identify the communication partner who will naturally elicit language (parent, sibling, familiar clinician) - Select a low-distraction environment with minimal background noise - Charge recording equipment and clear storage space
Get the Full Details

- Prepare open-ended prompts or toys appropriate to the client's age and interests During collection: - Begin recording before interaction starts so you capture the setup
- Avoid directing the conversation; let the client lead whenever possible - Do not correct errors in real time - Use minimal elicitors like "tell me more" or "what happened next"
- Keep the session going until you reach approximately 100 meaningful Utterances - Note any breaks, interruptions, or off-topic tangents in your session log Post-collection steps:

- Back up the audio file immediately - Document the date, time, setting, participants, activity, and any notable events - Transcribe using either a verbatim or edited transcription convention, staying consistent across sessions
- Run morphological and lexical analyses - Compare results to age-level expectations or prior samples
Transcription Conventions That Actually Matter
The transcription method you pick changes your numbers. Transcribing every disfluency, false start, and fill word produces a different MLU than editing those out. I use an edited transcription for general clinical samples because it gives cleaner grammatical data. You underline edits, bracket expansions, and parenthetical comments. Every utterance boundary gets a slash. The GAVE system or a simplified version of it works fine. Some teams use CLAN/CHILDES commands for the heavy lifting, which saves hours once you have the workflow dialed in. MLU is calculated by dividing the total number of morphemes by the total number of utterances. C-unit counting, where you isolate communicatively understandable units, is better for older children or individuals with apraxia because fragmented responses still carry useful morphological information. T-unit analysis serves school-age populations well since it isolates main clauses from complex embeddings. Pick one method and stick with it across sessions so you can track progress meaningfully.
A Specific Problem I Ran Into and How I Fixed It
Last fall I was working with a seven-year-old who had a strong preference for one-handed signing mixed with vocalizations. Her caregivers interpreted this as limited verbal output and wanted a language sample to justify continued therapy. The first three recordings yielded fewer than thirty transcribable utterances in twenty minutes because she would sign everything and vocalize minimally when prompted to speak. Standard transcription yielded useless MLU numbers. The workaround was switching to a multimodal transcription approach. I treated her manual signs as equivalent to spoken words for the purpose of morpheme counting, since her signing system had consistent morphological markers including aspect and plurality. I also included coders from her speech program to verify sign meanings in context. The resulting sample showed an MLU of 4.2 morphemes per utterance when signs and vocalizations were counted together, which placed her solidly in the expected range for her age when multimodal language is factored in. Without that adjustment, we would have misidentified her profile entirely.
Counter-Intuitive Things Nobody Teaches Beginners
One thing that surprises people is that longer samples do not always equal better data. After roughly 150 utterances, the returns on additional transcription drop sharply for morphological analysis. You are mostly capturing repetition and conversational filler at that point. For lexical diversity, you might benefit from pushing to 200 utterances, but for general grammatical sampling, 100 to 150 is the sweet spot. Another overlooked point is that the communication partner matters enormously. A parent who dominates the conversation with questions and directives will depress the client's utterance density by fifty percent or more compared to a partner who uses parallel talk and descriptive narration. Training the partner for ten minutes beforehand changes the sample quality more than any transcription tweak ever will. Informal language samples are not a substitute for standardized testing when you need diagnostic specificity. They cannot establish a disorder on their own. A child with a phonological disorder, auditory processing gap, or motor planning impairment may produce normally complex syntax in a language sample but still score well below norms on a formal battery. The sample tells you what the person can do in a low-demand context, not what they can do under structured conditions. If you need to document a deficit for eligibility or legal purposes, rely on standardized measures alongside the sample, not instead of them. The method also breaks down with very young speakers under three years old, where utterance boundaries are ambiguous and MLU becomes unreliable without extensive contextual inference. It struggles with aphasic speakers who have severe anomia or word-finding difficulty, since the resulting sample is sparse and difficult to interpret without knowing the specific lexical access profile. In those cases, a narrative retrieval task or a structured elicitation protocol yields more analyzable data than free conversation.
For practical analysis, the WCPA or SALT software packages handle most transcription and calculation tasks. SALT runs morphological and lexical analyses in minutes once the transcription is loaded. I use SALT for clinical reporting because the output is formatted for documentation. For quick internal checks, I sometimes calculate MLU manually in a spreadsheet to verify that the software is not miscounting edited units. Free transcription templates based on the Brown or CADES conventions are available from university speech labs and are sufficient for basic work. The real value of an informal language sample is that it shows functional communication. You see pragmatics, turn-taking, repair strategies, and syntactic range in a single sitting. That information does not appear on a standardized score sheet. Keep the checklist handy, transcribe consistently, and remember that the sample is one piece of the clinical picture rather than the whole thing.