Why the Thigh Is Often the Best Option
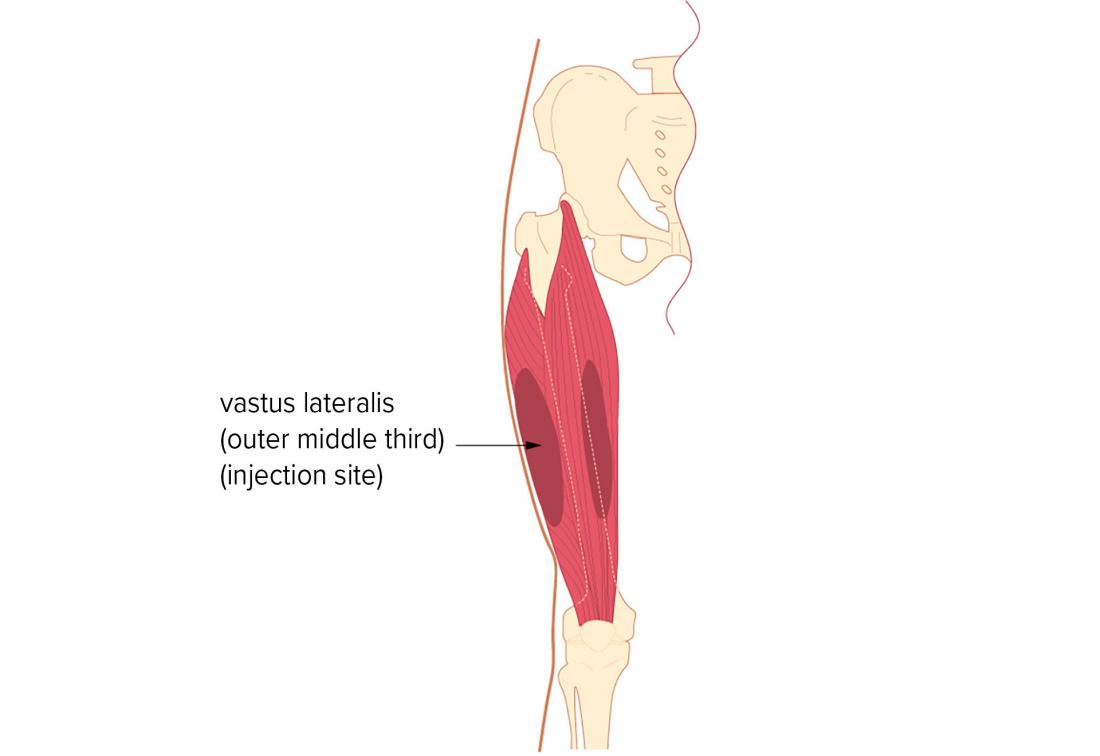
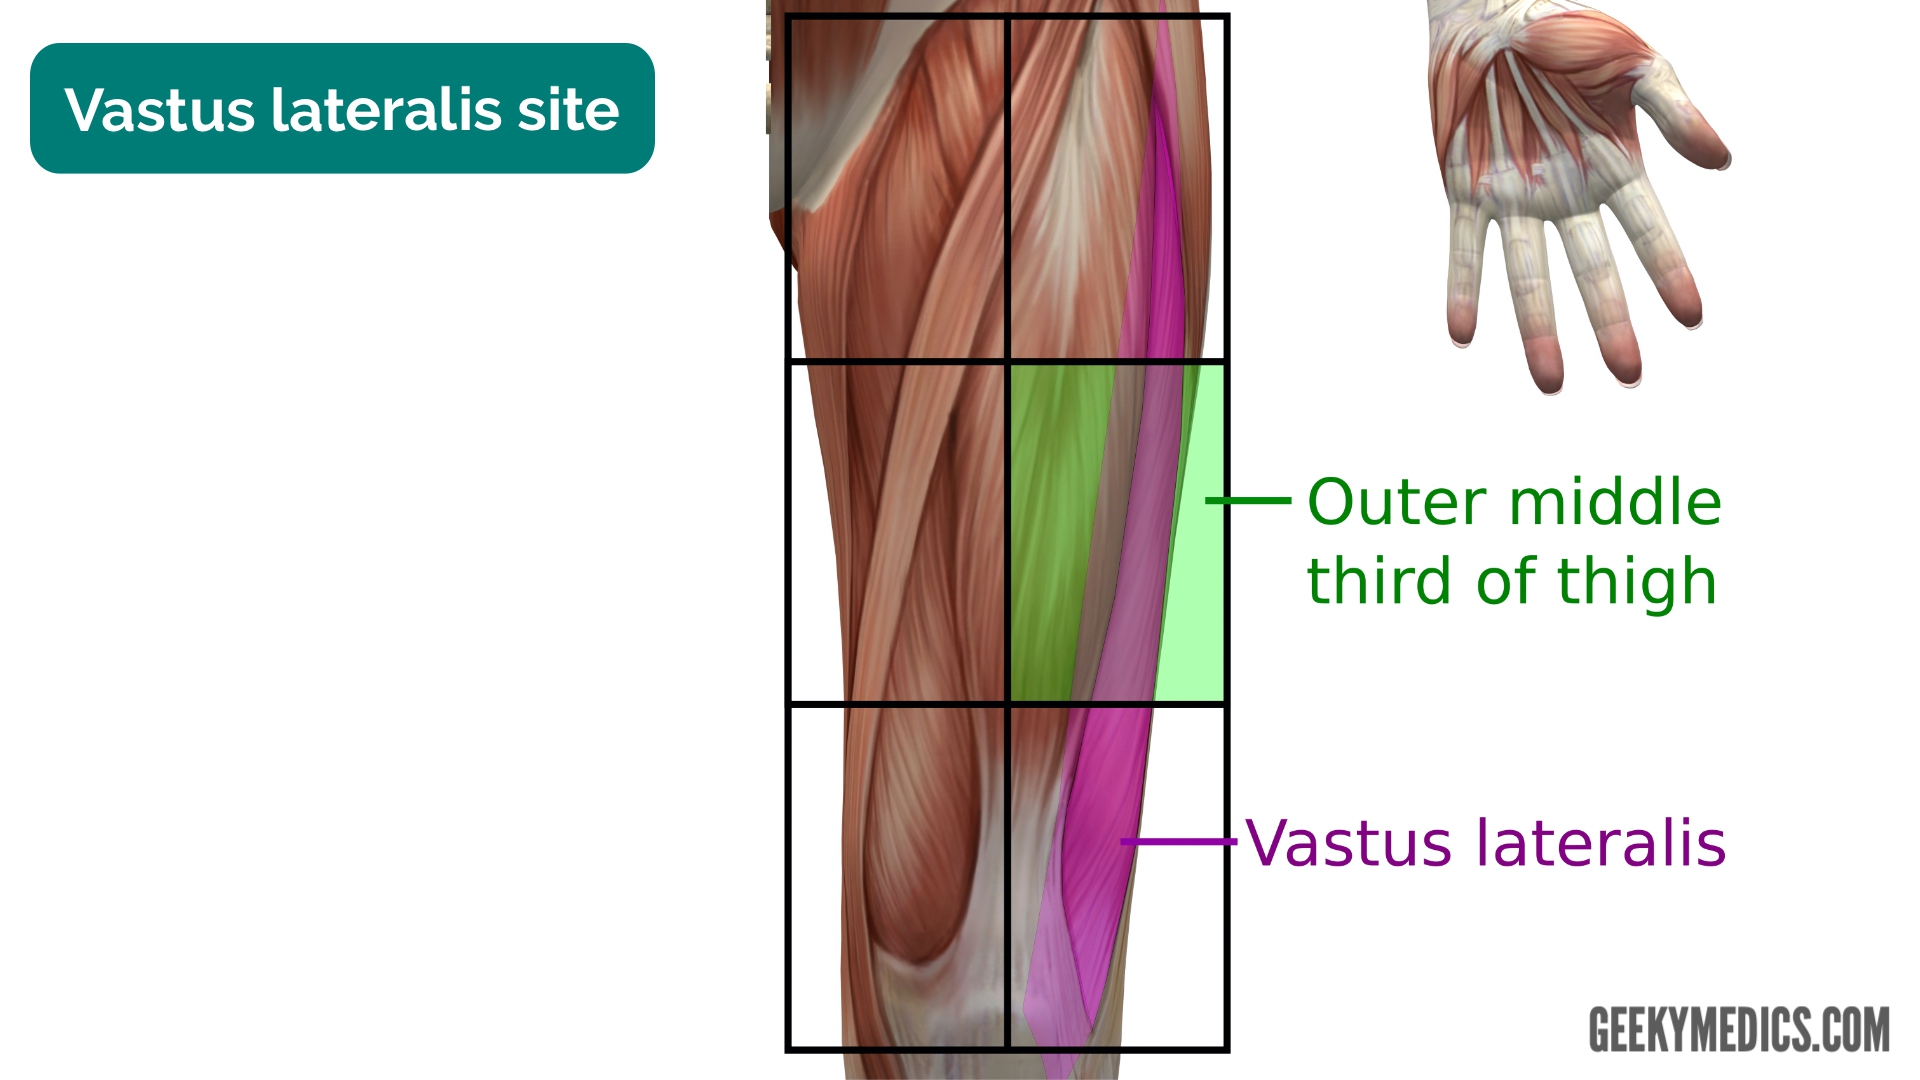
The vastus lateralis is one of the quadriceps muscles on the front-outer part of the thigh. It is a thick, well-vascularized muscle that works well for intramuscular injections. People pick it when the deltoid is not suitable, when giving larger volumes, or when the patient is an adult who cannot tolerate an arm injection well. It is not a glamorous site, but it gets the job done reliably. I have used this site more times than I care to count, mostly in emergency and inpatient settings where speed matters more than pride. The needle goes into the middle third of the muscle, roughly midway between the hip and the knee. That zone gives you enough meat to hit muscle without worrying about hitting bone or major nerves. It also tends to hurt less for the patient than the ventrogluteal site in my experience, and it is easier to expose without undressing someone completely.
Injection Site Vastus Lateralis: How to Actually Do It
Position the patient lying down or sitting with the leg relaxed. If they are sitting, have them lean slightly away from the side you are working on so the thigh muscles loosen up. A tense leg makes everything worse. Locate the midpoint of the thigh—measure from the greater trochanter down to the lateral condyle of the femur, or just eyeball it if you have done this enough. The injection target is the upper-middle portion of the muscle, about a hand's breadth below the hip bone. Load your syringe, select a needle length appropriate for the patient's body mass, and prepare alcohol swabs. Clean the area with a circular motion moving outward. Let it air dry. I know it is tempting to blow on it or tap it, but wet alcohol stings and reduces antisepsis effectiveness. Draw up the medication and check for bubbles. Hold the skin taut with your non-dominant hand. Insert the needle at a 90-degree angle. Quick, smooth motion. Do not hesitate. Once the needle is in, pull back on the plunger slightly to check for blood return. If you see blood, withdraw and restart with a new needle and syringe. Blood means you hit a vessel, and you do not want to inject intravenously without planning for it. If there is no blood, inject the medication slowly. About one milliliter per ten seconds is a safe pace. After the medication is in, wait a couple of seconds, then withdraw quickly and apply light pressure with gauze.
A real problem I ran into recently: a patient with significant edema in the lower extremity. The anatomical landmarks were difficult to palpate because the swelling distorted the surface anatomy. I ended up having the patient flex the knee slightly and using a slightly more anterior approach within the vastus lateralis zone, angling just a few degrees forward from the strict lateral position. It avoided the fluid-heavy area and still deposited the medication into muscle tissue. The volume was only 1 mL, but with edema even small mistakes can land you in subcutaneous tissue instead of muscle. The key details people miss. Needle length matters far more than most nurses check. A standard 1-inch needle works for most average-adult patients, but for a larger body habitus you may need 1.5 inches. Going too short puts the medication into subcutaneous fat, which absorbs many medications poorly and can cause nodules or abscesses. Conversely, in a very thin patient, a 1.5-inch needle risks hitting the femur. There is no universal needle size, and assuming one works for everyone is how complications start. Another thing nobody emphasizes enough: the B-mode ultrasound visibility of the vastus lateralis. In patients with obesity or severe muscle wasting, landmark-based injections become unreliable. I have seen colleagues inject into the fascial plane between the vastus lateralis and the rectus femoris because the muscle belly was too small to confidently target by touch alone. Using a portable ultrasound to confirm needle tip placement before injecting cut down my repeat-injection rate almost entirely. It adds about two minutes to the procedure, and it is worth it if you are dealing with a difficult anatomy case.
Get the Full Details

Limits of this site. The vastus lateralis is not ideal for everyone. Patients with known quadriceps trauma, recent knee surgery on that side, lymphedema, or significant peripheral vascular disease should not use this site. Also, recurrent injections into the same leg can cause fibrosis and reduced absorption over time. If a patient needs daily IM injections long-term, rotating between the deltoid, ventrogluteal, and vastus lateralis on alternate sides is standard practice. Using only one site leads to hardened tissue and unpredictable drug uptake. The volume limit for the vastus lateralis is generally around 2 to 3 mL per injection in adults. Going above that increases pain and the risk of leakage back through the needle tract. For larger volumes, split the dose across two sites or choose a different muscle like the ventrogluteal, which can accommodate up to 3 to 4 mL comfortably. Documentation usually gets overlooked but it matters. Record the exact site used, the needle gauge and length, the volume injected, the angle of insertion, and whether there was any immediate reaction. If a patient comes back with a sterile abscess two weeks later, that documentation is the first thing clinicians will look at to determine whether the injection technique was appropriate.
I generally do not recommend this site for self-administration by patients unless they have received hands-on training. The anatomy is straightforward in principle, but compensating for patient movement, body habitus variation, and proper needle depth takes practice. A poorly trained patient injecting into subcutaneous tissue repeatedly will develop lipohypertrophy and will not get consistent drug levels. That is a real clinical problem, not a minor inconvenience.