How Innate and Adaptive Immunity Actually Work Together in Practice
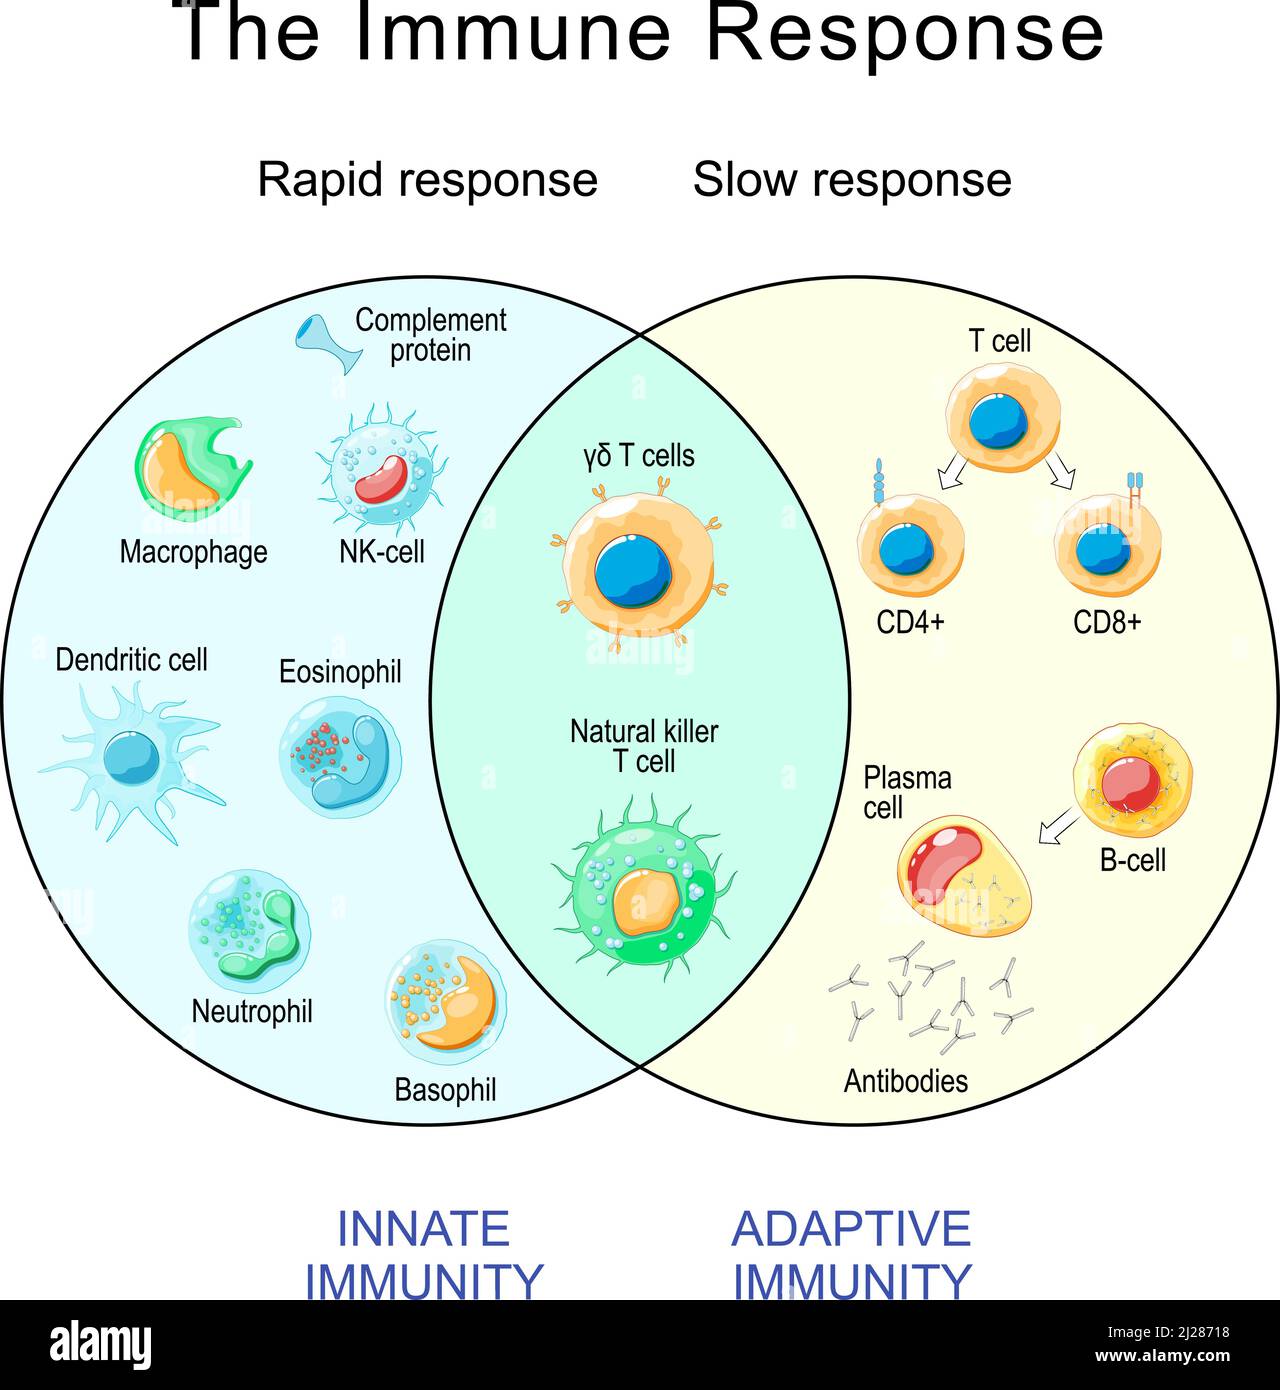
Most people treat innate and adaptive immunity as two completely separate systems, but that framing causes serious confusion when you actually try to work with real immune data. Innate immunity is the first line of defense, deployed within minutes of exposure. Adaptive immunity takes 4 to 7 days to fully activate but provides long-lasting pathogen-specific protection. The Innate Vs Acquired Immunity distinction matters far less than understanding how these two arms communicate in actual biological contexts.Understanding Innate Vs Acquired Immunity: The Practical Breakdown
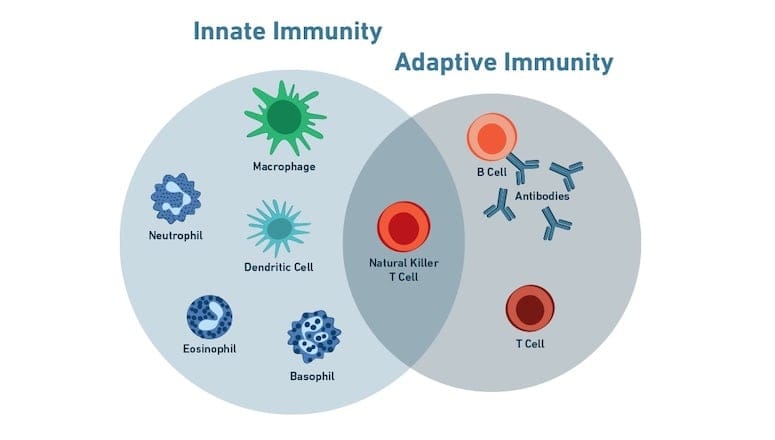
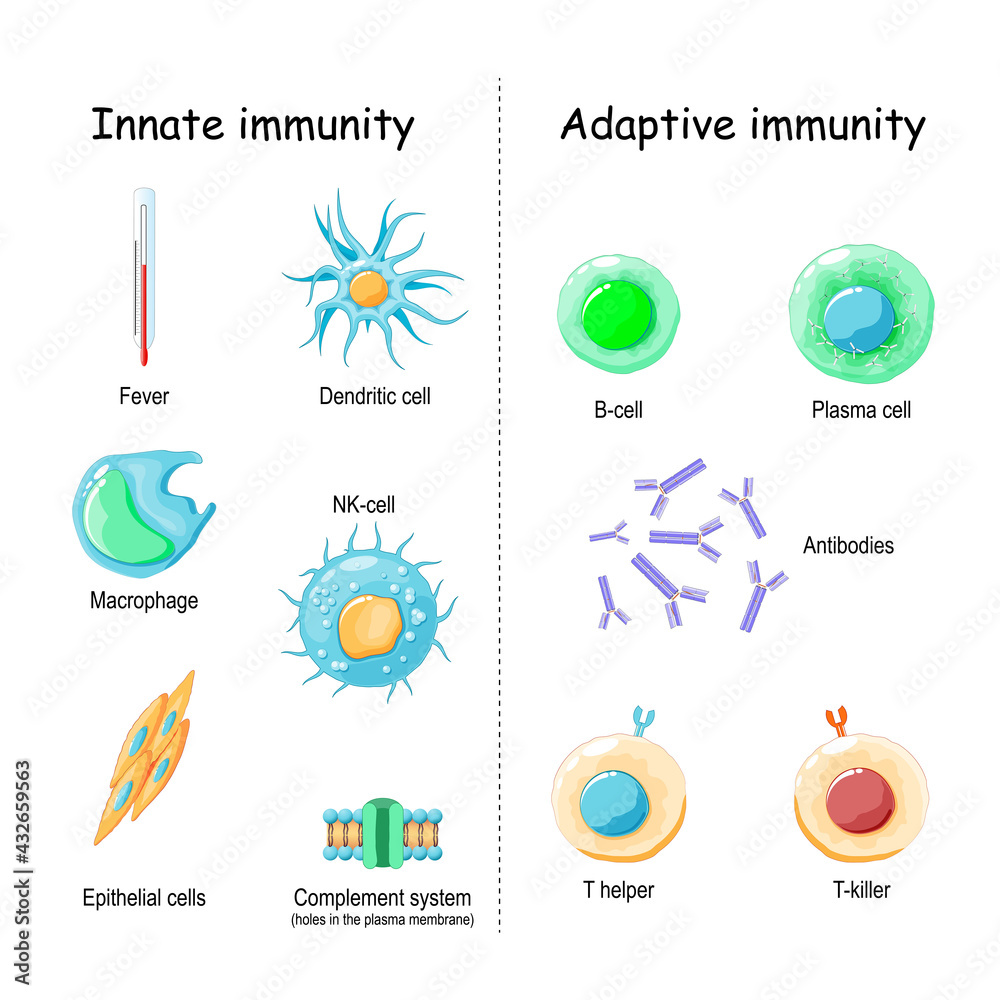
Innate immunity consists of physical barriers, phagocytic cells, and pattern recognition receptors that respond to conserved microbial structures. This means skin, mucous membranes, neutrophils, macrophages, dendritic cells, the complement cascade, and proteins like interferons all belong here. The defining feature is that recognition is germline-encoded, not shaped by prior exposure. A toll-like receptor (TLR) on a macrophage recognizes lipopolysaccharide on gram-negative bacteria regardless of whether that macrophage has ever encountered that specific bacterial strain. That speed comes at the cost of precision. Innate responses cannot distinguish between closely related pathogen variants the way an adaptive response can. Adaptive immunity involves B cells and T cells that rearrange their antigen receptors through somatic recombination. This generates a diverse repertoire capable of recognizing virtually any molecular structure. But this diversity is expensive to build and maintain. Naive B and T cells circulate indefinitely until they encounter their cognate antigen presented by an antigen-presenting cell. Without antigen presentation, the adaptive response simply does not start. Here is where the textbook simplification breaks down. Dendritic cells sit at the junction between these two systems. They capture antigen through innate mechanisms, migrate to lymph nodes, and present processed peptides on MHC molecules to naive T cells. This means innate signaling directly shapes adaptive outcomes. The cytokine environment during antigen presentation determines whether CD4+ T helper cells differentiate into Th1, Th2, Th17, or regulatory phenotypes. This differentiation cascade determines the quality of the eventual antibody response. IgG subclasses, IgA production, cytotoxic T lymphocyte activity—all of these are influenced by the initial innate stimulus.
I ran into a specific problem last year with a client working on a vaccine adjuvant formulation. They were seeing excellent antibody titers in mouse models but the protective efficacy in challenge studies was far lower than expected. After two weeks of debugging, the issue turned out to be that their candidate adjuvant was triggering a strong Th2-skewed innate response. The resulting antibodies were primarily IgG1 and IgE in the mouse model, but their target pathogen required a Th1-mediated cytotoxic response for effective clearance. The quantitative data looked good. The functional outcome was wrong because nobody had mapped the innate polarization signal to the downstream adaptive profile. We switched the adjuvant to one that drives stronger type I interferon signaling and Th1 differentiation. Protection improved dramatically with the same antigen dose. This kind of disconnect between measured biomarkers and actual protective outcomes is probably the most common mistake in immunology research. ELISA results showing high antibody concentrations mean very little if those antibodies are the wrong isotype or lack sufficient affinity. Similarly, a strong innate cytokine profile does not guarantee effective adaptive memory. The relationship is directional but not linear. One counter-intuitive point that rarely gets emphasized is that innate immunity has memory-like properties now called trained immunity. After certain infections or BCG vaccination, innate cells like monocytes and NK cells show enhanced responsiveness to unrelated pathogens for weeks or months. This epigenetic reprogramming involves histone methylation changes at promoter regions of inflammatory genes. It means the old classification of innate as purely non-specific and non-memorable is incomplete. Trained immunity blurs the boundary between the two arms, particularly in tissues where macrophage populations persist long-term.
Another practical consideration is the concept of original antigenic sin. When a person encounters a slightly different strain of a pathogen they have seen before, their adaptive immune system preferentially reuses pre-existing memory B cells recognizing conserved epitopes rather than generating new responses against strain-specific epitopes. This happens because memory B cells have a survival and activation advantage over naive B cells. The consequence is that the immune response may be less effective against the new variant. This was particularly evident in influenza immunology and continues to complicate vaccine design for rapidly mutating pathogens like SARS-CoV-2 and RSV.
Get the Full Details

Why the Distinction Matters for Clinical and Research Applications
Therapeutic interventions targeting each arm operate on fundamentally different timelines. Innate immune modulators like Toll-like receptor agonists or cytokine therapies produce effects within hours to days. This makes them useful in acute settings such as sepsis management or as vaccine adjuvants. Adaptive immune therapeutics like monoclonal antibodies, CAR-T cells, or vaccination programs take days to weeks to reach full effect but can provide protection lasting years. Understanding which arm you are manipulating determines your expectation for onset, duration, and monitoring requirements. Vaccine design inherently leverages both systems. The antigen targets the adaptive arm through B cell and T cell recognition. The adjuvant targets the innate arm to provide the necessary danger signals that activate dendritic cells and drive appropriate T helper differentiation. An adjuvant-free vaccine often produces weak or short-lived immunity because dendritic cells require innate signaling through pathways like NF-kB or STING to mature and migrate to lymph nodes. This is why most successful human vaccines contain adjuvants, even if the mechanism is not always fully characterized. A limitation worth noting is that innate immune responses can sometimes cause more tissue damage than the pathogen itself. Neutrophil extracellular traps, complement activation, and excessive cytokine release are mechanisms designed to contain infection but can trigger systemic inflammation, acute respiratory distress syndrome, or septic shock. This immunopathology is a major cause of morbidity in severe viral and bacterial infections. Managing the innate response without ablation is difficult because partial inhibition risks reducing pathogen clearance while complete inhibition risks uncontrolled infection.
Adaptive immunity has its own limitations. Immunosenescence reduces the diversity and responsiveness of T and B cell repertoires in older adults, which is why elderly patients show poorer responses to vaccination and higher rates of infectious disease. Autoimmunity arises when adaptive tolerance mechanisms fail, allowing self-reactive lymphocytes to cause tissue damage. Transplant rejection represents an adaptive immune response against foreign histocompatibility antigens. These are not edge cases. They are built-in risks of a system that must constantly distinguish self from non-self with imperfect precision. The practical takeaway is that neither system operates independently. Innate signaling dictates the magnitude and quality of adaptive responses. Adaptive effectors produce cytokines and other signals that feed back to modulate innate cell function. Trained immunity adds a third layer that challenges the clean separation between the two. When you are designing experiments, interpreting clinical data, or evaluating therapeutic approaches, the relevant question is not which system is involved but how signals flow between them at each stage of the response.