Understanding Your Body's Two-Layer Defense
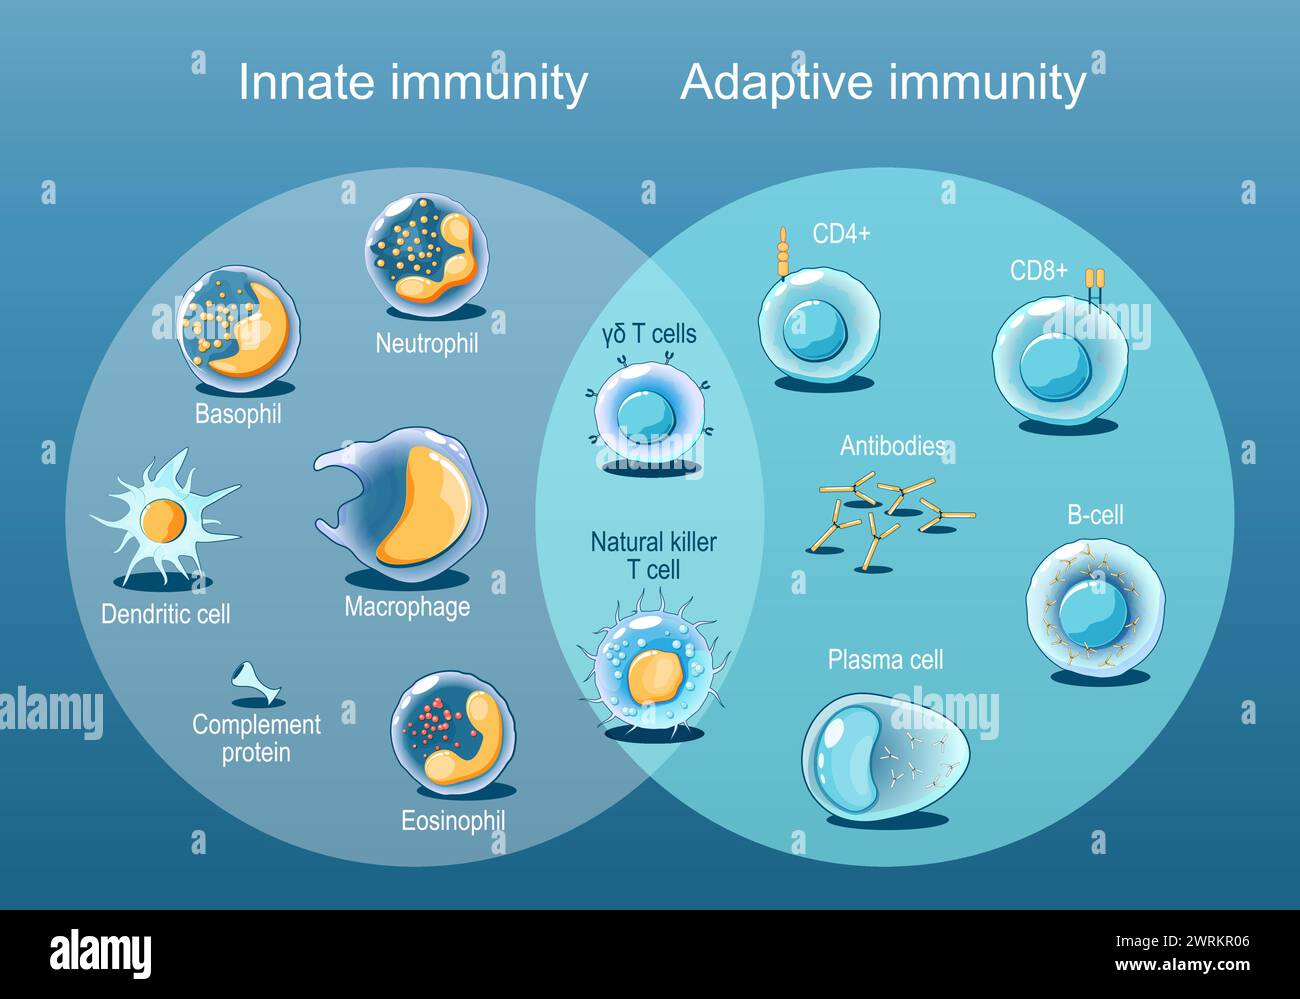
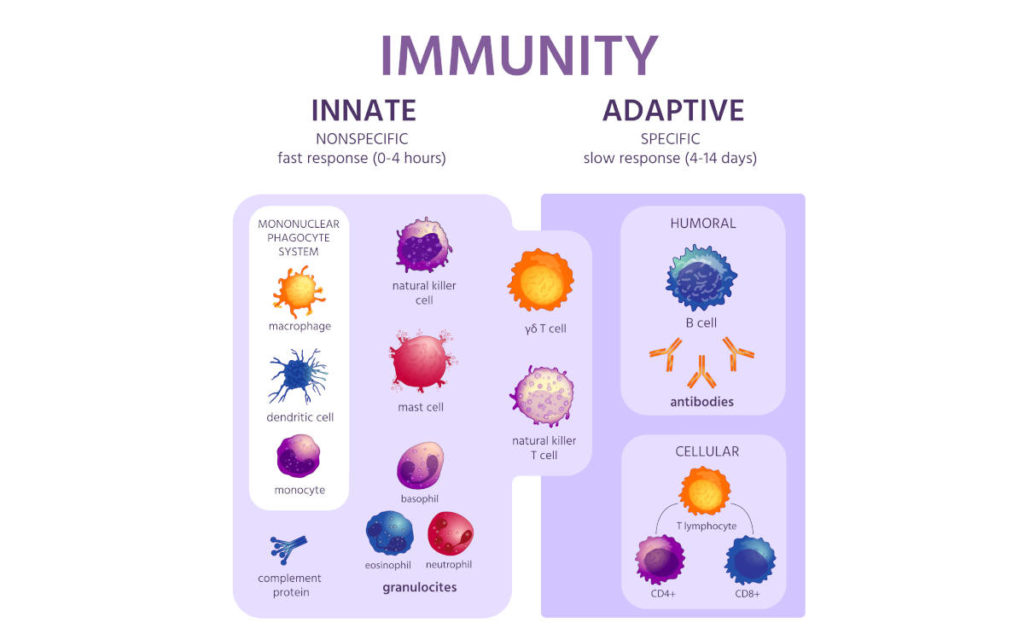
The innate immune system and the adaptive immune system are two distinct but interconnected layers of biological defense. They don't compete. They complement each other, and understanding how they actually work together matters more than memorizing definitions for anyone studying immunology or preparing for medical exams. Innate immunity is your first line of defense and it responds within minutes. It includes physical barriers like skin and mucous membranes, chemical barriers such as stomach acid and lysozyme in tears, phagocytic cells like neutrophils and macrophages, natural killer cells, and the complement cascade. The response is rapid but nonspecific. It recognizes broad patterns on pathogens through pattern recognition receptors like Toll-like receptors, not individual antigens. Adaptive immunity takes days to activate but provides highly specific recognition. B cells produce antibodies tailored to exact epitopes. T cells handle intracellular threats through direct cytotoxicity or coordinated helper functions. The critical feature here is immunological memory. Once your adaptive system encounters a pathogen, it remembers. Secondary exposure triggers a faster, stronger response. This is the principle behind vaccination, and it's why you don't get chickenpox twice.
The main cell types differ substantially. Innate immunity relies on neutrophils, macrophages, dendritic cells, eosinophils, basophils, mast cells, and natural killer cells. Adaptive immunity is built around B lymphocytes and T lymphocytes, subdivided into helper T cells (CD4+), cytotoxic T cells (CD8+), regulatory T cells, and memory B and T cells.
How They Actually Work Together in Practice
Here's where most textbooks fall short. The innate and adaptive systems don't operate sequentially like a relay race with clean handoffs. They're constantly communicating through cytokine signaling and antigen presentation. Dendritic cells are the critical bridge. They patrol tissues, engulf pathogens through phagocytosis, process antigens, and migrate to lymph nodes where they present those antigens via MHC molecules to naïve T cells. Without that dendritic cell step, adaptive immunity rarely activates properly. I spent considerable time studying this interaction during my immunology fellowship, and one specific edge case consistently trips people up. When someone has a severe combined immunodeficiency affecting thymic development, both T cell adaptive responses and the innate-adaptive bridge collapse. Patients present with recurrent infections from opportunistic organisms in the first year of life. Standard immune workups showing low CD4 counts can mislead clinicians into thinking this is purely an adaptive problem. The workaround I learned is to check thymic output directly using TREC quantification and evaluate NK cell function early, because treating only the adaptive deficit misses the root developmental failure. It changed how I approach diagnostic algorithms for pediatric immunodeficiency.
Get the Full Details

Coverage, Speed, and Specificity Compared
Innate immunity covers everything your body encounters. It responds immediately. It has no memory. Adaptive immunity covers specific pathogens your body has previously encountered or been vaccinated against. It responds slowly on first exposure but rapidly on subsequent exposures. It generates long-term memory that can last decades. Antigen recognition works differently between the two. Innate receptors recognize pathogen-associated molecular patterns like lipopolysaccharide on gram-negative bacteria or double-stranded RNA from viruses. Adaptive receptors recognize unique antigenic epitopes through highly variable B cell receptors and T cell receptors generated by somatic recombination.
Important Limitations and Where Both Systems Fail
The adaptive immune system is not universally advantageous. Autoimmune diseases like type 1 diabetes and multiple sclerosis occur when adaptive responses mistakenly target self-antigens. The same memory mechanism that protects you from measles can turn against your own pancreatic beta cells or myelin sheaths. Immunopathology is a real risk, and sometimes the immune response causes more tissue damage than the original infection. The innate system has its own ceiling. Certain pathogens have evolved specific mechanisms to evade or suppress innate detection. Mycobacterium tuberculosis inhibits phagosome-lysosome fusion inside macrophages. Herpes simplex virus blocks MHC class I presentation to avoid cytotoxic T cell detection. These evasion strategies mean neither system is sufficient alone, which is precisely why evolution produced two interdependent layers. Neither system works well in isolation under aging conditions. Immunosenescence degrades T cell receptor diversity and reduces thymic output with age. Innate immune responsiveness also declines, with neutrophils showing reduced chemotaxis and phagocytic capacity in elderly patients. Vaccine efficacy drops noticeably after age sixty-five, and infection severity increases. This is a well-documented bottleneck that affects clinical outcomes significantly.
Key Players and Their Functions
Neutrophils are the most abundant white blood cell and the primary responders to bacterial infection. They arrive at infection sites within hours and release antimicrobial granules and neutrophil extracellular traps. Macrophages are larger phagocytes that also function as antigen-presenting cells, linking innate recognition to adaptive activation. Natural killer cells bridge both systems. They kill virally infected cells and tumor cells without prior sensitization, which is an innate mechanism, but they also secrete cytokines that shape adaptive immune responses. Eosinophils target parasitic worms and contribute to allergic responses through histamine and major basic protein release. Mast cells stationed in tissues release histamine during allergic reactions and anaphylaxis, increasing vascular permeability and recruiting other immune cells. On the adaptive side, helper T cells coordinate responses by secreting cytokines that activate B cells, macrophages, and cytotoxic T cells. Cytotoxic T cells directly destroy infected or cancerous cells through perforin and granzyme release. Regulatory T cells suppress excessive immune responses and maintain tolerance to self-antigens. Memory B and T cells persist long after infection clears, providing rapid protection upon re-exposure.

The complement system illustrates innate adaptability within its own framework. The classical pathway bridges both systems by activating through antibody-antigen complexes, while the lectin and alternative pathways operate independently of antibodies. All three converge on C3 convertase, leading to pathogen opsonization, inflammation, and membrane attack complex formation that punches holes in bacterial cell walls.
Vaccination and Clinical Relevance
Vaccines exploit the adaptive immune system's memory capability by exposing the body to antigens without causing disease. Live attenuated vaccines like MMR trigger both humoral and cell-mediated immunity, typically providing lifelong protection after a single series. Inactivated vaccines like the flu shot primarily stimulate antibody production and require annual boosters because the antigenic drift of influenza viruses constantly rewrites the recognition profile. Understanding the distinction between these two systems matters clinically. A patient with Bruton's agammaglobulinemia lacks functional B cells and therefore cannot mount antibody responses. They survive with regular immunoglobulin replacement therapy but remain vulnerable to encapsulated bacteria. A patient with chronic granulomatous disease has a phagocyte defect in the innate system. Their adaptive immunity is intact, but without proper phagocytic killing, granulomas form and persistent infections develop. Treating these conditions requires understanding which layer is compromised. The innate versus adaptive immune system framework remains foundational in immunology education and clinical practice. Neither system is better than the other. They are interdependent. Innate immunity buys time and provides initial containment. Adaptive immunity provides precision and lasting protection. Both fail without the other under most realistic pathogen challenges.