Getting the Dose Right
Most nursing students freeze when they hit insulin math on their exams, and most new nurses panic when they encounter it on the floor. The math itself isn't complicated. What trips people up is the context switching between unit conversions, dosage formulas, and pump programming, usually under time pressure.
I've watched nurses second-guess themselves over Sliding Scale Insulin calculations for years. The core problem is rarely the arithmetic — it's skipping verification steps because the numbers looked "close enough" at a glance.
The Formula Framework
Here is the basic structure you will use repeatedly:
D = Desired dose (what the provider ordered)
H = Have on hand (what is available in the medication room)
Q = Quantity (volume or units per container)
The formula is D divided by H, multiplied by Q. This gives you the volume to administer. For insulin, H and Q often look identical since insulin comes in units per milliliter, usually U-100, meaning 100 units per 1 mL. That simplifies things, but it does not eliminate the risk of error.
Let me walk through a realistic example. A patient needs 18 units of Regular insulin subcutaneously. Your vial is U-100. You calculate 18 divided by 100, multiplied by 1. That equals 0.18 mL. You draw that up using an insulin syringe calibrated in units, not milliliters, which means you read directly to the 18-unit mark on the syringe. The 0.18 mL figure is just the mathematical equivalent.
Sliding scale calculations add another layer. You are looking up a patient's blood glucose against a scale and determining the dose. A typical scale might read: 200 to 250 mg/dL equals 4 units, 251 to 300 equals 8 units. The calculation is straightforward lookup, but the danger is rounding incorrectly or misreading the range boundaries. I once had a nurse administer 6 units instead of 8 because the blood glucose was 252 and she rounded down to the 200 to 250 bracket. That is a real near-miss I saw in practice. The workaround was simple: never round the glucose value. Use the exact reading and match it precisely to the scale ranges. Make it a habit to read the range inclusive of the lower bound and exclusive of the upper bound, like 200 up to but not including 250, then 250 up to but not including 300.
Pump calculations work differently. If a patient is on an insulin drip, you are calculating an hourly rate in units per hour, then converting that to milliliters per hour based on the concentration of the bag. A common concentration is 100 units of Regular insulin in 100 mL of normal saline, which makes the math almost too easy. 1 unit per hour equals 1 mL per hour. That simplicity is what kills people. They stop verifying because the numbers look trivial.
I encountered a case where a new nurse was running a heparin-insulin drip and set the pump to 10 mL per hour when the order called for 10 units per hour. Because the concentration was 1 unit per 1 mL, the math *should* have been identical, but the order actually called for a different concentration bag that had been mixed on a different shift. The pump was delivering 10 times the intended dose. I caught it during my nightly med pass when I noticed the bag had been hung at 0600 and the concentration label said 200 units in 250 mL, not 100 units in 100 mL. The hourly rate needed to be recalculated to 12.5 mL per hour to maintain the 10 units per hour order.
This is why you always verify the bag concentration independently before setting any pump rate. Do not assume standard concentration. Do not assume the label is correct without physically reading the bag yourself.
Common Pitfalls and What Actually Happens
Several patterns show up consistently in clinical practice. The first is the U-500 insulin confusion. Regular insulin is U-100, but some patients on high-dose regimens are prescribed U-500 Regular insulin, which contains 500 units per milliliter. If you use a standard U-100 syringe to draw up U-500, the markings are wrong. A U-500 syringe is mandatory. Using a U-100 syringe with U-500 insulin means every unit marking on the syringe represents five times the actual dose. This is one of the most dangerous calculation errors in nursing, and it is entirely preventable.
The second pitfall is basal-bolus mismatch. When calculating mealtime bolus doses, you need the patient's carbohydrate ratio and correction factor. These are individualized per patient. A typical carb ratio might be 1 unit of insulin per 12 grams of carbohydrate. A correction factor might be 1 unit for every 50 mg/dL above target. If a patient eats 48 grams of carbohydrate and their blood glucose is 220 with a target of 120, the calculation is: carbs divided by ratio equals 48 divided by 12 equals 4 units. Correction dose equals 220 minus 120 divided by 50 equals 2 units. Total is 6 units. Simple. Wrong if you use the wrong ratio or forget the correction component entirely.
I have seen nurses calculate only the carb coverage and skip the correction dose, or vice versa, resulting in significant hyperglycemia or hypoglycemia depending on which part was missed. The habit to develop is writing out both components before adding them. Never calculate mentally across both components simultaneously.
Advanced Nuances Beginners Miss
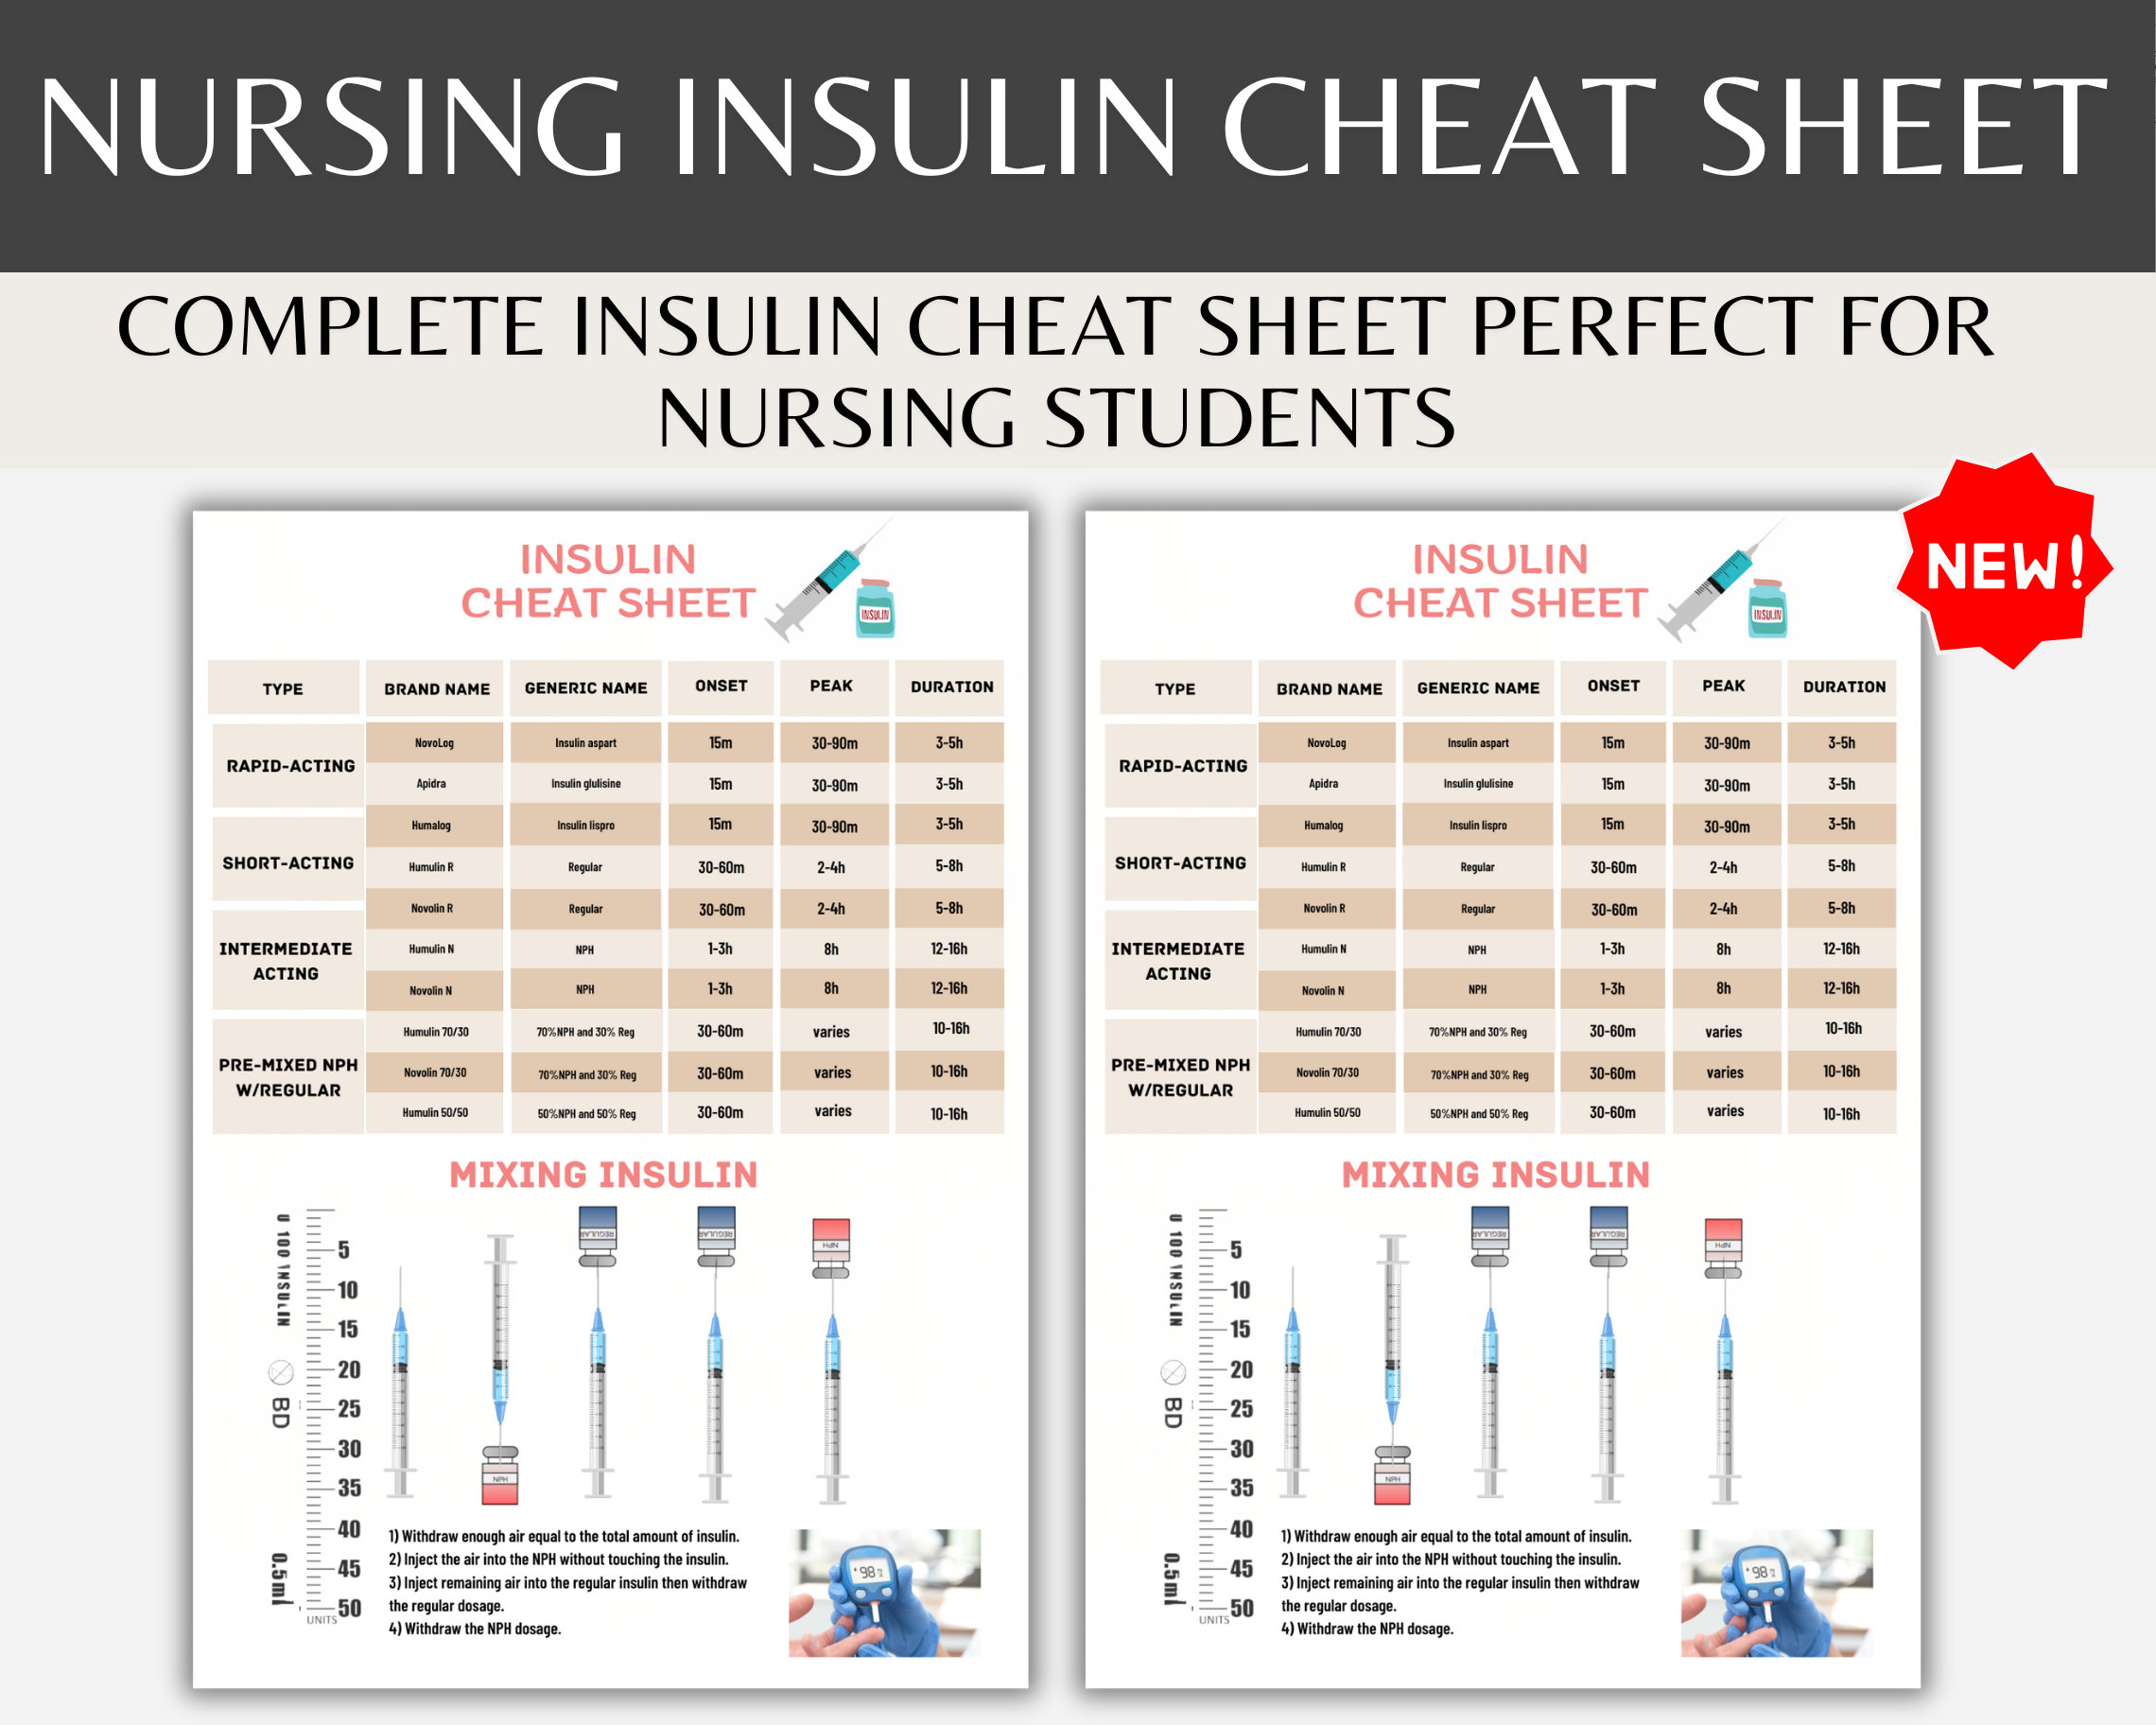
Insulin half-life matters more than textbooks typically emphasize. Regular insulin peaks in 2 to 4 hours and lasts 5 to 8 hours. Rapid-acting analogs like lispro and aspart peak in 1 to 3 hours and last 3 to 5 hours. When calculating timing for administration relative to meals, this difference is critical. Regular insulin should be given 30 minutes before a meal. Rapid-acting analogs should be given within 15 minutes before or immediately after starting a meal. Getting this timing wrong does not change the dose calculation, but it changes the clinical outcome significantly.
Another nuance is renal impairment. In patients with reduced kidney function, insulin clearance drops, meaning the same calculated dose can produce a prolonged and exaggerated hypoglycemic effect. There is no standard adjustment formula for this in nursing calculations, but experienced nurses factor it in clinically. If a patient's creatinine clearance is below 30, the dose you calculated correctly may still be too much. This is where calculation meets clinical judgment, and it is the gap most exam questions ignore.
Insulin Administration Nursing Calculations in Practice
On a busy med-surg floor, you might handle 4 to 8 insulin administrations per shift. Some are simple subcutaneous injections. Some are complex drip titrations. The time investment varies. A straightforward subq dose with verified calculation takes about 3 to 5 minutes from reading the order to administration. A drip initiation with bag preparation, concentration verification, and pump programming takes 15 to 20 minutes if everything goes smoothly. If you catch an error mid-process, it resets to zero and adds 10 to 15 minutes of rework.
The most practical tip I can offer is this: keep a small reference card with the standard insulin concentrations, the common sliding scale ranges used at your facility, and the formula for drip rates. Not because the math is hard, but because under workload pressure, cognitive bandwidth drops and simple verification aids prevent the kind of errors that do not show up until hours later when the patient becomes symptomatic.
There is no app or tool that replaces verifying the order against the patient's actual prescription. Automated systems flag some errors, but they miss others, particularly when the order itself is ambiguous or when concentration mismatches occur between the EMR documentation and the actual medication dispensed. The system I recommend personally is a two-person verify for all IV insulin orders and any sliding scale intervention where the calculated dose exceeds your facility's high-dose threshold. Most places set this at 10 units or more for subcutaneous corrections. It adds two minutes to the process and has prevented at least three near-misses in my experience.
What the Exams Actually Test
NCLEX-style questions on insulin calculations tend to test three things simultaneously. They want to see that you can convert between units and milliliters. They want to see that you can apply a sliding scale correctly. And they want to see that you recognize when a calculated dose is clinically inappropriate regardless of the math. The third point is where most students lose points. A question might present a scenario where the mathematical answer is correct but the clinical situation makes the dose unsafe, such as a hypoglycemic patient receiving a correction dose, or a patient with known renal failure receiving a standard dose. The right answer is not always the calculated number.
For practical competency exams, you will typically be asked to calculate a dose, draw it up correctly, and demonstrate administration technique. The calculation component usually involves one sliding scale lookup and one drip rate conversion. Time allocated is approximately 10 minutes for the full station. Rushing through the calculation to save time for the administration portion is a mistake. The calculation is worth the same points as the technique, and a wrong calculation means you are administering the wrong dose regardless of how well you pinch the skin or inject at the correct angle.