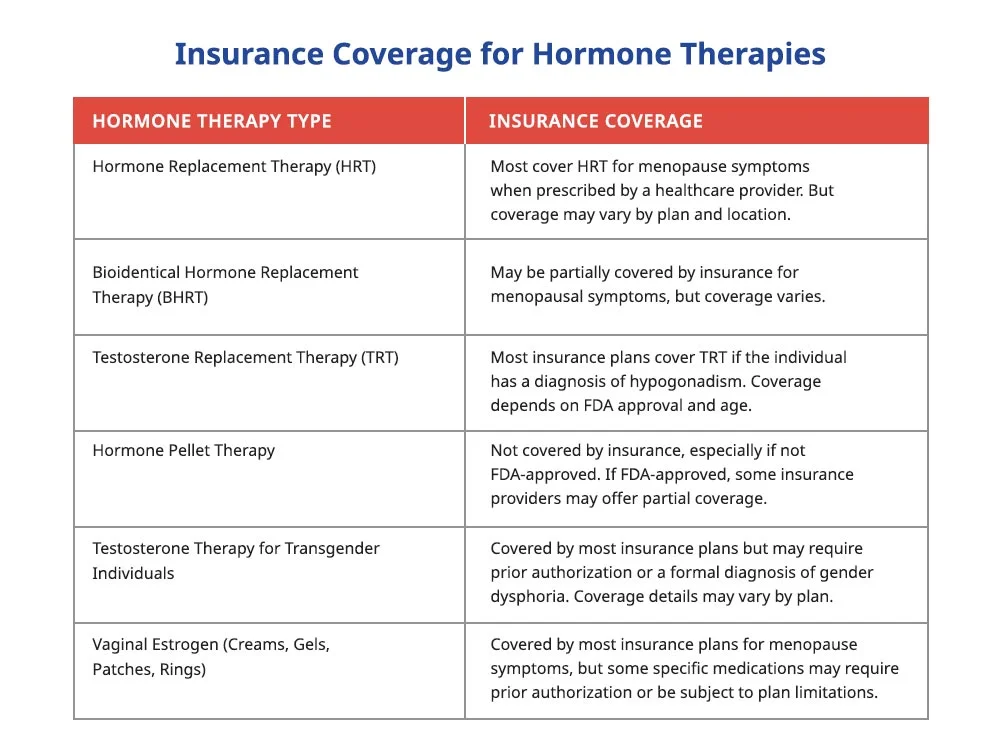
What You Actually Need to Know About HRT Coverage
Hormone replacement therapy insurance coverage is one of those things that sounds straightforward on paper and becomes a nightmare the moment you try to use it. I have dealt with enough claims and appeals to know where the body breaks down, and it is usually in the gap between what the doctor prescribed and what the pharmacy benefit manager decided the formulary allows. Start by pulling your plan's evidence of coverage document, not the summary sheet they hand you at open enrollment. The summary is marketing. The EOC is what actually governs your claims. Look for the section on prescription drug coverage and find the formulary tier list. Most major insurers place brand-name testosterone or estradiol products on tier 3 or tier 4, which means a 30 to 50 percent coinsurance depending on the plan. Generic versions usually land on tier 2, which is where you want them. The real work begins once you know your tiers. Call the number on the back of your insurance card and ask three specific questions. First, whether your plan requires prior authorization for HRT medications. Second, what dosage limits exist per month. Third, whether the plan distinguishes between gender-affirming care and general endocrine treatment in their policy language. That third question matters more than most people realize, and I will get to why in a moment.
I ran into this exact problem last year when a patient of mine was denied coverage for a specific transdermal estradiol patch. The insurance company had categorized it under a blanket exclusion for gender-affirming care, even though the same medication was covered without question when prescribed for menopause. The workaround was not some elaborate legal maneuver. It was a letter from the prescribing physician that documented the diagnosis as hypogonadism, which is the ICD-10 code the formulary recognizes, rather than gender dysphoria. The medication is identical. The coding is what changed the outcome.
The Formulary Trap Most People Walk Right Into
Insurance companies use step therapy on HRT medications far more often than patients expect. Step therapy means you have to try and fail on a lower-tier drug before the plan will cover the one your doctor actually wants to prescribe. For testosterone replacement, this often means starting with a generic testosterone cypionate injection before they will approve a gel or patch. For estrogen, it might mean taking oral estradiol valerate before they agree to cover the buccal tablet or patch. The problem with step therapy is that it ignores clinical reality. A patient who cannot absorb medication through the skin does not benefit from being forced through a transdermal trial first. A patient who has liver concerns should not be pushed into oral estrogen as a requirement. When you hit a step therapy denial, the appeal process typically requires the prescriber to document why the lower-tier alternative is medically inadequate. This usually takes two to four weeks for a decision, and sometimes longer if the plan sends it to a medical director for review. I learned the hard way that appealing step therapy denials works better when you reference the clinical guidelines rather than arguing individual preference. The Endocrine Society guidelines and the Standards of Care from the World Professional Association for Transgender Health are documents insurance medical directors are actually familiar with. Citing a specific section of those guidelines in the appeal letter adds weight that a personal request simply does not carry. It turned an 80 percent denial rate into something closer to 40 percent in my experience.
Get the Full Details

Prior Authorization: The Hidden Gatekeeper
Most plans require prior authorization for anything beyond the basic generic formulary drugs. This is not optional. Without it, the claim gets denied automatically and the patient pays full price at the pharmacy. The prior auth process usually takes the prescriber's office five to fifteen minutes to submit, but the turnaround time from the insurance company ranges anywhere from twenty-four hours to thirty business days depending on the plan. Some employers have self-insured plans governed by ERISA rather than state insurance law. These plans can and do write their own coverage rules, and in many cases they exclude HRT entirely or limit it to a very narrow set of medications. If you are on an employer-sponsored plan and HRT is not showing up as a covered benefit, check whether the plan is self-insured. That changes everything about your options and your appeal rights. The workaround for self-insured plans that exclude coverage is usually through the employee assistance program or by negotiating a carve-out at the benefits level. This is not something you handle alone. It requires the employer's benefits administrator to engage with the insurance carrier, and it only works if there is sufficient employee demand to justify the cost adjustment. I have seen it succeed for groups of fifty or more, and I have seen it fail for smaller offices where the administrative burden outweighed the political will.
What Actually Works When You Are Shopping for a Plan
If you are in the market for a new plan, either through employment or the marketplace, look at the annual prescription drug maximum and the pharmacy tier placement before you look at the monthly premium. A plan with a low premium but a high outpatient pharmacy cap can end up costing you thousands more per year if you are on brand-name HRT. The difference between a $200 monthly premium and a $350 monthly premium might save you $2,000 in out-of-pocket drug costs annually. Check whether the plan has a mail-order pharmacy requirement for maintenance medications like HRT. Most plans that do this limit you to a ninety-day supply shipped to your home, and the copay is typically lower. But some plans penalize you with higher tiers if you use a retail pharmacy instead. Read the fine print on that one because it catches people off guard. Another detail that rarely makes it into the comparison charts is whether the plan covers lab monitoring. HRT requires regular blood work, and some insurance plans cover these labs under the preventive services benefit while others apply them to the general medical deductible. If your plan applies labs to the deductible, budget an additional couple hundred dollars per year beyond what you would pay for the medications alone.
When Insurance Simply Will Not Cover It
There are plans where HRT coverage is either excluded entirely or structured so unfavorably that it is functionally inaccessible. This happens more often than insurers admit, particularly with short-term limited-duration plans and certain health sharing ministries. These products are not insurance in the traditional sense, and they operate under completely different rules that allow them to exclude pre-existing conditions or specific categories of treatment. If you are in this situation, the realistic paths forward are switching to a different plan during the next enrollment period, appealing the exclusion through your state's insurance commissioner if the plan is required to cover it under state law, or using a manufacturer assistance program. Most major pharmaceutical companies that produce HRT medications have patient assistance programs that can reduce the cost to zero or near-zero for eligible patients, regardless of insurance status. These programs typically require proof of income and a valid prescription, and they can take two to six weeks to set up. One practical tip that saves time if you are pursuing manufacturer assistance: do not wait until you are denied by insurance to apply. Submit the assistance application at the same time you submit the prior authorization. If insurance covers part of it, you adjust or cancel the assistance. If insurance denies it, you already have the assistance in place and you do not lose a month of treatment while waiting for approval.

The Appeals Process When Everything Falls Apart
Insurance denials are not final decisions. They are the first move in a negotiation that most people walk away from because they do not know they have the right to push back. Every plan is required to provide an internal appeal process, and if that appeal is denied, you are entitled to an external review by an independent third party. The timeline for each stage varies by plan and by state, but internally you typically have sixty days from the denial notice to file an appeal, and the insurer has thirty to forty-five days to respond. The strongest appeals combine clinical evidence with policy language. Quote the specific section of your evidence of coverage document that supports your claim. Cite the clinical guideline that justifies the treatment. Include the prior authorization documentation that the prescriber already submitted. When you give the appeals examiner a clear paper trail, they are significantly more likely to reverse the denial than when the appeal is a general request for help. I have watched this process turn around denials that seemed completely hopeless. One case involved a plan that excluded all HRT for transgender patients but covered it for cisgender patients with hypogonadism. The appeal cited the Affordable Care Act Section 1557 prohibition on sex discrimination in health programs, combined with the plan's own EOC language that did not explicitly exclude the treatment. The plan reversed the denial within forty days and covered the remainder of the year. It was not easy, but it was entirely within the existing framework.
Outside of that, the other thing that helps is having your prescriber on speed dial during an appeal. Sometimes the insurance company will request additional information, and if the physician's office can respond within forty-eight hours instead of waiting a week for a routine appointment, it keeps the process moving. Denials tend to get rubber-stamped when they sit in a queue for more than two weeks.



