ISTDP in Practice
What Intensive Short Term Dynamic Psychotherapy Actually Is
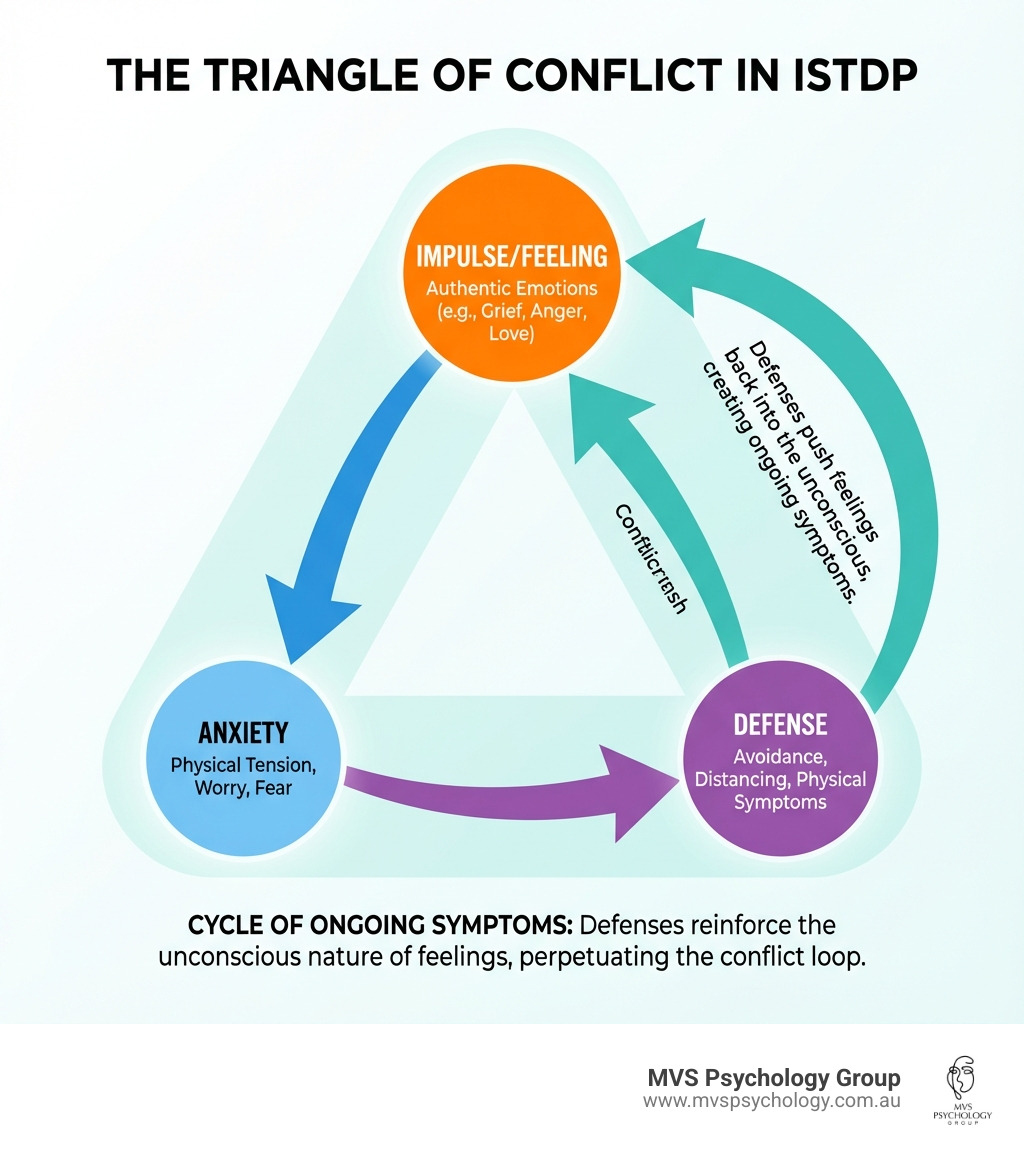
Intensive Short Term Dynamic Psychotherapy is a therapy model developed by Habib Davanloo that prioritizes rapid emotional processing over long-term insight. The core assumption is straightforward: most of your problems are maintained because you're unconsciously avoiding feeling certain emotions. The therapy works by systematically removing the barriers that keep those emotions locked away. It's not particularly gentle, and it's not designed to be. The mechanism is built around a concept called the dynamic triangulation. You have three things at play simultaneously: the patient's unconscious conflict, the anxiety that prevents them from accessing it, and the defense mechanisms they deploy to avoid both. The therapist's job is to identify which defenses are active in the room, challenge them directly, and use the therapeutic relationship to push the patient past the anxiety barrier so they can actually feel the underlying emotion. Once they feel it, the emotion tends to process itself. That's the basic arc. In a typical session, the therapist might spend the first twenty minutes identifying what the patient is doing to avoid feeling something. This isn't speculation. The patient will demonstrate it through body language, topic shifts, intellectualization, silence, or direct disagreement with the therapist's interpretations. The therapist names it. The patient usually resists. The therapist pushes again. This push-and-resist cycle is where most people think the therapy fails, but it's actually where the work happens. Avoiding the resistance means avoiding the anxiety that needs to be metabolized.
How It Feels in the Room
The patient is often confused or frustrated during the early sessions. They came in wanting to talk about their life circumstances, their relationship problems, their job stress. The therapist is asking them to close their eyes and notice what happens in their body when they think about something difficult. Most patients have never done this. They report feeling nothing, or they feel vague discomfort, or they feel anxious and can't articulate why. The breakthrough moment usually comes when the therapist connects a current emotional block to an earlier relational template. Not through a long historical analysis, but through a direct interpretation in the here-and-now. "When I suggest you focus on your chest, you tense up and say you feel nothing. That tension is exactly what happens when you try to tell your father how you actually feel. You shut it down before it can surface." That kind of intervention is blunt. It's supposed to be. The goal is to make the unconscious pattern conscious in a way that creates immediate experiential resistance, not intellectual agreement. I ran into a specific case a while back involving a patient who was extremely high-functioning in every domain. She was a senior consultant, articulate, able to describe her defense mechanisms with clinical precision. Standard ISTDP protocol would have her identified a defense and challenged it. But she had already intellectualized every defense I threw at her. She'd read the books. She knew what avoidance looked like. Every interpretation was absorbed and deflected through analysis. The therapy was going nowhere after six sessions.
The workaround was to stop interpreting and start directing. Instead of asking her to explore her resistance, I gave her a specific behavioral task: for the next week, every time she felt the urge to analyze a feeling, she had to write down what her body was doing instead. Heart rate, muscle tension, breath pattern. She had to report the physical data, not the cognitive narrative. On the seventh session, she brought me a notebook full of physiological observations. She'd finally been forced out of her intellectual fortress by having to engage with somatic data she couldn't argue with. That technique — redirecting from cognitive interpretation to somatic tracking — is something I've used more often than I'd like to admit. It bypasses the analytic mind when the analytic mind is the primary defense.
Get the Full Details

The Technical Core
The standard ISTDP protocol has three phases. The first phase is creating a therapeutic climate where the patient understands that the therapist's directness comes from a desire to help them change, not to criticize them. This is usually achieved through a technique called the supportive-individualizing-stimulating triangle. The therapist supports the patient's wish to feel better, individualizes the approach by naming the patient's specific defenses, and stimulates the patient to examine those defenses rather than just acknowledge them passively. The second phase is dismantling the defenses. This involves escalating interventions when the patient resists. Common techniques include directive pressure ("Tell me what you're feeling right now"), challenge interpretations ("You just described that as anxiety, but your body looks like it's preparing to flee"), and intensification (asking the patient to amplify an emotion they're barely sensing). The intensification step is critical. If a patient says their chest feels tight, the therapist might ask them to make the tightness louder. To exaggerate it. To push it further. The idea is that by consciously amplifying a sensation, the patient moves from passive awareness to active engagement with it, which breaks the avoidance cycle. The third phase is working through. Once the patient has accessed the repressed emotion — grief, rage, fear — the therapist helps them integrate it. This isn't a gentle reflective process. It's more like repeated exposure. The patient is brought back to the emotional state multiple times, each time with slightly less anxiety, until the emotion can be felt without triggering the old defense. The number of repetitions varies. Some patients need two or three. Others need ten or twelve across the course of the treatment.
Where It Actually Fails
ISTDP is not universally applicable. People with significant personality disorders, especially borderline and narcissistic pathology, often cannot tolerate the intensity of the intervention. Their structural defenses are too fragile. Pushing them into emotional overwhelm doesn't lead to processing — it leads to regression, acting out, or termination. I've seen therapists try to run standard ISTDP on patients with borderline features and end up with a client who was destabilized for weeks after a single session. That's not a critique of the method itself. It's a critique of applying it to the wrong population. Another failure mode is the patient who is emotionally literate but structurally avoidant. These are people who can describe their feelings in detail but have never actually experienced them as embodied states. They're narrators of their own interior lives, not inhabitants. For these patients, the standard interpretation-challenge cycle moves too slowly because the patient keeps translating somatic experience back into cognitive language. The somatic redirection technique I mentioned earlier helps, but it requires patience and a willingness to shift protocols mid-treatment. Most training programs don't emphasize this flexibility enough. There's also the issue of therapist stamina. ISTDP is demanding. It requires the therapist to maintain a consistent level of intensity and presence across many sessions. Some therapists burn out because they're trying to sustain a pace that's unsustainable. A realistic expectation for a time-limited ISTDP course is somewhere between twelve and twenty-five sessions, depending on the complexity of the case. Anything shorter than twelve sessions is usually insufficient for anything beyond surface-level personality issues. Anything longer than twenty-five suggests either a complicated case or a therapist who hasn't learned when to escalate versus when to consolidate.
If you're considering this approach for yourself, the practical question isn't whether it will work. It's whether your capacity for emotional tolerance aligns with the intensity of the method. People who need a slow, accommodating therapeutic relationship will find ISTDP hostile. People who feel stuck in avoidance patterns and want direct confrontation tend to respond well. There's no middle ground that satisfies both.