Reading a CBC is mostly pattern recognition, not math
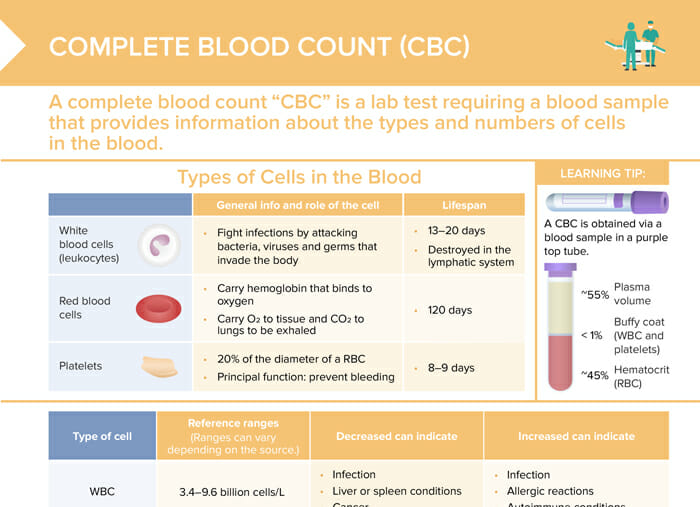
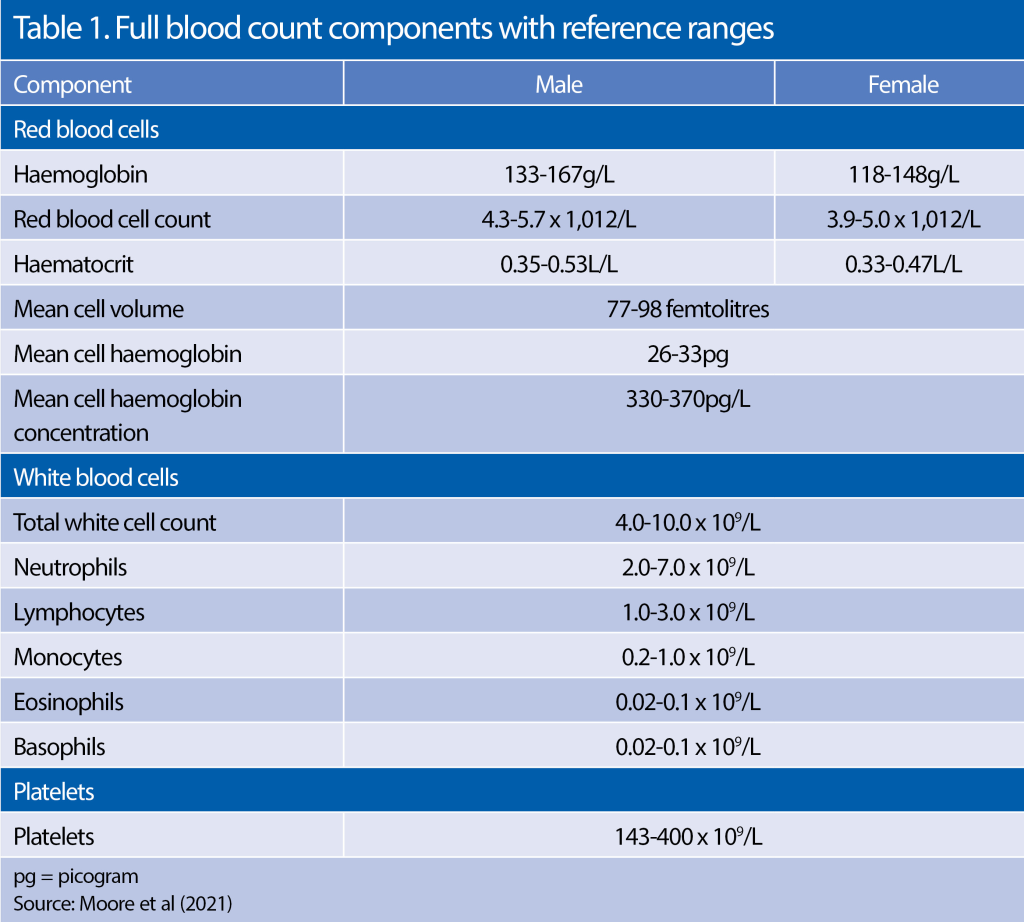
When you pull up a CBC, the first thing you do is look at the three main lineages: red cells, white cells, and platelets. Everything else branches off from there. A CBC reports hemoglobin, hematocrit, RBC count, MCV, MCH, MCHC, RDW, platelet count, and the various differential counts. That is the raw data. The work starts after that, when you figure out whether the numbers make sense together or if something is off. The hemoglobin and hematocrit tell you about oxygen-carrying capacity. If hemoglobin is low, you check the MCV to see if the red cells are small, normal, or large. Small cells point toward iron deficiency or thalassemia. Large cells point toward B12 or folate problems, alcohol use, or certain medications. Normal size with low hemoglobin usually means anemia of chronic disease or early iron deficiency before the cells shrink. This is the most common framework, and it works most of the time. I once had a patient whose hemoglobin was 11.2 with a normal MCV of 88. On paper it looked fine. But the RDW was elevated at 15.8 percent, which meant the red cell population was uneven. I checked the iron studies and found early iron deficiency that had not yet affected cell size. Missing the RDW would have let that slide. That is one of the details beginners often skip because the automated flag did not light up.
White blood cell counts break down into neutrophils, lymphocytes, monocytes, eosinophils, and basophils. Each one carries different clinical weight. Neutrophilia usually means infection or inflammation, but it also shows up with stress, steroids, and exercise. Lymphocytosis points toward viral infections or certain chronic conditions. Eosinophilia is a red flag for allergies, parasites, or drug reactions. Basophils are rare, so when they are elevated, you pay attention. Monocytes tend to rise in chronic inflammatory states and recovery phases of infection. Platelets are straightforward until they are not. A low count can mean destruction, sequestration, or decreased production. A high count is reactive in most cases, often from iron deficiency, inflammation, or post-splenectomy. True thrombocythemia is uncommon and requires hematology referral. The smear review catches what the machine misses, like pseudothrombocytopenia from EDTA clumping. I have seen flagged low platelets turn out normal once the smear was reviewed, saving the patient an unnecessary workup.
Advanced nuances that save you from embarrassment
MCV does not always reflect true cell size. Macrocytosis can appear with reticulocytosis because young red cells are larger. So if a patient is actively bleeding or hemolyzing, the MCV goes up even if the underlying condition is microcytic. You have to cross-reference the reticulocyte count or the red cell index pattern to get the real picture. Another pitfall is assuming a left shift always means bacterial infection. A left shift can occur in severe stress, tissue necrosis, or after glucocorticoid administration. The morphologic details matter: toxic granulation, Dohle bodies, and cytoplasmic vacuolization lean toward infection. Band forms without those features may just be stress demargination. When I see a monocytosis above 1.0 x 10^9/L persisting for more than three months, I think chronic infection, autoimmune disease, or myelodysplasia. The timeline matters. Acute monocytosis during recovery from neutropenia is normal. Chronic elevation is not. This distinction separates routine follow-up from urgent hematology consultation.
Get the Full Details
Hemoglobin A1c interference is another practical concern. Conditions like hemoglobinopathies, recent transfusion, and renal failure alter A1c reliability, and the CBC can hint at these issues. Elevated RDW with normal MCV in a diabetic patient should prompt you to question whether the A1c is trustworthy and consider fructosamine instead.
When the CBC lies to you
Automated counters are fast but blunt. They misclassify cells, miss basophils, and struggle with nucleated red cells. A sample with significant lipemia skews results. Hemolyzed samples corrupt potassium and some enzyme assays, though the CBC itself stays relatively intact. Cold agglutinins cause spuriously low RBC counts and high MCV. Warming the sample to 37 degrees Celsius before running it fixes most of those artifacts. Polycythemia vera can present with an apparently normal CBC early on because erythrocytosis coexists with functional iron deficiency. The iron stores deplete as the red cell mass expands, and the MCV drops into the normal or low range. The JAK2 mutation test resolves the ambiguity. Without it, you might chase iron replacement and miss the real diagnosis. For patients on hydroxyurea, the MCV rises predictably. Do not mistake drug-induced macrocytosis for B12 deficiency. The reticulocyte count helps: it will be low with hydroxyurea and high with B12 deficiency and active hemolysis. Context is everything, and the CBC alone rarely provides it.
I prefer pairing the CBC with a peripheral smear whenever the differential looks abnormal, the flags are scattered, or the clinical picture does not match the numbers. Smear review takes maybe ten minutes and catches problems machines regularly overlook. It is not mandatory for every routine CBC, but it is mandatory when the numbers surprise you. The bottom line is that Interpretation Of Complete Blood Count results depends on connecting the dots across lineages, checking indices against each other, and knowing when the machine is wrong. Start with hemoglobin and MCV for red cells. Check the white differential for patterns. Look at platelets and flag any discordance. Then decide whether a smear or additional labs are needed. Most abnormalities sort themselves out quickly if you follow that sequence.