Reading Labs Without Losing Your Mind
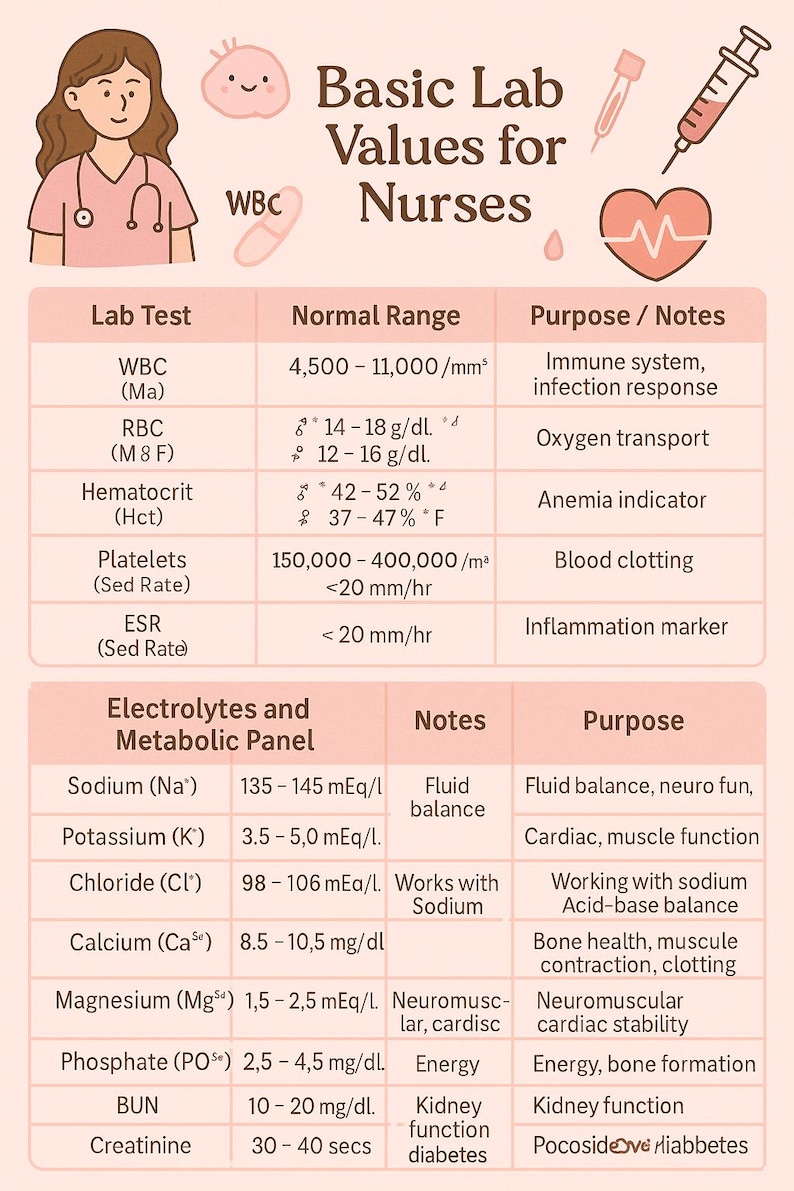
Most nurses are expected to interpret blood results on the fly during medication passes or rapid responses. The problem is that textbooks teach you reference ranges in isolation while practice requires you to read a panel of twenty values at once and figure out which ones actually matter for the patient in front of you. I spent years watching new nurses miss critical patterns because they were reading left to right, value by value, without a system. Here is how it works when you stop treating each number as an independent fact and start reading them like a story. The core mistake beginners make is anchoring on a single flagged value and stopping there. An elevated potassium grabs attention because the word "hyperkalemia" is drilled into you as an emergency. But the potassium of 5.4 might be hemolyzed from a difficult draw while the real issue is a sodium of 124 with a corresponding bicarbonate drop. You fix the wrong number and the patient gets worse. My rule is simple: read the electrolyte panel as a single unit before touching any other lab. Sodium, potassium, chloride, and bicarbonate interact. Change one and the others shift with it. If you do not check the anion gap after calculating it from those four values, you are leaving something behind. I had a patient who came in with confusion and a creatinine bump to 1.9. Everyone focused on the creatinine. The BUN was 62. That BUN-to-creatinine ratio above thirty pointed straight at pre-renal azotemia from dehydration, not intrinsic kidney damage. I pushed fluids and the creatinine dropped to baseline in twelve hours. If I had just treated the creatinine in isolation, the patient would have been sent for a CT scan and possibly a nephrology consult for no reason. That is the kind of pattern recognition that separates competent nursing from thorough nursing.
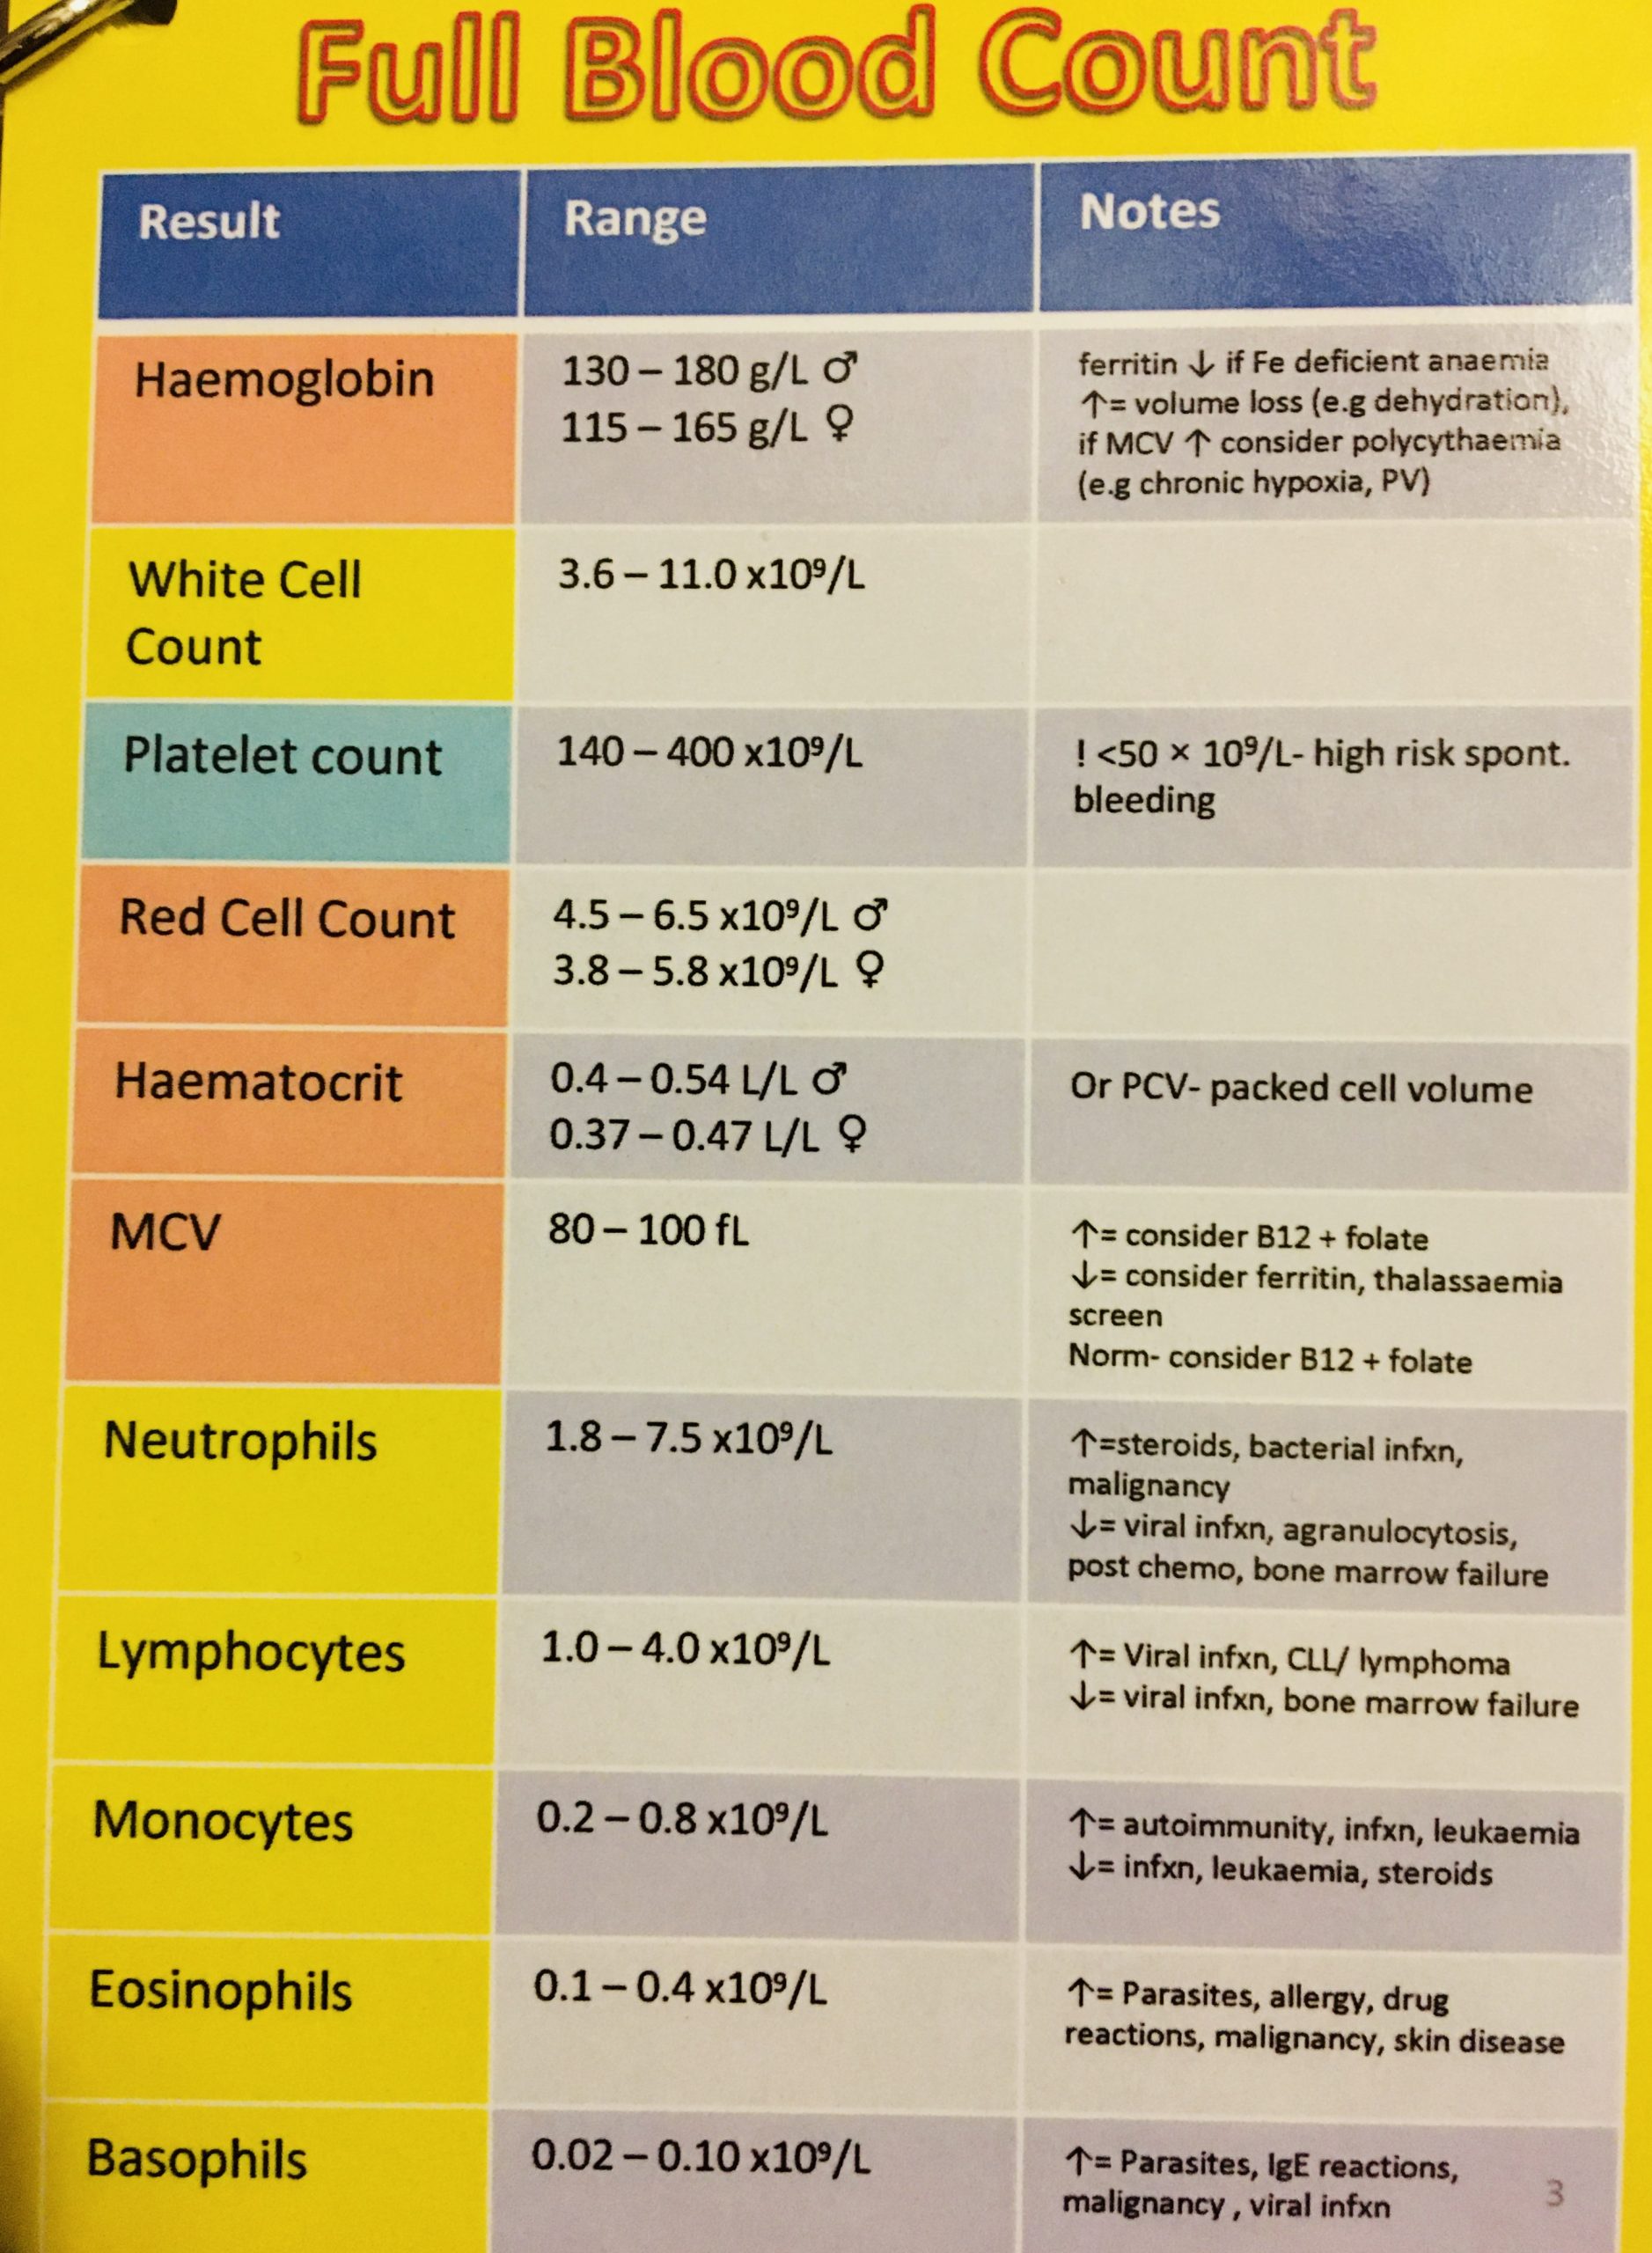
CBC interpretation follows the same principle. A white count of 14 sounds alarming until you look at the differential. Ninety percent neutrophils with a left shift tells a different story than sixty percent lymphocytes. And a band count of eight percent is clinically significant even when the total WBC is normal, especially in elderly patients whose immune systems do not mount dramatic leukocytosis the way younger patients do. I learned this the hard way with a seventy-eight-year-old woman who had pneumonia but her WBC never went above 10. Her band count was twelve. She was septic and her total white count would have made anyone think she was stable.
The Fast Pattern Method
Here is the method I use now and teach anyone who will listen. It takes about three minutes for a standard metabolic panel and a complete blood count when you know what to look for. You do not need a fancy formula calculator. A pen and a quick calculation are enough. First, scan for the critical flags. These are values outside the normal range that correlate with immediate clinical risk. Potassium above six or below twenty-five, sodium above one-sixty or below one-twenty, glucose above four-hundred or below fifty, troponin above the reference range, platelets below fifty. Anything in these zones gets documented and escalated immediately regardless of the rest of the panel. Second, calculate the anion gap. Subtract chloride and bicarbonate from sodium. The formula is Na minus Cl minus HCO3. Normal is between eight and twelve. A gap above twelve with a low bicarbonate means a high anion gap metabolic acidosis, which points toward conditions like diabetic ketoacidosis, lactic acidosis, renal failure, or toxic ingestion. A gap within normal range with low bicarbonate suggests a non-anion gap acidosis, usually from diarrhea or renal tubular issues. This single calculation narrows the differential significantly and it takes seven seconds to do by hand.
Get the Full Details

Third, look at the osmolality gap if you have a measured osmolality available. The calculated osmolality is two times sodium plus BUN divided by twenty-eight plus glucose divided by eighteen. If the measured osmolality is more than ten above the calculated value, you are dealing with unmeasured osmoles. Alcohol intoxication, ethylene glycol, and methanol all show up this way. I used this with a patient whose mental status did not match any visible cause. The ethanol level was negative but the osmolality gap was eighteen. We found out later she had been drinking windshield washer fluid. The gap saved hours of diagnostic delay. Fourth, track trends instead of isolated values. A hemoglobin of eleven might be normal for a chronic anemia patient but catastrophic for someone who was at fourteen two days ago. Always ask for previous results when you are unsure whether a number is alarming or expected. Electronic health records make this easier now but not every facility has trend graphs built in. Sometimes you have to pull the last three sets of labs yourself and compare them side by side.
Pitfalls That Waste Time and Endanger Patients
Microscopic hemolysis is the most common source of falsely elevated potassium. If the sample looks slightly pink and the potassium is only mildly elevated at five-point-three or five-point-four, repeat the draw from the opposite arm before calling the provider. A STAT potassium from a bad sample just creates noise and delays real treatment. Lipemic samples cause false hyponatremia through the ion-selective electrode effect. The lab might report sodium at one-twenty-five when the patient is actually at one-thirty-five. The plasma appears milky. In these cases the laboratory usually flags it and recommends direct potentiometry. Request it if the sodium does not match the clinical picture. Port draws are another trap. Taking blood from a line that is running normal saline gives you artificially low sodium and artificially high chloride. Always draw from a peripheral site or wait ten minutes after stopping the IV fluid before drawing if you have no other option. I once reviewed a panel from a port draw and the sodium looked critically low. The patient was acting completely normal. A repeat peripheral draw showed sodium at one-fourteen. The port had diluted everything.
Protein-bound medications can interfere with certain assays. Valproic acid competes with bilirubin for binding sites and skews total bilirubin readings. Phenytoin interferes with some creatinine methods. Know what medications your patient is on before you interpret the numbers, because a drug interaction might be the reason a value looks wrong.

When Lab Interpretation Fails Completely
No amount of pattern recognition replaces knowing when a lab result is unreliable. Hemolyzed, lipemic, and icteric samples invalidate a significant portion of the chemistry panel. If the lab flags a sample, do not waste time trying to interpret it. Request a redraw. The turnaround time for a redraw is usually under an hour and it saves you from making decisions based on garbage data. Chronic kidney disease patients live with elevated creatinine and altered electrolytes. Their "abnormal" values are their baseline. Comparing them to population reference ranges instead of their own history produces false alarms and unnecessary workups. Get the patient's baseline from their records or from their nephrologist's notes before you escalate anything. Point-of-care testing gives you faster results but less accuracy. A bedside glucose checker might read one-hundred-twenty while the lab result from the same draw is one-hundred-sixty. Do not use point-of-care values to make discharge decisions or adjust long-term treatment plans. Use them for immediate triage and confirm with lab results when you have time.
A Practical Workflow You Can Use Tonight
When you get a new set of labs, do this in order. Flag the critical values first. Calculate the anion gap. Check the BUN-to-creatinine ratio. Review the CBC differential, not just the totals. Compare to prior results if available. Look for sample quality issues like hemolysis or lipemia. Cross-reference with the patient's current medications and clinical presentation. Document your interpretation and any concerns in the chart. This process usually takes four to five minutes and catches the patterns that matter most. I keep a small laminated card at my workstation with the key formulas and critical thresholds. Anion gap, corrected calcium, osmolality, BUN-to-creatinine ratio. It took me months to memorize these and I still use the card because there is no reason to rely on memory when the calculation takes five seconds on paper. Every nurse should have their own version of this. Write it in the way that makes sense to you and keep it accessible during shift changes. Interpreting blood results is not about memorizing every normal range. It is about building a mental framework that lets you spot the relationships between values and recognize when a number does not fit the patient. The framework takes practice. The shortcut is to always look at the whole panel, calculate what you can calculate, and question any result that conflicts with what you see at the bedside. The patient will tell you if the lab is wrong more often than you think.