Working with Interqual Acute Adult Criteria 2013
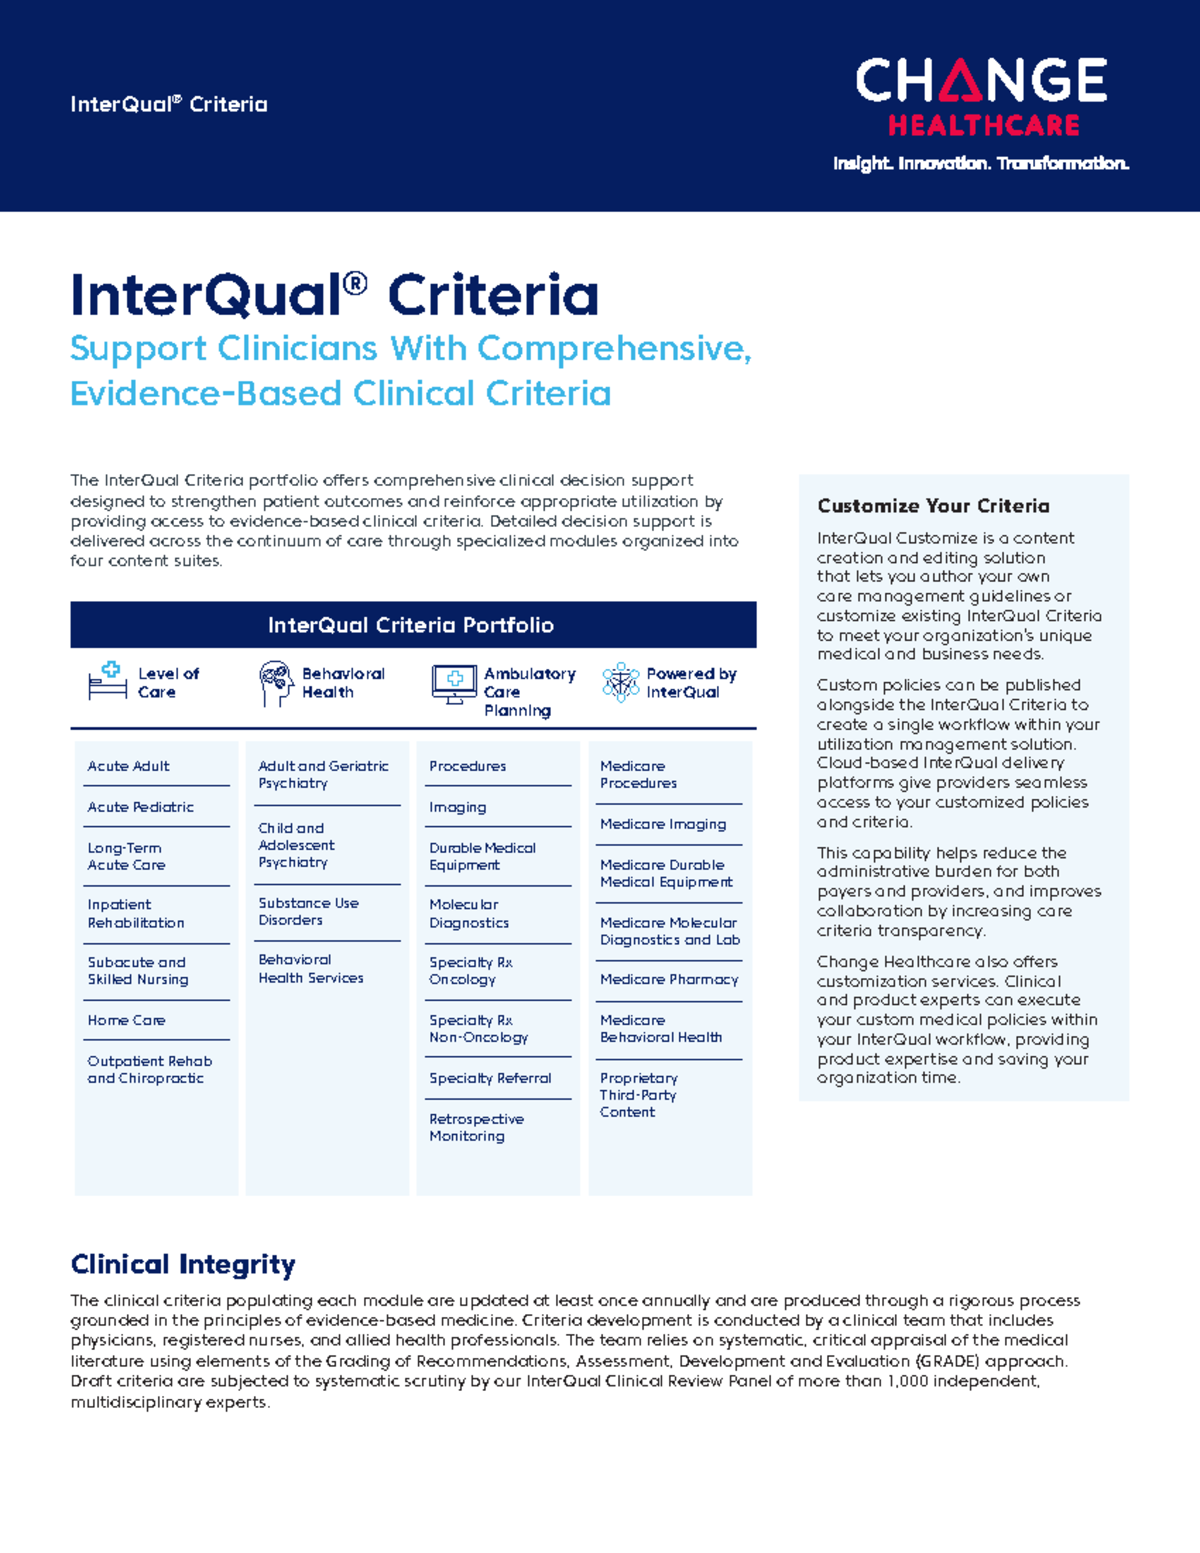
Most people running utilization management reviews don't actually know what changed in the 2013 clinical revisions for the acute adult criteria. They use the software, they click through screens, and they get approvals or denials. But when the devil is in the details, that lack of familiarity shows up fast in audit trails and peer-to-peer review outcomes. The 2013 revision cycle was one of the bigger overhaul periods for Interqual's acute inpatient criteria. It wasn't just a tweak to thresholds. Several sections got restructured, some criteria were retired, and new clinical concepts like medical necessity for behavioral health observation stays got formalized in a way that hadn't existed before. The MVP label you see attached to it is basically the initial vendor-published version before subsequent annual updates rolled in. If you're working with legacy data or older policy documents, that distinction matters because the scoring logic differs slightly between the MVP release and later patches.
Interqual Acute Adult Criteria 2013 Clinical Revisions Mvp
Getting your hands on the actual documentation is the first hurdle. The 2013 Clinical Revisions MVP manual isn't something you just find on a casual Google search. It lives inside the Milliman product library, which requires a paid Interqual subscription or an employer relationship with Milliman. If you're at an insurance company, a TPA, or a utilization management vendor, you should have access through your vendor portal. Log in, go to the reference library, and look for the 2013 Clinical Revisions update package. That's where the full criteria document lands. Third-party sites sometimes host copies, but I wouldn't trust those for anything compliance-related. The version numbers get fuzzy and you might be looking at a pre-release draft that doesn't match what your auditors expect. Here's what most people miss when they first start working through these criteria. The acute adult section is organized by body system and then by specific condition or procedure. Each criterion has a set of checkboxes that map to admission, continued stay, and outpatient surgery scenarios. The tricky part is that the criteria don't always align cleanly with how diagnoses are coded. I remember running a review where a patient came in with sepsis and acute respiratory failure, and the interqual application was flagging the case under a pneumonia criterion instead of the sepsis pathway. The documentation supported sepsis as the primary diagnosis, but the ICD-9 code sequencing and the way the algorithm parsed the comorbidities pushed it into the wrong bucket. The fix was to make sure the principal diagnosis code was linked correctly in the eligibility system and to attach a clarifying physician note that explicitly stated the sepsis was the reason for admission. It added about twenty minutes to the case, but it saved a denial that would have come back on audit. Another thing that trips people up is the difference between the criteria language and the documentation requirement. Interqual criteria tell you what the standard is. They don't always tell you exactly what clinical evidence satisfies that standard. For example, the criteria for orthopedic surgery admission might say the patient needs acute surgical intervention, but it won't spell out whether a plain X-ray is sufficient or if an MRI is required. That's where your clinical librarians and your physician advisors come in. You build internal documentation guidelines that bridge that gap. Without them, reviewers are guessing, and guessing is how appeals start.
Let me walk through a practical workflow for running a case through the 2013 acute adult criteria. First, pull the complete record. Not just the admission note and the discharge summary. I'm talking about the full lab panel, imaging reports, nursing flow sheets for at least the first forty-eight hours, and the physician progress notes. I've seen cases denied because a reviewer only had the admission paperwork and missed a lab trend that developed on day two which was the actual clinical justification for the extended stay. Second, identify the primary diagnosis and the top three secondary diagnoses. Map each one to the corresponding Interqual criterion. Don't skip the secondary diagnoses. A lot of the acute adult criteria have comorbidity modifiers that can shift a case from non-met to met, or vice versa. In the 2013 revision, several criteria added diabetes and renal failure as modifier conditions that change the acuity threshold. If you're not checking those, you're not running the full criterion.
Get the Full Details

Third, go through each checkbox in the relevant criterion and document yes or no with a citation to the medical record. I use a simple reference format like (Physician Note, 3/12/2013, pp. 3-4) so that any reviewer or auditor can find the supporting documentation in under thirty seconds. This sounds tedious, but it prevents the back-and-forth that slows down peer-to-peer reviews and internal appeals. One quick note: the 2013 MVP version of the criteria uses slightly different checkbox language than the 2014 and later versions. Make sure you're referencing the correct year's version. Mixing them up creates inconsistencies that external auditors catch immediately. Fourth, if the case doesn't clearly meet a criterion, look for alternate pathways. Sometimes a case that fails one criterion will meet another. A patient who doesn't qualify under the medical admission criteria might qualify under the surgical criteria if there's a documented planned procedure. The reverse is also true. I had a case where a patient with chest pain and negative cardiac enzymes didn't meet the medical observation criteria, but when I pulled the stress test order and the cardiology consult note, the case fit squarely under the elective cardiac procedure observation pathway. That one save prevented a member from filing a grievance. Now let's talk about where this system breaks down. The 2013 acute adult criteria have real limitations that you need to be aware of if you're relying on them for high-stakes decisions.
The biggest issue is that Interqual criteria are designed for population-level risk assessment, not individual patient care. They work well for the average case. They struggle with atypical presentations, complex multi-system patients, and cases that involve experimental or off-label treatments. I've seen reviewers deny cases for patients with rare autoimmune conditions simply because there was no matching criterion in the manual. The criterion set covers the common conditions pretty thoroughly, but it has blind spots. When you hit one of those gaps, you need a formal variance or exception process, and you need to document why the existing criteria don't apply. That usually requires physician advisor sign-off. Another limitation is the recertification timeline. The 2013 criteria use standard length-of-stay expectations for most conditions. For a typical pneumonia admission, that's around three to five days. But patients with complicated pneumonia, empyema, or those who are immunocompromised often need longer stays, and the criterion doesn't always account for that without additional documentation. The workaround is to reference the specific comorbidity modifiers in the criterion and make sure the medical record clearly documents the complication. If it's not in the record, the reviewer can't count it. There's also the issue of behavioral health criteria within the acute adult section. The 2013 revision expanded the behavioral health coverage significantly, but the criteria for psychiatric admissions are still one of the most contested areas in utilization management. The standards are subjective by nature, and different reviewers can reach different conclusions on the same case. I've seen two reviewers look at an identical psychiatric admission file and one approve while the other denies. That's not a flaw in the criteria per se, it's a feature of how subjective clinical judgment works. The best defense is thorough documentation and consistency in how your team applies the criteria.
If you're looking for a download of the 2013 Clinical Revisions MVP manual, your options are limited to legitimate channels. Milliman sells access through subscription licenses. Some hospital systems and insurance companies purchase enterprise licenses that include all historical versions. If you're a consultant or independent reviewer, you can contact Milliman directly about a single-user license. Avoid any site offering a free PDF download. Those are almost certainly outdated, incomplete, orpirated, and using them professionally exposes you to liability. The practical takeaway is that the Interqual Acute Adult Criteria 2013 Clinical Revisions Mvp is a solid foundational tool, but it's not a substitute for clinical judgment. It works best when you understand its structure, know where its gaps are, and have processes in place to handle the edge cases. Spend time with the actual manual, not just the software interface. The checkbox version in the application strips away a lot of the nuance that's in the full documentation. And when you run into a case that doesn't fit neatly, don't force it. Flag it, escalate it, and document the reasoning. That's how you stay compliant and how you protect your patients at the same time.