Setting Up and Working with Interqual Criteria in Practice
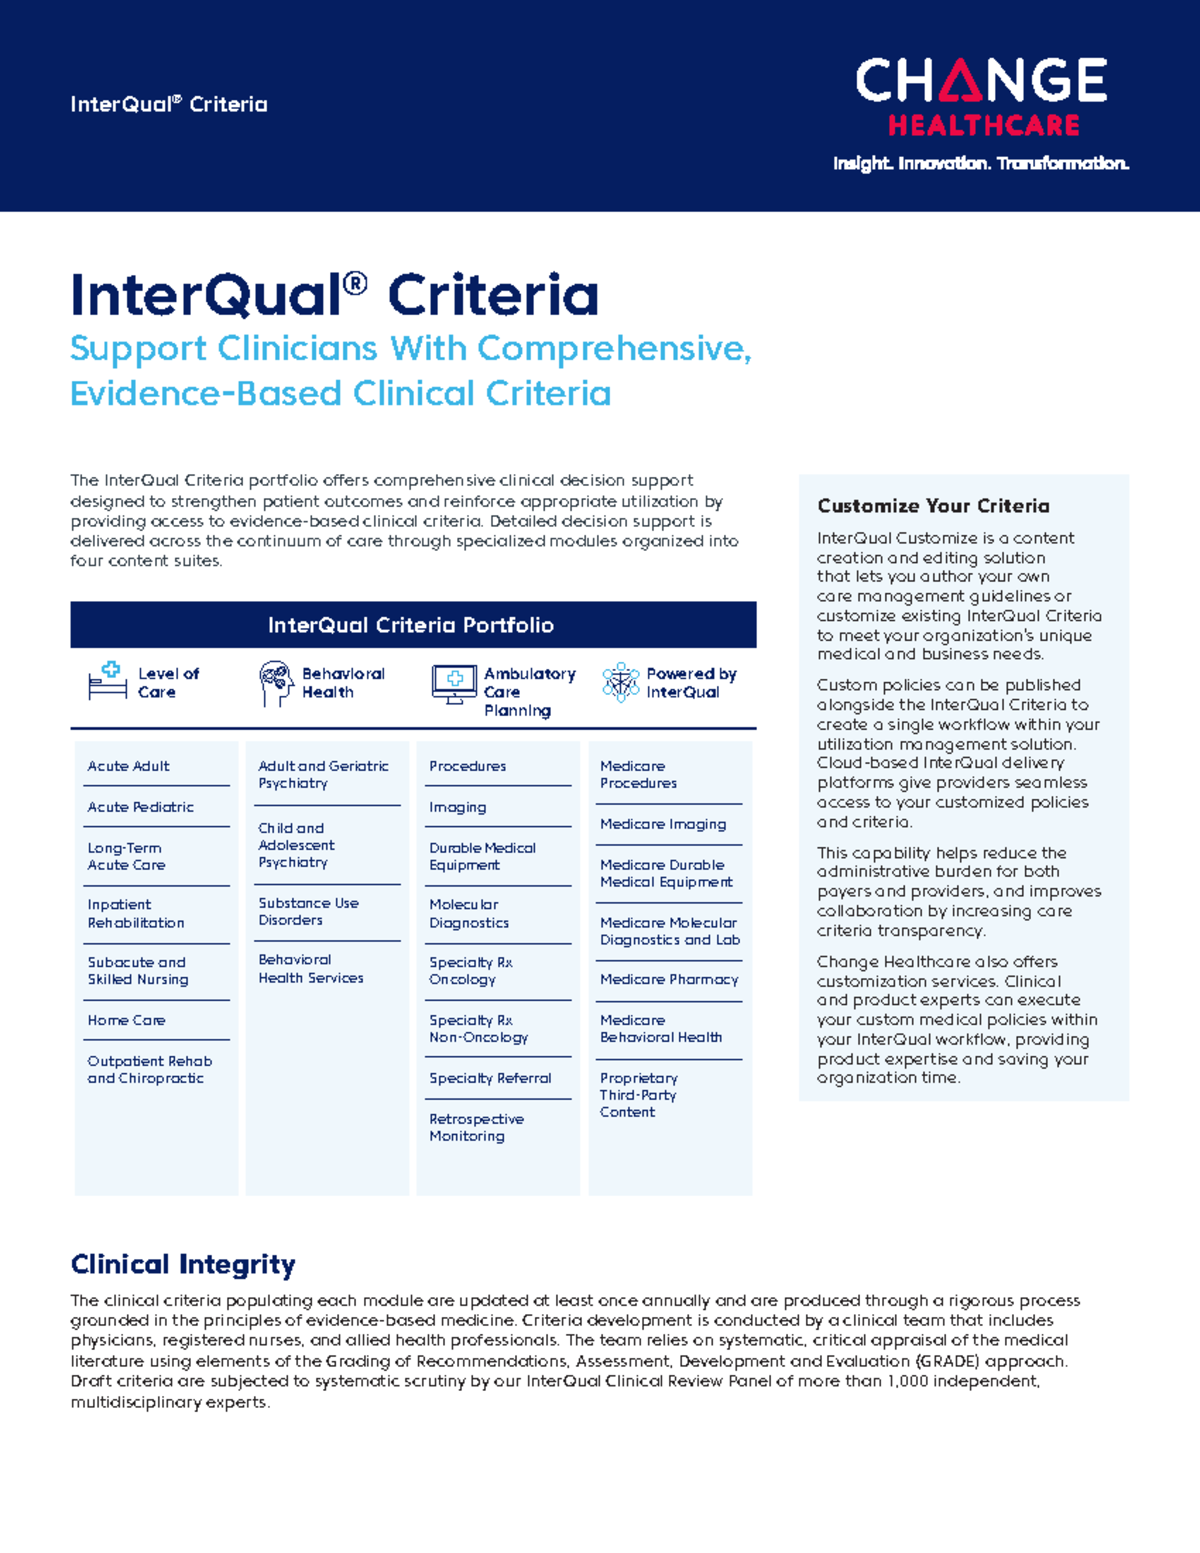
Most people encounter Interqual through their health plan or utilization management vendor. The platform itself is managed by MCG Health, and it's used extensively for prospective and concurrent authorization decisions. The guidelines cover everything from inpatient admission to imaging and prescription drugs.When you're actually using the Interqual Care Criteria Guidelines on a daily basis, the real challenge isn't understanding the criteria themselves. It's dealing with the mismatch between clinical documentation and what the system expects. I spent three years working in utilization review before moving into a different role, and the part that always caused friction was front-maturity screening criteria and how they interact with documentation gaps.
Where to Find the Interqual Care Criteria Guidelines
MCG makes the current criteria available on their website. You need a registered account, which typically requires your organization to have an active license agreement with them. The free public portal has limited content. Full criteria sets require activation of your specific product lines, whether that's hospital criteria, pharmacy criteria, or behavioral health criteria.The download process is straightforward if your account is set up correctly. Log into the MCG portal, navigate to the criteria section, and select the relevant products. For most organizations, the full annual update arrives in early January with incremental updates throughout the year. The PDF versions are searchable but not editable. If you need to reference specific criteria codes frequently, some teams export the data into their internal systems through API access, though that requires a separate integration agreement.
How the Criteria Actually Work in Real Decisions
The structure behind the criteria is consistent across product lines. Each criterion has a code, a title, a clinical description, and a set of yes-or-no questions that lead to a recommendation. The recommendation categories are usually things like "meets criteria," "does not meet criteria," or "requires additional information." The logic flows from the first screen to the final recommendation, and each branching path is built around evidence-based thresholds.Here's something most people don't realize going in: the criteria are deterministic. They don't incorporate clinical judgment outside of what's explicitly coded into the question set. If your documentation hits a question that isn't answered clearly, the system defaults to "does not meet criteria" in most cases. That default behavior is where most appeals originate. I had a case where a patient had clear clinical justification for continued inpatient stay, but the documentation team had checked the wrong box on labor and delivery criteria, which triggered an automatic denial. The fix was pulling the record, correcting the documentation snapshot, and resubmitting with the right clinical notes attached. Took about twenty minutes total.
Get the Full Details

A Specific Problem I Ran Into
Front-maturity criteria for pediatric admissions caused a lot of head-scratching. The system applies age-based logic that sometimes conflicts with specialty-specific criteria. I encountered a situation where a twelve-year-old with complex chronic conditions was being evaluated under general pediatric admission criteria instead of the appropriate specialty pathway. The result was a denial because certain clinical markers that should have satisfied the specialty criteria weren't being evaluated at all under the default front-screen.The workaround was to manually bypass the front-maturity screen by selecting the correct specialty criterion directly in the application. This isn't documented prominently in the user guide. You have to know to search for the specific criterion code rather than relying on the automatic front-screen routing. Once you do that, the right clinical questions appear and the recommendation flips to meets criteria. This usually takes about five minutes once you know the trick, but if you're new to the platform it can cost you a day or two of back-and-forth with the reviewing clinician.
Common Mistakes That Slow Everything Down
The biggest time-waster is incomplete initial documentation. Every yes-or-no question in the criterion needs a defensible answer in the clinical record. If you submit with gaps, the reviewer has to request additional information, which adds twenty to forty-five minutes to the turnaround. Some organizations use structured templates to force complete documentation before submission, and that cuts average processing time significantly.Another mistake is applying the wrong version of the criteria. MCG updates the guidelines annually, and using an outdated version can produce recommendations that are clinically reasonable but formally incorrect. I've seen denials get overturned after a version mismatch was caught during peer review. Always verify the edition date stamped on the criterion you're referencing, usually located in the footer of the PDF or at the top of the digital criterion display.
What the Criteria Don't Handle Well
Interqual criteria work best for standard utilization scenarios. They struggle with complex social determinants, atypical presentations, and cases where multiple comorbidities interact in ways the single-pathway logic can't capture. The system also doesn't account for provider-patient relationship factors or institutional capacity constraints. If your organization relies exclusively on Interqual without a peer-to-peer override process, you'll encounter situations where the recommendation is technically correct according to the criteria but clinically wrong for the individual patient.The workaround for these edge cases is the professional review exception process. Most contracts with MCG include a formal appeal pathway where a licensed clinician in the same specialty can review the case de novo. This process takes longer, typically three to five business days, but it's the safety valve that keeps the system from becoming absurd. I recommend using it early and often rather than waiting for a pattern of denials to build up.

Practical Setup Steps
If your organization is implementing Interqual for the first time, start by mapping your current authorization workflows to the relevant MCG product lines. You'll need inpatient hospital criteria, possibly outpatient criteria, and pharmacy criteria if you're handling formulary management. Coordinate with your vendor to activate the correct licenses before go-live. Then train your utilization reviewers on the criterion structure and the front-maturity bypass procedure I mentioned earlier. Budget at least two weeks for the training period because reviewers will make version and routing errors until the processes become muscle memory.Keep a running log of criteria exceptions and overrides. After three months, you'll see which criteria generate the most appeals and where your documentation team consistently misses key questions. That data is worth more than any generic training module because it tells you exactly where to focus your corrective efforts.