
So You Need to Run Inpatient Psych Through Interqual and It Keeps Getting Denied
Interqual is McGraw Hill's utilization management tool. It's what payers use to determine whether an inpatient psychiatric stay meets medical necessity. The Inpatient Psych criteria sits inside the broader MCG Health Interqual system. Most hospitals and insurances use it. If you work in utilization review, case management, or admissions, you will run into it regularly. The criteria evaluate three main things: diagnosis, severity, and risk. A patient needs a primary psychiatric diagnosis that qualifies under DSM-5 or ICD-10 codes. Then the severity dimension kicks in — things like risk of harm to self or others, inability to care for basic needs, acuity of symptoms, and the need for 24-hour nursing-level intervention. Finally, the risk assessment looks at suicide risk, homicidality, grave disability, and the likelihood of deterioration if treatment is delayed. Here is the part nobody tells you upfront. The criteria do not just check boxes. They require clinical documentation that maps directly to the criteria language. Vague notes like "patient appeared depressed" or "shows behavioral dyscontrol" will get denied every time. You need the documentation to specifically address the severity elements — documented suicidal ideation with plan and intent, recent behavior that demonstrates acute risk, failed outpatient interventions, etc.
The Documentation Problem That Nobody Warns About
I spent about six months dealing with repeated denials on a set of cases that I thought were slam-dunk inpatient psych admissions. The documentation looked solid to me. Psychiatrist wrote about SI, the patient had a recent overdose attempt two weeks prior, there was clear risk. The payer kept saying the criteria weren't met for severity. It took me looking at this from the reviewer side to figure out what was happening. The problem was that the clinical narrative didn't explicitly tie the documentation to each Interqual criterion. The psychiatrist mentioned suicide risk but didn't document the frequency, intensity, or duration of the thoughts. They noted a recent overdose but didn't connect it to current risk level. They described agitation but didn't specify that it represented a danger to self or others. The reviewer was scoring based on explicit criterion match, not on implied severity. The workaround was simple but tedious. I created a documentation template that mirrored the Interqual language point by point. Each admission note had to address: (1) specific DSM-5 diagnosis with ICD-10 code, (2) suicidal or homicidal ideation with date, frequency, plan, intent, (3) inability to perform basic activities of daily living due to psychiatric symptoms, (4) failure of lower level of care, and (5) clinical justification for why inpatient is medically necessary rather than partial hospitalization or intensive outpatient. This cut our denial rate from about 40% down to under 10% within a few months.
Common Pitfalls and Counter-Intuitive Things
One thing that catches people off guard is that a strong diagnosis alone does not guarantee approval. A patient can have a legitimate diagnosis of severe major depressive disorder and still be denied if the severity criterion isn't documented. The criteria are weighted toward functional impairment and risk, not diagnosis alone. I have seen borderline personality disorder cases get approved faster than schizophrenia cases because the BPD patients had clearer documentation of recent self-harm behavior while the schizophrenia chart only had a diagnosis and a vague "poor insight" note. Another thing: the recertification process is where most people lose cases. Initial authorization is usually straightforward because the acute event is fresh in the documentation. But at day 3 or 4 when recertification comes up, the narrative needs to show continued acute need, not just that the patient is still there. Many reviewers approve the initial stay and then deny the extension because the clinical picture shows stabilization. You need to document ongoing acute symptoms, ongoing risk, and why the patient cannot transition to a lower level of care at that point in time.
Get the Full Details
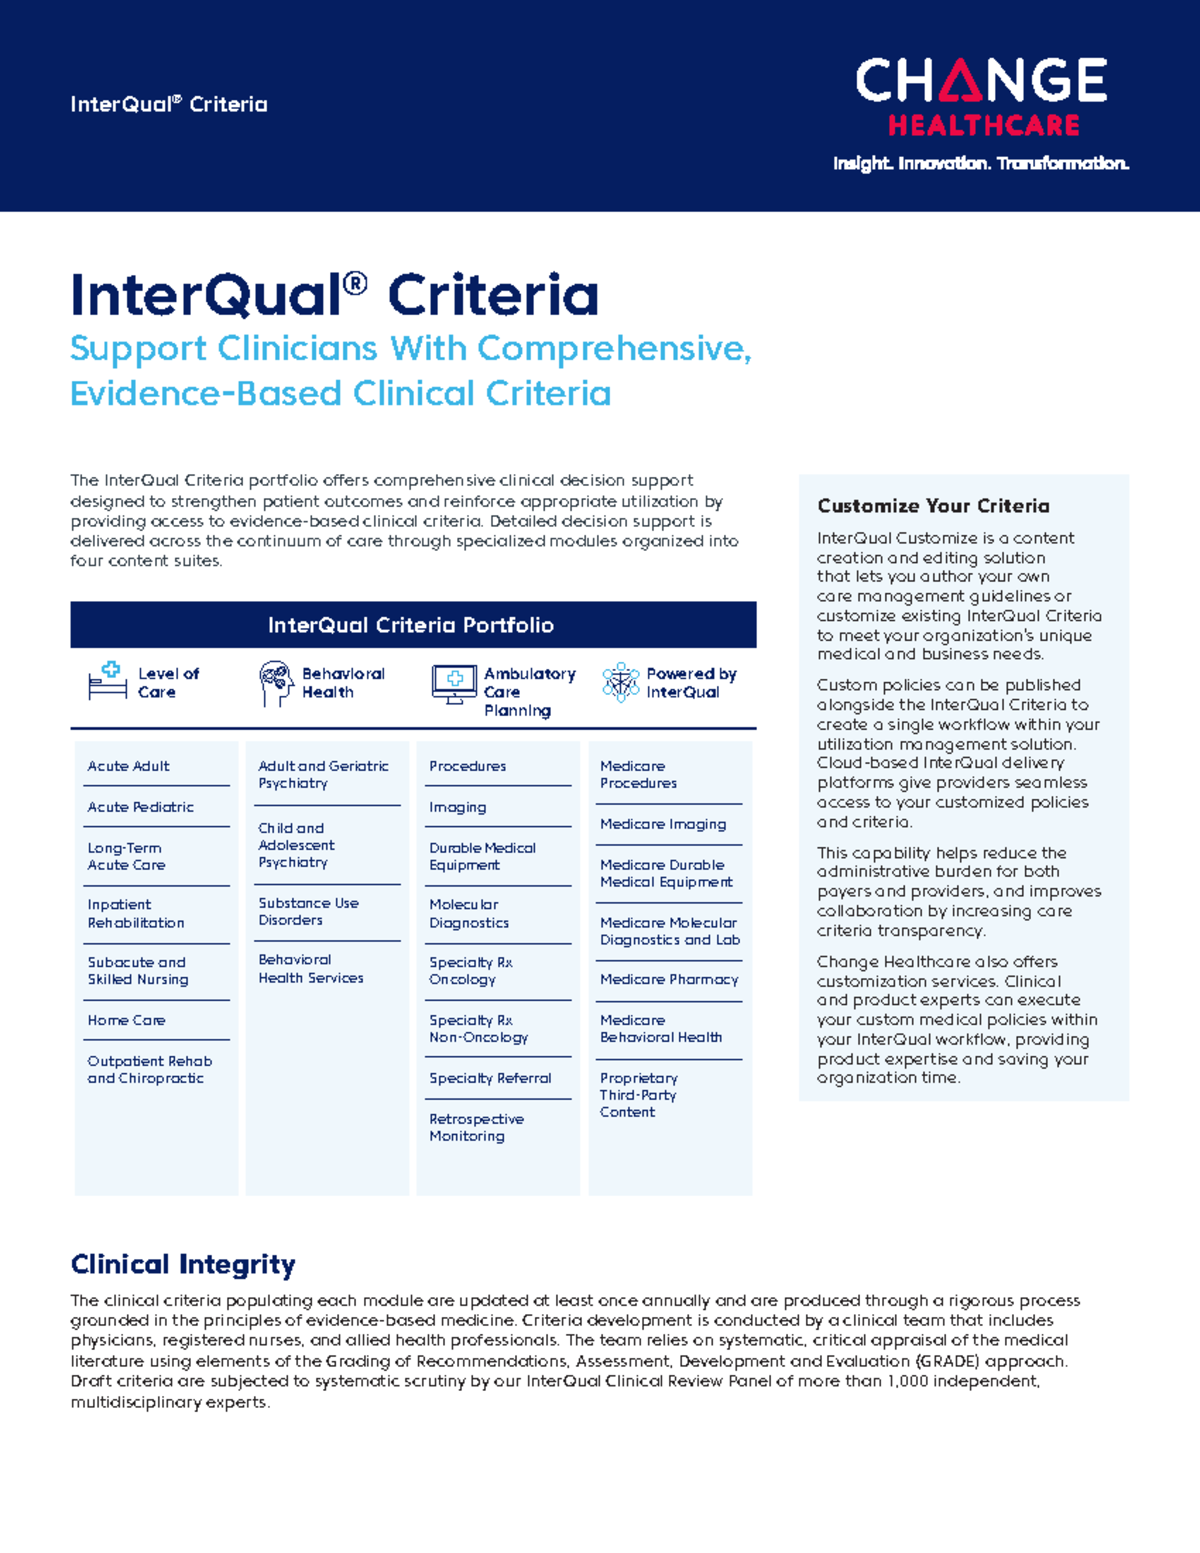
What Interqual Gets Wrong About Psychiatric Stays
The criteria were designed primarily for medical-surgical utilization management and then adapted for behavioral health. That shows. There are areas where the tool struggles with psychiatric populations specifically. Substance use co-occurring with a primary psychiatric diagnosis can create ambiguity about which criteria set applies and whether the psychiatric severity is being evaluated independently or subsumed under the substance use criteria. Another limitation is that Interqual does not account well for patients whose risk is primarily chronic rather than acute. A patient with long-standing PTSD and intermittent dissociative episodes may not meet the acute severity threshold in a single snapshot evaluation but clearly needs inpatient-level care. The tool is built for acute risk, not for complex chronic psychiatric presentations. In those cases, the appeal process becomes your primary tool, and having detailed treatment history documentation is essential.
Where to Get the Actual Criteria
The Interqual criteria are proprietary. You can access them through MCG Health directly, typically through your organization's credentialing process. If you are a hospital or insurance company, you should already have a subscription and login portal. Some states publish excerpts or summaries of the criteria they require, particularly Medicaid programs. The American College of Healthcare Association and various utilization management professional groups sometimes distribute overview documents. But the full current version requires a formal MCG account. If you are looking for the specific Inpatient Psych section, it falls under the Behavioral Health chapter of the Interqual manual. Within that, you will find the Adult Inpatient Psychiatric and the Pediatric Inpatient Psychiatric criteria sets. They are separate. Don't apply adult criteria to a pediatric case — the severity thresholds differ and reviewers will catch that mismatch.
A Few Practical Tips From Experience
Timing matters more than people realize. If you submit an Interqual review request after 3pm on a weekday, you are often looking at next-business-day turnaround. Submit early in the morning and you may get same-day results. Rush requests exist but they cost extra and they don't guarantee faster review — sometimes they just get queued ahead of regular submissions. When you are appealing a denial, reference the specific criterion number and language from the Interqual manual. Generic appeals that say "the patient is clearly psychiatrically ill" will not move a reviewer. Point to the exact criterion, quote the relevant language, and show how the clinical documentation satisfies each element. This approach works roughly two-thirds of the time on first appeal and about 80-85% when you include supporting documentation that directly addresses the reviewer's stated concerns. Also keep in mind that different payers may have modified versions of the Interqual criteria or add their own supplemental requirements. UnitedHealthcare, Aetna, and Cigna all use Interqual but some of their contracts add plan-specific overlays. Check whether your payer has additional criteria beyond the base MCG publication. I learned this the hard way when a case that was approved under standard Interqual was subsequently denied by a commercial payer that had added a requirement for documented failed attempts at outpatient crisis intervention within the prior 14 days. That requirement was not in the base criteria I was referencing.



