Why the Neonatal Interqual Criteria Keeps You Up at 2 AM
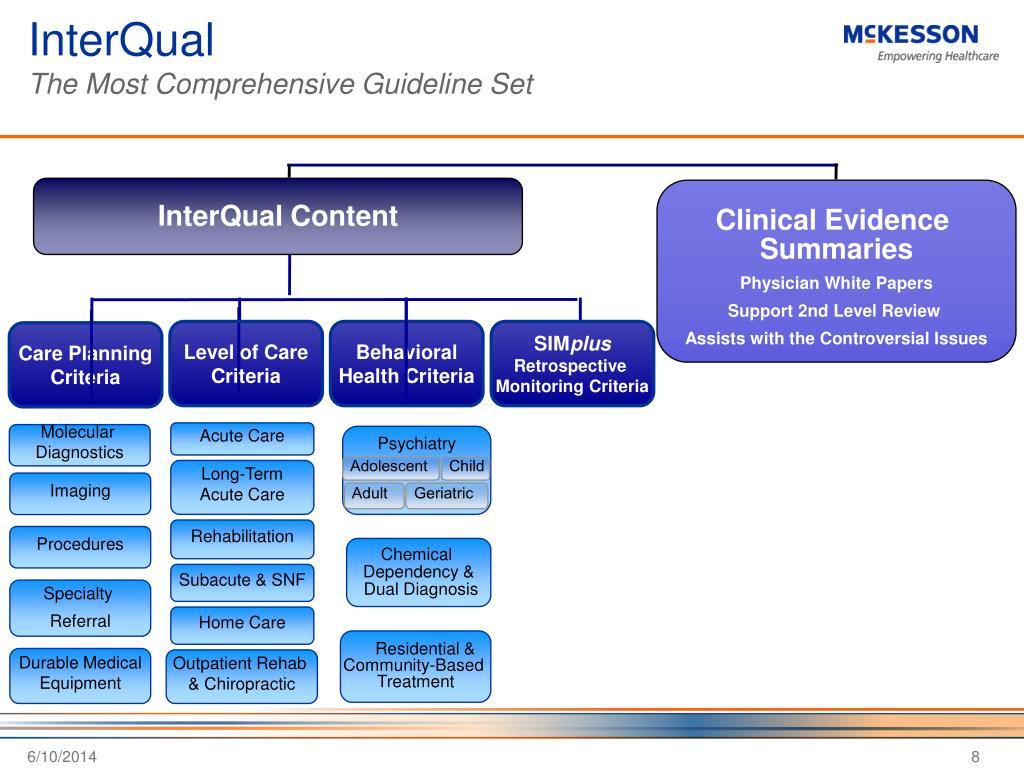
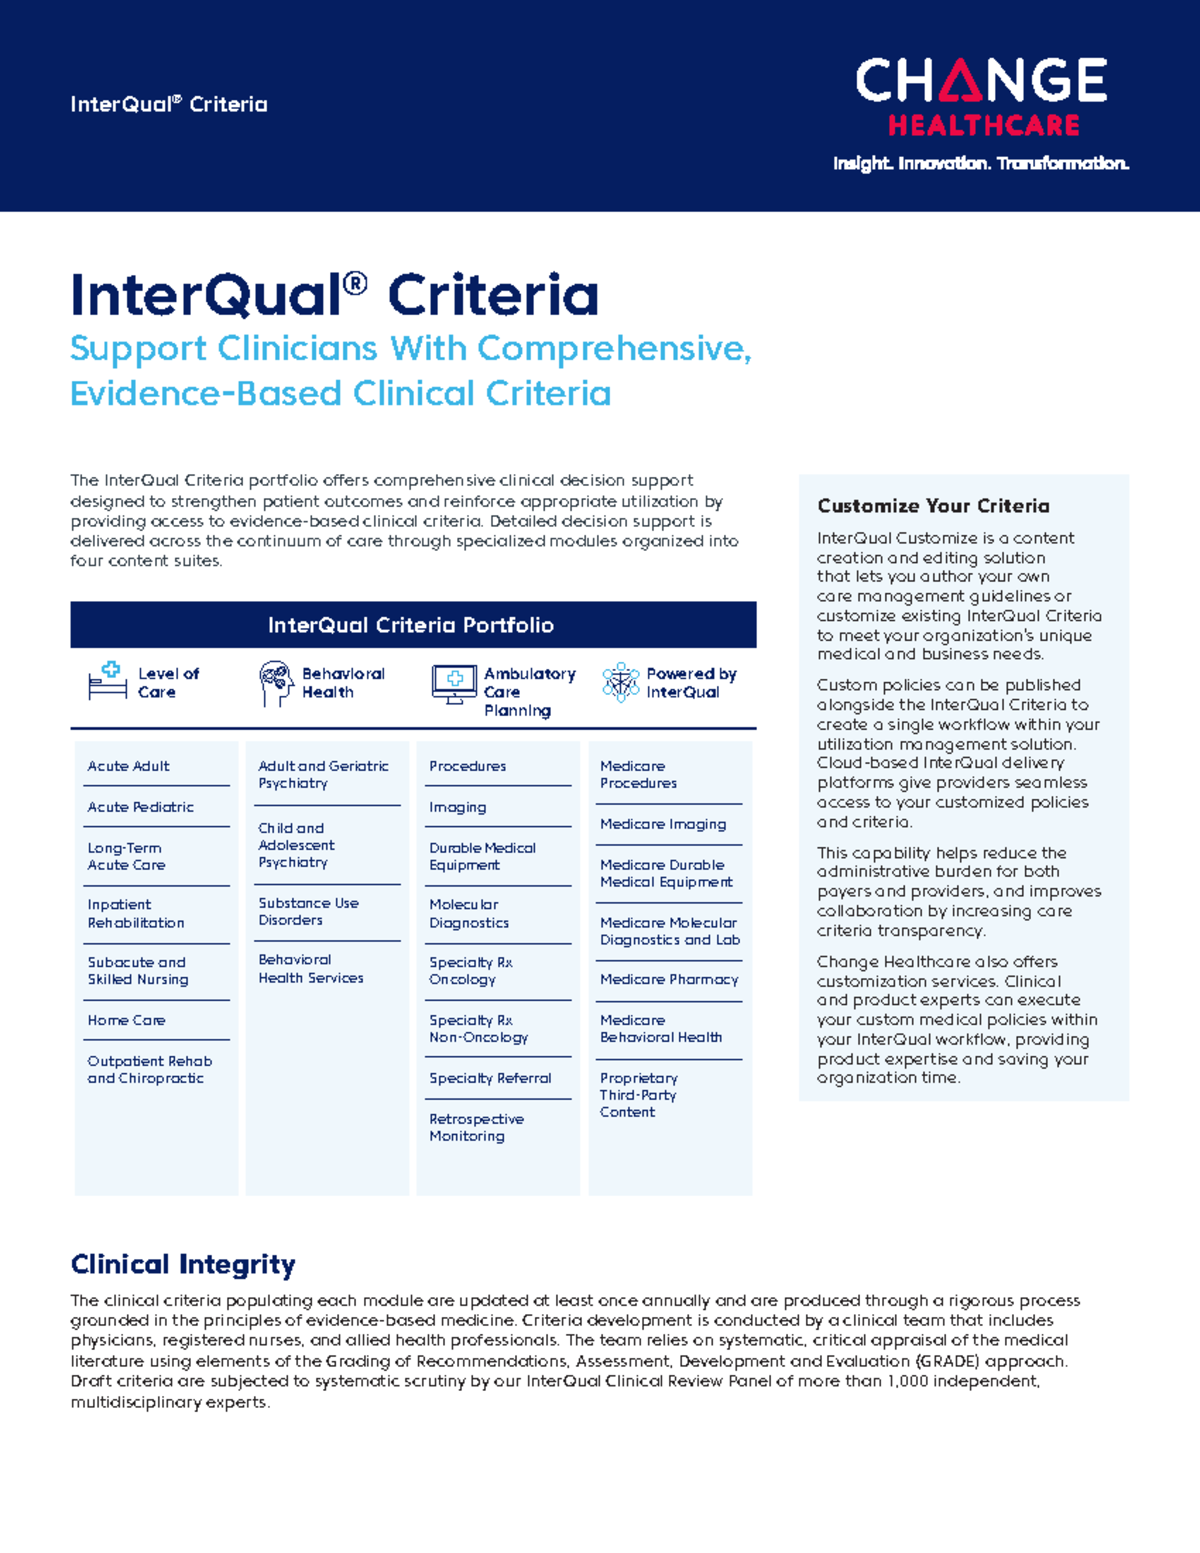
I spent three years working utilization review for a regional health system, and the neonatal portion of Interqual was always the most frustrating section to argue with. Not because the criteria themselves are poorly written — they're actually fairly precise — but because the documentation requirements don't match what clinicians are realistically able to provide in a NICU environment. You'll read an appeal denial and realize the request was turned down because someone couldn't document a weight-based calculation in a format the reviewers expect. That happens more than you'd think. The neonatal criteria under Interqual, published by Milliman Care Guidelines, cover admission and continued-stay requirements for well newborns, sick newborns, and neonatal intensive care across all three levels (NICU 1, 2, and 3). The criteria are organized by diagnosis, procedure, and severity of illness. When a payer or a hospital's utilization management department reviews a neonatal case, they're looking for specific clinical triggers that justify the intensity of care being provided. Here's the thing most people miss: the criteria don't just apply to the baby. They apply to the reason for admission and the ongoing medical necessity of the stay. A preterm infant born at 28 weeks with respiratory distress syndrome will be evaluated under one set of criteria at admission, but after day five, the continued stay criteria take over and the clinical justification needs to shift accordingly. I've seen cases where the initial authorization was granted properly, but the continued stay review failed because the attending physician never updated the documentation to reflect the current clinical picture. The baby was still in the NICU for valid reasons. The paperwork just wasn't aligned with the Interqual language.
The actual criteria document for neonates runs roughly 40 to 60 pages depending on the version and whether you're looking at the standalone neonatal section or the combined maternal-newborn criteria. You can download it directly from the Milliman website, but you'll need a subscription or a provider account to access the full text. Some health systems already have a site license through their utilization management vendor, so check with your UM department before purchasing anything. A single copy runs anywhere from $300 to $800 depending on the format and whether you need ongoing updates.
How the Criteria Actually Work in Practice
Each criterion follows a structured format. There's a header that states the clinical scenario, followed by bullet points or checkboxes that describe what qualifies for admission or continued stay at a given level of care. Some criteria are binary — the patient either meets the threshold or doesn't. Others involve clinical judgment, which is where the friction comes in. For a term infant with transient tachypnea of the newborn, the admission criteria require documentation of respiratory distress signs: tachypnea, grunting, flaring, or retractions. Oxygen requirement above a certain fraction also triggers the criterion. The continued stay criteria then evaluate whether those symptoms persist and whether the infant requires supplemental oxygen or feed intolerance management. It seems straightforward. It isn't. One common pitfall I ran into repeatedly involves the distinction between observation and inpatient admission for well newborns. The Interqual criteria for well newborn observation are narrow, and many facilities struggle to demonstrate that observation-level criteria are being met when the stay extends beyond 24 hours. The criteria technically allow for extended observation under specific conditions, but the reviewer may default to a denial if the documentation reads like a routine well-baby stay. I learned to explicitly document the medical reason for continued observation — failure to thrive, jaundice requiring phototherapy, borderline sepsis workup — rather than relying on the assumption that the clinical rationale would be obvious from the chart. It wasn't obvious to anyone on the other side of the screen.
Get the Full Details

Another edge case that tripped me up for months involved very low birth weight infants (
1500 grams) admitted under the sick newborn criteria. The Interqual criteria reference birth weight thresholds, but the exact wording around which level of NICU care qualifies under which criteria shifted between versions. In one case, an infant at 1350 grams was admitted to a level 3 NICU, but the initial review came back as denied because the criteria version the payer was using hadn't been updated to reflect the infant's weight bracket under the revised language. I had to pull the official version history from Milliman, cross-reference the applicable date of service with the correct criteria version, and resubmit with a citation. The appeal was approved on the second review. This took about four hours of work that could have been avoided if the initial authorization request had included the criteria version number from the start.
Documentation Tips That Actually Matter
The most effective approach I found was to build a documentation checklist that mirrored the Interqual criteria structure for the diagnoses my facility saw most often. Respiratory distress, prematurity, sepsis workup, hyperbilirubinemia, and congenital heart disease covered the vast majority of NICU admissions. For each, I noted the specific criterion number, the required documentation elements, and the most common denial reasons. This took about a week to put together but cut average authorization request preparation time from two hours down to roughly twenty minutes. When writing appeals, cite the exact Interqual criterion number and the edition year. Reviewers can't work with a general reference to "the neonatal criteria." They need the specific language you're invoking. Include the patient's relevant lab values, vital signs, and imaging results in the same format the criterion expects. If the criterion asks for oxygen saturation data, provide the actual numbers, not a statement that the patient is "oxygen dependent." There are limitations to this approach. Interqual criteria are designed for payer utilization management, not for clinical decision-making. They don't capture every nuance of a complex neonatal case, and there will be situations where the criteria simply don't fit — premature infants with multiple comorbidities, congenital anomalies requiring surgical intervention, or babies transferred from a lower-acuity facility. In those cases, the criteria become a bureaucratic hurdle rather than a useful framework. For those instances, I recommend supplementing the Interqual citation with a detailed peer-to-peer review request and attaching supporting literature when relevant. The criteria aren't the final word in every case, and knowing when to push past them is part of the job.
The download link for the most current Interqual criteria is on the Milliman website at milliman.com. You'll want to verify which version applies to your date of service, since the criteria are updated annually and changes between editions can affect how borderline cases are scored. The neonatal section gets revised most frequently, so don't assume the 2024 version matches 2025 requirements.