What Actually Works When Rebuilding Function After Stroke
Most stroke rehabilitation programs focus on the obvious targets: regaining the ability to walk, feed yourself, and dress. But the gap between "they can do it with help" and "they can do it alone" is where occupational therapy interventions live. This is the space where fine motor control, cognition, and environmental adaptation all collide at once. I have worked with post-stroke patients across acute, inpatient, and community settings. The interventions that actually move the needle tend to be boring, repetitive, and highly individualized. The ones people write about in journals often collapse under the weight of real-world compliance and fatigue. Let me walk through what I have found useful.
Evidence-Based Interventions For Stroke Patients Occupational Therapy
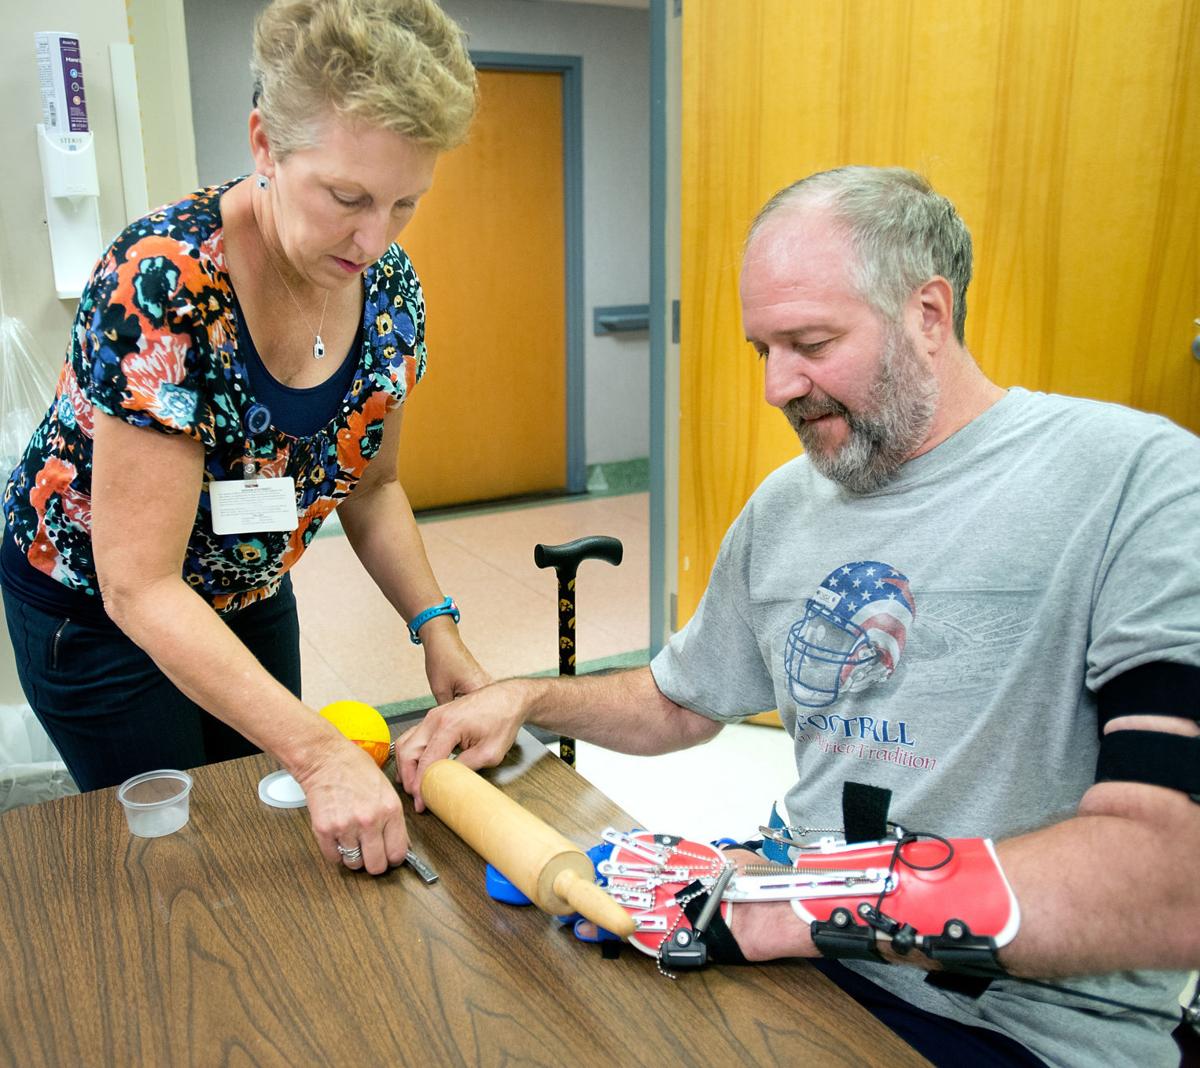
Constraint-Induced Movement Therapy, or CIMT, remains one of the more robustly studied approaches for hemiparesis after stroke. The principle is straightforward: you restrict the unaffected limb and force use of the affected arm through massed practice over two to three weeks. In my experience, it works best for patients who have some active wrist and finger extension—usually partial hand opening, not a completely flaccid extremity. When I try this with patients who have no voluntary movement in the hand, it just creates frustration and they drop out within days. The literature typically reports gains in the Fugl-Meyer Upper Extremity scale ranging from 4 to 8 points over four weeks of intensive training. That is measurable. It is not dramatic. Mirror therapy is another option worth considering, particularly for patients with severe paresis who cannot generate meaningful voluntary movement yet. The setup is simple: a mirror sits vertically between the arms so the patient sees the reflection of their unaffected hand moving while their affected hand remains hidden. The visual feedback tricks the brain into perceiving movement on the affected side. I use this primarily in the subacute phase, before I commit to more forceful active training. It is low effort, inexpensive, and patients tolerate it better than repetitive task training when their confidence is already worn thin from weeks of limited progress. The evidence base is smaller than for CIMT, but it is directionally consistent across multiple randomized trials. Task-oriented training is the backbone of most stroke OT programs. You pick a real activity—the patient wants to pour coffee, button a shirt, or carry a tray—and you break it down into trainable components. You drill each component, then reassemble them. This is standard practice, but the part most people get wrong is the selection of tasks. I have seen therapists assign generic exercises like stacking blocks or sorting pegboards because those are easy to quantify. The patient loses interest within two sessions and performance plateaus. I instead interview every patient about their specific goals before designing the intervention. A retired chef will respond to cutting vegetables. A grandmother who wants to hold her grandchild benefits from a different set of tasks entirely. The evidence supports this: goal-concordant training produces better adherence and faster functional gains than standardized exercise protocols.
Bimanual training addresses a gap that many programs ignore. Stroke survivors are frequently told to use their unaffected side to compensate, which reinforces learned non-use of the paretic limb. Bimanual therapy requires both hands to work together on asymmetrical tasks—opening a container, folding laundry, typing on a keyboard. Studies show modest improvements in bimanual coordination, and clinically, I notice it reduces the compensatory strategies that become deeply habituated after discharge.
Get the Full Details

The Problem Nobody Talks About: Cognitive Fatigue and Motor Learning
Post-stroke cognitive impairment affects roughly forty percent of survivors, and it changes how motor learning interventions perform. I ran into this problem repeatedly during inpatient rehab: a patient would demonstrate excellent performance during a morning therapy session, then fail to transfer the skill the next day or under slightly different conditions. The issue was not lack of effort. Their working memory and attentional capacity were depleted by the cognitive load of recovery itself. Standard repetitive task practice assumes the patient can sustain attention across dozens of trials. That assumption is wrong for many stroke patients. The workaround I adopted was to chunk practice into shorter blocks with embedded rest, and to reduce the cognitive demands of each trial by externalizing steps. Instead of asking a patient to remember a three-step sequence, I wrote it on a card they could reference. Instead of timed trials, I used self-paced repetition. Errorless learning techniques also helped—providing cues early enough that the patient rarely made mistakes, which reduced frustration and preserved their ability to engage in subsequent blocks. This approach trades raw volume of practice for higher quality repetitions. The total number of trials drops, but retention improves. A study by Lang et al. demonstrated that the relationship between repetition count and recovery is not linear, and that distributed practice with adequate recovery outperforms massed practice in patients with moderate cognitive involvement.
Adaptive Equipment and Environmental Modification
Not every intervention aims to restore function. Sometimes the goal is to enable independence through compensation. Adaptive equipment—weighted utensils, button hooks, reachers, one-handed kitchen tools—can restore a level of daily functioning that would otherwise require constant caregiver assistance. The trick is matching the device to the patient's residual abilities rather than prescribing off-the-shelf solutions based on assumptions. I once had a patient with right-sided neglect and mild left hemiparesis who insisted on making his own breakfast. The standard prescription would have been a plate guard and a weighted fork. What actually worked was a non-slip mat under the plate, a spring-loaded knife that required minimal grip strength, and a two-handed bowl that prevented sliding. The equipment cost under fifty dollars. The outcome was that he could feed himself independently for the first time in three weeks. Generic OT supply catalogs will never list this specific combination. It required observation of the actual task breakdown and an understanding of which barrier was most limiting. Home modification assessments are equally important. Steps, narrow doorways, unstable rugs, and poorly placed light switches create access barriers that no amount of arm strengthening will overcome. I recommend a structured home evaluation within the first two weeks of discharge planning. Documenting hazards and recommending modifications before the patient leaves the hospital prevents a cascade of secondary complications—falls, missed medications, abandoned rehabilitation routines.
Technology-Assisted Interventions
Robot-assisted therapy and virtual reality systems have entered stroke rehab with considerable funding and promising early data. The reality is mixed. Robot-assisted devices like the ArmeoSpring or InMotion provide high-repetition, guided movement patterns that are difficult to replicate manually. They are expensive, require technical support, and are not available outside major rehabilitation centers. For patients I see in community or home-based settings, these are not practical options. Virtual reality, specifically the consumer-grade systems, has been more accessible. I have used modified gaming platforms with patients for upper extremity reaching and grasping practice. The feedback is immediate, engagement is higher than with standard exercises, and the dosage can be self-paced. The limitation is that VR does not replicate the force and tactile feedback required for many ADL tasks. A patient might improve their reaching distance in a virtual environment but still struggle to pick up a heavy ceramic mug without spilling. VR should supplement, not replace, task-specific training with real objects.

What These Interventions Cannot Do
I need to be clear about the limitations. Occupational therapy interventions after stroke produce gains, but the magnitude is constrained by the severity and location of the initial injury. Large middle cerebral artery infarcts with complete hemiplegia have a fundamentally different prognosis than small lacunar strokes with mild weakness. No amount of CIMT or bimanual training will restore independent hand function if the corticospinal tract is severely damaged. Diffusion tensor imaging can predict recovery potential more accurately than clinical assessment alone, but this is not routinely available in most rehabilitation settings. Another limitation is the window of neuroplasticity. The highest recovery rates occur within the first three to six months post-stroke, but meaningful gains are still possible beyond that period. Patients and families sometimes interpret the decline in insurance-covered therapy sessions after six months as a signal that recovery has stopped. It has not. The rate of improvement slows, and the interventions need to shift from intensive remediation toward maintenance and compensation, but neuroplasticity persists. I have seen patients continue to make functional gains for up to two years post-stroke with consistent practice. A more practical bottleneck is caregiver burnout. Stroke rehabilitation requires hundreds of hours of practice spread across weeks and months. When the primary caregiver is exhausted, inconsistent, or untrained, the patient's progress stalls regardless of how well-designed the therapy program is. I address this by training family members as co-therapists and establishing home exercise programs that fit into existing routines rather than adding new obligations. A five-minute exercise session after morning coffee is more sustainable than a thirty-minute routine that competes with other responsibilities.
Putting It Together
Effective stroke rehabilitation OT does not require exotic equipment or cutting-edge technology. It requires accurate assessment of the patient's residual abilities, clear goal-setting, and intervention selection that matches the clinical picture. CIMT for patients with some voluntary movement. Mirror therapy for those with severe impairment. Task-oriented training anchored in personal goals. Bimanual work to counteract compensatory strategies. Adaptive equipment when restoration is not feasible. Cognitive accommodations when attention and memory are compromised. The interventions I described are supported by varying levels of evidence. CIMT and task-oriented training have the strongest support. Mirror therapy and bimanual training have moderate support. Technology-assisted approaches are promising but context-dependent. What ties them together is that they all require the therapist to observe the patient performing actual tasks, identify the specific barrier to independence, and design practice around that barrier rather than around a standardized protocol. If you are looking for downloadable resources to support this work, the American Occupational Therapy Association and the American Heart Association both publish clinical practice guidelines that outline intervention recommendations by stroke phase. The Stroke Recovery and Rehabilitation Network maintains a summary of evidence graded by intervention type. These documents are freely available and more current than most textbooks.
The work itself is less glamorous than the research suggests, but it is consequential. A patient who can feed themselves independently regains something fundamental that no metric captures fully. That is what this intervention field is actually about.