Placing electrodes isn't as simple as the diagram makes it look
I still remember the first time I did this properly. A patient with a left bundle branch block and a prior inferior MI. The machine auto-interpreted it as acute ischemia. I had to sit there for twenty minutes tracing through every lead by hand before realizing the R waves were actually normal and the ST depressions were reciprocal changes, not primary injury. That's the thing nobody tells you about a 12 lead Ecg — the algorithm is helpful but it will absolutely lie to you if you let it. A 12-lead ECG records electrical activity from twelve different angles around the heart. Six are limb leads: Lead I, II, III, aVR, aVL, and aVF. Six are precordial leads: V1 through V6. Each one tells you something different about cardiac depolarization and repolarization. Lead II is usually the best rhythm lead because the P waves point upward and are easiest to identify. That's why most monitors default to showing it in the bottom row.
Introduction To 12 Lead Ecg
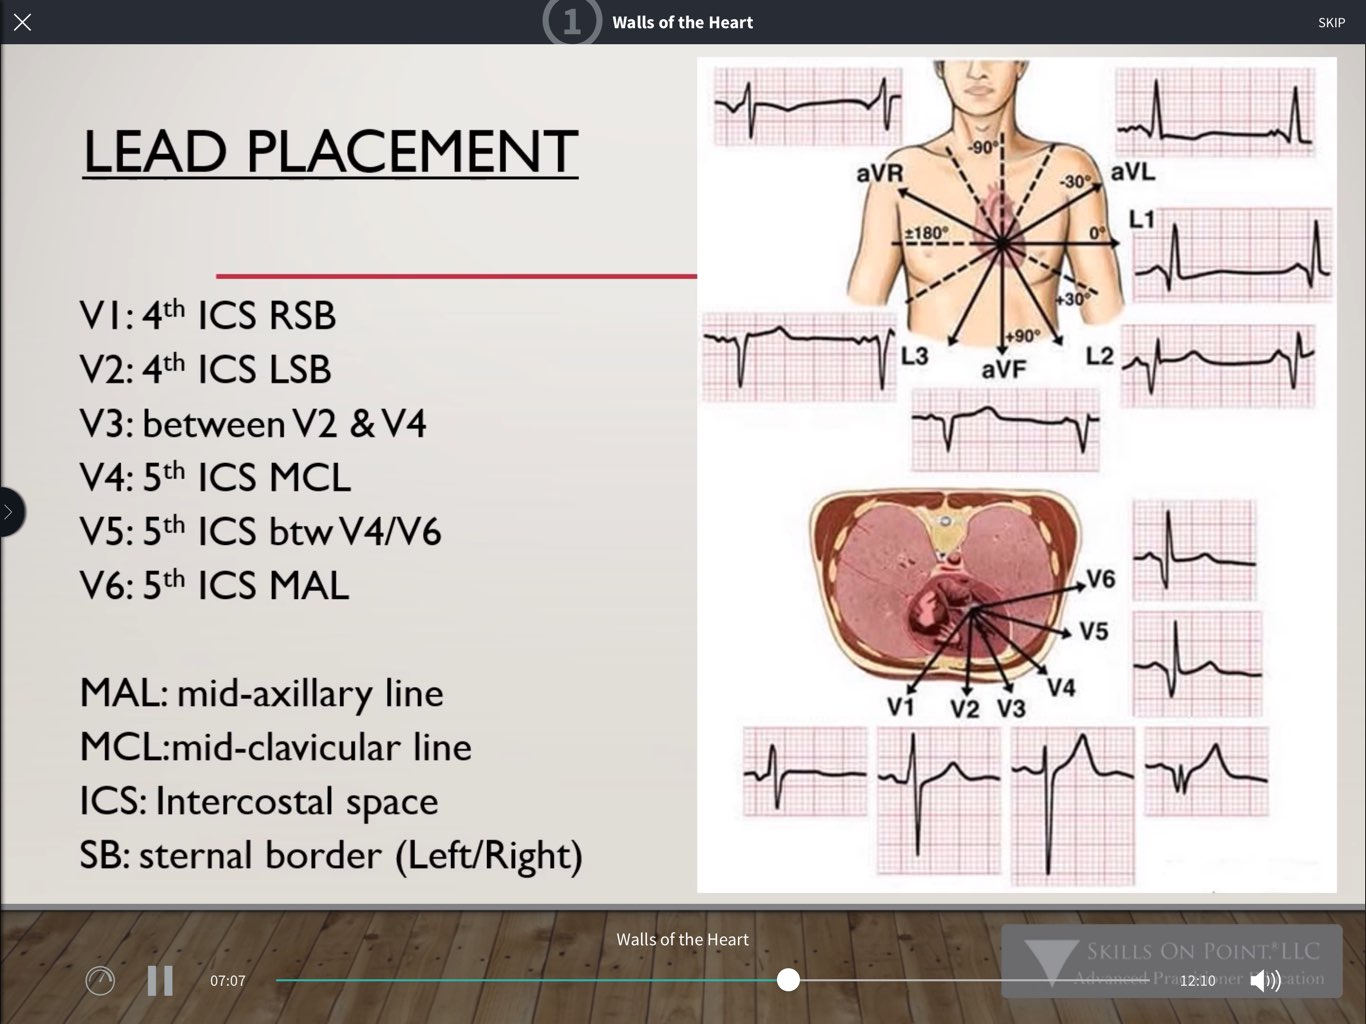
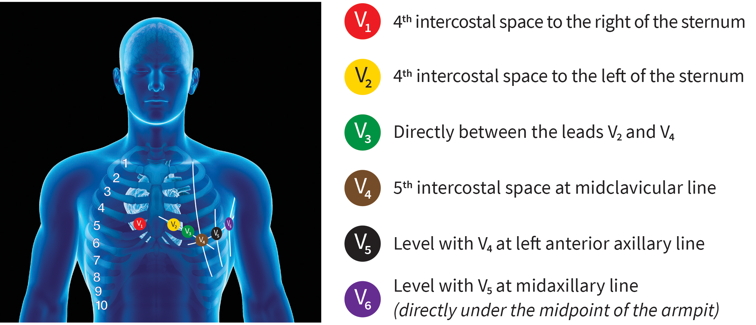
The actual process takes about three to five minutes on a cooperative adult patient. Place the four limb electrodes first — right arm, left arm, right leg, left leg. Then place the six chest leads in their anatomical positions. V1 goes in the fourth intercostal space at the right sternal border. V2 at the same space on the left. V4 at the fifth intercostal space midclavicular line. V3 sits between V2 and V4. V5 at the same horizontal level as V4 on the anterior axillary line. V6 at the midaxillary line. Most people mess up the precordial placements. They put V4 too high or too low and then wonder why the R wave progression looks weird. Or they place V1 in the fourth space when the patient has a barrel chest and it should be the third or fourth — hard to tell intercostal spaces through thick breast tissue. I've seen it constantly. The workaround is to mark the sternum with your finger and count down from the angle of Louis, which is the second rib landmark. It takes another ten seconds and prevents about half the placement errors I see in practice. There is a practical nuance most beginners miss. The standard 12-lead ECG only gives you a frontal and horizontal plane view. It completely misses the posterior and right ventricular walls unless you add extra leads. Posterior MI shows up as pure ST depression in V1 through V3 with tall R waves. Without a posterior lead placement (V7, V8, V9), you miss it entirely. Right ventricular infarction presents with ST elevation in V4R — you need to place an electrode on the right side of the chest at the same level as V4. This comes up in about 30 to 40 percent of inferior STEMIs. If you don't check for it, you give the patient fluids cautiously when they actually need aggressive fluid resuscitation, and that can be the difference between life and death.
Another thing that trips people up is lead reversal. If you swap the right and left arm electrodes, Lead I gets inverted, aVR becomes positive, and Leads II and III flip their morphologies. The computer will produce garbage interpretation. I had a case where the ECG showed what looked like massive lateral ischemia. I spent five minutes convinced the patient was crashing until I noticed the P wave axis was completely wrong for the clinical picture. Swapped the arm leads and the whole thing normalized. Just one of those moments where you question your entire understanding of cardiology for about thirty seconds. Speed matters in emergencies. A well-practiced technician can do a full 12-lead in under two minutes. On an agitated or intubated patient, it takes longer. I've done them on trauma patients with bilateral chest tubes and multiple other lines competing for space. You prioritize the chest lead placement and skip the unnecessary limb electrodes if the tracing quality is already adequate. A quick and dirty ECG with noisy baseline is worse than a slow and clean one, so don't rush the skin prep. Shave hair, abrade slightly if the skin is calloused, and use enough gel. Good contact resistance is below five kilo-ohms. Anything higher and you're picking up artifact that mimics arrhythmias. Here's the blunt truth about limitations: the 12-lead ECG has poor sensitivity for non-ST-elevation myocardial infarction in the early stages. Up to 50 percent of NSTEMIs can present with a completely normal or near-normal initial ECG. It also misses about 25 percent of acute aortic dissections because the ECG can look deceptively normal or show only nonspecific ST-T changes. And in obesity, COPD, or dextrocardia, lead placement changes significantly and the standard interpretations don't apply. Dextrocardia is one you should know about — mirror image leads go on the right side, and V1 through V6 are placed in the same positions on the right chest. If you don't spot it, the machine reads everything backwards and flags pseudo-infarction patterns.
Get the Full Details
For learning purposes, I'd recommend starting with normal sinus rhythm strips and working outward. Memorize the lead groups and what each territorial artery supplies. Leads II, III, aVF = inferior wall = right coronary artery or left circumflex. Leads I, aVL, V5, V6 = lateral wall = left circumflex or diagonal branch. Leads V1 through V4 = anterior wall = left anterior descending. When you learn to think in territories rather than individual leads, interpretation becomes much faster. There are free ECG libraries online that I find useful. The MIT-BIH Arrhythmia Database has over 48 hours of annotated recordings. The PTB Diagnostic ECG Database includes 290 subjects with various pathologies. Both are free for academic use. You can download them and practice reading without any cost. I spent my first six months going through those archives every evening after work. By month seven, I could spot most arrhythmias without thinking about it. The machine-generated interpretation should never be the final word. Algorithms miss things. They overcall anterior MI on early repolarization variants. They flag hypertrophy when the patient is young and thin. They call acute injury on baseline wander that looks like ST depression. Your eyes and your clinical context always matter more than what the printer spits out. Read the ECG yourself first, then check the machine's opinion. If they disagree, trust your reading — or get a second set of eyes on it.