What Bronchoscopy Actually Looks Like in Practice
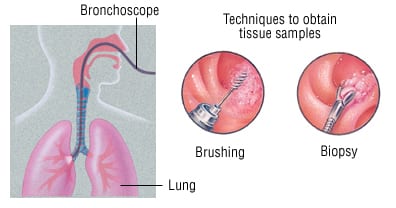
Most medical students encounter bronchoscopy as a chapter in a textbook before they ever see the procedure on a real patient. The gap between reading about it and doing it is enormous. Cambridge Medicine's Introduction To Bronchoscopy Cambridge Medicine series fills some of that gap, but it is not a substitute for hands-on training. It is a structured starting point. You need to treat it as one.I remember sitting in a respiratory ward in 2014, watching a registrar perform a flexible bronchoscopy on a patient with a suspected endobronchial lesion. The monitor feed was grainy, the nurse was calling out oxygen saturations, and the registrar had to navigate past a tongue that kept hitting the side of the scope. That is the reality. Textbook diagrams show perfect airway anatomy. Real patients do not cooperate. The Cambridge Medicine framework breaks bronchoscopy into phases: indication, preparation, consent, topical anaesthesia, instrumentation, the procedure itself, and post-procedure monitoring. Each phase has defined decision points. The value of the material is that it forces you to think through the sequence before you touch equipment. Most junior doctors I have worked with skip straight to the technique and ignore the consent discussion. That is where things go wrong. Consent for bronchoscopy is not a checkbox. Patients need to understand that the scope goes down the throat, that they will be awake, and that there is a small risk of bleeding, infection, pneumothorax, and arrhythmia. The incidence of clinically significant complications sits around one to two percent for diagnostic bronchoscopy, but that number jumps when you add interventions like biopsy or bronchial artery embolisation planning. I had a patient develop significant haemoptysis after a transbronchial lung biopsy. She was on ticagrelor for a cardiac stent placed three months earlier. We had held the medication for five days, but the platelet dysfunction from ticagrelor does not fully reverse in that window. We packed the airway with cold saline and adrenaline, called interventional pulmonology, and stabilized her. She recovered. It took six hours of monitoring. This is the sort of case the Cambridge framework mentions in passing, but it does not teach you the visceral pressure of managing it at 2 AM.
Preparation Steps You Cannot Skip
Check coagulation profile. INR should be under 1.5 for biopsy. Platelets above 80, ideally above 100 if you plan forceps work. Review imaging. I once went in blind on a CT because the report was not yet digitised and the film room was closed. The lesion was a 12 mm nodule in the right upper lobe posterior segment. I spent forty minutes searching. I felt foolish. Always review the CT yourself before you introduce the scope. NPO status matters. Six hours for solid food, two hours for clear fluids. Not negotiable if you want a clean field and reduced aspiration risk. Obtain IV access. Monitor ECG and pulse oximetry. Have suction ready before you enter the room. This sounds basic. It is not optional.
Topical Anaesthesia and Sedation
Topical anaesthesia typically involves lidocaine, 4 percent via nebuliser or 2 percent via spray. Total dose should stay under 400 mg in a standard adult. I use atomisers for the oropharynx, then deliberate slow instillation down the vocal cords as the patient breathes out. The cough reflex is your guide. If the patient cannot tolerate the scope at the glottis, you have not anaesthetised adequately. Adding more lidocaine at that point causes more problems than it solves. Sedation is usually a combined approach. Midazolam in small incremental doses, often 1 to 2 mg total, paired with fentanyl 25 to 50 mcg. Titrate to effect. The goal is mild sedation, not general anaesthesia. You want the patient cooperative and comfortable, breathing spontaneously. Deep sedation increases the risk of hypoventilation and desaturation, especially in COPD patients. I lost count of how many times I have seen oxygen saturation drop to 82 percent in a morbidly obese patient with severe emphysema because someone pushed too much midazolam. Pull back. Give less. Wait longer between doses.
Get the Full Details

Navigation and Technique
The sequence is straightforward in theory. Nose or mouth, pharynx, larynx, trachea, main bronchi, segmental branches. The reality depends on anatomy. A deviated septum changes the entry route. A goitre narrows the pharynx. An unrecognised stricture can stop the scope dead. I encountered a patient with a benign tracheal stricture from prior intubation that was not visible on the pre-procedure CT because the beam was too wide. The scope tip hit a wall at 6 cm past the cords. I backed out, switched to a thinner pediatric scope, and completed the exam. That is not in any protocol. It is just what you do when the standard approach fails. When you reach the carina, go right into the right main bronchus first. It is more direct. Then sweep the left. Systematic sampling beats random wandering every time. If you are doing bronchoalveolar lavage, use 20 to 30 ml of sterile saline per segment. Instill slowly. Aspirate immediately. Repeat three to four times per site. Yield improves with gentle massage of the chest wall between lavages. Do not flush more than 60 ml total in a single lobe. Fluid overload in the alveolar space causes transient hypoxia and can trigger bronchospasm.
Common Pitfalls
Vasovagal responses happen more often than people admit. Bradycardia, hypotension, sometimes syncope. Atropine 0.5 mg IV is the rescue. Have it drawn up before you start if the patient has a history of fainting. Laryngospasm is less common but more dangerous. Stop the stimulus immediately. Positive pressure with 100 percent oxygen. If it persists, small dose succinylcholine 0.5 mg/kg IV. This is why you need someone trained in airway management present during every bronchoscopy, even a routine diagnostic one. Pneumothorax after transbronchial biopsy occurs in roughly one to two percent of cases. Risk is higher with copd, male sex, and multiple biopsy sites. Post-procedure chest X-ray is standard. I once discharged a patient with a small apical pneumothorax that was not visible on the immediate film. He presented four hours later with pleuritic chest pain. A repeat film confirmed it. Watch the patient for at least two hours after the procedure. Discharge earlier than that is rarely worth the risk.
What the Material Does Not Cover Well
The Cambridge resources are excellent for structure and indication selection. They are less helpful for managing unexpected anatomy, dealing with anxious patients who refuse to cooperate, or handling complications that arise during the procedure. No online module can teach that. You learn that from doing it, from making mistakes, from being watched by someone who has made the same mistakes. I also find the coverage of EBUS (endobronchial ultrasound) somewhat thin in the introductory material. EBUS has become a standard part of diagnostic bronchoscopy for mediastinal staging and peripheral nodule evaluation. If you are training in a UK centre, you will encounter EBUS early. The Cambridge introduction gives you the foundation, but you need additional focused training on ultrasound probe handling, needle passes, and rapid on-site cytology interpretation. Nothing replaces performing thirty to fifty procedures under supervision before you feel competent.

Practical Advice for Beginners
Practice on manikins first. Not because it translates perfectly, but because it builds hand-eye coordination without a living patient at risk. Get comfortable with the scope controls before you touch a real airway. Watch recordings of experienced bronchoscopists. Note how slowly they move. Rushing causes trauma and reduces diagnostic yield. Learn to read the scope screen in three dimensions. The image is two-dimensional on a monitor, but the airway is a branching three-dimensional tree. Spend time correlating what you see on the scope with the CT reconstruction. I keep a lateral and coronal CT in my mind's eye when I advance the scope. It saves time and improves navigation accuracy. Documentation matters. Record what you saw, what you sampled, and any complications. Use standard anatomical terminology. Right upper lobe anterior segment. B5. Not "some part of the right lung." Future clinicians will read your report. Make it useful.
Know your limits. If you are struggling, stop. Ask for help. A prolonged difficult bronchoscopy benefits no one. Transfer to a more experienced colleague. I once spent twenty-five minutes trying to intubate a segmental branch in a patient with severe kyphoscoliosis. The oxygen saturation was dropping. I aborted, sedated the patient, and referred to a senior fellow the next day. We completed the procedure in twelve minutes. Admitting you are out of your depth is a skill, not a failure. The Cambridge Medicine introduction gives you a solid framework. Use it. Read it carefully. Take notes. Then get into the suite and watch as many procedures as possible. The rest comes from repetition, reflection, and the occasional scare that keeps you sharp.