What Medical Practice Management Actually Looks Like
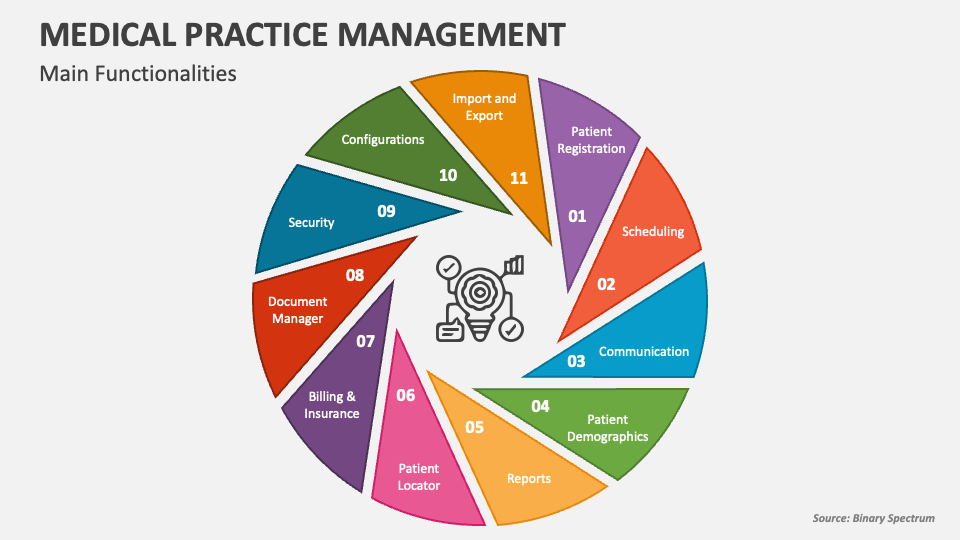
Most people think medical practice management is just billing software with a nicer name. It isn't. It's the entire operational backbone of a clinic — scheduling, billing, compliance, staffing, patient flow, and the constant negotiation between what the law requires and what your budget allows. I ran a small multi-provider practice for eight years before moving into consulting, and the first thing I learned was that nothing breaks faster than a practice that treats management as an afterthought. If you're starting out, the actual introduction isn't a textbook chapter. It's the moment you realize your front desk is spending forty minutes a day on hold with payers, your clinicians are seeing patients three hours behind schedule, and you have no idea where your revenue is leaking. That's when you actually start learning practice management. Everything else is theory. The core components are straightforward in description and brutal in execution. Scheduling isn't just putting patients in slots. It's managing no-shows, provider availability, room turnover time, and the fact that Dr. Patel always runs fifteen minutes late because she stays to chart. Revenue cycle management covers everything from registration through final payment, and the gap between submission and collection is where most small practices bleed out. Compliance touches HIPAA, OSHA, state licensing, and payer-specific rules that change every year. Staffing determines whether any of this actually gets done. Technology is the tool that either enables or obstructs it all.
I remember one specific issue that took us six weeks to resolve. We were transitioning from paper charts to an EHR and our coding team was using ICD-10 codes that were technically valid but didn't match the clinical documentation our physicians were writing. Claims were being denied at a 34% rate. The problem wasn't the software. It was that nobody had mapped the documentation templates to the coding requirements before go-live. The fix was simple in hindsight but expensive in practice. I pulled a certified coding specialist in on contract, spent two days auditing our top twenty procedures by volume, rebuilt the documentation templates to align with payer-specific requirements, and ran a parallel testing period for three weeks before fully switching. Denial rate dropped to under four percent within the next billing cycle.
How to Build a Functional Management Framework
Start with your revenue cycle and work backward. Most people begin with scheduling or EHR selection, which is backwards. If your billing isn't clean, fancy scheduling does nothing for your bottom line. Map out every step from patient intake to final payment. Identify where claims get rejected, where denials pile up, and which payer contracts are underperforming. Do this with actual data, not estimates. Pull your last six months of claim denial reports and group them by denial reason. You'll usually find that thirty percent of denials come from the same five causes. Next, look at staffing ratios. A typical small practice needs one front desk person per eight active providers, one medical assistant per four providers, and one billing specialist per twelve providers. These are rough baselines. Your actual numbers depend on complexity — a dermatology practice handles more prior authorizations than a general follow-up clinic. Understaffing shows up first as patient wait times and second as staff turnover. Both are costly. Technology selection should come third. Here's a counter-intuitive point that beginners consistently miss: the most popular practice management systems aren't always the best fit for smaller practices. Large platforms like Epic or AthenaHealth have massive ecosystems, but their implementation costs can range from fifty thousand to two hundred thousand dollars for a small practice, and they require dedicated IT support. For a practice with fewer than ten providers, a mid-tier platform like AdvancedMD or Kareo often delivers better ROI because the features match your actual volume rather than the volume of a hospital system.
Get the Full Details

Another thing nobody tells you about practice management software: customization is a trap. Every vendor will offer custom workflows, custom reporting dashboards, custom integrations. Most of these features create more problems than they solve. Custom report builds break during updates. Custom integrations fail when APIs change. Stick to configurable out-of-the-box settings wherever possible. You can usually achieve ninety percent of what you need without a single line of custom code.
Compliance and the Things That Will Get You in Trouble
HIPAA compliance isn't a checklist you complete once a year. It's an operational state. I've seen practices get hit with fines ranging from fifty thousand to two million dollars because someone forwarded a patient file to a personal email account, or because a receptionist left a clipboard of check-in sheets on a lobby counter overnight. The violations are almost never sophisticated. They're lazy. The most common compliance failure I encounter is inadequate business associate agreements. If you use a billing company, a cloud storage provider, a transcription service, or even a practice management vendor that stores data offsite, you need a signed BAA on file. I audited a practice that had been running for twelve years without BAAs with three of their vendors. They were fined forty-seven thousand dollars. The entire fix cost us about three days of work and some legal review. Payer compliance is another minefield. Each major insurer has its own prior authorization requirements, coding guidelines, and documentation standards. Medicare changed its telehealth reimbursement rules multiple times between 2020 and 2023 alone. If you're not tracking these changes, you're billing incorrectly and exposing yourself to audits. Set up a quarterly compliance review at minimum. Track denial reasons by payer, monitor your clean claim rate, and update your procedures when rules change.
Practical Metrics That Actually Matter
Forget vanity metrics like total patient volume. Track these instead. Days in accounts receivable should be under forty-five for a well-run practice. Anything above sixty means you have a cash flow problem. Clean claim rate should be above ninety-five percent. If it's below ninety, you're leaving money on the table. Collection rate — the percentage of allowed charges you actually collect — should be above ninety-three percent. Patient no-show rate above ten percent is a revenue leak that scheduling tweaks can usually fix. Staff-to-patient ratio is harder to optimize but directly affects both satisfaction scores and burnout rates. Here's where most practice management guides fail: they tell you what to track but not how to act on the data. I recommend a simple weekly review cadence. Monday morning, pull the prior week's AR days, denial rate, and top denial reasons. Wednesday, check scheduling fill rates and no-show percentage. Friday, review patient satisfaction scores and any compliance flags. Twenty minutes each day, ten minutes total. This creates pattern recognition. You'll start seeing trends before they become problems instead of after they become emergencies.

When Practice Management Systems Fail You
I need to be blunt about something most vendors won't tell you. Practice management software cannot fix a broken process. If your registration staff is entering incorrect patient demographics, the software will process incorrect demographics faster and more efficiently. If your clinicians aren't documenting adequately, the software will generate denials more rapidly. Technology amplifies whatever system you already have. It doesn't replace fundamentals. There's also a hard limit to automation in medical practice management. Prior authorizations, especially for specialty medications and procedures, still require human intervention in most cases. Payer portals change their interfaces without notice. Phone trees rotate through multiple menus. No software can fully automate this. You need staff who understand the exceptions, who know when to escalate, and who can document the conversation for appeal purposes. I've seen practices try to fully automate prior auth and lose more revenue in denied claims than they saved in labor costs within six months. If your practice is small enough that full practice management software feels overwhelming, you can start with modular tools. A dedicated scheduling platform like Solutionreach or PatientPop paired with a simpler billing service like RopesCorp or MGMA-certified billers can handle the core operations while you build internally. The tradeoff is data silos — your scheduling and billing won't talk to each other seamlessly — but the initial complexity barrier is much lower.
A Few More Things I Learned the Hard Way
Your patient population determines more about your management needs than you might expect. A geriatric practice needs different no-show mitigation strategies than a pediatric practice. Geriatric patients miss appointments at higher rates, but they also tend to keep them if you call them twice. Pediatric practices deal with different scheduling constraints entirely — school absences, parental work schedules, acute illness patterns. Design your management approach around your actual population, not the default settings in your software. Staff training is the single highest-ROI activity in practice management, but it's also the most neglected. I've watched practices spend tens of thousands on software they barely use because they never trained their staff on the features. Budget at least forty hours of training per new employee and twenty hours of continuing education per existing employee per year. Cover billing basics, EHR navigation, patient communication protocols, and compliance updates. The cost is negligible compared to the revenue recovered from proper system utilization. Finally, accept that practice management is never finished. Payer rules change. Staff turns over. Technology updates. Patient expectations shift. The practices that survive aren't the ones with perfect systems. They're the ones that review their metrics regularly, adjust processes without sentimentality, and invest in their people. Everything else is noise.