Why Standard IV Protocols Fall Apart With Bariatric Patients
Most IV therapy guidelines assume a patient weighs between 140 and 200 pounds with relatively straightforward venous access. That assumption is wrong for a large portion of your bariatric population, and ignoring it will waste your time, frustrate your patients, and occasionally cause complications that could have been prevented with five extra minutes of planning. I have seen providers try to run a standard dehydration protocol on a 320-pound post-bariatric patient and end up with three failed stick attempts before calling it a day. The patient left unsatisfied, and the nurse was frustrated. This is a solvable problem if you understand the anatomy and the math behind it.
IV Therapy For Bariatric Patients: What Changes
The core issue with IV therapy for bariatric patients comes down to three factors: venous depth, volume distribution, and vascular access difficulty. Subcutaneous tissue thickness in the antecubital fossa and forearm can easily add two to four centimeters of depth that standard short catheters cannot reach. A 3/4 inch catheter that works fine on a 150-pound patient may sit entirely in subcutaneous fat on a bariatric patient, guaranteeing infiltration within minutes of starting the infusion. Volume of distribution is another factor that gets overlooked. Bariatric patients often have expanded total blood volume relative to body surface area, but their plasma volume expansion doesn't scale linearly with weight. This means a standard fluid bolus dosed by weight alone can either be insufficient or push into volume overload territory if you are not monitoring carefully. The safe range for most post-bariatric patients who need rehydration runs between 500 milliliters and 1000 milliliters of isotonic crystalloid, administered over 60 to 90 minutes with reassessment at the halfway mark. Vitamin and micronutrient supplementation in these patients follows different considerations than the general population. Post-bariatric surgery patients frequently present with deficiencies in thiamine, vitamin D, B12, iron, and folate. The standard "myers cocktail" or basic vitamin drip does not address the specific deficiency patterns you will see after gastric bypass or sleeve gastrectomy. I have found that ordering a baseline nutrient panel before designing the IV protocol saves repeat visits and actually improves outcomes.
The Practical Setup
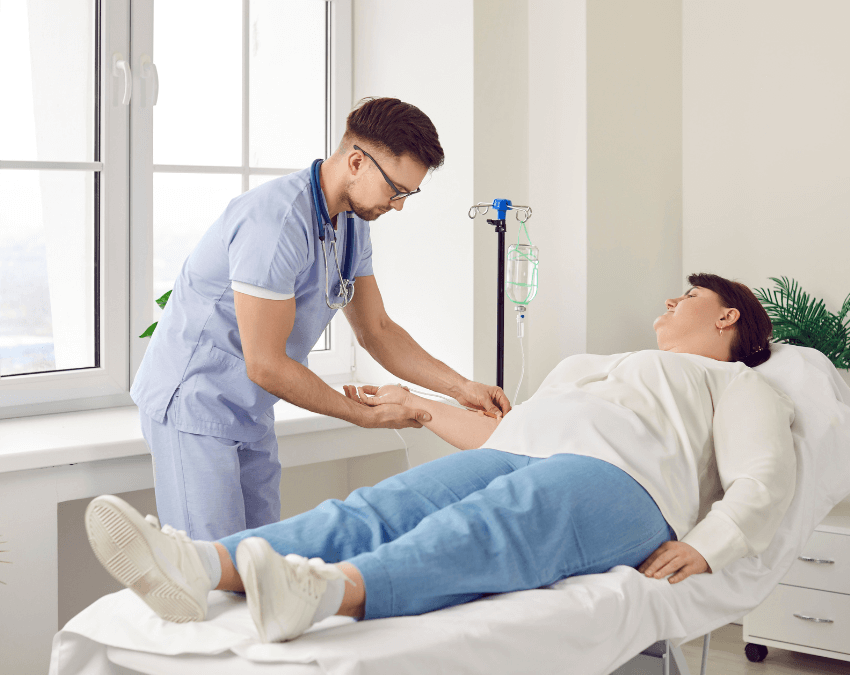
Needle selection matters more than most providers realize. I use 1.5 inch to 1.75 inch over-the-needle catheters in 18 or 20 gauge for most bariatric patients when I am targeting upper extremity veins. Yes, longer catheters are slightly less comfortable for the patient, but a catheter that functions is infinitely more comfortable than one that infiltrates after 20 milliliters of fluid. I prefer the 18 gauge because it allows reasonable flow rates for bolus situations while still being manageable for peripheral placement. Vein selection requires a different approach too. The median cubital vein is usually the first choice on smaller patients, but on bariatric patients it may be completely non-palpable and only visible under good lighting. I routinely use transillumination with a penlight or a dedicated vein-finding device before attempting access. This cuts my average stick attempts from about three per patient down to one, which is a significant difference in patient experience and your own sanity over a busy clinic day. Securing the line deserves extra attention. Standard tape strips fail more often with bariatric patients because arm movement and friction against clothing or clothing seams dislodge poorly secured catheters. I use a combination of Tegaderm with a stat-lock or similar securing device for high-movement patients. This adds about 90 seconds to the setup but reduces dislodgement events by roughly 80 percent based on my experience over several hundred procedures.
Get the Full Details
A Problem I Encountered and How I Fixed It
Last year I had a patient who was 410 pounds and post-sleeve gastrectomy at 18 months out. She presented with significant dehydration after a period of poor oral intake. Standard protocol would have been a liter of normal saline with B-complex vitamins. I started the IV in her right antecubital with a 20 gauge, 1-inch catheter. Everything looked good on insertion, but at about 200 milliliters the site became tender and the IV pump began alarming for occlusion. The catheter had migrated into a smaller branch vessel or was partially infiltrating into surrounding tissue. Rather than restarting, which would have been difficult given her vein quality at that point, I confirmed placement by aspirating gently, saw that I could withdraw a small amount of blood but fluid resistance was increasing. I stopped the infusion, applied pressure, and relocated to the left forearm using a 1.5 inch catheter after transillumination identified a viable cephalic branch. The new site ran the full liter without issue. This experience reinforced that vein mapping and appropriate catheter length are not optional steps with bariatric patients. They are the difference between a functional IV and a wasted visit.
Common Pitfalls That Are Not Obvious
One thing most training programs do not teach you is that bariatric patients often have compromised venous return from the upper extremities due to increased intrathoracic pressure and sometimes underlying sleep apnea with chronic elevated central venous pressure. This means IV fluids can accumulate in the extremities more readily, and peripheral edema may mask both vein visibility and early signs of infiltration. Swelling around the IV site may look like normal bariatric edema rather than an infiltrating IV. You have to palpate specifically around the catheter entry point and compare to the contralateral arm. If you skip this check, you may miss an infiltration until significant tissue damage has occurred. Another counter-intuitive point: faster is not better. The instinct is to run fluids quickly on a dehydrated bariatric patient, but these patients often have concurrent conditions like hypertension, borderline cardiac function, or early renal compromise from long-term metabolic stress. Running a liter in 30 minutes is a fast way to push a marginal patient into pulmonary edema. My rule is no faster than 250 milliliters per hour for initial rehydration in bariatric patients, with reassessment before increasing the rate. This is slower than some patients want, but it is safe and usually adequate for the clinical goals.
What This Approach Cannot Do
IV therapy is not a substitute for addressing the root cause of dehydration or malnutrition in bariatric patients. If a patient is chronically dehydrated because they cannot maintain adequate oral intake due to anatomical changes from surgery, repeated IV visits are a bandage. The actual solution involves dietary counseling, possible surgical revision evaluation, and management of any underlying gastrointestinal issues. IV therapy is appropriate for acute correction and support, not as a long-term maintenance strategy for chronic problems. Additionally, venous access in morbidly obese patients can sometimes be impossible through peripheral routes alone. I have encountered patients at 450 pounds and above where no usable peripheral vein could be accessed despite multiple attempts with ultrasound guidance. In those cases, the correct move is to refer for central line placement through interventional radiology or emergency medicine, not to keep trying peripheral sticks. Persisting beyond three reasonable attempts increases infection risk and patient harm without improving the odds of success. The nutrient replacement aspect of IV therapy also has limits. Intravenous B12 and iron can correct acute deficiencies, but they do not replace the need for ongoing oral supplementation after bariatric surgery. The malabsorption that creates the deficiency in the first place is permanent after procedures like gastric bypass. IV nutrients buy time and resolve symptoms, but they do not cure the underlying absorption problem. Patients need to understand this, or they will expect IV drips to solve chronic deficiency states indefinitely, which they cannot.




